Handson Innovation Opportunities and Challenges Srijoy Mahapatra MD








- Slides: 41
Hands-on Innovation: Opportunities and Challenges Srijoy Mahapatra, MD MBA Chief Strategy Officer, M Health Fairview Assistant Dean of Clinical Innovation, University of Minnesota Minneapolis MN A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services
Disclosures • Abbott Labs, Former Employee, Shareholder • Abbott Labs Sponsored this session & provided some data • Share holder K 2 A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services
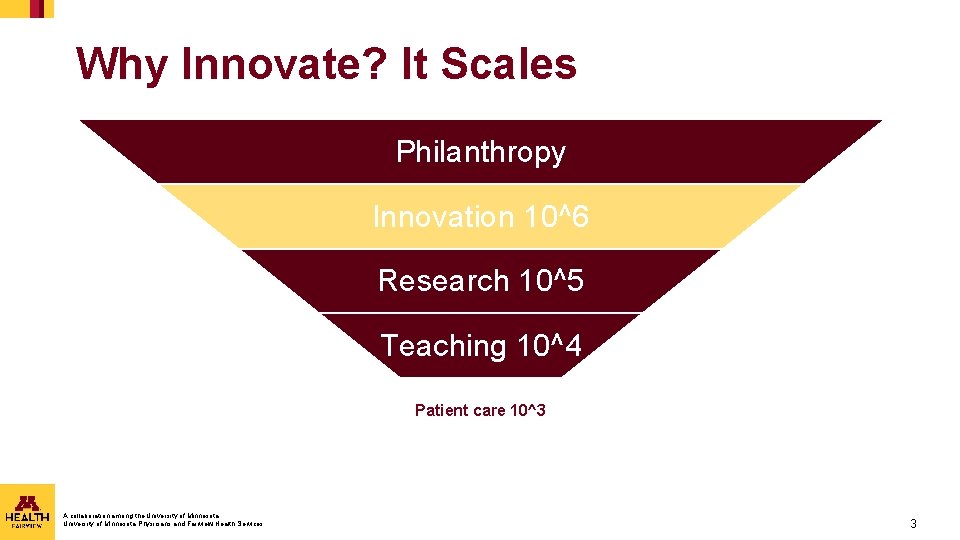
Why Innovate? It Scales Philanthropy Innovation 10^6 Research 10^5 Teaching 10^4 Patient care 10^3 A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services 3
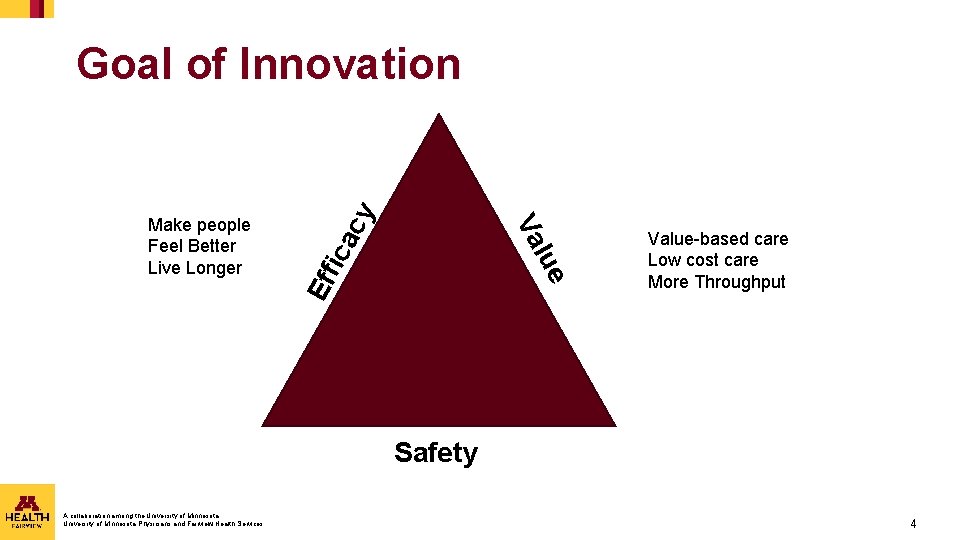
lue Eff ica Va Make people Feel Better Live Longer cy Goal of Innovation Value-based care Low cost care More Throughput Safety A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services 4
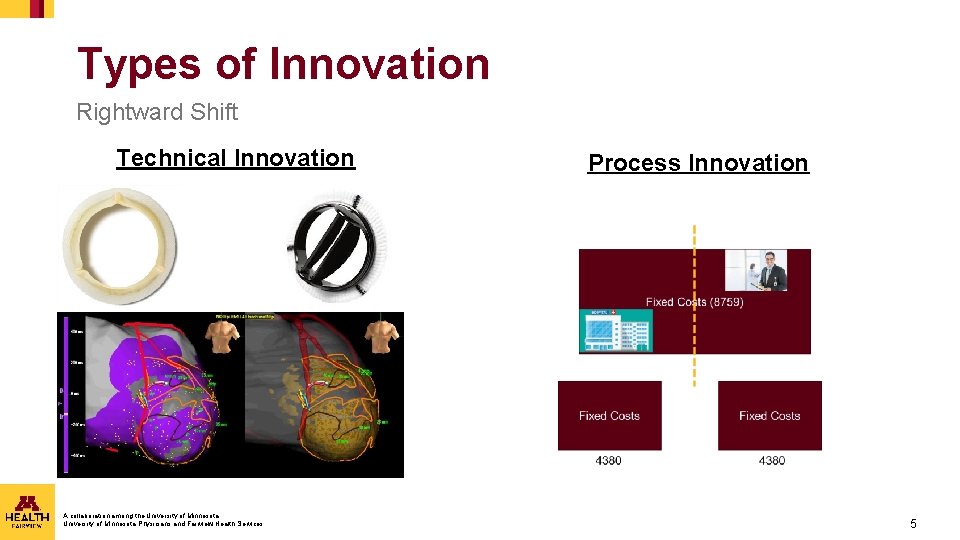
Types of Innovation Rightward Shift Technical Innovation A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services Process Innovation 5
Technical Innovation Traditional Advantages Weaknesses • Leverage Engineering • Slow • Patents • Acquisition is later • Startups A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services 6
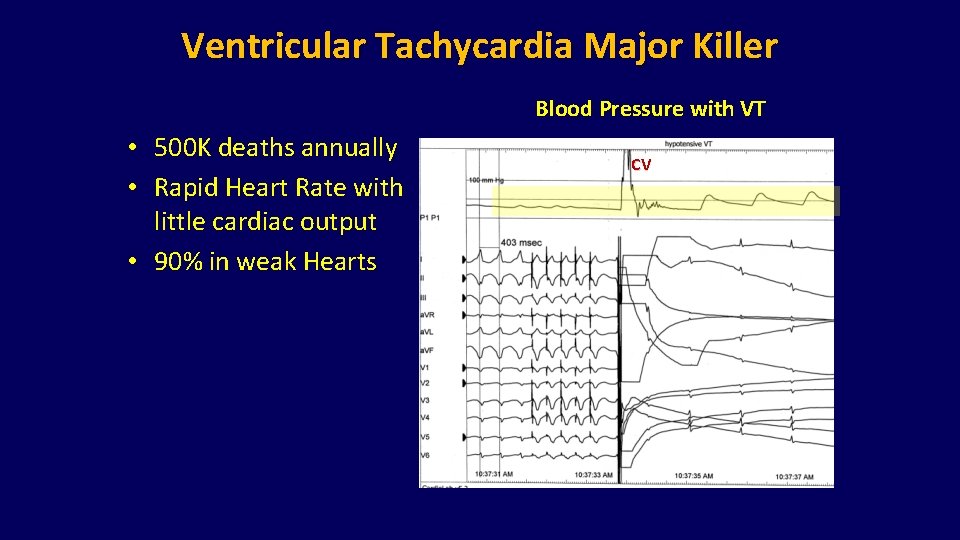
Ventricular Tachycardia Major Killer Blood Pressure with VT • 500 K deaths annually • Rapid Heart Rate with little cardiac output • 90% in weak Hearts CV
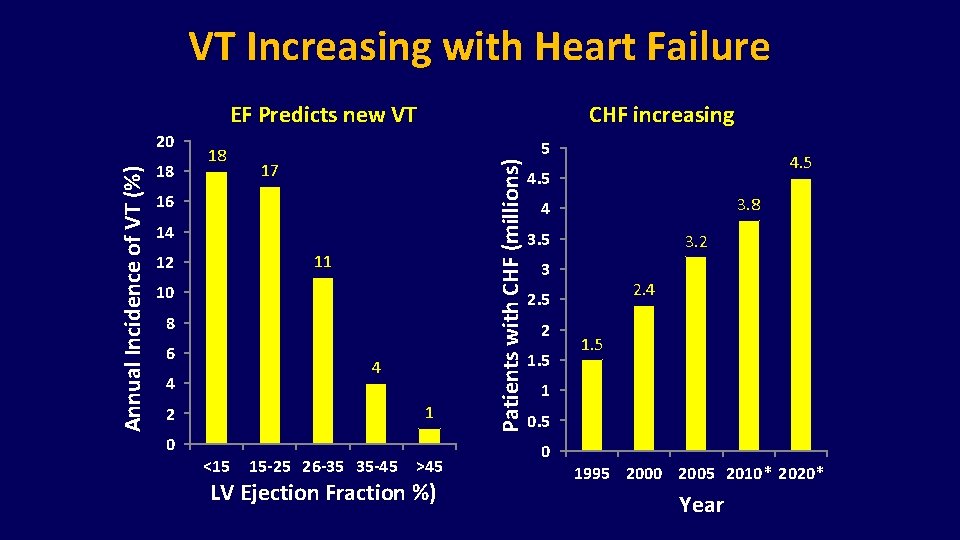
VT Increasing with Heart Failure CHF increasing Annual Incidence of VT (%) 20 18 18 17 16 14 11 12 10 8 6 4 4 1 2 0 <15 15 -25 26 -35 35 -45 >45 LV Ejection Fraction %) Patients with CHF (millions) EF Predicts new VT 5 4. 5 3. 8 4 3. 5 3. 2 3 2. 4 2. 5 2 1. 5 1 0. 5 0 1995 2000 2005 2010* 2020* Year
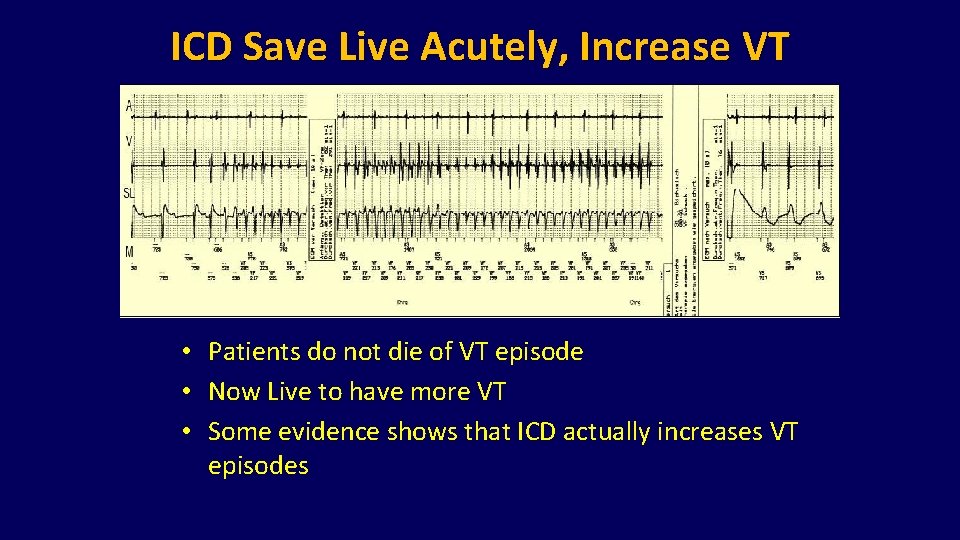
ICD Save Live Acutely, Increase VT • Patients do not die of VT episode • Now Live to have more VT • Some evidence shows that ICD actually increases VT episodes
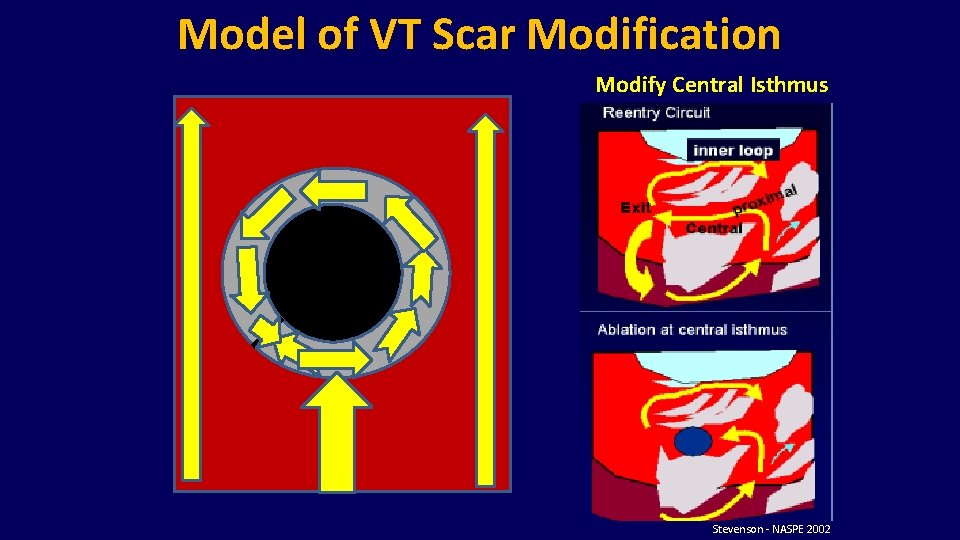
Model of VT Scar Modification Modify Central Isthmus Stevenson - NASPE 2002
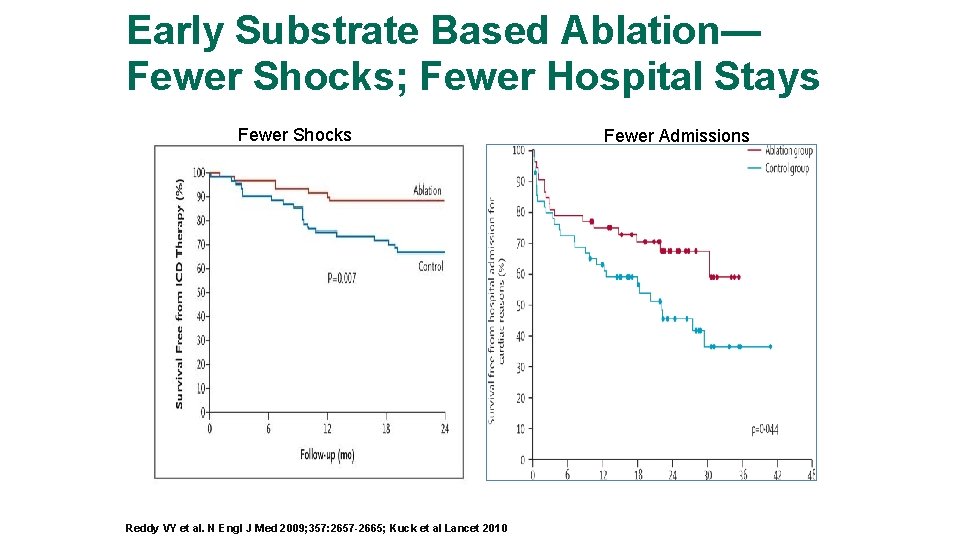
Early Substrate Based Ablation— Fewer Shocks; Fewer Hospital Stays Fewer Shocks Reddy VY et al. N Engl J Med 2009; 357: 2657 -2665; Kuck et al Lancet 2010 Fewer Admissions
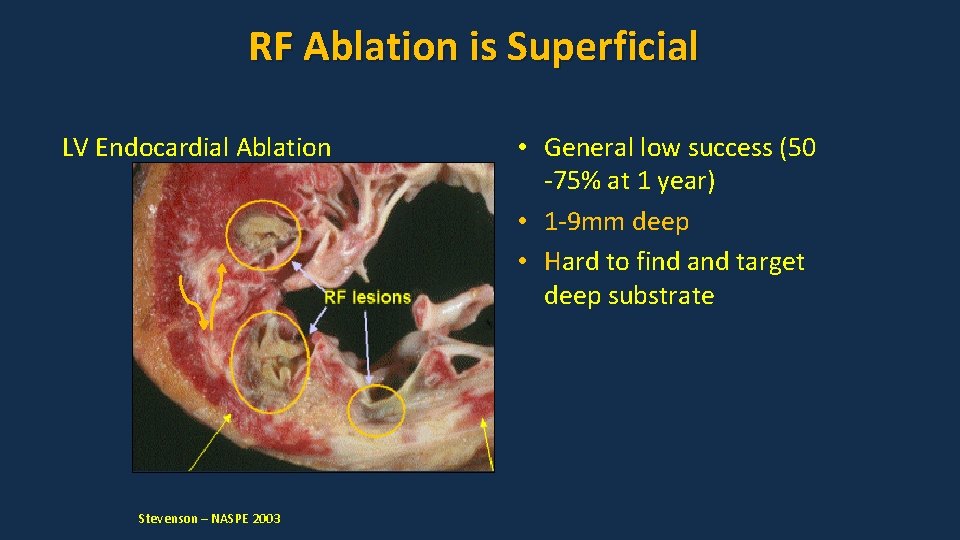
RF Ablation is Superficial LV Endocardial Ablation Stevenson – NASPE 2003 • General low success (50 -75% at 1 year) • 1 -9 mm deep • Hard to find and target deep substrate
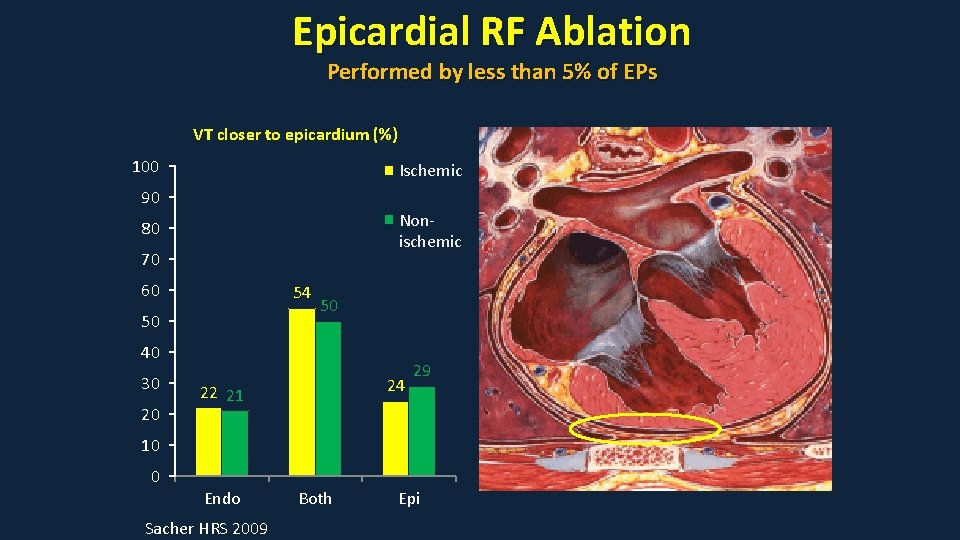
Epicardial RF Ablation Performed by less than 5% of EPs VT closer to epicardium (%) 100 Ischemic 90 Nonischemic 80 70 60 54 50 50 40 30 20 24 22 21 29 10 0 Endo Sacher HRS 2009 Both Epi
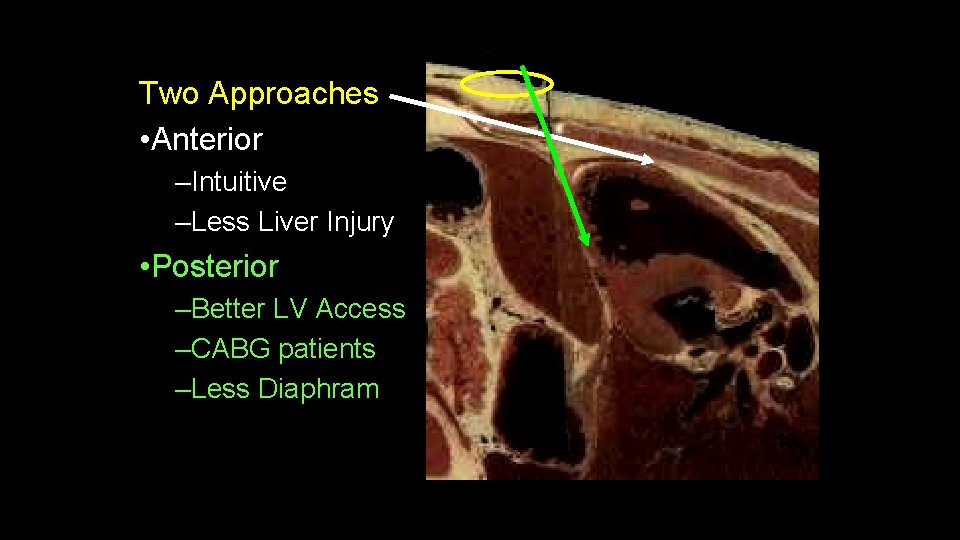
Two Approaches • Anterior –Intuitive –Less Liver Injury • Posterior –Better LV Access –CABG patients –Less Diaphram
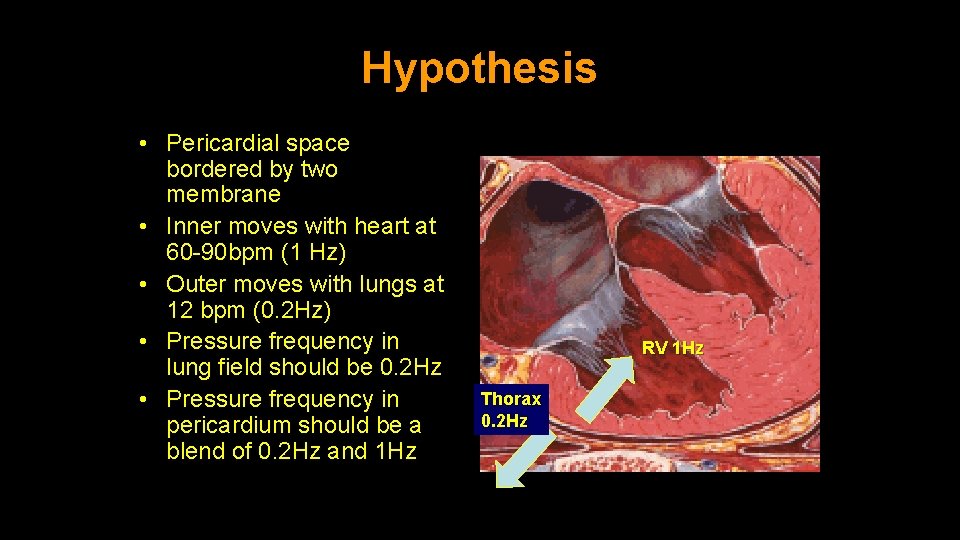
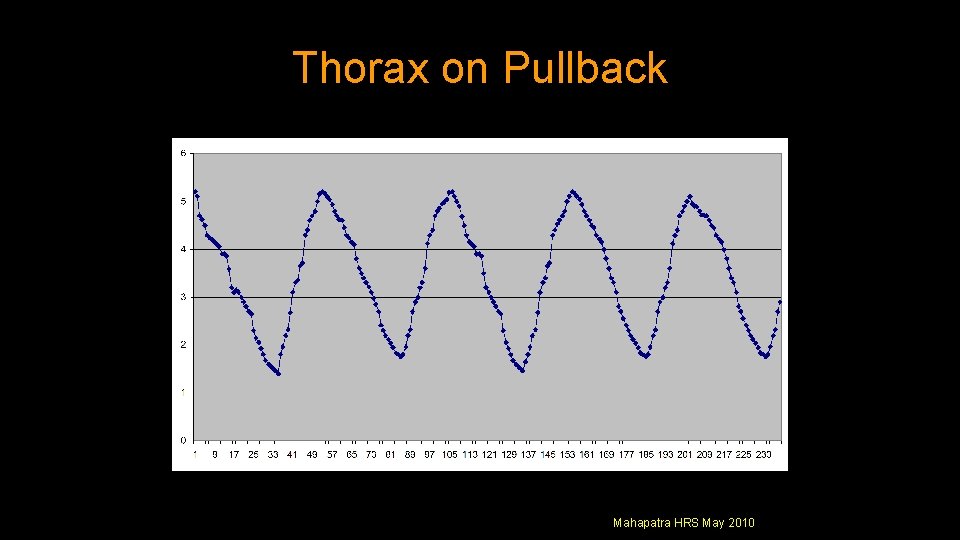
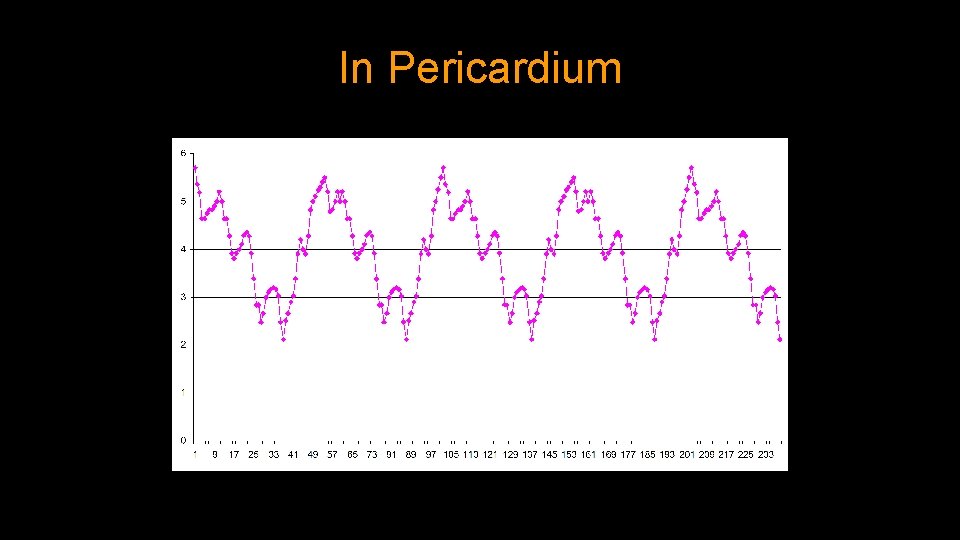
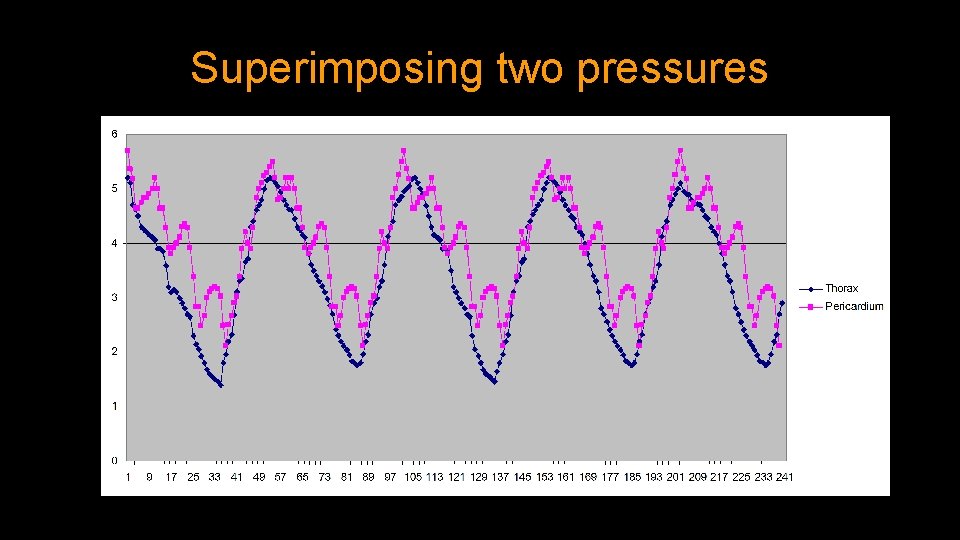
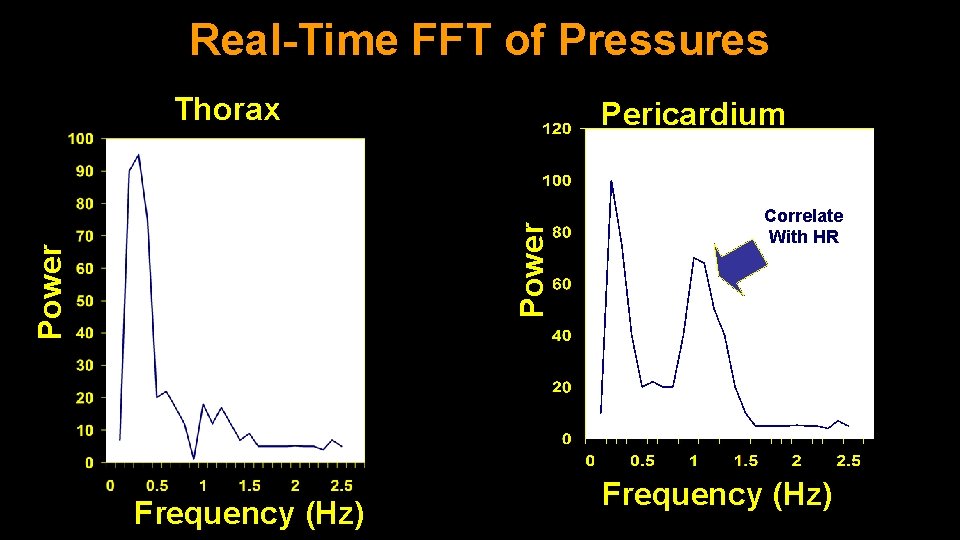
Hypothesis • Pericardial space bordered by two membrane • Inner moves with heart at 60 -90 bpm (1 Hz) • Outer moves with lungs at 12 bpm (0. 2 Hz) • Pressure frequency in lung field should be 0. 2 Hz • Pressure frequency in pericardium should be a blend of 0. 2 Hz and 1 Hz RV 1 Hz Thorax 0. 2 Hz
Thorax on Pullback Mahapatra HRS May 2010
In Pericardium
Superimposing two pressures
Real-Time FFT of Pressures Thorax Power Pericardium Frequency (Hz) Correlate With HR Frequency (Hz)
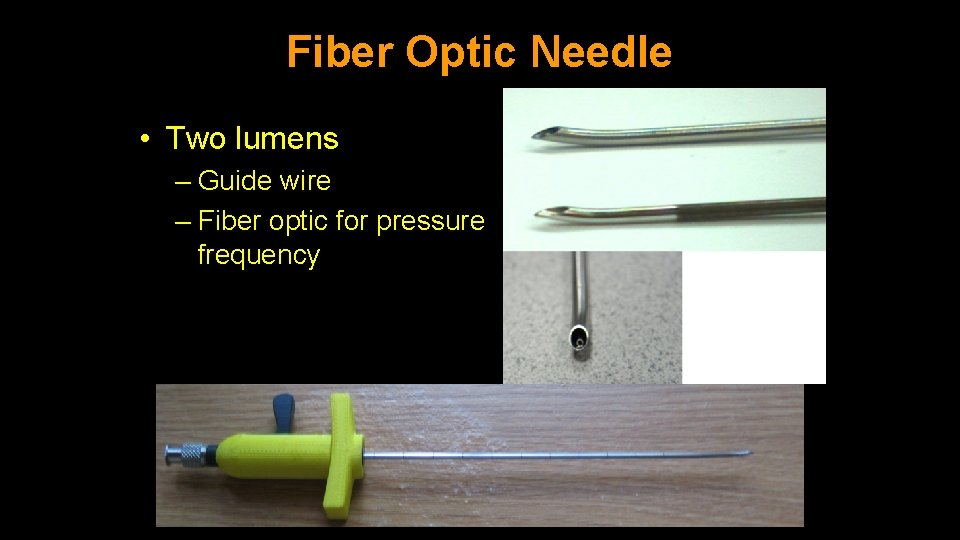
Fiber Optic Needle • Two lumens – Guide wire – Fiber optic for pressure frequency
10 year Timeline A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services 22
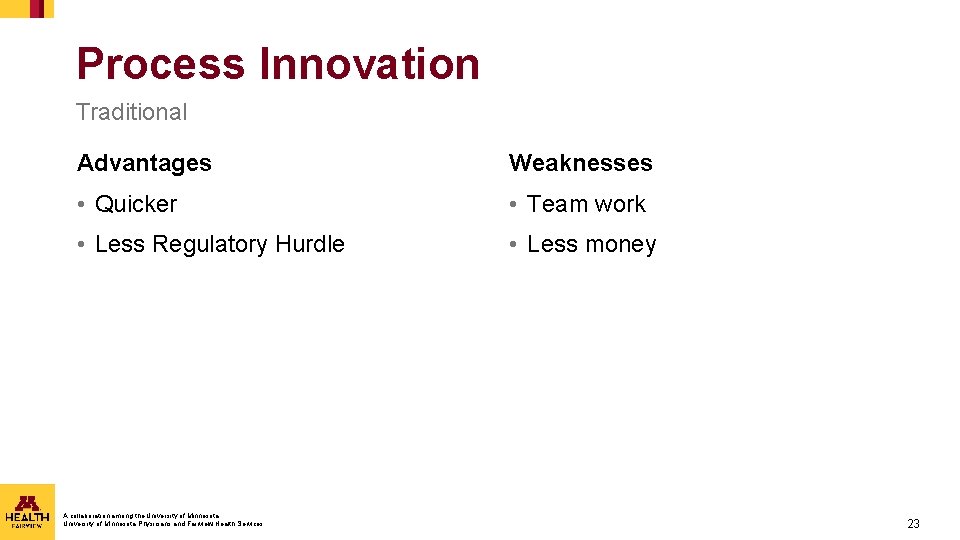
Process Innovation Traditional Advantages Weaknesses • Quicker • Team work • Less Regulatory Hurdle • Less money A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services 23
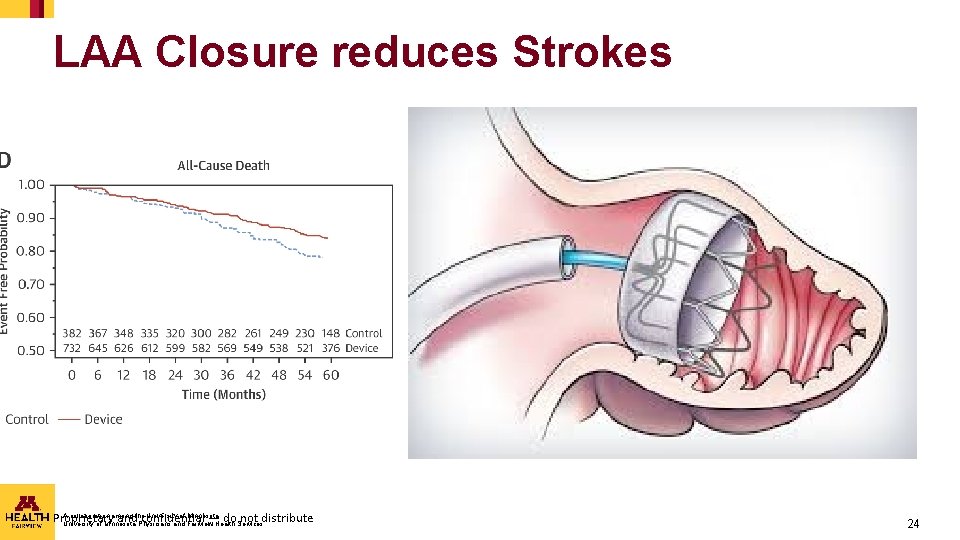
LAA Closure reduces Strokes A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services 24
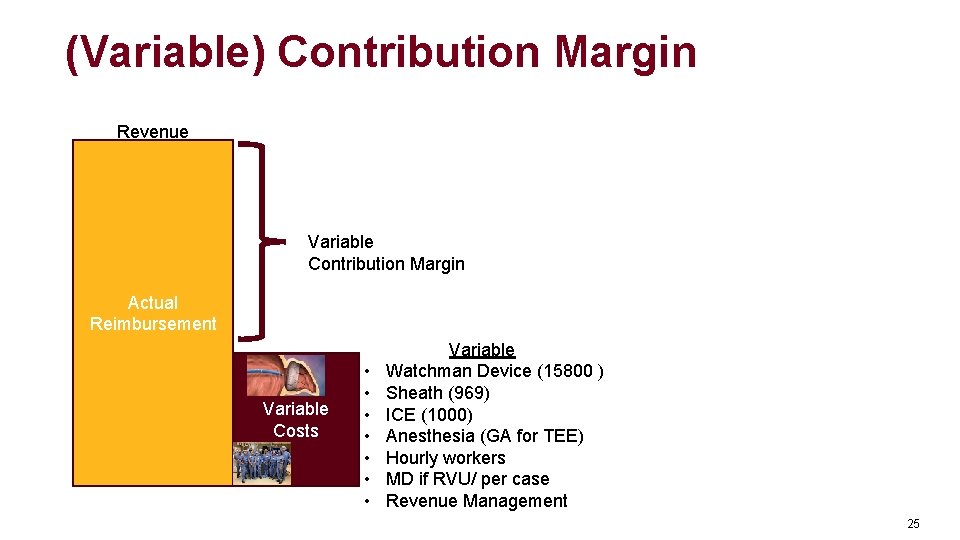
(Variable) Contribution Margin Revenue Variable Contribution Margin Actual Reimbursement Variable Costs • • Variable Watchman Device (15800 ) Sheath (969) ICE (1000) Anesthesia (GA for TEE) Hourly workers MD if RVU/ per case Revenue Management 25
Contribution Margin Revenue Contribution Margin Actual Reimbursement • Fixed Costs • • Fixed Capital Expenses Buildings Administrators Salaried MDs Overhead allocation Variable Costs 26
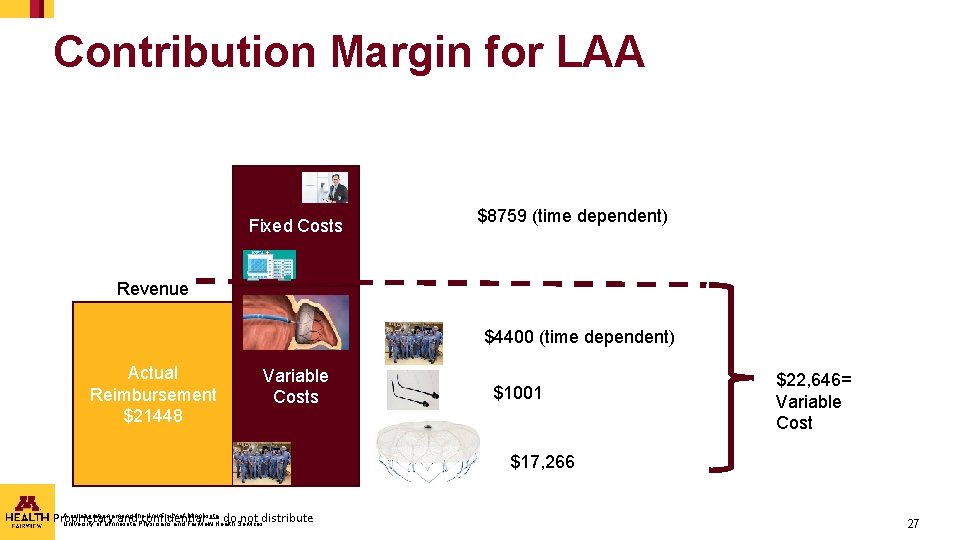
Contribution Margin for LAA Fixed Costs $8759 (time dependent) Revenue $4400 (time dependent) Actual Reimbursement $21448 Variable Costs $1001 $22, 646= Variable Cost $17, 266 A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services 27
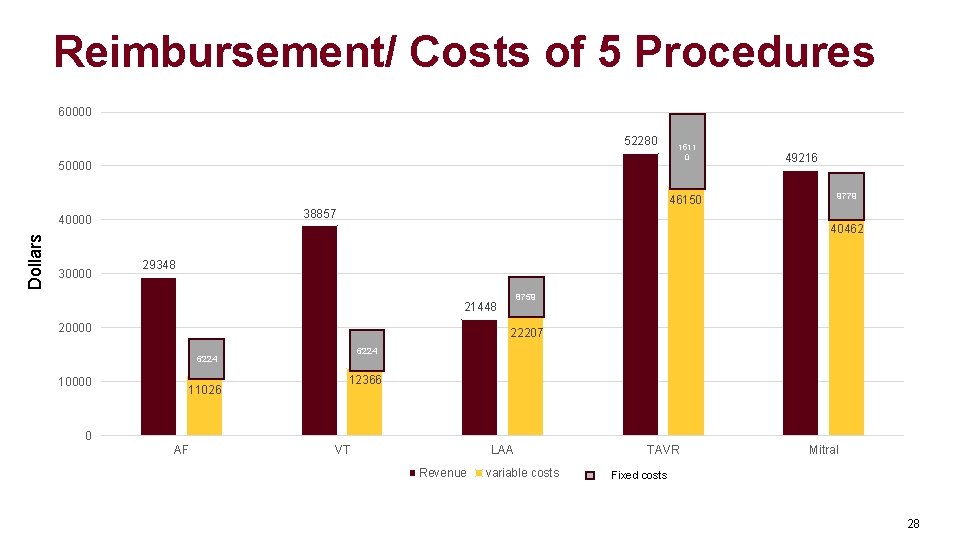
Reimbursement/ Costs of 5 Procedures 60000 52280 50000 Dollars 30000 46150 38857 40000 49216 9779 40462 29348 8759 21448 20000 22207 6224 10000 1511 0 11026 12366 0 AF VT LAA Revenue variable costs TAVR Mitral Fixed costs 28
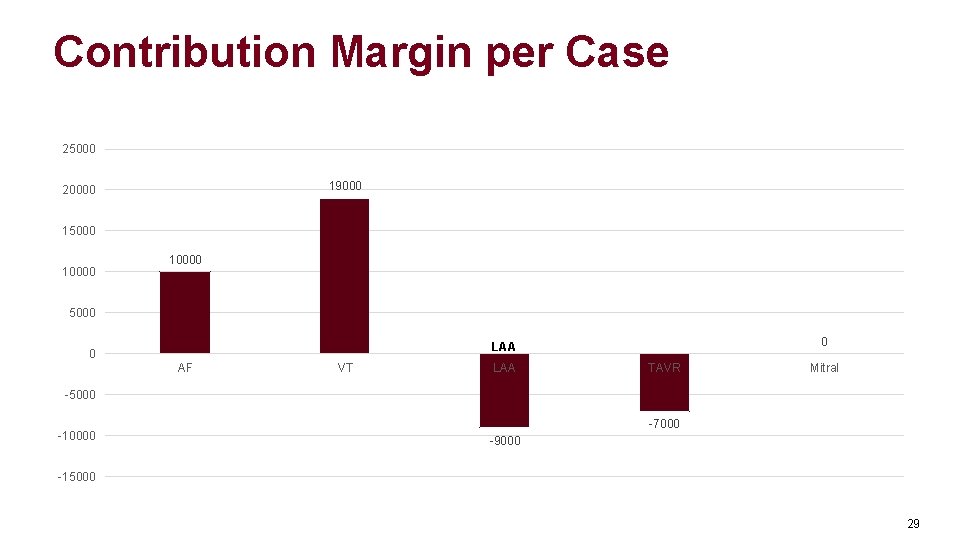
Contribution Margin per Case 25000 19000 20000 15000 10000 5000 0 LAA 0 AF VT LAA TAVR Mitral -5000 -10000 -7000 -9000 -15000 29
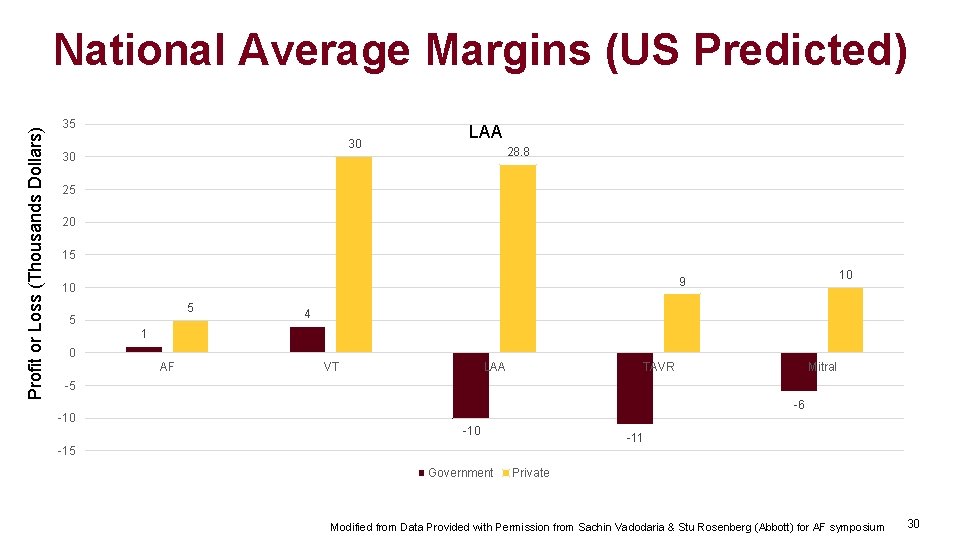
Profit or Loss (Thousands Dollars) National Average Margins (US Predicted) 35 30 30 LAA 28. 8 25 20 15 10 9 10 5 5 4 1 0 AF VT LAA TAVR Mitral -5 -6 -10 -11 -15 Government Private Modified from Data Provided with Permission from Sachin Vadodaria & Stu Rosenberg (Abbott) for AF symposium 30
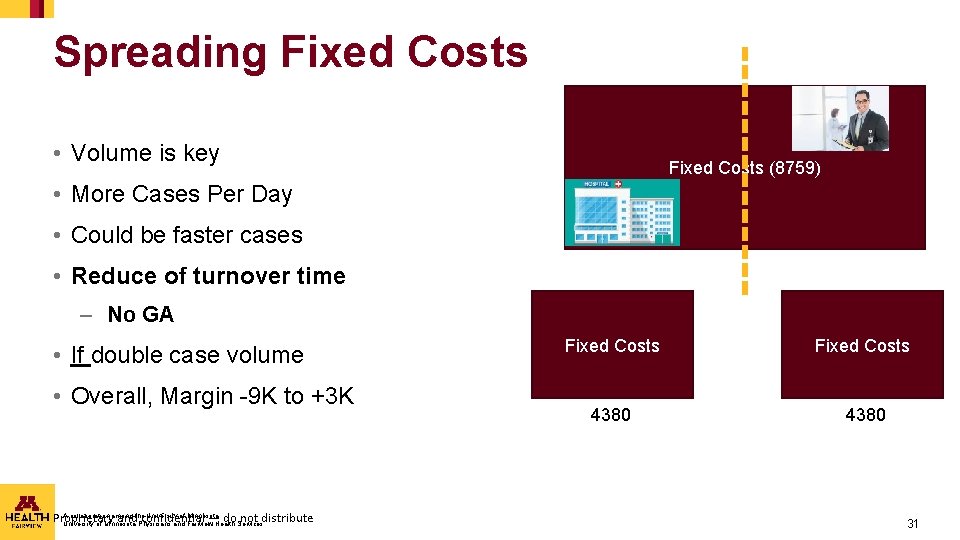
Spreading Fixed Costs • Volume is key Fixed Costs (8759) • More Cases Per Day • Could be faster cases • Reduce of turnover time – No GA • If double case volume • Overall, Margin -9 K to +3 K A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services Fixed Costs 4380 31
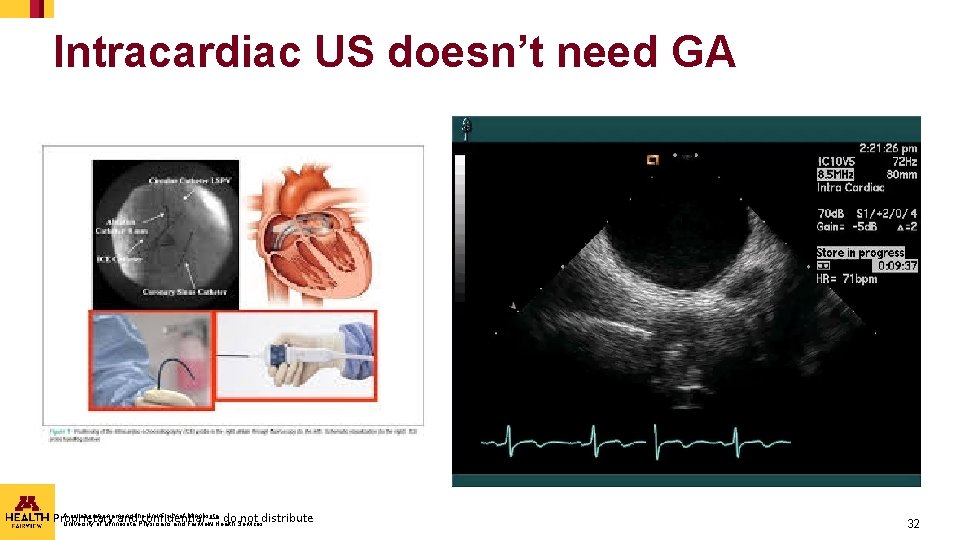
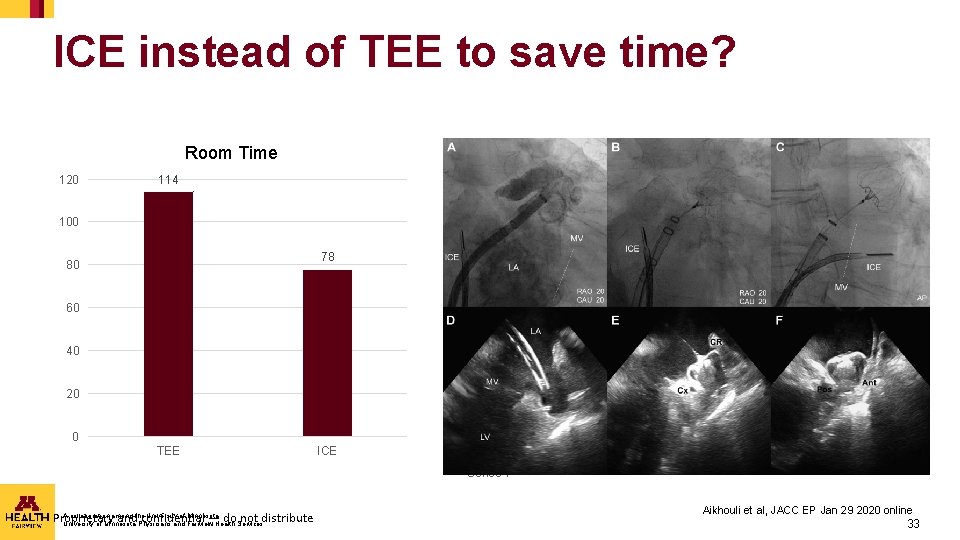
Intracardiac US doesn’t need GA A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services 32
ICE instead of TEE to save time? Room Time 120 Series 1 114 100 78 80 60 40 20 0 TEE ICE Series 1 A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services Aikhouli et al, JACC EP Jan 29 2020 online 33
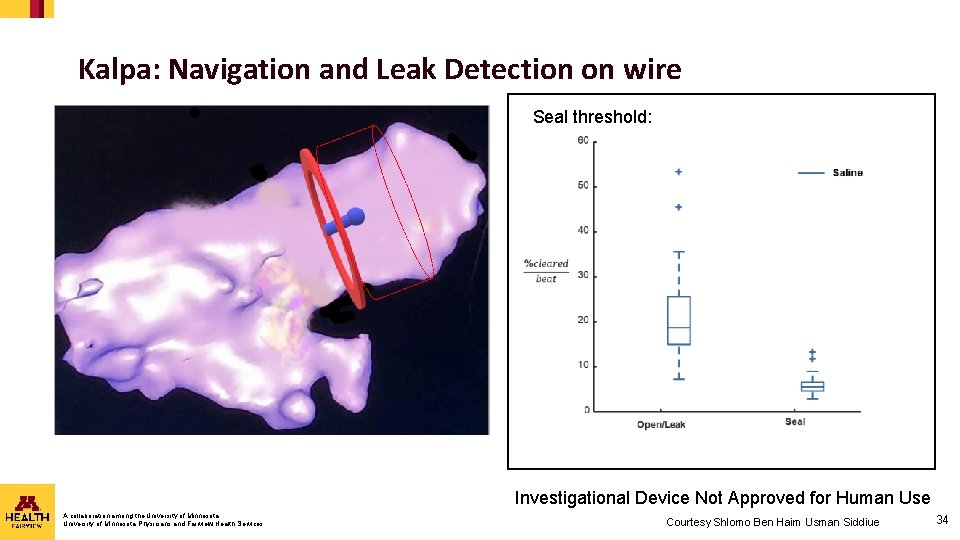
Kalpa: Navigation and Leak Detection on wire Seal threshold: Investigational Device Not Approved for Human Use A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services Courtesy Shlomo Ben Haim Usman Siddiue 34
Barriers • Financial changes make acquisition later • Conflict of Interest Rules • Risk Aversion • Funding of initial ideas • Focus on urgent not important A collaboration among the University of Minnesota, Proprietary and confidential — do not distribute University of Minnesota Physicians and Fairview Health Services 35
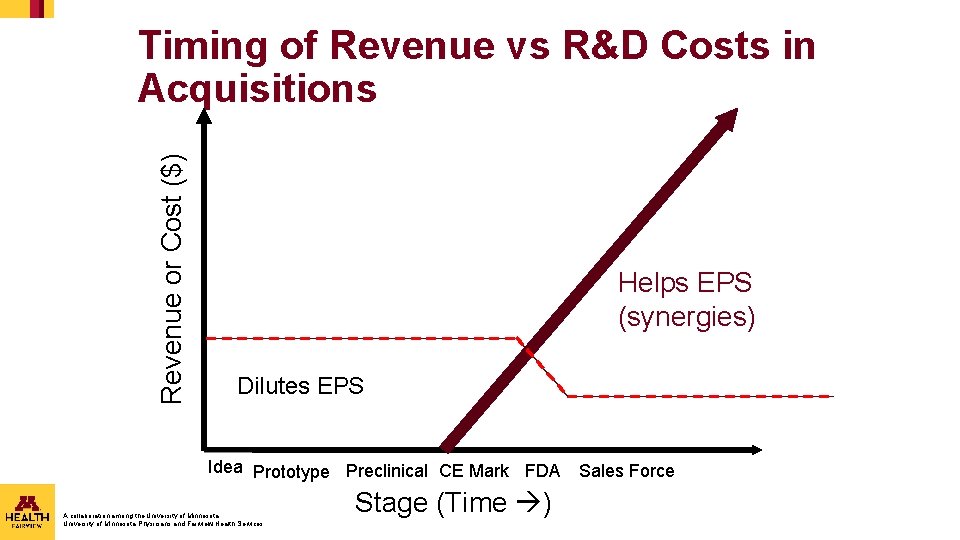
General Criteria for Acquisition • Most acquisitions are targeting technologies that will enhance sales and earnings growth. – Look for “natural” fit with existing infrastructure to drive post-acquisition success. – ROIC and EPS impact are benchmarks used to maintain financial discipline. – Transactions that require a continuing R&D expenditure and/or future regulatory approval to achieve financial goals are less attractive. A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services
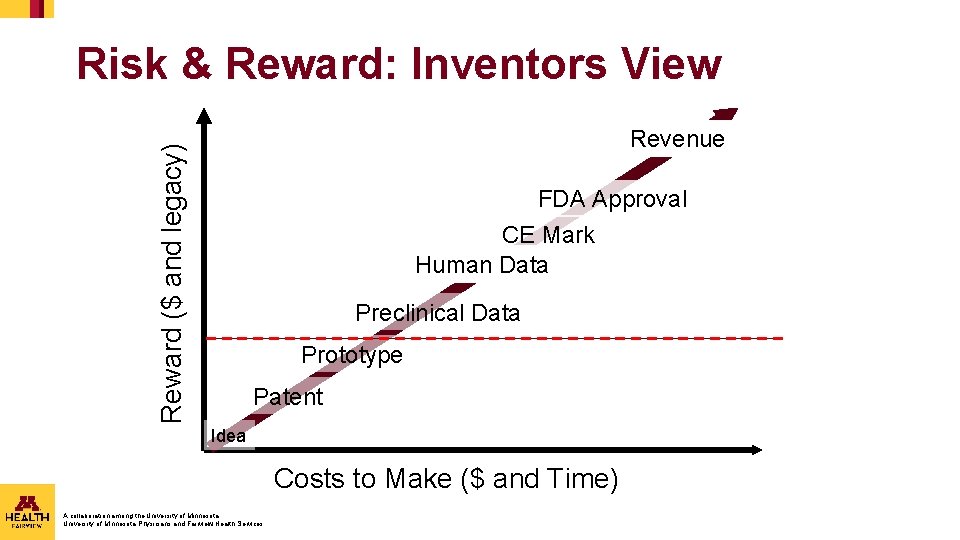
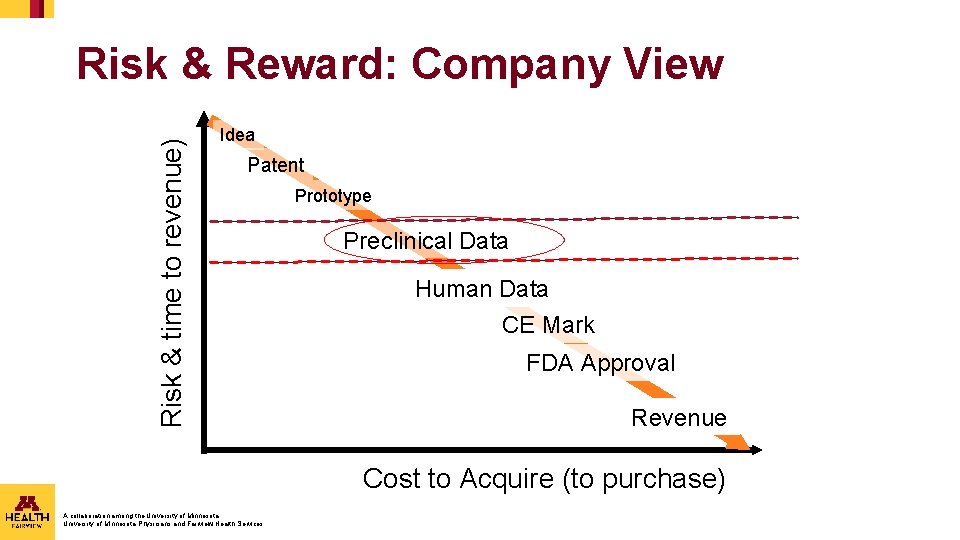
Risk & Reward: Inventors View Reward ($ and legacy) Revenue FDA Approval CE Mark Human Data Preclinical Data Prototype Patent Idea Costs to Make ($ and Time) A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services
Risk & time to revenue) Risk & Reward: Company View Idea Patent Prototype Preclinical Data Human Data CE Mark FDA Approval Revenue Cost to Acquire (to purchase) A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services
Revenue or Cost ($) Timing of Revenue vs R&D Costs in Acquisitions Helps EPS (synergies) Dilutes EPS Idea Prototype Preclinical CE Mark FDA A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services Stage (Time ) Sales Force
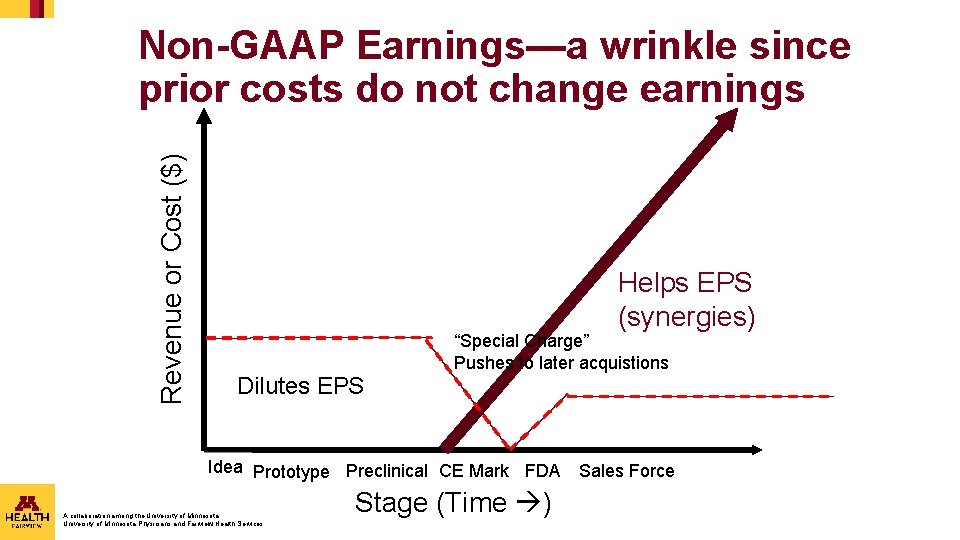
Revenue or Cost ($) Non-GAAP Earnings—a wrinkle since prior costs do not change earnings Helps EPS (synergies) Dilutes EPS “Special Charge” Pushes to later acquistions Idea Prototype Preclinical CE Mark FDA A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services Stage (Time ) Sales Force
Conflict of interest is real Key is • Acknowledge industry can help • Make sure testing done by someone who doesn’t own shares A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services 42 Confi dentia l
Summary • Innovation is key • Process Innovation often as important but ignored • Need time to incubate ideas internally • Need conflict of interest rules to acknowledge benefits A collaboration among the University of Minnesota, University of Minnesota Physicians and Fairview Health Services 43 Confi dentia l