Copyright Notice You are authorized to use these




- Slides: 34
Copyright Notice You are authorized to use these slides subject to the following terms, conditions and exceptions: • They are to be used solely for personal, noncommercial, informational, and educational purposes. • They may not to be modified in any way. • Copyright information or other proprietary notices may not be removed, changed, or altered. • The authors, contributors, and editorial staff have made every effort to contact holders of copyright to obtain permission to reproduce copyright material. However, if any permissions have been inadvertently overlooked, Baylor College of Medicine will be pleased to make the necessary and reasonable arrangements. • To request permission to reproduce or modify a slide or image from Hypertension Online, please contact us at ccit@bcm. tmc. edu. Slide Source Hypertension Online www. hypertensiononline. org
Los 100 mg + Other Antihypertensive Therapy (excluding ACEI, AIIA) Los 100 mg Los 50 mg NIDDM Patients with proteinuria Maintain prior antihypertensive therapy (excluding ACEI, AIIA) n = 1520 Goal BP < 140/90 mm. Hg Placebo + Other Antihypertensive Therapy (excluding ACEI, AIIA) Clinical Trials in Hypertension and Renal Diseases Slide Source Hypertension Online www. hypertensiononline. org
The Dual Significance of Proteinuria • Proteinuria (albuminuria) results from injury to glomerular circulation Ø Increased proteinuria (albuminuria) is associated with progressive kidney disease • In diabetes and hypertension, proteinuria (albuminuria) is also an indicator of injury in the systemic circulation Ø Proteinuria (albuminuria) is associated with increased cardiovascular risk Slide Source Hypertension Online www. hypertensiononline. org
Renal Disease and Hypertension Core Concepts of Treatment • Hypertension and proteinuria (albuminuria) are both independent variables that predict long-term decline in renal function Ø Renal disease is both a cause and consequence of hypertension Ø Reduction of blood pressure reduces cardiovascular risk and renal risk Ø Reduction of proteinuria (albuminuria) may lower both cardiovascular risk and renal risk Slide Source Hypertension Online www. hypertensiononline. org
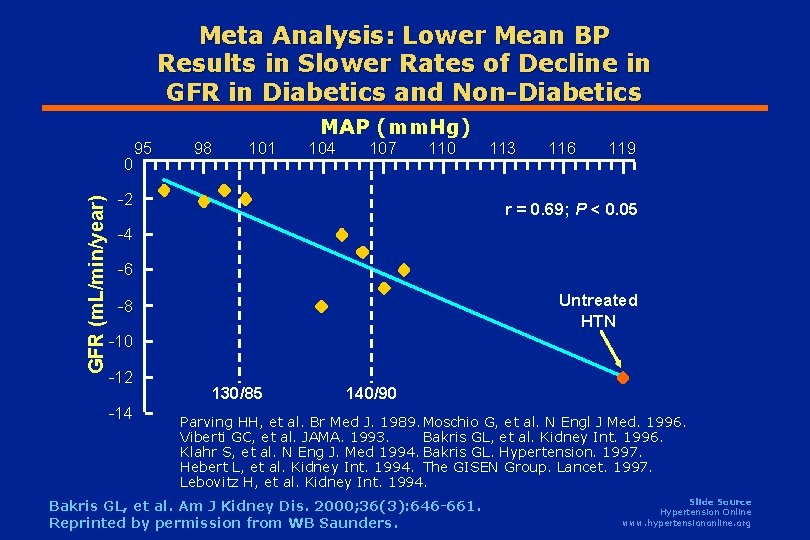
Meta Analysis: Lower Mean BP Results in Slower Rates of Decline in GFR in Diabetics and Non-Diabetics MAP (mm. Hg) GFR (m. L/min/year) 0 95 98 101 104 107 110 -2 113 116 119 r = 0. 69; P < 0. 05 -4 -6 Untreated HTN -8 -10 -12 -14 130/85 140/90 Parving HH, et al. Br Med J. 1989. Moschio G, et al. N Engl J Med. 1996. Viberti GC, et al. JAMA. 1993. Bakris GL, et al. Kidney Int. 1996. Klahr S, et al. N Eng J. Med 1994. Bakris GL. Hypertension. 1997. Hebert L, et al. Kidney Int. 1994. The GISEN Group. Lancet. 1997. Lebovitz H, et al. Kidney Int. 1994. Bakris GL, et al. Am J Kidney Dis. 2000; 36(3): 646 -661. Reprinted by permission from WB Saunders. Slide Source Hypertension Online www. hypertensiononline. org
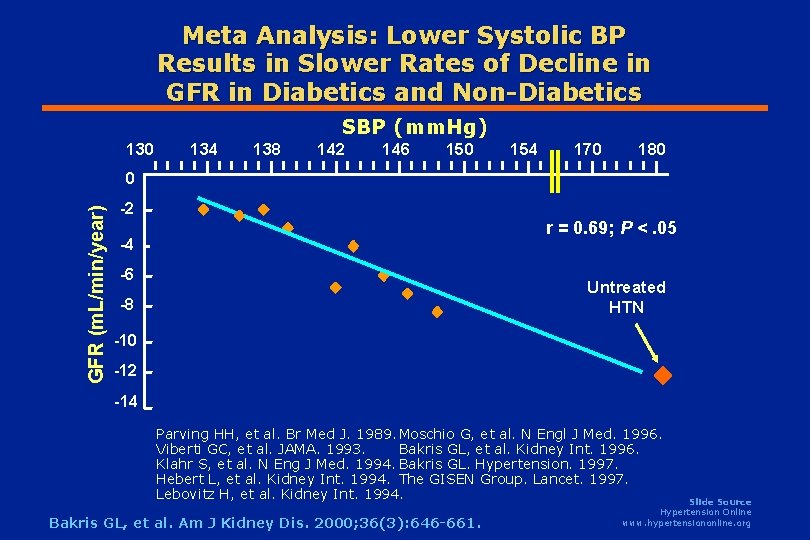
Meta Analysis: Lower Systolic BP Results in Slower Rates of Decline in GFR in Diabetics and Non-Diabetics SBP (mm. Hg) 130 134 138 142 146 150 154 170 180 GFR (m. L/min/year) 0 -2 r = 0. 69; P <. 05 -4 -6 Untreated HTN -8 -10 -12 -14 Parving HH, et al. Br Med J. 1989. Moschio G, et al. N Engl J Med. 1996. Viberti GC, et al. JAMA. 1993. Bakris GL, et al. Kidney Int. 1996. Klahr S, et al. N Eng J Med. 1994. Bakris GL. Hypertension. 1997. Hebert L, et al. Kidney Int. 1994. The GISEN Group. Lancet. 1997. Lebovitz H, et al. Kidney Int. 1994. Bakris GL, et al. Am J Kidney Dis. 2000; 36(3): 646 -661. Slide Source Hypertension Online www. hypertensiononline. org
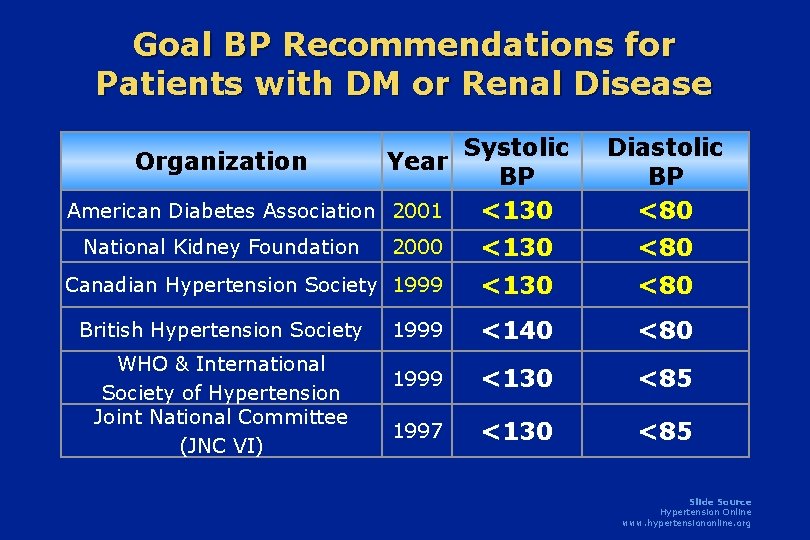
Goal BP Recommendations for Patients with DM or Renal Disease Systolic Organization Year BP American Diabetes Association 2001 <130 Diastolic BP <80 2000 <130 <80 Canadian Hypertension Society 1999 <130 <80 1999 <140 <80 1999 <130 <85 1997 <130 <85 National Kidney Foundation British Hypertension Society WHO & International Society of Hypertension Joint National Committee (JNC VI) Slide Source Hypertension Online www. hypertensiononline. org
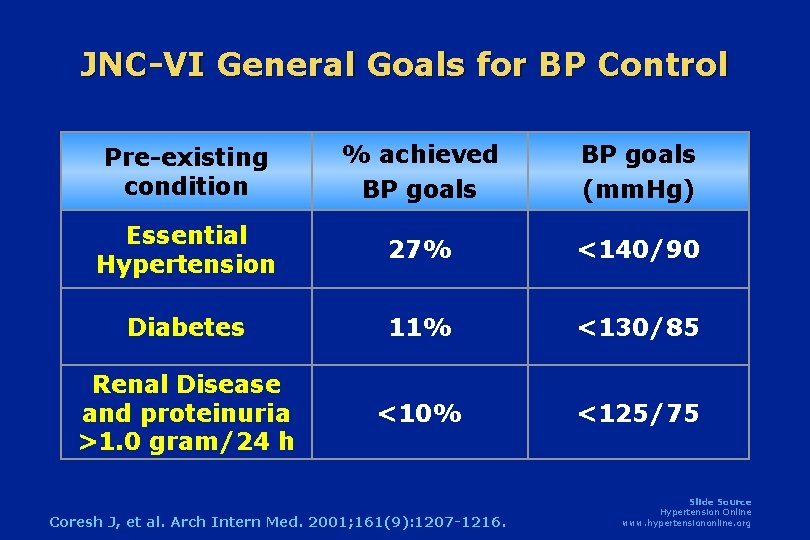
JNC-VI General Goals for BP Control Pre-existing condition % achieved BP goals (mm. Hg) Essential Hypertension 27% <140/90 Diabetes 11% <130/85 Renal Disease and proteinuria >1. 0 gram/24 h <10% <125/75 Coresh J, et al. Arch Intern Med. 2001; 161(9): 1207 -1216. Slide Source Hypertension Online www. hypertensiononline. org
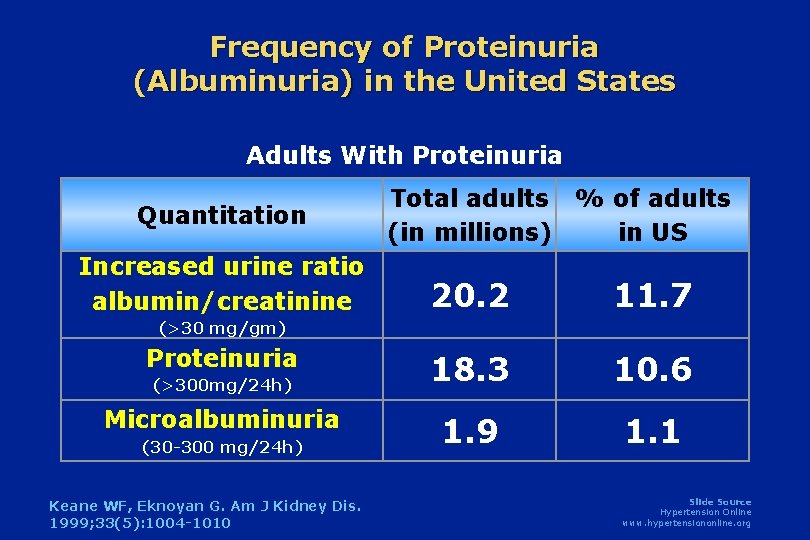
Frequency of Proteinuria (Albuminuria) in the United States Adults With Proteinuria Quantitation Increased urine ratio albumin/creatinine Total adults % of adults (in millions) in US 20. 2 11. 7 18. 3 10. 6 1. 9 1. 1 (>30 mg/gm) Proteinuria (>300 mg/24 h) Microalbuminuria (30 -300 mg/24 h) Keane WF, Eknoyan G. Am J Kidney Dis. 1999; 33(5): 1004 -1010 Slide Source Hypertension Online www. hypertensiononline. org
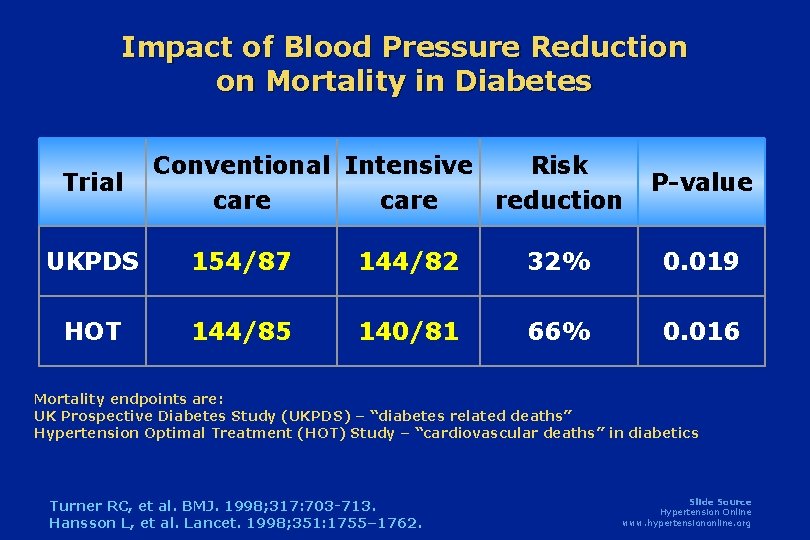
Impact of Blood Pressure Reduction on Mortality in Diabetes Trial Conventional Intensive Risk care reduction P-value UKPDS 154/87 144/82 32% 0. 019 HOT 144/85 140/81 66% 0. 016 Mortality endpoints are: UK Prospective Diabetes Study (UKPDS) – “diabetes related deaths” Hypertension Optimal Treatment (HOT) Study – “cardiovascular deaths” in diabetics Turner RC, et al. BMJ. 1998; 317: 703 -713. Hansson L, et al. Lancet. 1998; 351: 1755– 1762. Slide Source Hypertension Online www. hypertensiononline. org
UK Prospective Diabetes Study (UKPDS) Major Results: Powerful Risk Reductions Better blood pressure control reduces… • Strokes by > one third • Serious deterioration of vision by > one third • Death related to diabetes by one third Better glucose control reduces… • Early kidney damage by one third • Major diabetic eye disease by one fourth Turner RC, et al. BMJ. 1998; 317: 703 -713. Slide Source Hypertension Online www. hypertensiononline. org
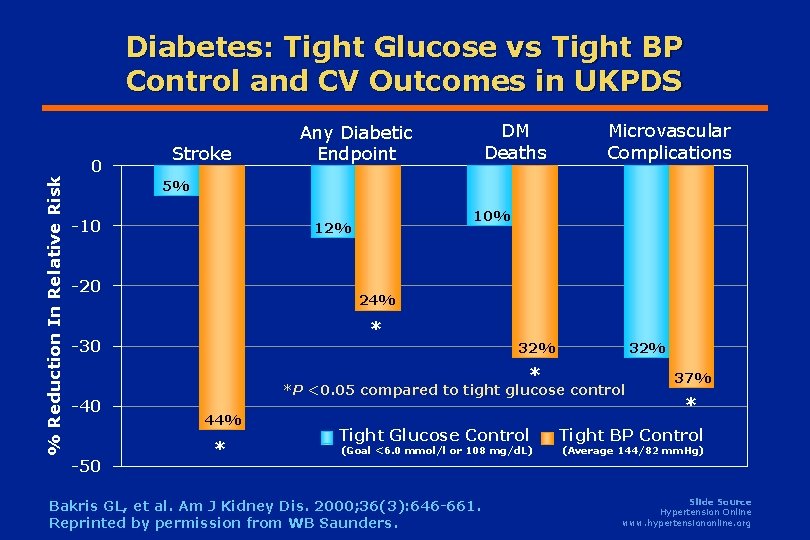
Diabetes: Tight Glucose vs Tight BP Control and CV Outcomes in UKPDS % Reduction In Relative Risk 0 Stroke DM Deaths Any Diabetic Endpoint Microvascular Complications 5% -10 10% 12% -20 24% * -30 32% * -40 -50 32% *P <0. 05 compared to tight glucose control 44% * Tight Glucose Control (Goal <6. 0 mmol/l or 108 mg/d. L) Bakris GL, et al. Am J Kidney Dis. 2000; 36(3): 646 -661. Reprinted by permission from WB Saunders. 37% * Tight BP Control (Average 144/82 mm. Hg) Slide Source Hypertension Online www. hypertensiononline. org
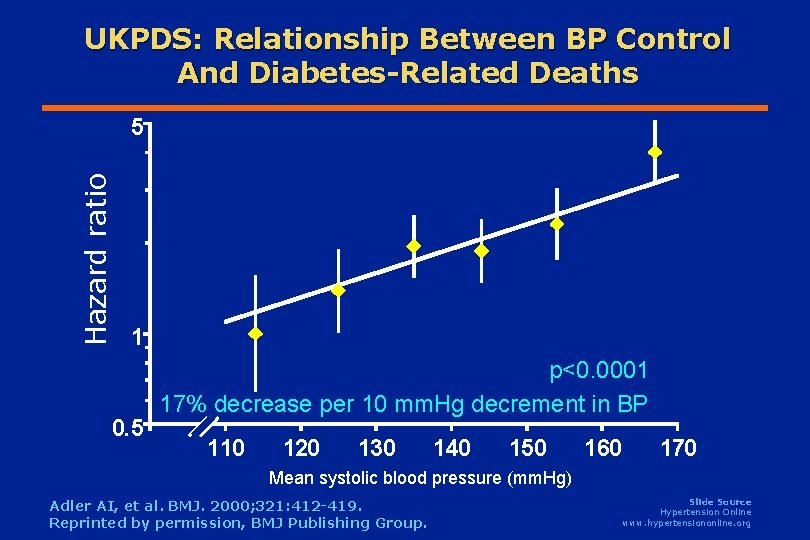
UKPDS: Relationship Between BP Control And Diabetes-Related Deaths Hazard ratio 5 1 0. 5 p<0. 0001 17% decrease per 10 mm. Hg decrement in BP 110 120 130 140 150 160 170 Mean systolic blood pressure (mm. Hg) Adler AI, et al. BMJ. 2000; 321: 412 -419. Reprinted by permission, BMJ Publishing Group. Slide Source Hypertension Online www. hypertensiononline. org
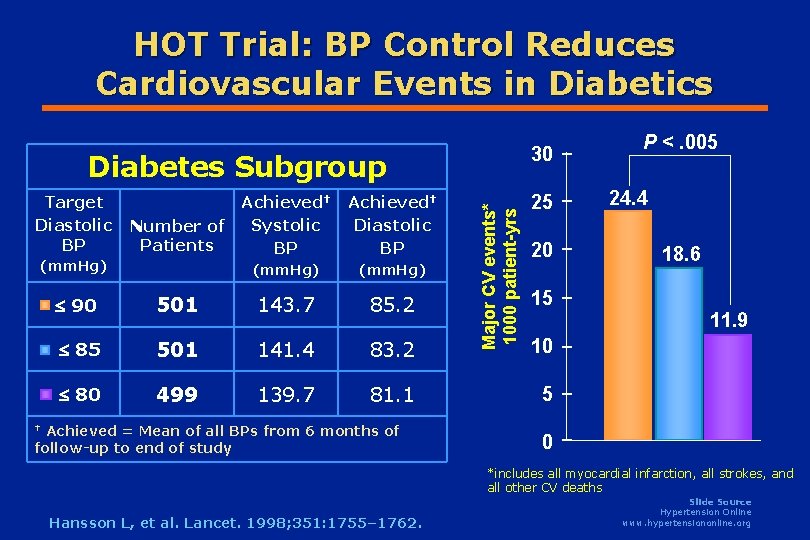
HOT Trial: BP Control Reduces Cardiovascular Events in Diabetics 30 Target Diastolic BP Number of Patients (mm. Hg) Achieved† Systolic BP Achieved† Diastolic BP (mm. Hg) 90 501 143. 7 85. 2 85 501 141. 4 83. 2 80 499 139. 7 81. 1 Achieved = Mean of all BPs from 6 months of follow-up to end of study † Major CV events* 1000 patient-yrs Diabetes Subgroup 25 20 15 P <. 005 24. 4 18. 6 11. 9 10 5 0 *includes all myocardial infarction, all strokes, and all other CV deaths Hansson L, et al. Lancet. 1998; 351: 1755– 1762. Slide Source Hypertension Online www. hypertensiononline. org
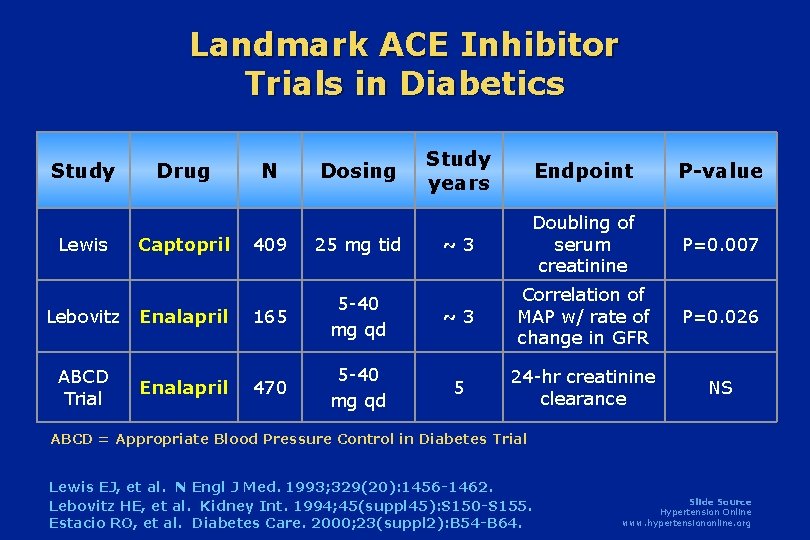
Landmark ACE Inhibitor Trials in Diabetics Study Lewis Drug Captopril N Dosing Study years Endpoint P-value ~3 Doubling of serum creatinine P=0. 007 P=0. 026 NS 409 25 mg tid ~3 Correlation of MAP w/ rate of change in GFR 5 24 -hr creatinine clearance Lebovitz Enalapril 165 5 -40 mg qd ABCD Trial Enalapril 470 5 -40 mg qd ABCD = Appropriate Blood Pressure Control in Diabetes Trial Lewis EJ, et al. N Engl J Med. 1993; 329(20): 1456 -1462. Lebovitz HE, et al. Kidney Int. 1994; 45(suppl 45): S 150 -S 155. Estacio RO, et al. Diabetes Care. 2000; 23(suppl 2): B 54 -B 64. Slide Source Hypertension Online www. hypertensiononline. org
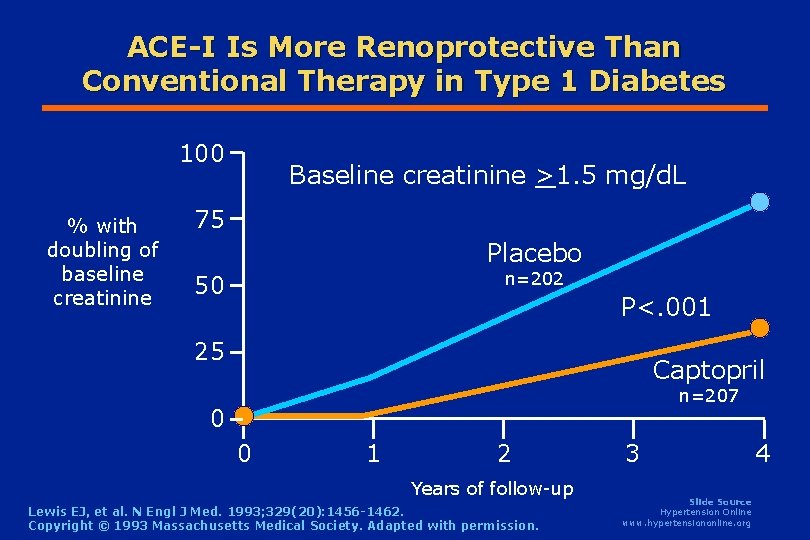
ACE-I Is More Renoprotective Than Conventional Therapy in Type 1 Diabetes 100 % with doubling of baseline creatinine Baseline creatinine >1. 5 mg/d. L 75 Placebo n=202 50 P<. 001 25 Captopril n=207 0 0 1 2 Years of follow-up Lewis EJ, et al. N Engl J Med. 1993; 329(20): 1456 -1462. Copyright © 1993 Massachusetts Medical Society. Adapted with permission. 3 Slide Source Hypertension Online www. hypertensiononline. org 4
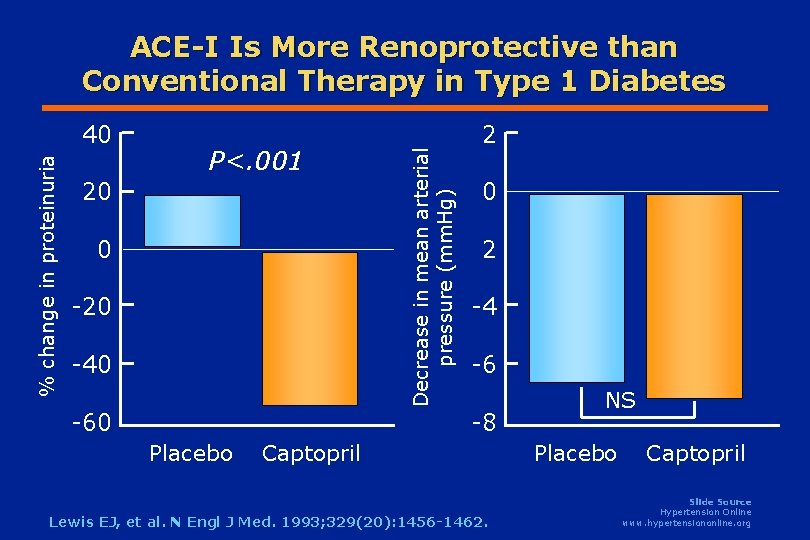
ACE-I Is More Renoprotective than Conventional Therapy in Type 1 Diabetes P<. 001 20 0 -20 -40 -60 Placebo 2 Decrease in mean arterial pressure (mm. Hg) % change in proteinuria 40 0 2 -4 -6 -8 Captopril Lewis EJ, et al. N Engl J Med. 1993; 329(20): 1456 -1462. NS Placebo Captopril Slide Source Hypertension Online www. hypertensiononline. org
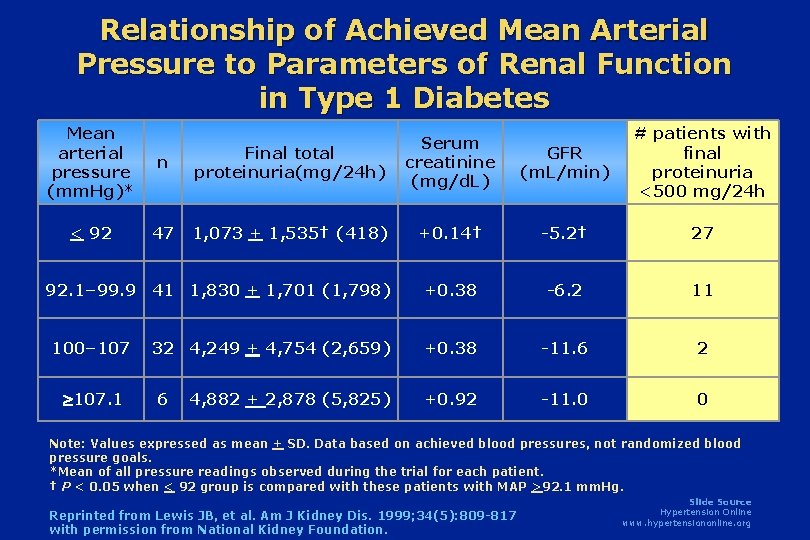
Relationship of Achieved Mean Arterial Pressure to Parameters of Renal Function in Type 1 Diabetes Mean arterial pressure (mm. Hg)* n < 92 47 Final total proteinuria(mg/24 h) Serum creatinine (mg/d. L) GFR (m. L/min) # patients with final proteinuria <500 mg/24 h 1, 073 + 1, 535† (418) +0. 14† -5. 2† 27 +0. 38 -6. 2 11 +0. 38 -11. 6 2 +0. 92 -11. 0 0 92. 1– 99. 9 41 1, 830 + 1, 701 (1, 798) 100– 107. 1 32 4, 249 + 4, 754 (2, 659) 6 4, 882 + 2, 878 (5, 825) Note: Values expressed as mean + SD. Data based on achieved blood pressures, not randomized blood pressure goals. *Mean of all pressure readings observed during the trial for each patient. † P < 0. 05 when < 92 group is compared with these patients with MAP >92. 1 mm. Hg. Reprinted from Lewis JB, et al. Am J Kidney Dis. 1999; 34(5): 809 -817 with permission from National Kidney Foundation. Slide Source Hypertension Online www. hypertensiononline. org
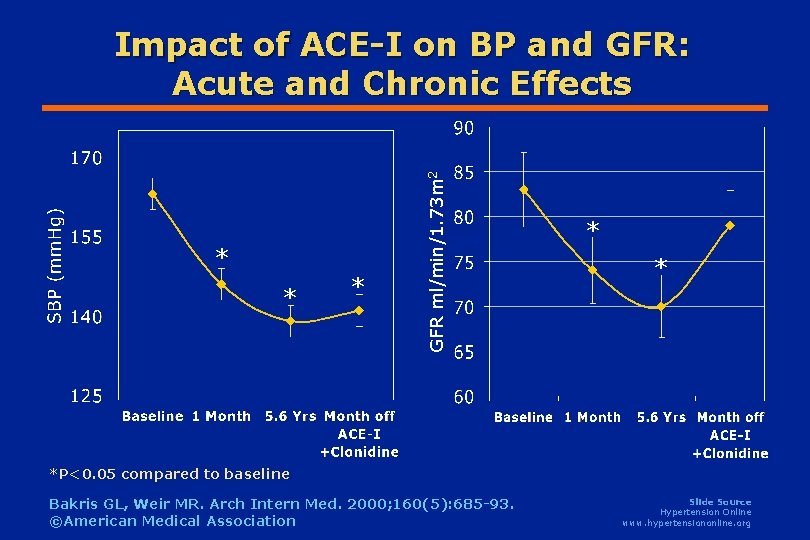
* * * GFR ml/min/1. 73 m 2 Impact of ACE-I on BP and GFR: Acute and Chronic Effects * * *P<0. 05 compared to baseline Bakris GL, Weir MR. Arch Intern Med. 2000; 160(5): 685 -93. ©American Medical Association Slide Source Hypertension Online www. hypertensiononline. org
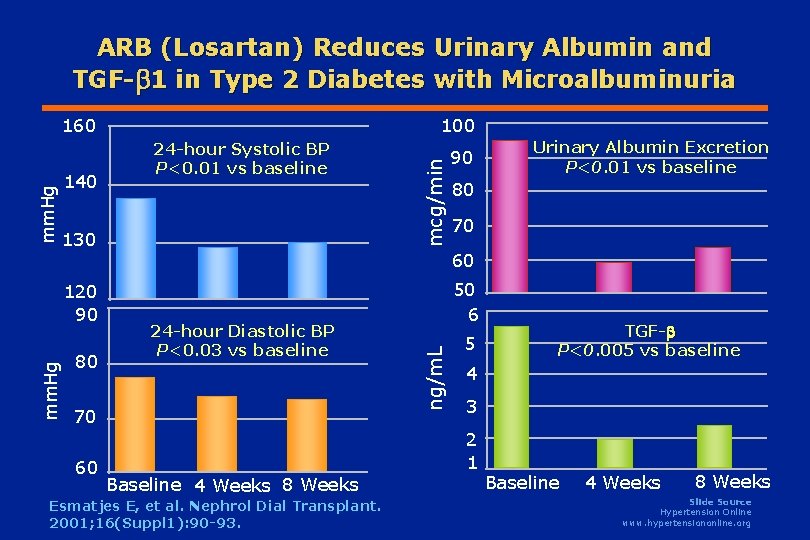
ARB (Losartan) Reduces Urinary Albumin and TGF- 1 in Type 2 Diabetes with Microalbuminuria 130 120 90 mm. Hg 24 -hour Systolic BP P<0. 01 vs baseline 80 90 Urinary Albumin Excretion P<0. 01 vs baseline 80 70 60 24 -hour Diastolic BP P<0. 03 vs baseline 70 60 mcg/min 140 100 50 6 ng/m. L mm. Hg 160 5 4 3 2 1 Baseline 4 Weeks 8 Weeks Esmatjes E, et al. Nephrol Dial Transplant. 2001; 16(Suppl 1): 90 -93. TGF- P<0. 005 vs baseline Baseline 4 Weeks 8 Weeks Slide Source Hypertension Online www. hypertensiononline. org
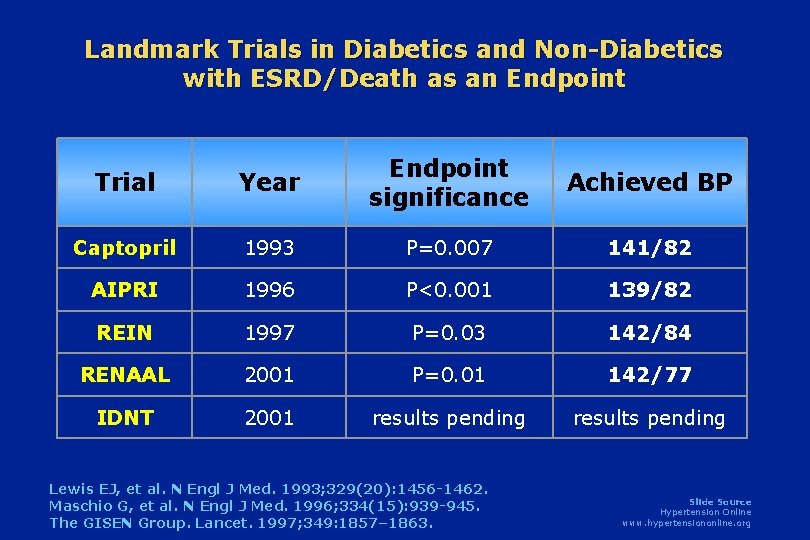
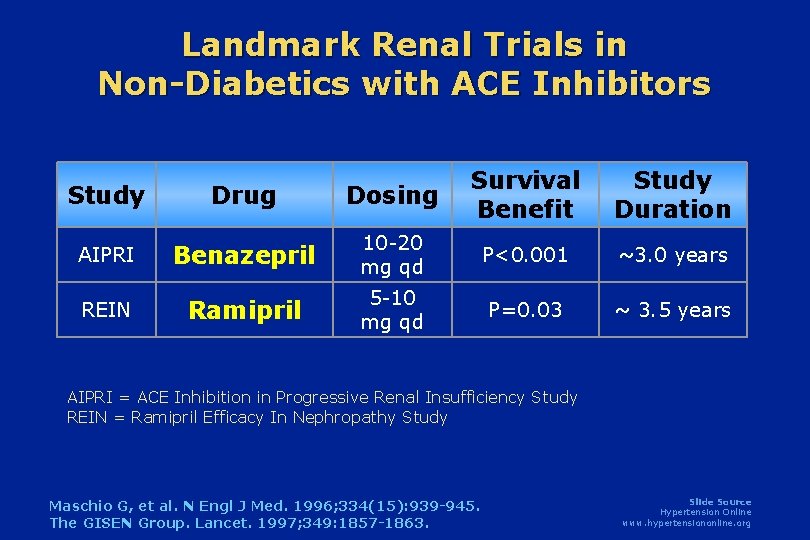
Landmark Trials in Diabetics and Non-Diabetics with ESRD/Death as an Endpoint Trial Year Endpoint significance Achieved BP Captopril 1993 P=0. 007 141/82 AIPRI 1996 P<0. 001 139/82 REIN 1997 P=0. 03 142/84 RENAAL 2001 P=0. 01 142/77 IDNT 2001 results pending Lewis EJ, et al. N Engl J Med. 1993; 329(20): 1456 -1462. Maschio G, et al. N Engl J Med. 1996; 334(15): 939 -945. The GISEN Group. Lancet. 1997; 349: 1857– 1863. Slide Source Hypertension Online www. hypertensiononline. org
Landmark Renal Trials in Non-Diabetics with ACE Inhibitors Study Drug Dosing Survival Benefit Study Duration AIPRI Benazepril 10 -20 mg qd P<0. 001 ~3. 0 years REIN Ramipril 5 -10 mg qd P=0. 03 ~ 3. 5 years AIPRI = ACE Inhibition in Progressive Renal Insufficiency Study REIN = Ramipril Efficacy In Nephropathy Study Maschio G, et al. N Engl J Med. 1996; 334(15): 939 -945. The GISEN Group. Lancet. 1997; 349: 1857 -1863. Slide Source Hypertension Online www. hypertensiononline. org
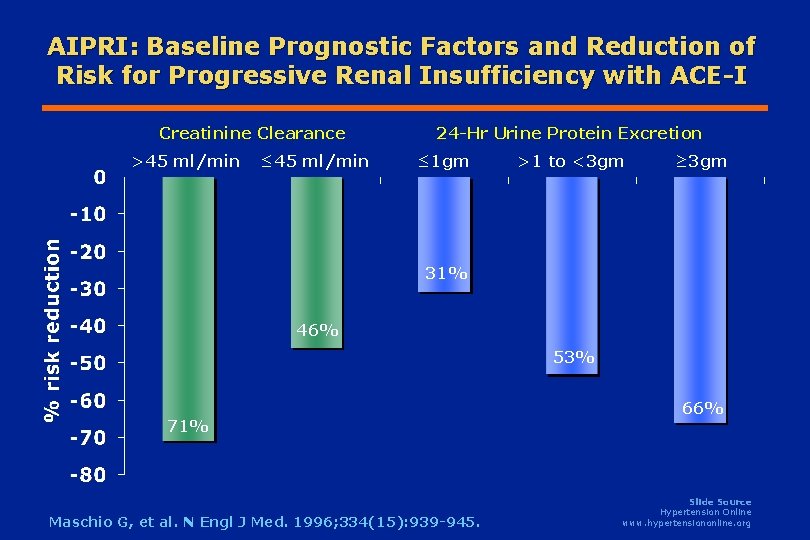
AIPRI: Baseline Prognostic Factors and Reduction of Risk for Progressive Renal Insufficiency with ACE-I Creatinine Clearance >45 ml/min ≤ 45 ml/min 24 -Hr Urine Protein Excretion ≤ 1 gm >1 to <3 gm ≥ 3 gm 31% 46% 53% 71% Maschio G, et al. N Engl J Med. 1996; 334(15): 939 -945. 66% Slide Source Hypertension Online www. hypertensiononline. org
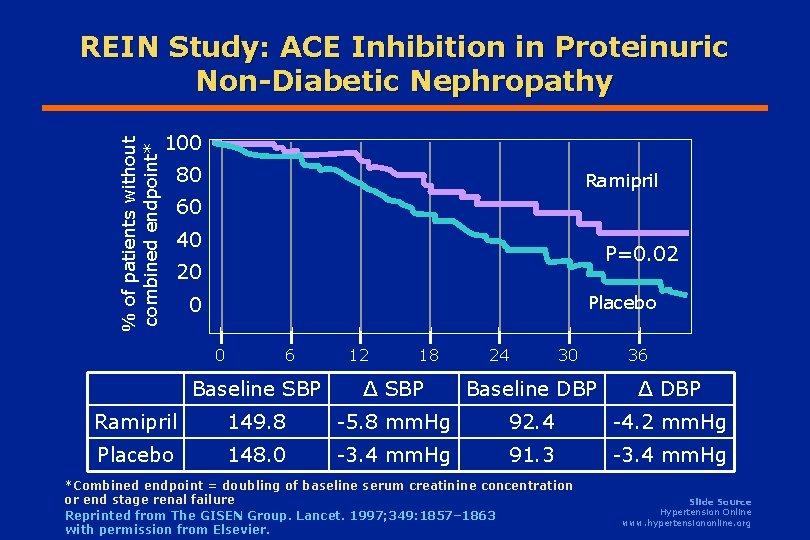
% of patients without combined endpoint* REIN Study: ACE Inhibition in Proteinuric Non-Diabetic Nephropathy 100 80 Ramipril 60 40 P=0. 02 20 Placebo 0 0 6 12 18 24 30 36 Baseline SBP ∆ SBP Baseline DBP ∆ DBP Ramipril 149. 8 -5. 8 mm. Hg 92. 4 -4. 2 mm. Hg Placebo 148. 0 -3. 4 mm. Hg 91. 3 -3. 4 mm. Hg *Combined endpoint = doubling of baseline serum creatinine concentration or end stage renal failure Reprinted from The GISEN Group. Lancet. 1997; 349: 1857– 1863 with permission from Elsevier. Slide Source Hypertension Online www. hypertensiononline. org
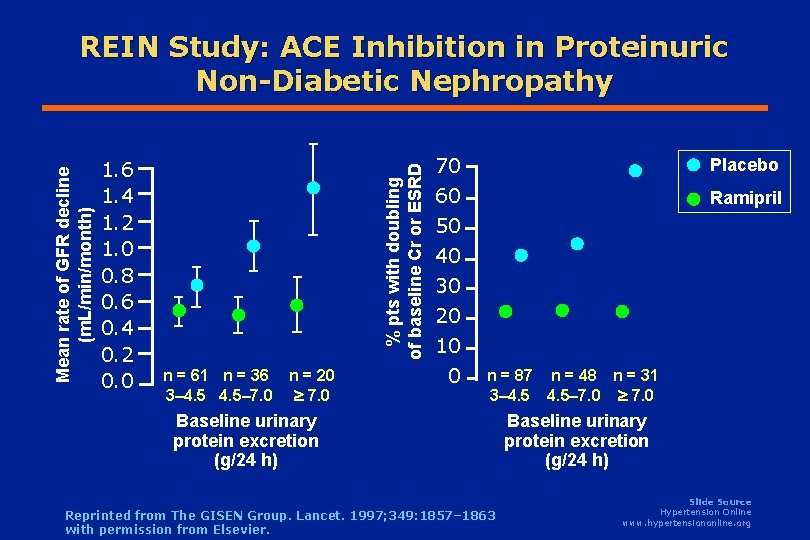
1. 6 1. 4 1. 2 1. 0 0. 8 0. 6 0. 4 0. 2 0. 0 % pts with doubling of baseline Cr or ESRD Mean rate of GFR decline (m. L/min/month) REIN Study: ACE Inhibition in Proteinuric Non-Diabetic Nephropathy n = 61 n = 36 3– 4. 5– 7. 0 n = 20 7. 0 70 60 50 40 30 20 10 0 Placebo Ramipril n = 87 n = 48 n = 31 3– 4. 5– 7. 0 Baseline urinary protein excretion (g/24 h) Reprinted from The GISEN Group. Lancet. 1997; 349: 1857– 1863 with permission from Elsevier. Baseline urinary protein excretion (g/24 h) Slide Source Hypertension Online www. hypertensiononline. org
REIN Study: Ramipril Group Median Change in Urinary Protein Excretion % change in urinary protein excretion Months The GISEN Group. Lancet. 1997; 349: 1857– 1863. Slide Source Hypertension Online www. hypertensiononline. org
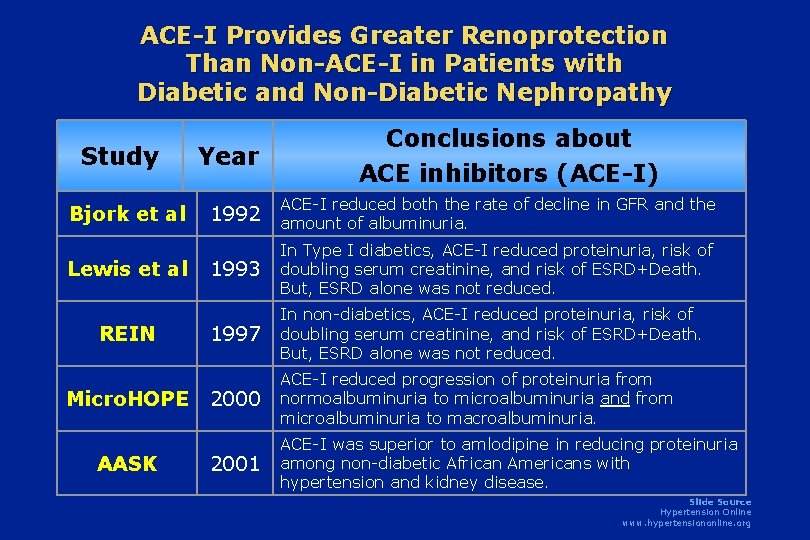
ACE-I Provides Greater Renoprotection Than Non-ACE-I in Patients with Diabetic and Non-Diabetic Nephropathy Study Bjork et al Lewis et al REIN Micro. HOPE AASK Year Conclusions about ACE inhibitors (ACE-I) 1992 ACE-I reduced both the rate of decline in GFR and the amount of albuminuria. 1993 In Type I diabetics, ACE-I reduced proteinuria, risk of doubling serum creatinine, and risk of ESRD+Death. But, ESRD alone was not reduced. 1997 In non-diabetics, ACE-I reduced proteinuria, risk of doubling serum creatinine, and risk of ESRD+Death. But, ESRD alone was not reduced. 2000 ACE-I reduced progression of proteinuria from normoalbuminuria to microalbuminuria and from microalbuminuria to macroalbuminuria. 2001 ACE-I was superior to amlodipine in reducing proteinuria among non-diabetic African Americans with hypertension and kidney disease. Slide Source Hypertension Online www. hypertensiononline. org
AASK: The African American Study of Kidney Disease and Hypertension • The AASK trial enrolled 1, 094 African American patients with renal disease at 21 US centers, and randomized them to receive one of 3 study drugs: – Ramipril – ACEI or – Amlodipine – CCB or – Metoprolol – Beta-blocker • Results – After adjustments for covariates, the risk reduction for ramipril vs amlodipine groups in the clinical composite outcomes (GFR, dialysis, or death) was 38% (p=0. 005) Agodoa L, et al. JAMA. 2001; 285(21): 2719 -2728. Slide Source Hypertension Online www. hypertensiononline. org
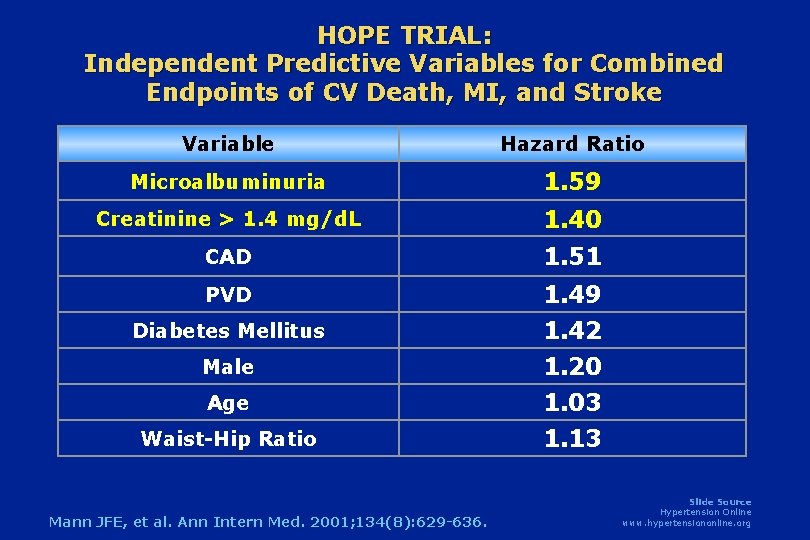
HOPE TRIAL: Independent Predictive Variables for Combined Endpoints of CV Death, MI, and Stroke Variable Hazard Ratio Microalbuminuria 1. 59 Creatinine > 1. 4 mg/d. L 1. 40 CAD 1. 51 PVD 1. 49 1. 42 1. 20 1. 03 1. 13 Diabetes Mellitus Male Age Waist-Hip Ratio Mann JFE, et al. Ann Intern Med. 2001; 134(8): 629 -636. Slide Source Hypertension Online www. hypertensiononline. org
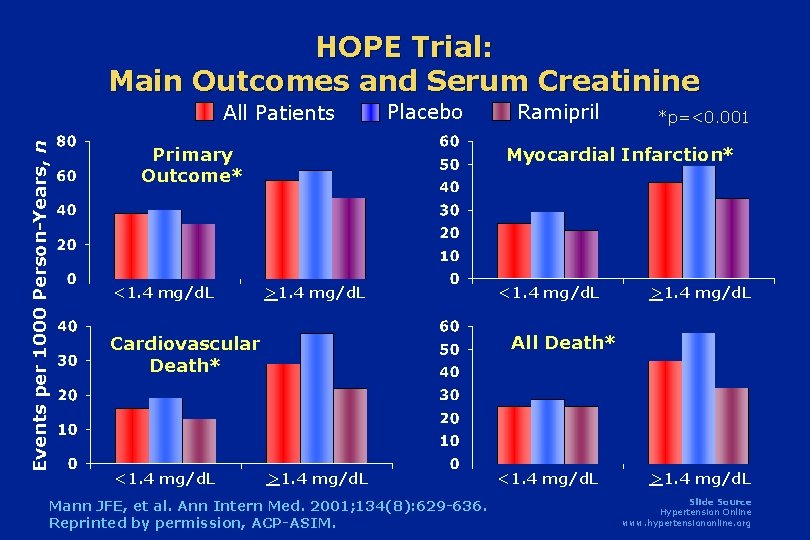
HOPE Trial: Main Outcomes and Serum Creatinine Events per 1000 Person-Years, n All Patients Placebo Primary Outcome* <1. 4 mg/d. L *p=<0. 001 Myocardial Infarction* >1. 4 mg/d. L <1. 4 mg/d. L >1. 4 mg/d. L All Death* Cardiovascular Death* <1. 4 mg/d. L Ramipril >1. 4 mg/d. L Mann JFE, et al. Ann Intern Med. 2001; 134(8): 629 -636. Reprinted by permission, ACP-ASIM. <1. 4 mg/d. L >1. 4 mg/d. L Slide Source Hypertension Online www. hypertensiononline. org
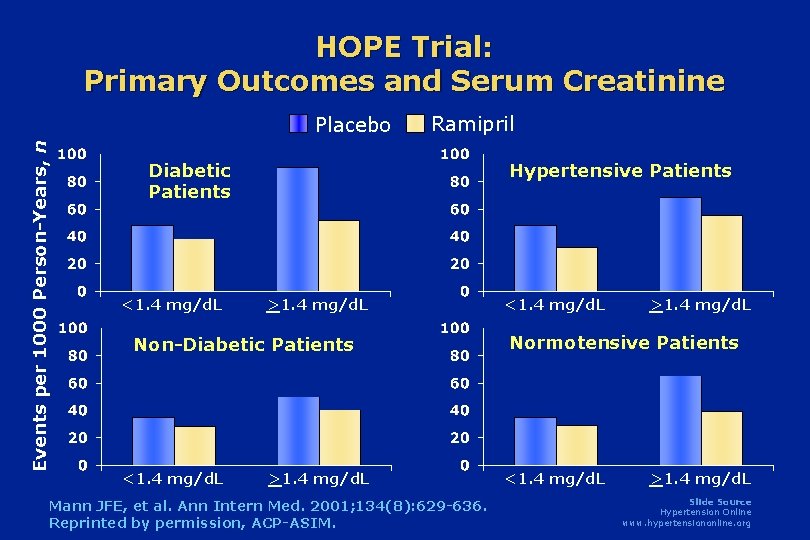
HOPE Trial: Primary Outcomes and Serum Creatinine Events per 1000 Person-Years, n Placebo Ramipril Hypertensive Patients Diabetic Patients <1. 4 mg/d. L >1. 4 mg/d. L Non-Diabetic Patients <1. 4 mg/d. L >1. 4 mg/d. L Mann JFE, et al. Ann Intern Med. 2001; 134(8): 629 -636. Reprinted by permission, ACP-ASIM. <1. 4 mg/d. L >1. 4 mg/d. L Normotensive Patients <1. 4 mg/d. L >1. 4 mg/d. L Slide Source Hypertension Online www. hypertensiononline. org
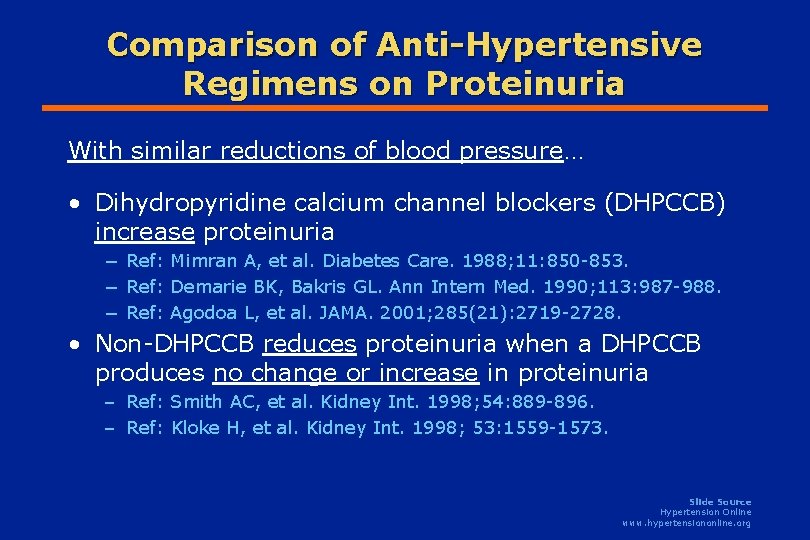
Comparison of Anti-Hypertensive Regimens on Proteinuria With similar reductions of blood pressure… • Dihydropyridine calcium channel blockers (DHPCCB) increase proteinuria − Ref: Mimran A, et al. Diabetes Care. 1988; 11: 850 -853. − Ref: Demarie BK, Bakris GL. Ann Intern Med. 1990; 113: 987 -988. − Ref: Agodoa L, et al. JAMA. 2001; 285(21): 2719 -2728. • Non-DHPCCB reduces proteinuria when a DHPCCB produces no change or increase in proteinuria – Ref: Smith AC, et al. Kidney Int. 1998; 54: 889 -896. – Ref: Kloke H, et al. Kidney Int. 1998; 53: 1559 -1573. Slide Source Hypertension Online www. hypertensiononline. org
Mean Changes in Albuminuria and Mean Arterial Pressure (MAP) in Studies of Patients with HTN and Proteinuria Other Diltiazem & All Dihydropyridine Verapamil Nifedipine ACE Inhibitors CCBs N=173 N=121 Kloke H, et al. Kidney Int. 1998; 53: 1559 -1573. N=111 N=723 Slide Source Hypertension Online www. hypertensiononline. org
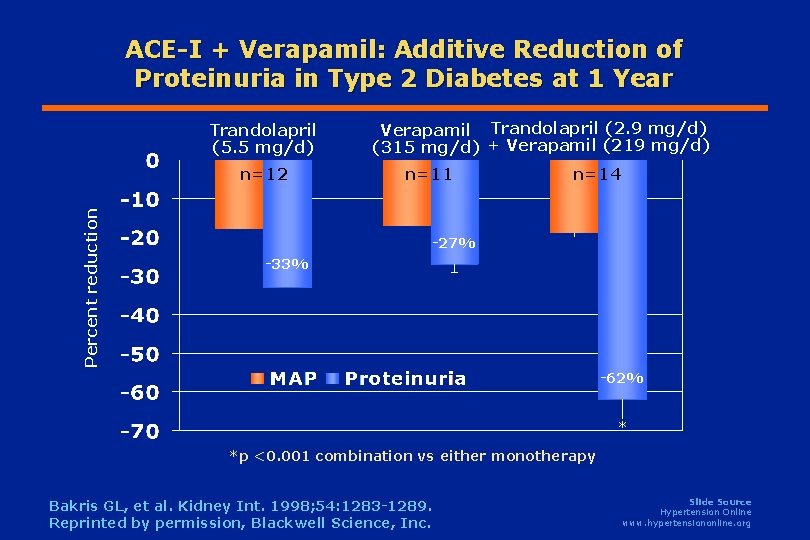
ACE-I + Verapamil: Additive Reduction of Proteinuria in Type 2 Diabetes at 1 Year Trandolapril (5. 5 mg/d) Percent reduction n=12 Verapamil Trandolapril (2. 9 mg/d) (315 mg/d) + Verapamil (219 mg/d) n=11 n=14 -27% -33% -62% * *p <0. 001 combination vs either monotherapy Bakris GL, et al. Kidney Int. 1998; 54: 1283 -1289. Reprinted by permission, Blackwell Science, Inc. Slide Source Hypertension Online www. hypertensiononline. org