Critical Care Aspects of COVID19 Vikram Mukherjee MD











- Slides: 21
Critical Care Aspects of COVID-19 Vikram Mukherjee, MD Director, Medical ICU, Bellevue Hospital Center Director, Special Pathogens Program, Bellevue Hospital Center
Clinical aspects: overall impressions so far • Presentation • Clinical Characteristics • Organ dysfunction • Outcomes
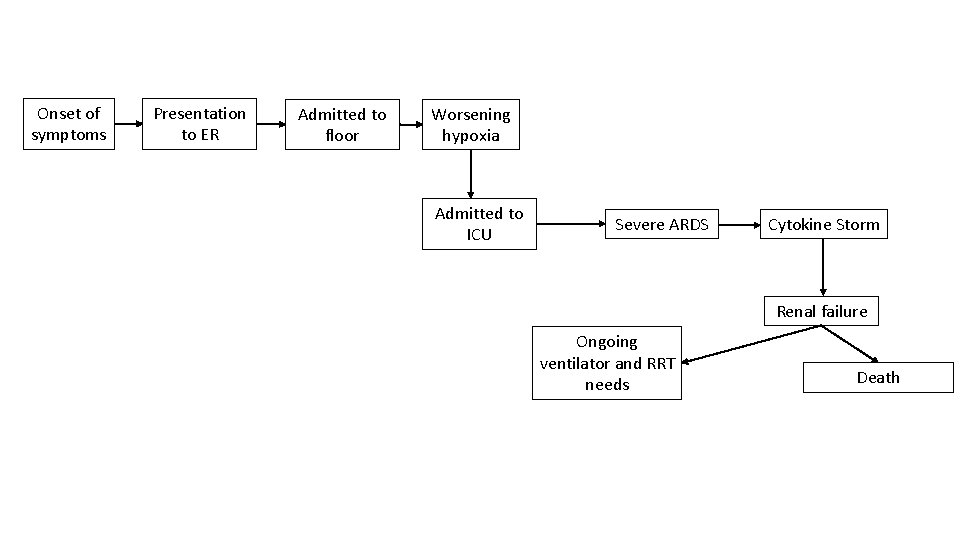
Onset of symptoms Presentation to ER Admitted to floor Worsening hypoxia Admitted to ICU Severe ARDS Cytokine Storm Renal failure Ongoing ventilator and RRT needs Death
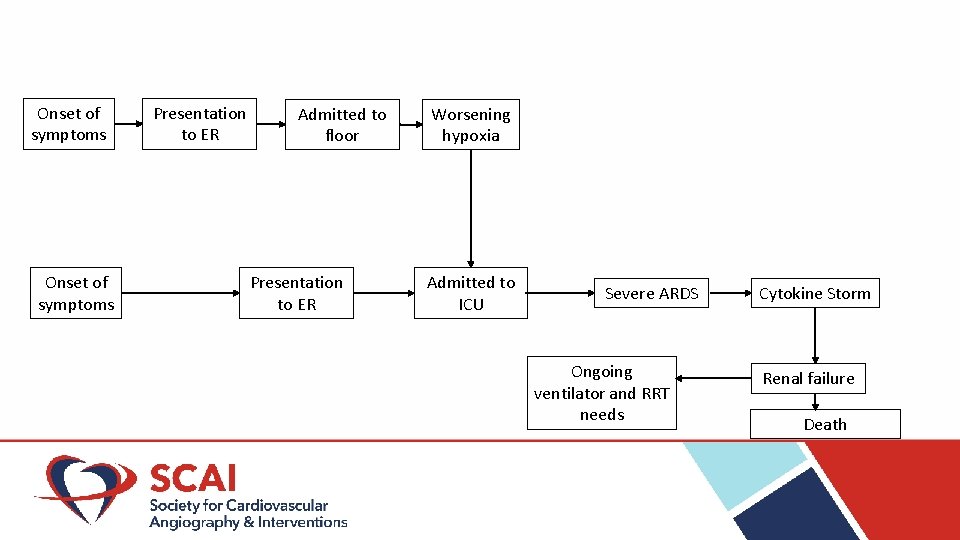
Onset of symptoms Presentation to ER Admitted to floor Presentation to ER Worsening hypoxia Admitted to ICU Severe ARDS Ongoing ventilator and RRT needs Cytokine Storm Renal failure Death
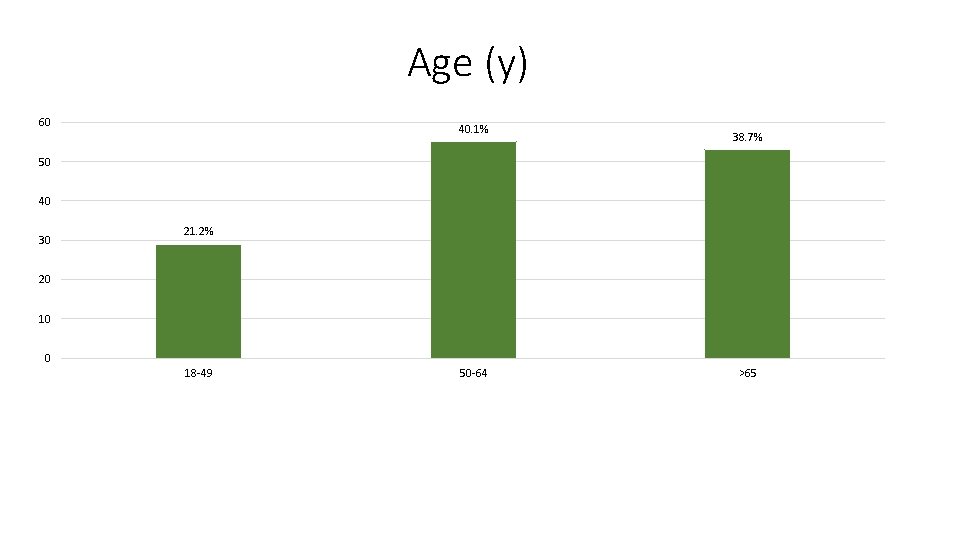
Age (y) 60 40. 1% 38. 7% 50 40 30 21. 2% 20 10 0 18 -49 50 -64 >65
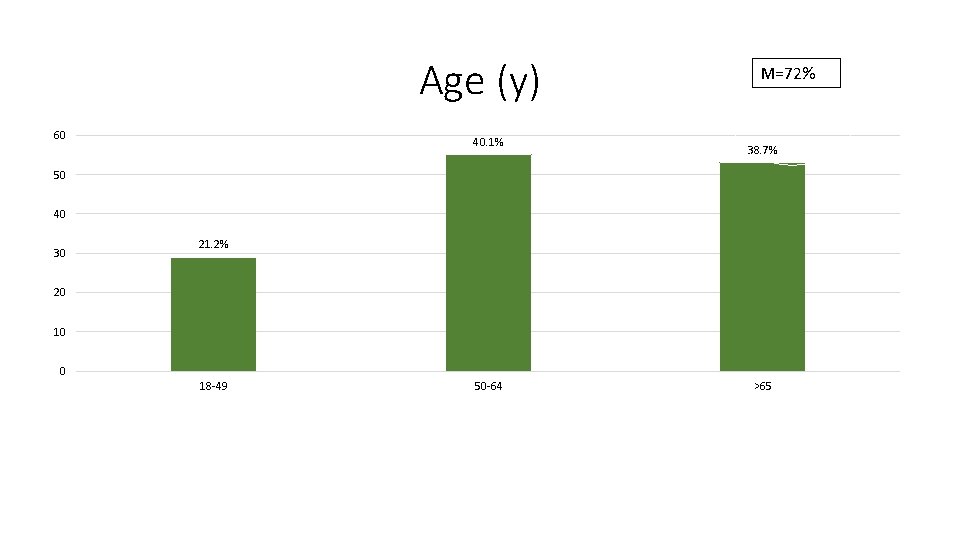
Age (y) M=72% 60 40. 1% 38. 7% 50 40 30 21. 2% 20 10 0 18 -49 50 -64 >65
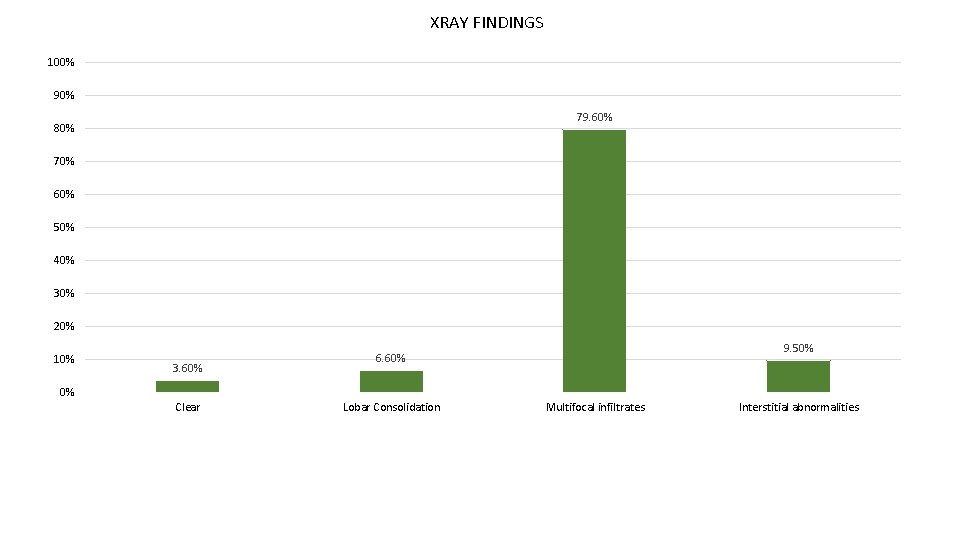
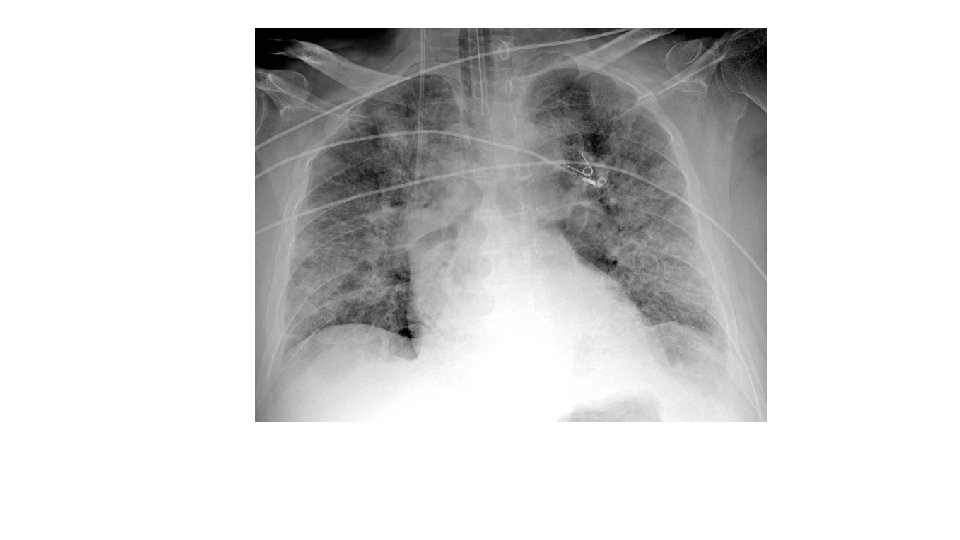
XRAY FINDINGS 100% 90% 79. 60% 80% 70% 60% 50% 40% 30% 20% 10% 3. 60% 9. 50% 6. 60% 0% Clear Lobar Consolidation Multifocal infiltrates Interstitial abnormalities
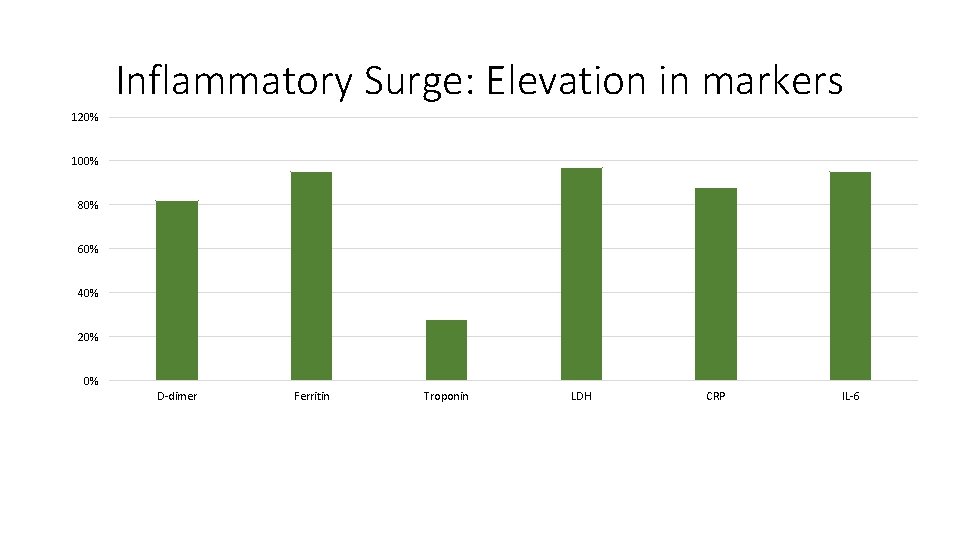
Inflammatory Surge: Elevation in markers 120% 100% 80% 60% 40% 20% 0% D-dimer Ferritin Troponin LDH CRP IL-6
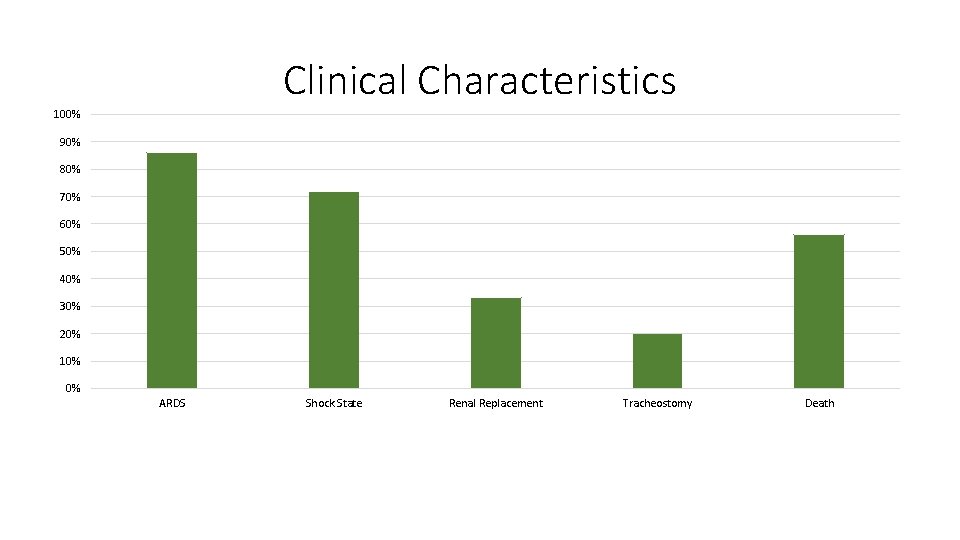
Clinical Characteristics 100% 90% 80% 70% 60% 50% 40% 30% 20% 10% 0% ARDS Shock State Renal Replacement Tracheostomy Death
Organ Dysfunction • ARDS • Cytokine Storm • Renal failure • Hypercoagulable state
Severe ARDS • Conventional management: • Trial of HFNC • Lung Protective Strategy • ARDSNET peep/fio 2 ladder, though some patients improve on lower PEEPs • Account for insensible losses and undetected hypovolemia • Recruitment • Attention to fluid balance • Trial of antibiotics • Neuromuscular blockade and RASS-4 sedation • i. NO for refractory hypoxia • Manual proning • ECMO
Severe ARDS • Other issues • CVL and A-line in most patients • Prefer left IJ CVL • • Many have substantial sedation requirements Many need neuromuscular blockade to achieve ventilator dysynchrony Tracheostomy team with protocolized bedside PDT Plaquenil/Azithromycin • Watch Qtc • Family updates
Cytokine Release Syndrome • Common to see the following a few days into ICU course • Recurring marked fevers in the absence of obvious infectious source • Tachycardia, tachypnea, diaphoresis • Elevated CRP, ferritin, LDH, IL-6 • Trend daily (except IL-6) • D-Dimer • Progression to renal failure • ~30% of our ICU patients are in acute renal failure requiring RRT • Unclear on how to mitigate • Steroids • Risks • Anti- IL 6 • No clear data on efficacy
Renal Replacement Therapy (RRT) • High incidence of AKI requiring RRT • Unclear etiology • Role of Peritoneal Dialysis in crisis situations
Hypercoagulability • High incidence of arterial and venous thromboembolism • Inflammatory milieu • Virus- induced endothelial damage • D-dimer as a surrogate of clot formation • Further studies ongoing to define risk & therapies
Other considerations • No evidence based treatment • Critical care support is the mainstay of therapy • Altered standard of care • Role of POCUS • Things move slowly • Has repercussions on management choices • Levels of sedation • Timing of invasive interventions
Need for a multidisciplinary approach • • • Tracheostomy team Proning team Palliative care team Procedure team Renal Replacement Therapy Team Site manager team
Questions
Disclosures