
Mikula Peter Department of Clinical Haematology Hospital in




- Slides: 7
Mikula Peter Department of Clinical Haematology Hospital in Havirov Czech Republic
Case history details l 63 - year-old man l 2002 dg. B-CLL with typical immunophenotype l l (Matutes 5/5), unmutated Ig. VH status, Binet B, large abdominal lymphadenopathy 10/02 – 3/03: 4 cycles of fludarabine-based treatment progressive dyspnoe, cough 2 weeks after the fourth cycle of chemotherapy no fever, no chest pain physical examination – dyspnoe with tachypnoe, absent breath sound in the lower half of the right hemithorax, normal blood pressure and pulse, normal heart examination, small peripheral lymphadenopathy, no hepatosplenomegaly, no edema
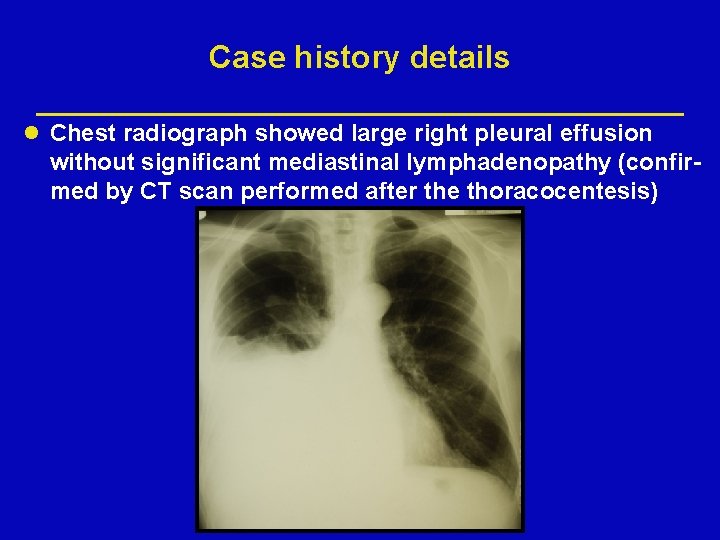
Case history details l Chest radiograph showed large right pleural effusion without significant mediastinal lymphadenopathy (confirmed by CT scan performed after the thoracocentesis)
Case history details l Laboratory values: • WBC 18000/ul (72% lymphocytes), haemoglobin 157 g/l, platelet count 240000/ul • normal serum urea, creatinine, transaminases, alkaline phosphatase, bilirubin, total protein and albumin levels • slightly elevated CRP 17. 9 mg/l • reduced level of serum triglycerides at 0. 31 mmol/l, cholesterol level was normal • blood coagulation tests were normal
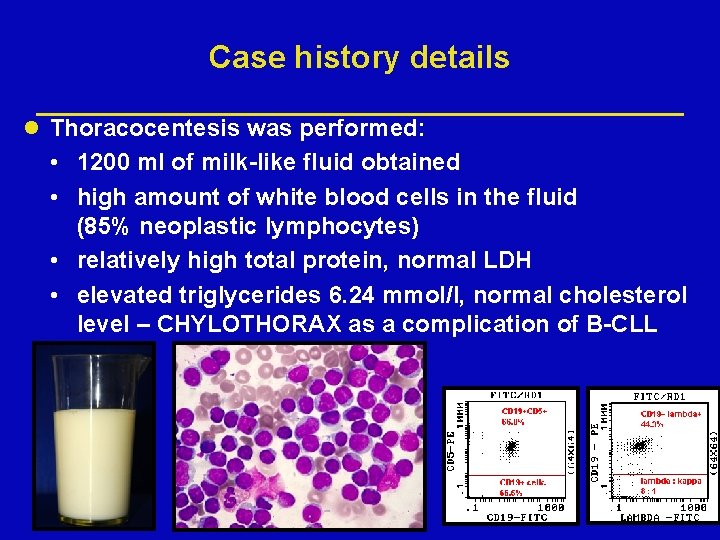
Case history details l Thoracocentesis was performed: • 1200 ml of milk-like fluid obtained • high amount of white blood cells in the fluid (85% neoplastic lymphocytes) • relatively high total protein, normal LDH • elevated triglycerides 6. 24 mmol/l, normal cholesterol level – CHYLOTHORAX as a complication of B-CLL
Treatment received l recurrence of chylothorax a few days after l l l thoracocentesis, thoracocentesis was repeated progressive malnutrition total parenteral nutrition needed intrapleural application of cyclophosphamide not effective intrapleural application of Corynebacterium parvum not effective pneumology expert consultation –chemical pleurodesis (talc) performed
Outcome l no recurence of chylothorax following talc pleurodesis l fludarabine-based chemotherapy completed, total 6 cycles l partial remission of B-CLL achieved l 2003 – 2006 without progression of B-CLL l 2006 death caused by renal carcinoma (secondary malignancy)







