
Y L N 2018 Clinical Practice Guidelines O




















- Slides: 34
Y L N 2018 Clinical Practice Guidelines O E S U L A N Retinopathy SO R E P Chapter 30 Filiberto Altomare MD FRCSC Amin Kherani MD FRCSC Julie Lovshin MD FRCPC
Disclaimer All Content contained on this slide deck is the property of Diabetes Canada, its content suppliers or its licensors as the case may be, and is protected by Canadian and international copyright, trademark, and other applicable laws. Diabetes Canada grants personal, limited, revocable, non-transferable and non-exclusive license to access and read content in this slide deck for personal, non-commercial and not-for-profit use only. The slide deck is made available for lawful, personal use only and not for commercial use. The unauthorized reproduction, distribution of this copyrighted work is not permitted. For permission to use this slide deck for commercial or any use other than personal, please contact guidelines@diabetes. ca
2018 Diabetes Canada CPG – Chapter 30. Retinopathy 2018 Key Changes • New information on Y • The effectiveness of local intraocular L N O pharmacological therapies in. Eimproving vision and reducing the level of diabetic US retinopathy L A N O S R E P PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Checklist üSCREEN regularly O E Y L N üDELAY onset and progression with glycemic and S U L BP control ± fibrate A R E P N O S üTREAT established disease with laser photocoagulation, intra-ocular injection of medications or vitreoretinal surgery BP, blood pressure PERSONAL USE ONLY
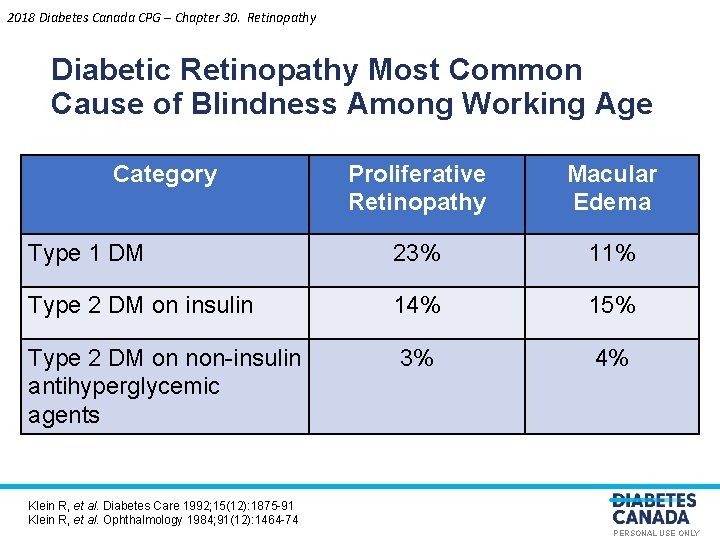
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Diabetic Retinopathy Most Common Cause of Blindness Among Working Age Category Proliferative Y L Retinopathy N O E Type 1 DM S U L 23% 11% 14% 15% 3% 4% A N O S R PE Type 2 DM on insulin Type 2 DM on non-insulin antihyperglycemic agents Macular Edema Klein R, et al. Diabetes Care 1992; 15(12): 1875 -91 Klein R, et al. Ophthalmology 1984; 91(12): 1464 -74 PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Increases Morbidity and Mortality • Visual loss is associated with: NLY O • • Increased falls More hip fractures L A N E S U 4 -fold increase. Sin. Omortality R E P (in type 1 diabetes) Early death PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Forms of Retinopathy 1. Macular Edema O E Y L N S U L 2. Non-proliferative and A N O Proliferative S R E P 3. Retinal Capillary Closure PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Macular Edema • Diffuse or focal vascular leakage at the macula O E Y L N S U L A N O S R PE PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Non-proliferative/Proliferative Retinopathy • Blood vessel changes • Non-proliferative O E Y L N S U L – Microaneurysms, intraretinal hemorrhage, vascular tortuosity A and vascular malformation ON S R PE • Proliferative – Abnormal vessel growth PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Retinal Capillary Closure • Seen with fluorescein angiography O E Y L N S U L A N O • Potentially blinding. S R E complication P • Currently no treatment options PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Screening for Retinopathy O E Y L N S U L A N O S R PE PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy (cont’d) O E Y L N S U L A N O S R PE PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Risk Factors for Progression • Longer duration of diabetes Y • Elevated A 1 C L N O • Hypertension E S U L • Dyslipidemia A N O • Low hemoglobin level S R E P (with type 1 diabetes) • Pregnancy • Proteinuria • Severe retinopathy itself PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Delay of the Disease 1. Glycemic control: target A 1 C ≤ 7% O E Y L N S U 2. Blood pressure control: target BP <130/80 L A N O S R E P 3. Lipid-lowering therapy: Fibrates have been shown to decrease progression and may be considered PERSONAL USE ONLY
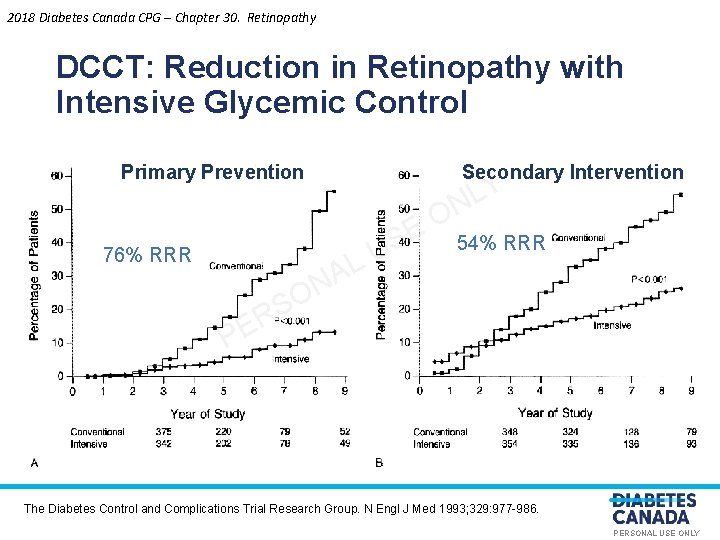
2018 Diabetes Canada CPG – Chapter 30. Retinopathy DCCT: Reduction in Retinopathy with Intensive Glycemic Control Primary Prevention Secondary Intervention O E S U L 76% RRR Y L N 54% RRR A N O S R PE The Diabetes Control and Complications Trial Research Group. N Engl J Med 1993; 329: 977 -986. PERSONAL USE ONLY
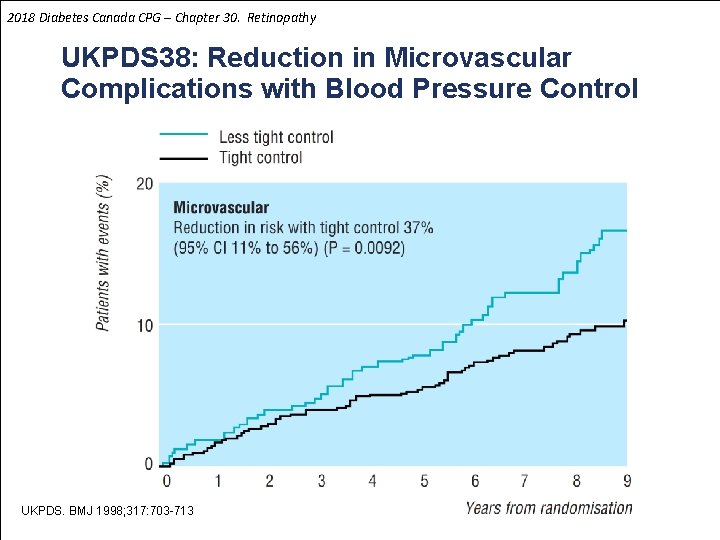
2018 Diabetes Canada CPG – Chapter 30. Retinopathy UKPDS 38: Reduction in Microvascular Complications with Blood Pressure Control O E Y L N S U L A N O S R PE UKPDS. BMJ 1998; 317: 703 -713 PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy UKPDS 38: Reduction in Retinopathy with Blood Pressure Control O E Y L N S U L A N O S R PE UKPDS. BMJ 1998; 317: 703 -713 PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy ACCORD Eye: Glycemic control and Combo of fenofibrate and simvastatin reduced progression Effect Odds Ratio Glycemia 0. 67 (0. 51 - 0. 87) LY 0. 0025 Lipid 0. 60 (0. 42 S - 0. 86) 0. 0056 BP 1. 23 ON 95% CI N O E U L A (0. 84 - 1. 79) P-value 0. 29 S R Intensive glycemic PE control and combination of fenofibrate and simvastatin, but not intensive blood pressure control, reduced the rate of progression of diabetic retinopathy in this older, high-risk population. ACCORD Study Group. N Engl J Med 2010; 363(3): 233 -244. PERSONAL USE ONLY
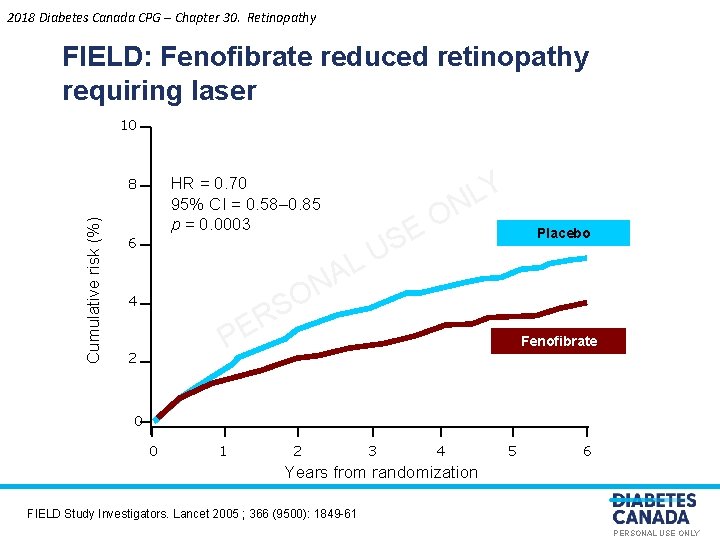
2018 Diabetes Canada CPG – Chapter 30. Retinopathy FIELD: Fenofibrate reduced retinopathy requiring laser 10 HR = 0. 70 95% CI = 0. 58– 0. 85 p = 0. 0003 Cumulative risk (%) 8 6 L A N O E Y L N US Placebo O S R E P 4 2 Fenofibrate 0 0 1 2 3 4 5 6 Years from randomization FIELD Study Investigators. Lancet 2005 ; 366 (9500): 1849 -61 PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Diabetic Retinopathy CAN be Treated 1. Pan-retinal photocoagulation laser therapy Y L non-proliferative or • Reduces blindness by 90% in severe N O proliferative retinopathy SE U L Apharmacologic intervention 2. Local (intra-ocular) N O S VEGF antagonists R E P • Aflibercept, ranibizumab, bevacizumab (off-label use in Canada) improve vision 3. Surgical intervention vitrectomy PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Sight-threatening Retinopathy MUST be Y and blood L üPrevented with good blood glucose N O pressure control (±SE fenofibrate) U L A üDetected. Nthrough screening O S R therapy, anti-VEGF medications üTreated with laser E P or vitrectomy to save VISION PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 1 1. In individuals >15 years of age with type 1 diabetes, screening and evaluation for retinopathy should be Y vision care L performed annually by an experienced N O E professional (optometrist or ophthalmologist) starting S Udiabetes [Grade A, Level 1] 5 years after the onset of L A N for children and adolescents (for screening recommendation O S <15 years with type. R 1 diabetes see Type 1 Diabetes in Children E P and Adolescents chapter; for screening recommendations for pregnant women, see Diabetes and Pregnancy chapter) PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 2 2. 2018 In individuals with type 2 diabetes, screening and evaluation for diabetic retinopathy should be Y L performed by an experienced vision. Ncare professional O (optometrist or ophthalmologist) E at the time of S U A, Level 1]. The interval diagnosis of diabetes [Grade L A should be tailored to the N for follow-up assessments O S severity of the retinopathy [Grade D, Consensus]. In R E those with no. Por minimal retinopathy, the recommended interval is 1 -2 years [Grade A, Level 1] (for screening recommendations for children and adolescents with type 2 diabetes see Type 2 Diabetes in Children and Adolescents chapter) PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 3 2018 3. Screening for diabetic retinopathy should be performed by an experienced vision Y care L N professional (optometrist or ophthalmologist), either O E of retinal S in person or through interpretation U L photographs taken through dilated pupils [Grade A, A N O Level 1] or undilated. Spupils with high-resolution ultra. R E wide field imaging P [Grade D, Consensus] PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 4 2018 4. Results of eye examinations and the follow-up interval and plan should be clearly communicated to all Y L N members of the diabetes health-care team to promote O E S optimal care [Grade D, Consensus] U L A N O S R E P PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 5 5. To prevent the onset and delay the progression of Y should be diabetic retinopathy, people with diabetes L N O treated to achieve optimal control E of BG [Grade A, S U A, Level 1 A for type 2 Level 1 A for type 1 diabetes; Grade L A diabetes] and BP [Grade N A, Level 1 A for type 2 diabetes; O Sfor type 1 diabetes] Grade D, Consensus R PE BG, blood glucose; BP, blood pressure PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 6 6. Though not recommended for CVD prevention or treatment, fenofibrate, in addition. Nto LYstatin therapy, O may be used in people with type E 2 diabetes to slow S the progression of established L U retinopathy [Grade A, Level 1 A] A N O S R PE CVD, cardiovascular disease PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 7 7. Individuals with sight-threatening diabetic Yqualified retinopathy should be assessed by a L N O ophthalmologist and/or retina E specialist [Grade D, S U intervention [Grade A, Consensus]. Pharmacological L Aand/or vitrectomy [Grade A, N Level 1 A], laser therapy O S Rused to manage the diabetic Level 1 A] may be E P retinopathy PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Recommendation 8 8. Visually disabled people should be referred for low. Y[Grade D, vision evaluation and rehabilitation L N O E Consensus] S U L A N O S R PE PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Key Messages • Regular screening is important for early detection of treatable diabetic retinopathy. Screening intervals for Y individual’s L diabetic retinopathy vary according to the N O age and type of diabetes E S U Lreduces the onset and • Optimal glycemic control A N progression of sight-threatening diabetic retinopathy O S R E • Local intraocular P pharmacological therapies have the potential to improve vision and reduce the level of retinopathy PERSONAL USE ONLY
2018 Diabetes Canada CPG – Chapter 30. Retinopathy Key Messages for People with Diabetes • Diabetic retinopathy involves changes to retinal blood vessels that can cause them to bleed or leak fluid, distorting vision Y L N • With good glycemic control, regular eye exams and early O E treatment, the risk of vision loss is. Sreduced U L • Diabetic retinopathy often goes A unnoticed until vision loss N Owith diabetes should get a occurs, therefore people S R eye exam regularly. Discuss the comprehensive dilated E P recommended frequency with your diabetes healthcare team and experienced vision care professionals (optometrists or ophthalmologists) • Diabetic retinopathy can be treated with several therapies used alone or in combination PERSONAL USE ONLY
Visit guidelines. diabetes. ca O E Y L N S U L A N O S R PE PERSONAL USE ONLY
Or download the App O E Y L N S U L A N O S R PE PERSONAL USE ONLY
Diabetes Canada Clinical Practice Guidelines LY www. guidelines. diabetes. ca – for. Nhealth-care O providers E S U L A N O 1 -800 -BANTING (226 -8464) S R E P www. diabetes. ca – for people with diabetes PERSONAL USE ONLY