
www rrnmf com Plasmapheresis Treatment for Myasthenia Gravis









- Slides: 11
www. rrnmf. com Plasmapheresis Treatment for Myasthenia Gravis Richard J. Barohn, MD Chair, Department of Neurology Gertrude and Dewey Ziegler Professor of Neurology University Distinguished Professor Vice Chancellor for Research University of Kansas Medical Center Kansas City, KS
Plasmapheresis for MG • Directly removes humoral factors such as autoantibodies, immune complexes, complement and other nonspecific inflammatory mediators • Remove 3 -6 liters of plasma over several hours. Replace with albumin or purified protein fraction (PPF). • Indications for MG: crises pre-thymectomy severe MG (not in crises) when initiating or increasing oral immunosuppressive drugs chronic Rx
Early Reports of Plasmapheresis for MG 1. Dau PC, Lindstrom JM, Cassel CK, Denys EH, Shev EE, Spitler LE: Plasmapheresis and immunosuppressive drug therapy in myasthenia gravis. N Engl J Med 297: 1134, 1977 • 5 pts 2. Newsom-Davis J, Pinching AJ, Vincent A, Wilson SG: Function of circulating antibody to acetylcholine receptor in myasthenia gravis: Investigation by plasma exchange. Neurology 28(3): 266 -272, 1978 • 8 pts 3. Newsom-Davis J, Wilson SG, Vincent A et al: Long term effects of repeated plasma exchange in myasthenia gravis. Lancet 1: 464, 1979 • 13 pts 4. Olarte MR, Schoenfeldt RS, Penn AS et al: Effect of plasmapheresis in myasthenia gravis, 1978 -1980. Ann NY Acad Sci 377: 725, 1981 • 21 pts 5. Keesey J, Buffkin D, Kebo D, et al: Plasma exchange alone as therapy for myasthenia gravis. Ann NY Acad Sci 377: 729, 1981 • 3 pts
MG: Plasma Exchange • First successful reports in late 1970’s • Antibody levels fall but response does not correlate with starting titers • Improvement occurs in days • Improvement may be seen even if serum antibody is absent • All small case series • No randomized trial done against placebo or no PE
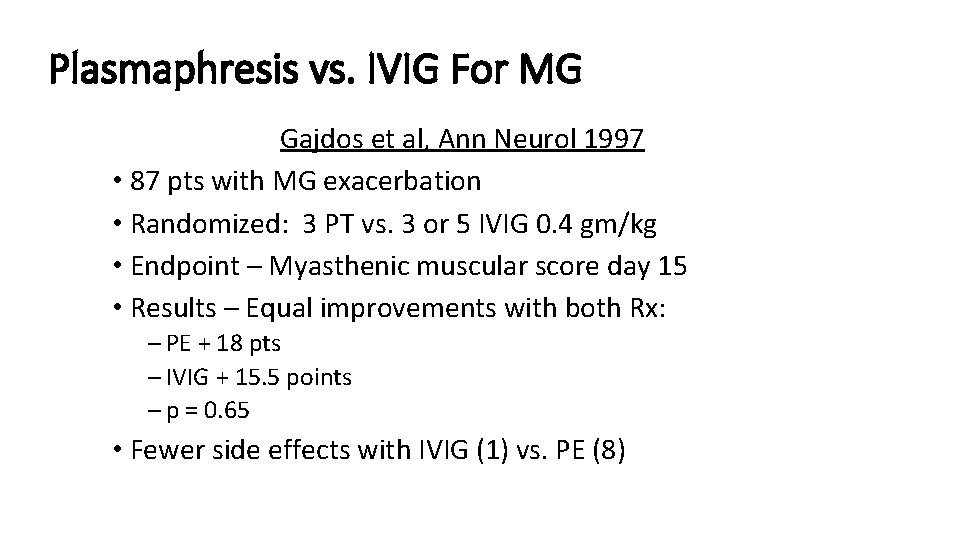
Plasmaphresis vs. IVIG For MG Gajdos et al, Ann Neurol 1997 • 87 pts with MG exacerbation • Randomized: 3 PT vs. 3 or 5 IVIG 0. 4 gm/kg • Endpoint – Myasthenic muscular score day 15 • Results – Equal improvements with both Rx: – PE + 18 pts – IVIG + 15. 5 points – p = 0. 65 • Fewer side effects with IVIG (1) vs. PE (8)
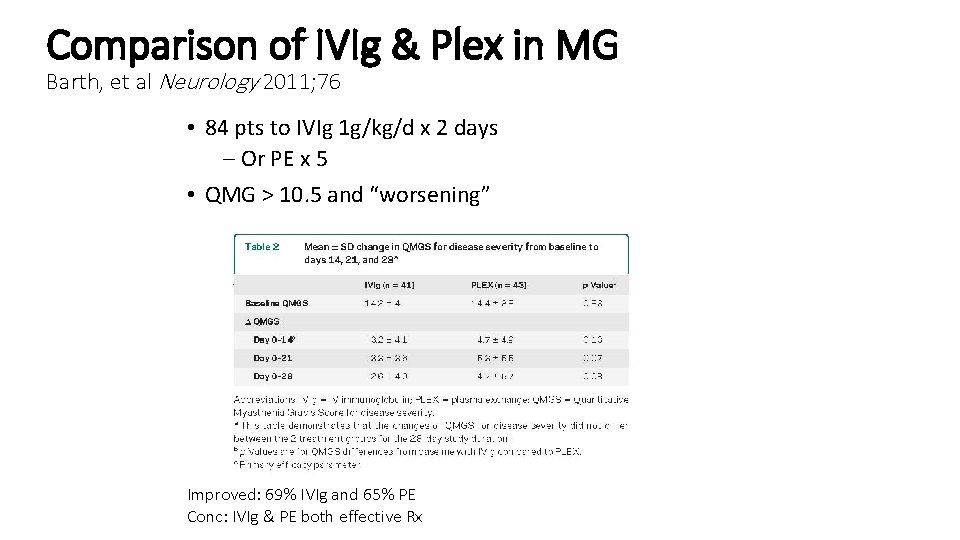
Comparison of IVIg & Plex in MG Barth, et al Neurology 2011; 76 • 84 pts to IVIg 1 g/kg/d x 2 days – Or PE x 5 • QMG > 10. 5 and “worsening” Improved: 69% IVIg and 65% PE Conc: IVIg & PE both effective Rx
Pheresis for MG: Recommendation: Level U (Unknown) Neurology 2011; 76: 294 -300
Plasmapheresis Rx for MG HOW MUCH? • 4 -6 Exchanges of 3 -5 Liters of Plasma • Can be Daily or QOD • However, No Exact Science For # Exchanges or Amount Removed in MG • Often Depends on How Pt Tolerates PE and How Much Can Be Removed
Plasmapheresis Rx for MG LIMITATIONS • Trained technician • Equipment • IV Access - Often Requires Large Double-Lumen Catheter • Complications: Pneumothorax, Hypotension, Sepsis, Pulmonary Embolism • Expensive • Benefit Lasts Several Weeks
Plasmapheresis: The Problem of Access • Periph IV hard to access • Chron IJ line – 1 mo to 12 mo infection • Ports – We tried Vortex Dx – Can’t take pressure • AV fistulas – Clot – Cosmetic
A-V Fistulas for Pheresis