
UROLOGY mi Ulli DEPARTMENT Ente Ecclesiastico Ospedale Generale






























- Slides: 52
UROLOGY mi Ulli DEPARTMENT Ente Ecclesiastico Ospedale Generale Regionale “F. Miulli” Acquaviva delle Fonti Struttura Complessa di Urologia Centro di Chirurgia Robotica - Laparoscopica – Mininvasiva Direttore: Giuseppe Mario Ludovico CHIRURGIA ROBOTICA E QUALITA’ DI VITA Giuseppe Mario Ludovico Martina Franca 15 dicembre 2012
UROLOGY mi Ulli DEPARTMENT The most updates European Association of Urology (EAU) guidelines report about: bilateral nerve-sparing radical retropubic prostatectomy (BNSRP) unilateral nerve-sparing radical retropubic prostatectomy (UNSRP) represent the recommended approach of choise in all men with both a normal preoperative erective-function (EF) and organ confined disease Heidenreich A. , Bellmunt J, et all; EAU GUIDELINES; 2011
UROLOGY mi Ulli DEPARTMENT Since the introduction of Patrick Walsh’s tecnique, open radical prostatectomy (RP) is the standard surgical treatment of localised Pca. Walsh PC: J Urol 2000 . . . WHICH ARE THE OUTCOMES AFTER RADICAL PROSTATECTOMY FOR A LOCALIZED PROSTATE CANCER ?
UROLOGY mi Ulli DEPARTMENT The current robotic literature reveals 12 -months potency outcomes favorable (70 to 80%) with the robotic approach and comparable to even longer term (24 months) data of expert open series (46% to 54%). Berryhill R. Jr, Jhaveri J et al: Urology 2008 Ficarra V. , Novara G. et al: Eur Urol. 2012 Box GN Ahlering TE: Curr. Opin. Urol 2006 3 -month potency outcomes (46% to 54%) seem to suggest the relatively rapid return of erectile function, Box GN Ahlering TE: Curr. Opin. Urol 2009
UROLOGY mi Ulli DEPARTMENT Comprehensive review including RRP series pubblished between 1990 and 2005 showed a wide range of recovery of erectile function after a minimun follow up of 12 mo. , in patients who received bilateral NSRRP showing potency rates ranging from 31% to 86%. Dubbelman YD, Dohle GR, et all: Eur Urol 2006 Comprehensive review including RRP series pubblished before 2005 showed that the prevalence of erectile dysfunction according to difference definition was 47, 8% after RRP and 24, 2% after RARP. The cumulative analysis showed a statistically significant advantage in favour of RARP ( OR : 2, 84; 95% CI: 1. 48 -5, 43; p= 0, 002). Ficarra V, Novara G et al: BJU Int, Di Pierro GB, Baumeister P et al: Eir. Urol. , Kim Sc, Song C: Eur urol. , Rocco B. , Matei DV et al: BJU Int, 2009 2011 2009
UROLOGY mi Ulli DEPARTMENT The real problem isn’t this: If the open radical prostatectomy is better than robotic radical prostatectomy, we’ll obtain or not nerve preservation but this one: How we’ll perform a TRUE NERVE SPARING PROCEDURE? or. . Where are really the NVBs?
UROLOGY mi Ulli DEPARTMENT New anatomic concepts distribution and course of the cavernous nerves, New anatomic tecniques anterior incision of the periprostatic fascia inter- or intrafascial surgical planes New devices thermal or athermal dissection of the neurovascular bundles i. e. monopolar vs bipolar vs clips, cold dissection, countertraction Surgeon’s experience case-load, high volume centre, learning curve Costs
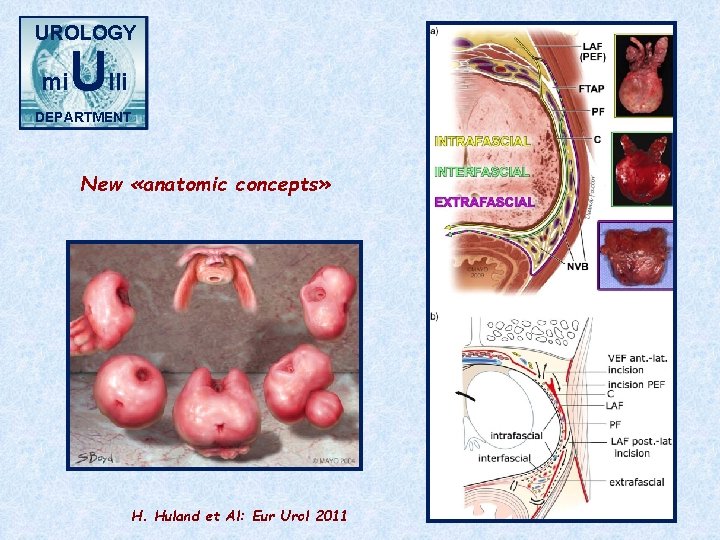
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT Initially, Walsh’s description of the anatomic nerve-sparing tecnique in 1982 was based on the concept that the neurovascular bundles (NVBs) are situated posterolaterally and simmetrically to the prostate in the space among the levator fascia, prostatic fascia and Denonvillier’s fascia. Walsh PC, Donker PJ et all. : J. Urol. , 1982 In the last decade, deeper insight into the distribution and course of the cavernous nerves showed that, especially in men with a small prostate, NVBs may have either an anterolateral position or, rarely, an asymmetric posterolateral position on one side while lateral on the other. Menon M. , Tewari A. et al: J Urol 2003 Kiyoshima K. Yokomizo A. et al: Jpn J Clin Oncol, 2004 Tewari A, Rao S. et al: BJU Int, 2008
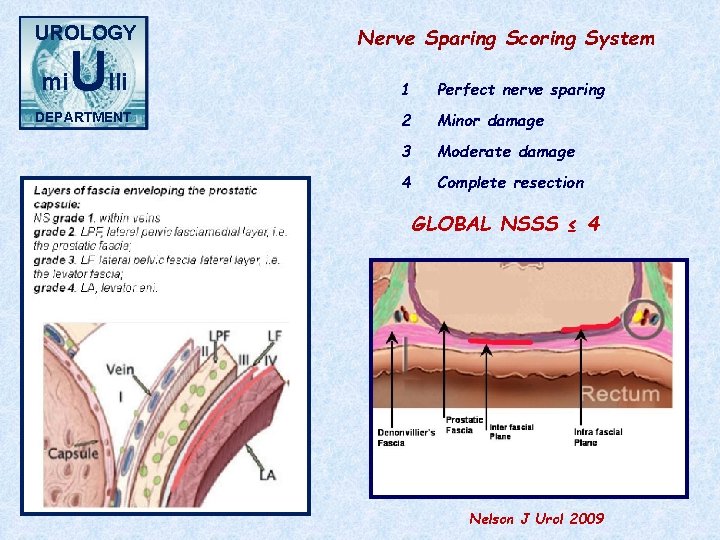
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT These new anatomic concepts supported the incision of the periprostatic fascia anteriorly and parallel to the NVBs preserves cavernous nerve located at both the posterolateral and anterolateral surfaces of the prostate. Menon M. , Tewari A. et al: J Urol 2003 The multiple compartments that could be developed from the levator fascia to the prostate capsula by entering fascial planes during surgery explain the possibility of realizing a different extension of the nerve-sparing procedure according to cancer risk stratification and patient preoperative characteristics Tewari A. , Rao S. et al: BJU Int, 2008
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT Graefen et al and Montorsi et al demonstred the feasibility of the anterior incision of the periprostatic fascia and the possibility of realizing an interfascial or intrafascial surgical plane in open surgery. Graefen M. Walz J. et al: Eur Urol, 2006 Montorsi F. , Salonia A. et al: Eur Urol, 2005 The influence of anterior periprostatic nerve tissue suggests the use of a more anterior incision of the fascia, as Briganti experience Briganti A. , Salonia A. et al. : EAU-EBU Update, 2006 In order to spare these anterior fibres, the surgeon should choose a more ventral incision in the mid-part as suggested similarly by Montorsi et al. with an even higher incision at the 11 -1 o'clock position Montorsi F. Salonia A. et al. : Eur Urol. , 2005
UROLOGY mi Ulli DEPARTMENT But what is the exact distribution of periprostatic autonomic nerves ?
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT The largest percentage of periprostatic nerves is located in the dorsolateral position Periprostatic nerve distribution is variable, with a high percentage of nerves in the ventrolateral and dorsal positon in some cases The periprostatic nerve density decrease to the base towards the apex A significant portion of nerves of the NVB appears to branch into the prostate The highest density of capsular nerves is found at the apex Ganzer R. , Blana A. , et coll: Eur. Urol, 2008
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT Therefore, it is recommended that the surgeon focus on nerve preservation in particular at the apex, starting in the anterior at the mid section as well as the common posterolateral course Sievert KD. , Hennenlotter J. et al. : Eur Urol. , 2010 . . . the neurovascular bundle appears to be a complex confluence of nerves passing through the posterolateral main track in different inclined courses without forming a distinct bundle of parallel nerves
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT The role of accessory pudendal artery (APAs) in normal erectile function, and their impact on postoperative potency and eventually on continence has become a topic of increasing interest. Some studies have shown that, when present, APAs may often represent the only arterial supply to the penis Myers RP. : Urol. Clin North Am. , 2001 Breza J. , Abeserif SR. Et al. : J. Urol. , 1989
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT Iacono e Giannella demonstrated that progressive fibrosis in the corpora cavernosa after RP results from denervation and/or an ischemic process, which is caused in turn by the ligation of anomalous pudendal artery branches or of venous plexuses that drain to or from the corpora cavernosa. Fibrosis and the subsequent loss in elasticity and function of erectile tissue probably togheter cause erectile dysfunction Iacono F. , Giannella R. et coll. : J of Urol 2005
UROLOGY mi New «anatomic concepts» Ulli DEPARTMENT The Mayo clinic group emphasized in open bilateral neurovascular bundle preservation (BNVBP) during RRP the potential role of: q HAR, i. e high anterior release of the levator fascia and NVBs q surgical loupe magnification (x 4, 3) Hubanks JM, Myers RP et al: Eur Urol, 2012
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT «When you perform an intrafascial nerve -sparing approach or “veil of aphrodite” tecnique, you make a high lateral incision of the periprostatic fascia in order to preserve the nerve tissue within the periprostatic fascia in the lateral and ventrolateral position » Ganzer R. , Blana A. , et coll: Eur. Urol, 2008
UROLOGY mi Ulli New «anatomic concepts» DEPARTMENT Shikanov et al analyzed the impact of the extension of the nerve-sparing procedure, comparing pts that received intrafascial nerve sparing versus extrafascial nerve preservation observing a significant advantages in term of mean potency rate at 3, 6 and 12 in favour of intrafascial nerve sparing procedures Shikanov S. , Woo J et al: Urology 2009
UROLOGY mi Ulli DEPARTMENT New «anatomic concepts» H. Huland et Al: Eur Urol 2011
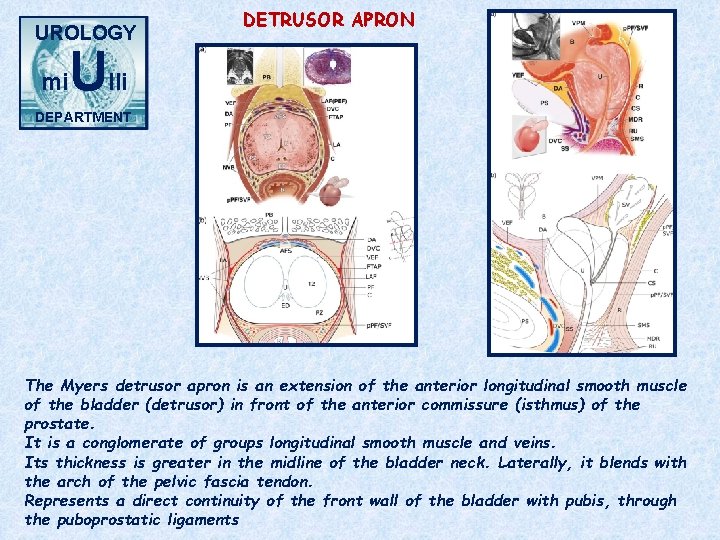
UROLOGY mi DETRUSOR APRON Ulli DEPARTMENT The Myers detrusor apron is an extension of the anterior longitudinal smooth muscle of the bladder (detrusor) in front of the anterior commissure (isthmus) of the prostate. It is a conglomerate of groups longitudinal smooth muscle and veins. Its thickness is greater in the midline of the bladder neck. Laterally, it blends with the arch of the pelvic fascia tendon. Represents a direct continuity of the front wall of the bladder with pubis, through the puboprostatic ligaments
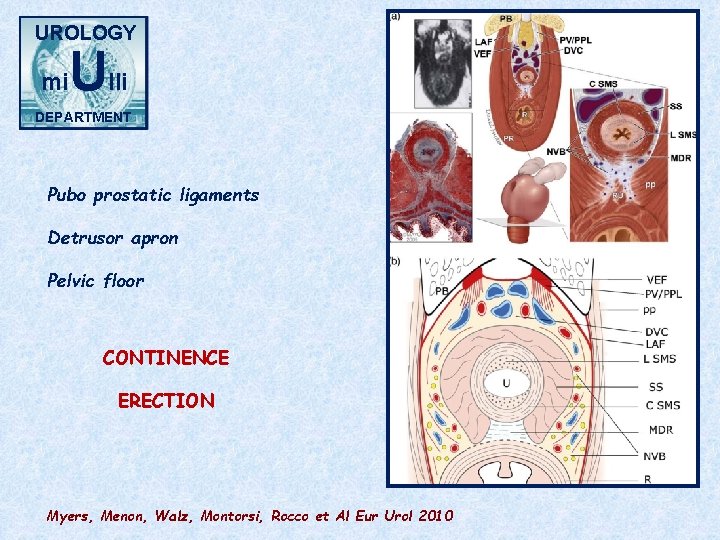
UROLOGY mi Ulli DEPARTMENT Pubo prostatic ligaments Detrusor apron Pelvic floor CONTINENCE ERECTION Myers, Menon, Walz, Montorsi, Rocco et Al Eur Urol 2010
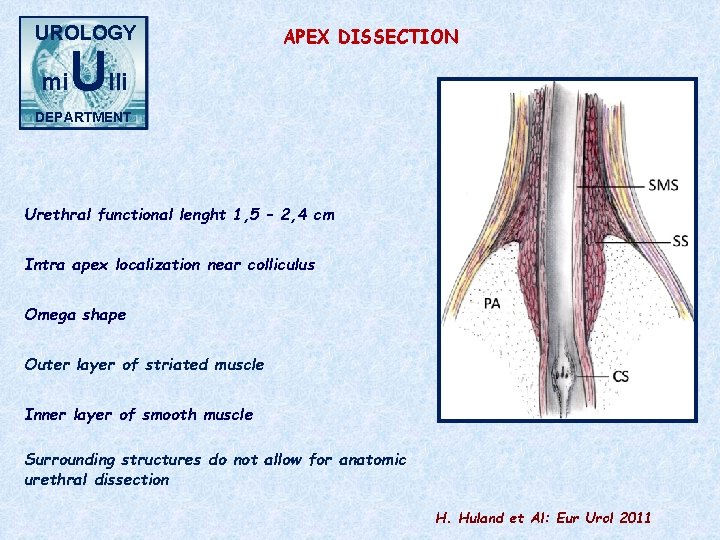
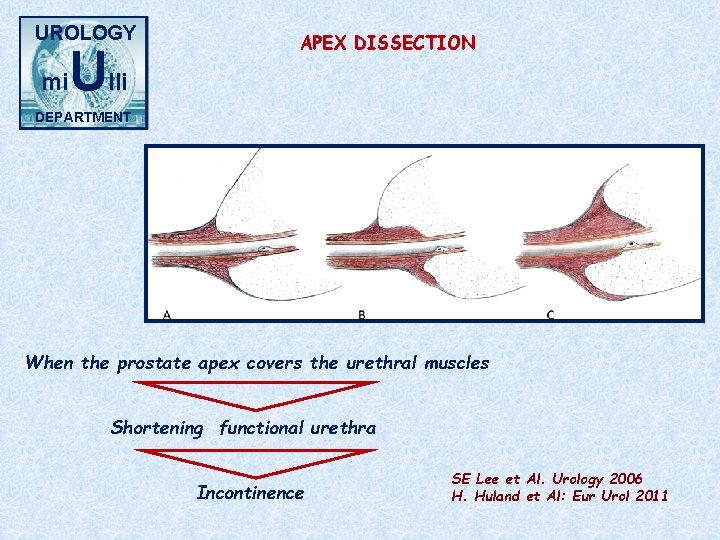
UROLOGY mi Ulli APEX DISSECTION DEPARTMENT Urethral functional lenght 1, 5 – 2, 4 cm Intra apex localization near colliculus Omega shape Outer layer of striated muscle Inner layer of smooth muscle Surrounding structures do not allow for anatomic urethral dissection H. Huland et Al: Eur Urol 2011
UROLOGY mi Ulli APEX DISSECTION DEPARTMENT When the prostate apex covers the urethral muscles Shortening functional urethra Incontinence SE Lee et Al. Urology 2006 H. Huland et Al: Eur Urol 2011
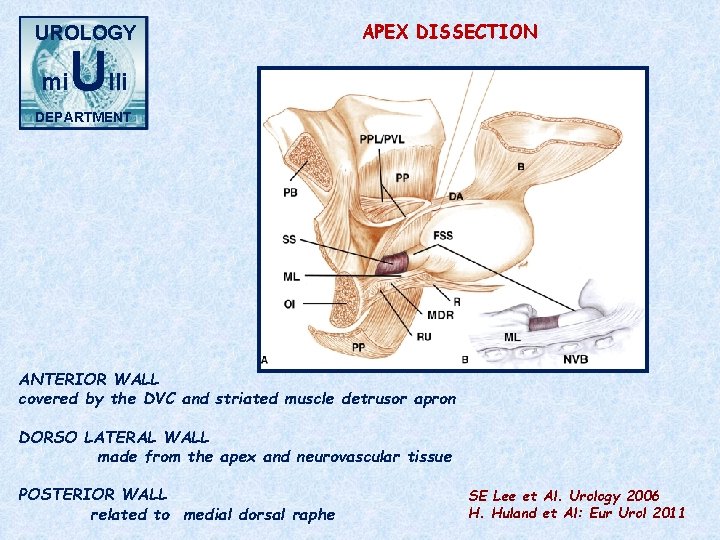
UROLOGY mi Ulli APEX DISSECTION DEPARTMENT ANTERIOR WALL covered by the DVC and striated muscle detrusor apron DORSO LATERAL WALL made from the apex and neurovascular tissue POSTERIOR WALL related to medial dorsal raphe SE Lee et Al. Urology 2006 H. Huland et Al: Eur Urol 2011
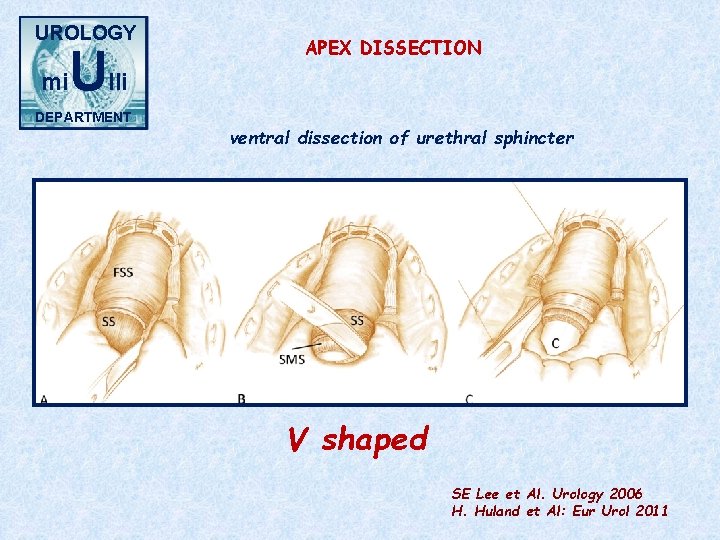
UROLOGY mi Ulli DEPARTMENT APEX DISSECTION ventral dissection of urethral sphincter V shaped SE Lee et Al. Urology 2006 H. Huland et Al: Eur Urol 2011
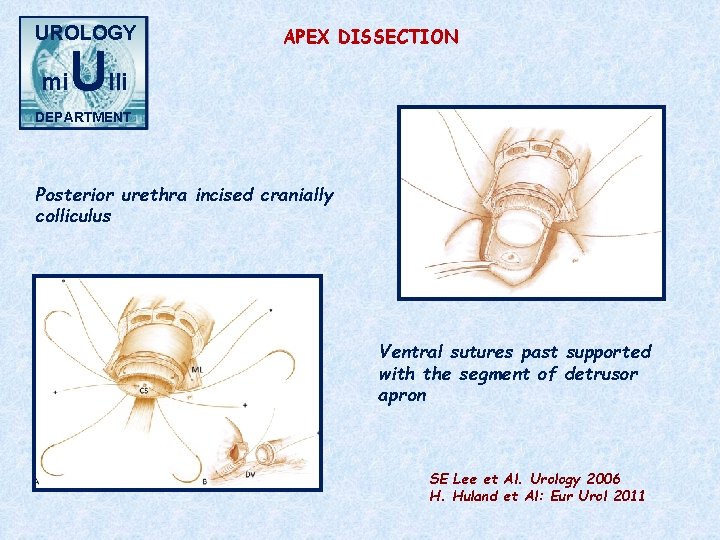
UROLOGY mi Ulli APEX DISSECTION DEPARTMENT Posterior urethra incised cranially colliculus Ventral sutures past supported with the segment of detrusor apron SE Lee et Al. Urology 2006 H. Huland et Al: Eur Urol 2011
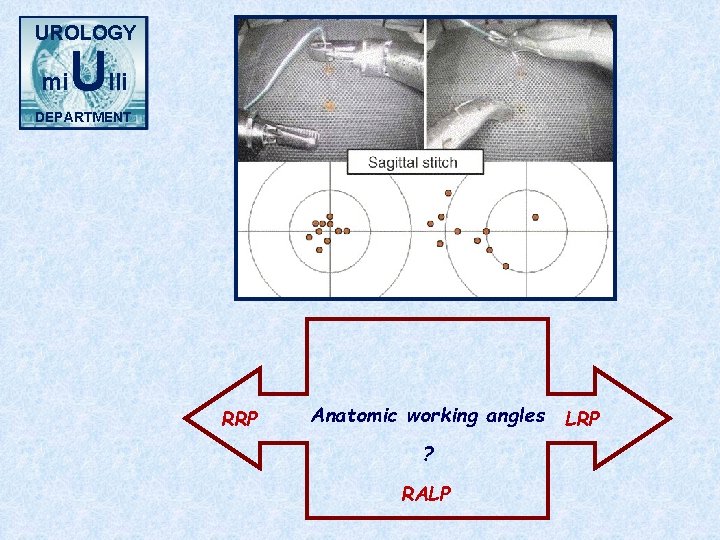
UROLOGY mi Ulli DEPARTMENT RRP Anatomic working angles LRP ? RALP
UROLOGY mi Ulli DEPARTMENT INTERFASCIAL SURGICAL PLANE
UROLOGY mi Ulli DEPARTMENT INTRAFASCIAL SURGICAL PLANE
UROLOGY mi Ulli DEPARTMENT NERVE SPARING
UROLOGY mi Ulli DEPARTMENT ACCESSORY PUDENDAL ARTERY
UROLOGY mi Ulli DEPARTMENT APEX
UROLOGY mi Ulli DEPARTMENT ANASTOMOSIS
UROLOGY mi Ulli New devices DEPARTMENT Some studies evaluated the difference between thermal and athermal dissection of the neurovascular bundles: q Ahlering et al compared pts receiving cautery nerve sparing versus cautery-free cavernous nerve preservation patients observing a significant advantages in favor of athermal dissection 24 mo. after the procedures. Ahlering TE, Rodriguez E et al: J. Endourol, 2008 q Samadi et al compared patients who received an anterograde cautery nerve- sparing procedure using the bipolar device with two other groups who underwent atherml dissection using clips and a «curtain» tecnique observing that mean potency rate at 3, 6 and 12 were 44%, 50% and 66%, respectively. Samadi DB, Munter P. et al: J Endourol, 2010
UROLOGY mi Ulli New devices DEPARTMENT Finley et al. evaluated the potential role of cold dissection of the cavernous nerves ( plus an endorectal cooling balloon cycled with 4 C°) observing a statistically significant better 12 -mo potency rates Finley DS, Osann K. : J Endourol, 2009 Kowalczyk et al reported weak statistical significant advantages in favor of patients receveing a nerve sparing tecnique without cauterysation 5 mo after RARP. Kowalczyk KJ; Huang Acet al: Eur Urol, 2011 This study confirmed two aspects related to the nerve sparing procedure : § the effect of mechanical trauma on the function of the cavernous nerves during the early follow-up §The short time of this negative effect during the robotic procedure
Surgeon’s experience UROLOGY mi Ulli DEPARTMENT A common refrain from busy robotic surgeons, residents and community urologists is that RALP IS EASY TO LEARN COMPARED TO LRP OR EVEN RRP. Certainly, the laparoscopic surgeon may require only 12 to 20 cases to develop comfort with the platform and the steps of the procedure J. A. Cadeddu: J. Urol. , 2010 However, is the real learning curve? Herrel et al reported that results comparable to RRP were not attained until 150 cases and that “self-perception” of a comparable degree of comfort with RALP and RRP was not recognized until greater than 250 RALP procedures. Herrel SD, Smith JA Jrs: Urology, 2005
UROLOGY mi Ulli DEPARTMENT MIULLI ROBOTIC CENTER RALP Volume Feb 2006 – Dec 2008 serie pioneristica 136 3 bracci April 2009 – Sep 2012 serie matura 633 4 bracci
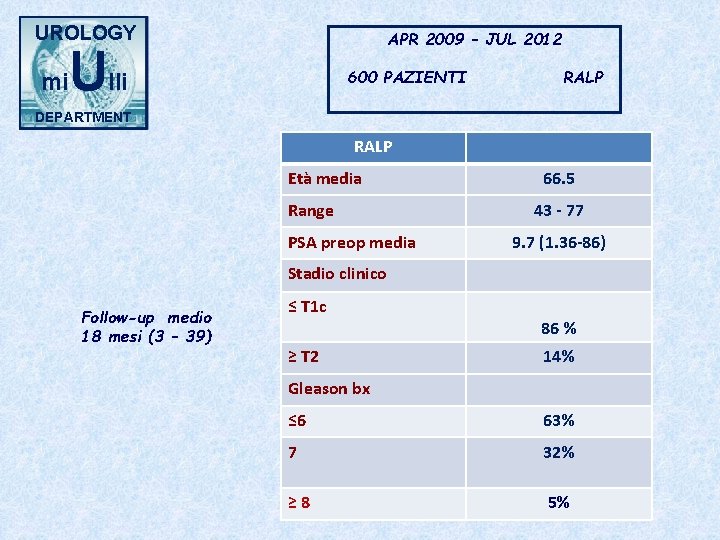
UROLOGY mi APR 2009 – JUL 2012 Ulli 600 PAZIENTI RALP DEPARTMENT RALP Età media Range PSA preop media 66. 5 43 - 77 9. 7 (1. 36 -86) Stadio clinico Follow-up medio 18 mesi (3 – 39) ≤ T 1 c ≥ T 2 86 % 14% Gleason bx ≤ 6 63% 7 32% ≥ 8 5%
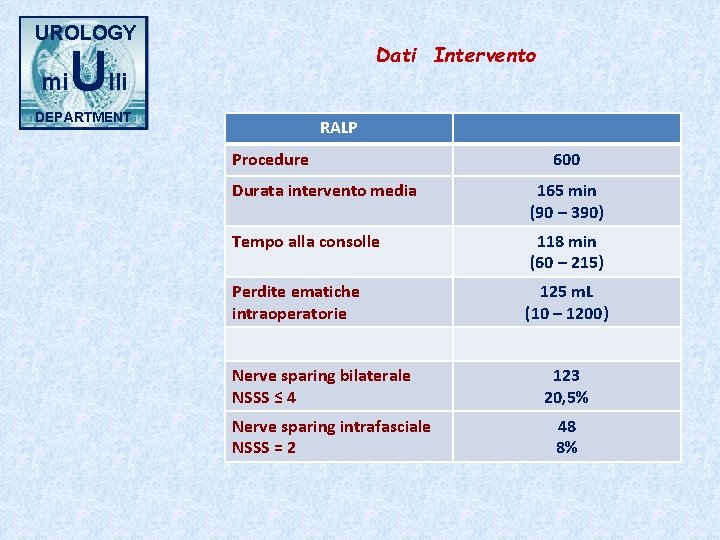
UROLOGY mi Dati Intervento Ulli DEPARTMENT RALP Procedure 600 Durata intervento media 165 min (90 – 390) Tempo alla consolle 118 min (60 – 215) Perdite ematiche intraoperatorie 125 m. L (10 – 1200) Nerve sparing bilaterale NSSS ≤ 4 Nerve sparing intrafasciale NSSS = 2 123 20, 5% 48 8%
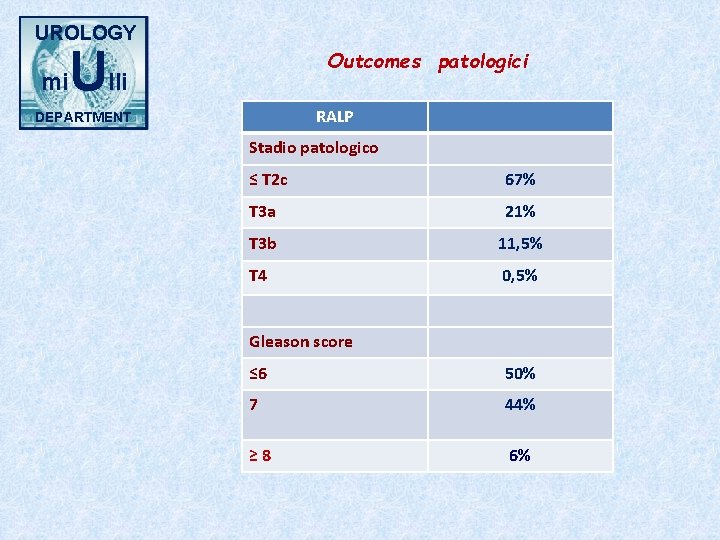
UROLOGY mi Ulli Outcomes patologici RALP DEPARTMENT Stadio patologico ≤ T 2 c 67% T 3 a 21% T 3 b 11, 5% T 4 0, 5% Gleason score ≤ 6 50% 7 44% ≥ 8 6%
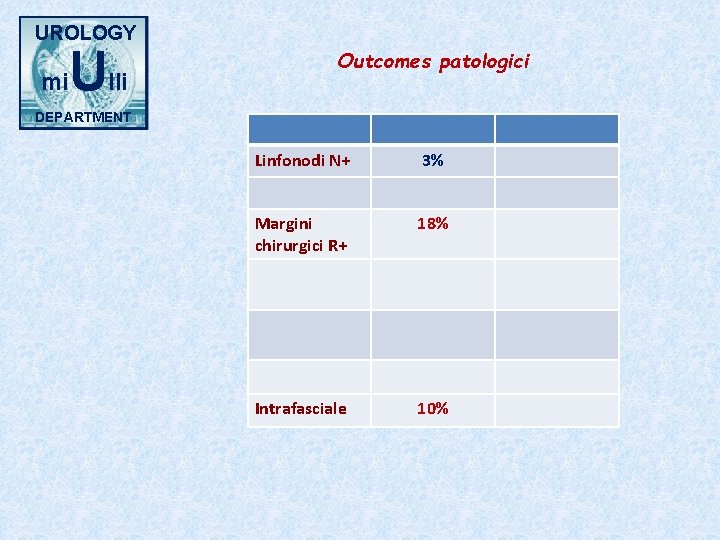
UROLOGY mi Ulli Outcomes patologici DEPARTMENT Linfonodi N+ 3% Margini chirurgici R+ 18% Intrafasciale 10%
UROLOGY mi Ulli DEPARTMENT Nerve Sparing Scoring System 1 Perfect nerve sparing 2 Minor damage 3 Moderate damage 4 Complete resection GLOBAL NSSS ≤ 4 Nelson J Urol 2009
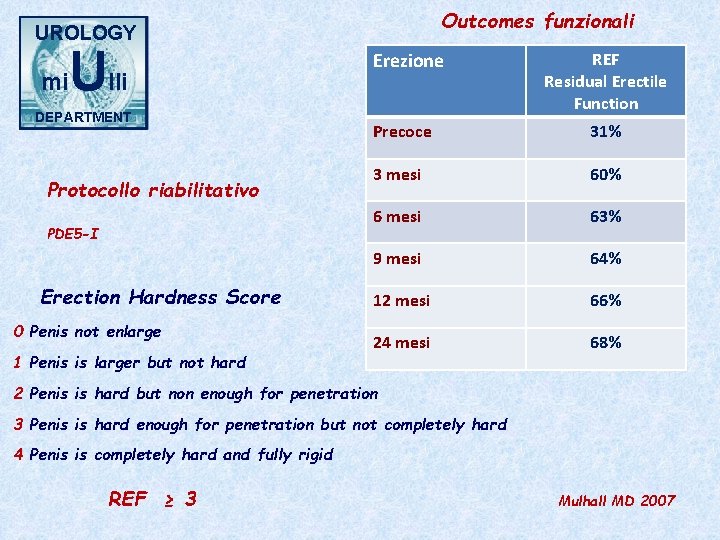
UROLOGY mi Ulli Erection Hardness Score DEPARTMENT 0 Penis not enlarge 1 Penis is larger but not hard 2 Penis is hard but non enough for penetration 3 Penis is hard enough for penetration but not completely hard 4 Penis is completely hard and fully rigid REF ≥ 3 Mulhall J Sex Med 2007
Outcomes funzionali UROLOGY mi Ulli DEPARTMENT Protocollo riabilitativo PDE 5 -I Erection Hardness Score 0 Penis not enlarge 1 Penis is larger but not hard Erezione REF Residual Erectile Function Precoce 31% 3 mesi 60% 6 mesi 63% 9 mesi 64% 12 mesi 66% 24 mesi 68% 2 Penis is hard but non enough for penetration 3 Penis is hard enough for penetration but not completely hard 4 Penis is completely hard and fully rigid REF ≥ 3 Mulhall MD 2007
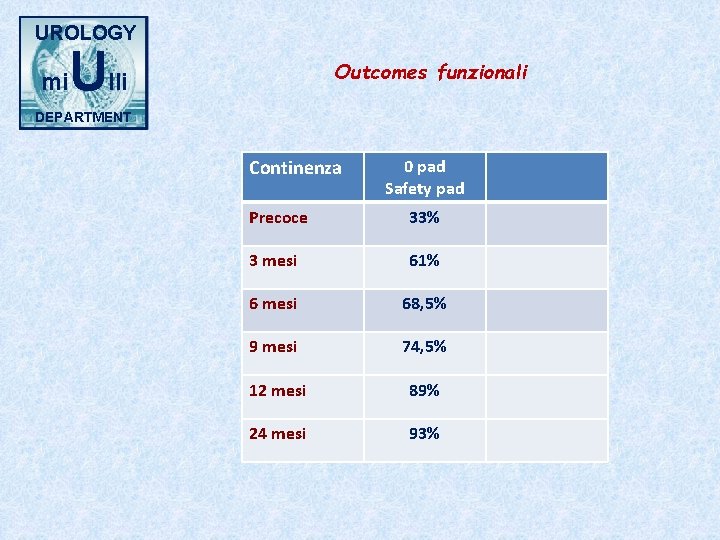
UROLOGY mi Ulli Outcomes funzionali DEPARTMENT Continenza 0 pad Safety pad Precoce 33% 3 mesi 61% 6 mesi 68, 5% 9 mesi 74, 5% 12 mesi 89% 24 mesi 93%
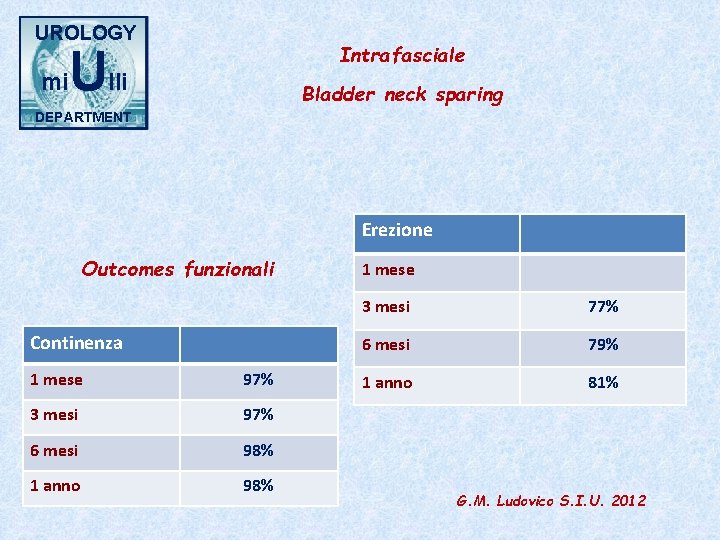
UROLOGY mi Intrafasciale Ulli Bladder neck sparing DEPARTMENT Erezione Outcomes funzionali Continenza 1 mese 97% 3 mesi 97% 6 mesi 98% 1 anno 98% 1 mese 3 mesi 77% 6 mesi 79% 1 anno 81% G. M. Ludovico S. I. U. 2012
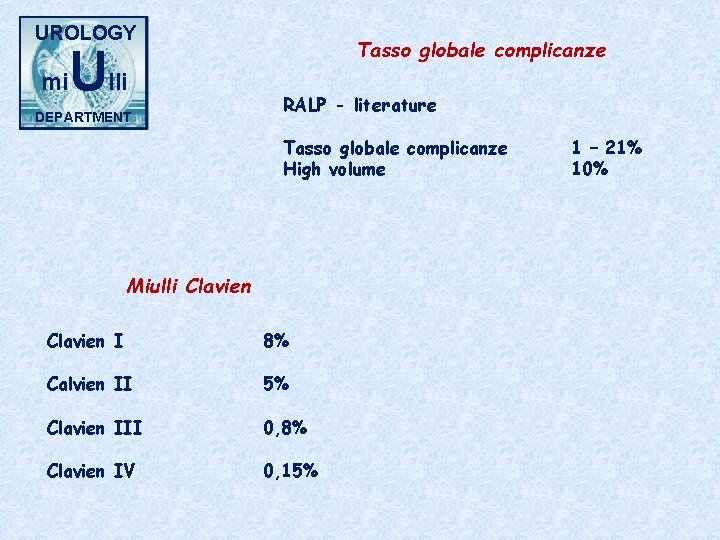
UROLOGY mi Ulli DEPARTMENT Tasso globale complicanze RALP - literature Tasso globale complicanze High volume Miulli Clavien I 8% Calvien II 5% Clavien III 0, 8% Clavien IV 0, 15% 1 – 21% 10%
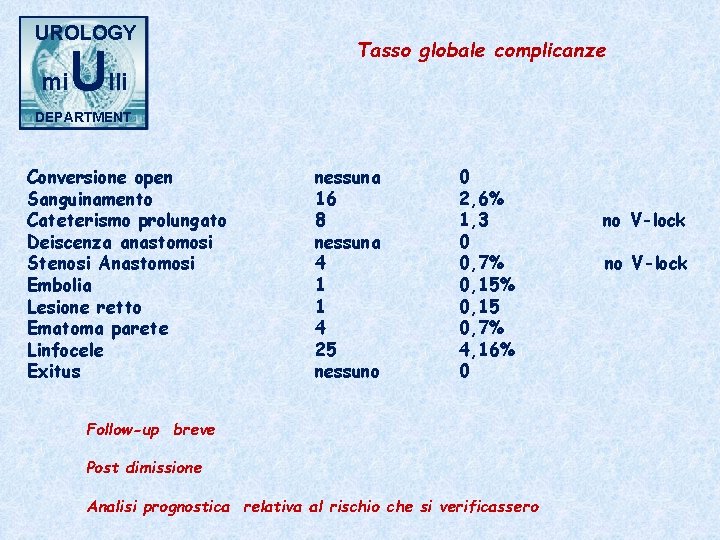
UROLOGY mi Ulli Tasso globale complicanze DEPARTMENT Conversione open Sanguinamento Cateterismo prolungato Deiscenza anastomosi Stenosi Anastomosi Embolia Lesione retto Ematoma parete Linfocele Exitus nessuna 16 8 nessuna 4 1 1 4 25 nessuno 0 2, 6% 1, 3 0 0, 7% 0, 15 0, 7% 4, 16% 0 Follow-up breve Post dimissione Analisi prognostica relativa al rischio che si verificassero no V-lock
UROLOGY mi Ulli CONCLUSIONS DEPARTMENT Surgeon experience Surgical institutional volume Anatomic working angles Robotic team Better outcomes
UROLOGY mi Ulli CONCLUSIONS DEPARTMENT RALP is displacing RRP as the gold standard surgical approach for clinically localised prostate cancer in the United States and is also being increasingly used in Europe and other parts of the world. This trend has occurred despite the paucity of high-quality evidence to support its relative superiority to more-established treatment modalities. Recent in-depth systematic reviews of the literature have compared the results of RRP versus LRP/RALP. Systematic review indicates that RALP is advantageous in preservation of continence and potency recovery Ficarra V, Eur Urol 2012. Coelho RF; J Endourol 2010. Kang DC, Eur Urol 2010.
UROLOGY mi Ulli CONCLUSIONS DEPARTMENT Currently the best treatment is to continue to perform and perfect a good bilateral nerve-sparing technique Major modification in surgical technique (intrafascial RALP) appear to be promising Men who undergo this procedure have a reasonable chance of regaining complete erectile function in 12 to 24 months.
UROLOGY mi Ulli DEPARTMENT http: //www. urologiamiulli. it