
Urine analysis Dr Usha Introduction n Urine is























































- Slides: 69
Urine analysis Dr. Usha
Introduction n Urine is formed in the kidneys, is a product of ultrafiltration of plasma by the renal glomeruli.
Collection of urine Early morning sample-qualitative n Random sample- routine n 24 hrs sample- quantitative n Midstream sample-UTI n Post prandial sample-D. M n
24 hour urine sample 1. 2. 3. 4. For quantitative estimation of proteins For estimation of vanillyl mandelic acid, 5 -hydroxyindole acetic acid, metanephrines For detection of AFB in urine For detection of microalbuminuria
n
Urine examination Macroscopic examination n Chemical examination n Microscopic examination n
Macroscopic examination Volume n Color n Odour n Reaction or urinary p. H n Specific gravity n
Urinary volume n n n Normal = 600 -1550 ml Polyuria- >2000 ml Oliguria-<400 ml Anuria-complete cessation of urine(<200 ml) Nocturia-excretion of urine by a adult of >500 ml with a specific gravity of <1. 018 at night (characteristic of chronic glomerulonephritis)
Causes of polyuria Diabetes mellitus n Diabetes insipidus n Polycystic kidney n Chronic renal failure n Diuretics n Intravenous saline/glucose n
oliguria Dehydration-vomiting, diarrhoea, excessive sweating n Renal ischemia n Acute tubular necrosis n Obstruction to the urinary tract n Acute renal failure n
Color & appearance n 1. 2. 3. 4. 5. Normal= clear & pale yellow Colourless- dilution, diabetes mellitus, diabetes insipidus, diuretics Milky-purulent genitourinary tract infection, chyluria Orange-fever, excessive sweating Red-beetroot ingestion, haematuria Brown/ black- alkaptunuria, melanin
Urinary p. H/ reaction Reaction reflects ability of kidney to maintain normal hydrogen ion concentration in plasma & ECF n Normal= 4. 6 -8 n Tested by- 1. litmus paper 2. p. H paper 3. dipsticks n
Acidic urine Ketosis-diabetes, starvation, fever n Systemic acidosis n UTI- E. coli n Acidification therapy n
Alkaline urine Strict vegetarian n Systemic alkalosis n UTI- Proteus n Alkalization therapy n
Odour Normal= aromatic due to the volatile fatty acids n Ammonical – bacterial action n Fruity- ketonuria n
Specific gravity Depends on the concentration of various solutes in the urine. n Measured by-urinometer - refractometer - dipsticks n
Urinometer Take 2/3 of urinometer container with urine n Allow the urinometer to float into the urine n Read the graduation at the lowest level of urinary meniscus n Correction of temperature & albumin is a must. n Urinometer is calibrated at 15 or 200 c So for every 3 oc increase/decrease add/subtract 0. 001 For 1 gm/dl of albumin add 0. 001 n
n
High specific gravity(hyperosthenuria) Normal-1. 016 -1. 022 n Causes All causes of oliguria Gycosuria n
Low specific gravity(hyposthenuria) n All causes of polyuria except gycosuria Fixed specific gravity (isosthenuria)=1. 010 Seen in chronic renal disease when kidney has lost the ability to concentrate or dilute n
Chemical examination Proteins n Sugars n Ketone bodies n Bilirubin n Bile salts n Urobilinogen n Blood n
Tests for proteins n n Test – HEAT & ACETIC ACID TEST Principle-proteins are denatured & coagulated on heating to give white cloud precipitate. Method-take 2/3 of test tube with urine, heat only the upper part keeping lower part as control. Presence of phosphates, carbonates, proteins gives a white cloud formation. Add acetic acid 12 drops, if the cloud persists it indicates it is protein(acetic acid dissolves the carbonates/phosphates)
Other tests Sulphosalicylic acid test n Dipsticks n Esbach’s albuminometer- for quantitative estimation of proteins n
Causes of proteinuria n n n Prerenal causes-Heavy exercise, Fever, hypertension, multiple myeloma, ecalmpsia Renal –acute & chronic glomerulonephritis, Renal tubular dysfunction, Polycystic kidney, nephrotic syndrome Post renal- acute & chronic cystitis, tuberculosis cystitis
Selective proteinuria n Nonselective proteinuria n
microalbuminuria n The level of albumin protein produced by microalbuminuria cannot be detected by urine dipstick methods. In a properly functioning body, albumin is not normally present in urine because it is retained in the bloodstream by the kidneys. Microalbuminuria is diagnosed either from a 24 -hour urine collection
Significance of microalbuminuria n n n an indicator of subclinical cardiovascular disease an important prognostic marker for kidney disease in diabetes mellitus in hypertension increasing microalbuminuria during the first 48 hours after admission to an intensive care unit predicts elevated risk for acute respiratory failure , multiple organ failure , and overall mortality
Bence Jones proteins These are light chain globulins seen in multiple myeloma, macroglobulimias, lymphoma. n Test- Thermal method(waterbath): Proteins has unusual property of precipitating at 400 -600 c & then dissolving when the urine is brought to boiling(1000 c) & reappears when the urine is cooled. n
Test for sugar Test-BENEDICT’S TEST(semiquantitative) n Principle-benedict’s reagent contains cuso 4. In the presence of reducing sugars cupric ions are converted to cuprous oxide which is hastened by heating, to give the color. n Method- take 5 ml of benedict’s reagent in a test tube, add 8 drops of urine. Boil the mixture. v Blue-green= negative v Yellow-green=+(<0. 5%) v Greenish yellow=++(0. 5 -1%) v Yellow=+++(1 -2%) v Brick red=++++(>2%) n
Benedict’s test Detects all reducing substances like glucose, fructose, & other reducing sustances. n To confirm it is glucose, dipsticks can be used (glucose oxidase) n
Causes of glycosuria Glycosuria with hyperglycaemia- diabetes, acromegaly, cushing’s disease, hyperthyroidism, drugs like corticosteroids. n Glycosuria without hyperglycaemia- renal tubular dysfunction n
Ketone bodies 3 types Ø Acetone Ø Acetoacetic acid Ø β-hydroxy butyric acid n Ø They are products of fat metabolism
Rothera’s test Principle-acetone & acetoacetic acid react with sodium nitroprusside in the presence of alkali to produce purple colour. n Method- take 5 ml of urine in a test tube & saturate it with ammonium sulphate. Then add one crystal of sodium nitroprusside. Then gently add 0. 5 ml of liquor ammonia along the sides of the test tube. n Change in colour indicates + test n
Causes of ketonuria Diabetes n Non-diabetic causes- high fever, starvation, severe vomiting/diarrhoea n
Bilirubin n n Ø Ø Test- fouchet’s test. Causes Liver diseases-injury, hepatitis Obstruction to biliary tract
Urobilinogen Test- ehrlich test n Causes-hemolytic anemia's n Bile salts. Hay’s test Cause- obstruction to bile flow (obstructive jaundice) n
Blood in urine n n n Test- BENZIDINE TEST Principle-The peroxidase activity of hemoglobin decomposes hydrogen peroxide releasing nascent oxygen which in turn oxidizes benzidine to give blue color. Method- mix 2 ml of benzidine solution with 2 ml of hydrogen peroxide in a test tube. Take 2 ml of urine & add 2 ml of above mixture. A blue color indicates + reaction.
Causes of hematuria Pre renal- bleeding diathesis, hemoglobinopathies, malignant hypertension. n Renal- trauma, calculi, acute & chronic glomerulonephritis, renal TB, renal tumors n Post renal – severe UTI, calculi, trauma, tumors of urinary tract n
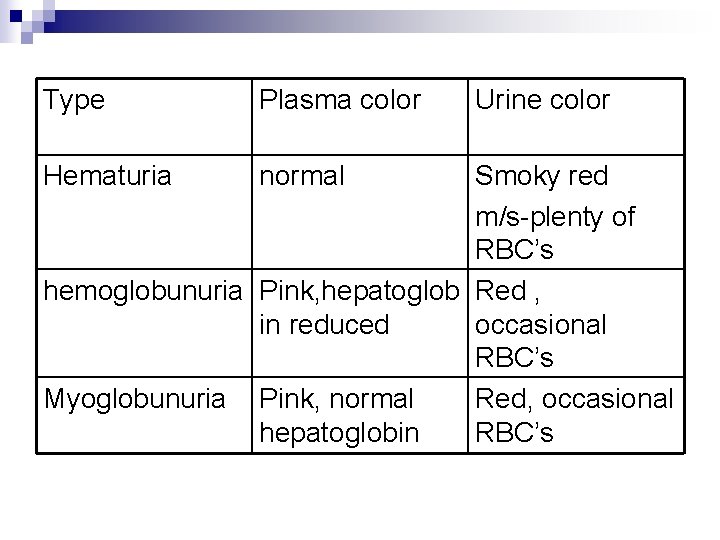
Type Plasma color Hematuria normal Urine color Smoky red m/s-plenty of RBC’s hemoglobunuria Pink, hepatoglob Red , in reduced occasional RBC’s Myoglobunuria Pink, normal Red, occasional hepatoglobin RBC’s
Microscopic examination n Microscopic urinalysis is done simply pouring the urine sample into a test tube and centrifuging it (spinning it down in a machine) for a few minutes. The top liquid part (the supernatant) is discarded. The solid part left in the bottom of the test tube (the urine sediment) is mixed with the remaining drop of urine in the test tube and one drop is analyzed under a microscope
Contents of normal urine m/s n Contains few epithelial cells, occasional RBC’s, few crystals.
Crystals in urine Crystals in acidic urine Ø Uric acid Ø Calcium oxalate Ø Cystine Ø Leucine Crystals in alkaline urine Ø Ammonium magnesium phosphates(triple phosphate crystals) Ø Calcium carbonate
crystals n
casts n Urinary casts are cylindrical aggregations of particles that form in the distal nephron, dislodge, and pass into the urine. In urinalysis they indicate kidney disease. They form via precipitation of Tamm. Horsfall mucoprotein which is secreted by renal tubule cells.
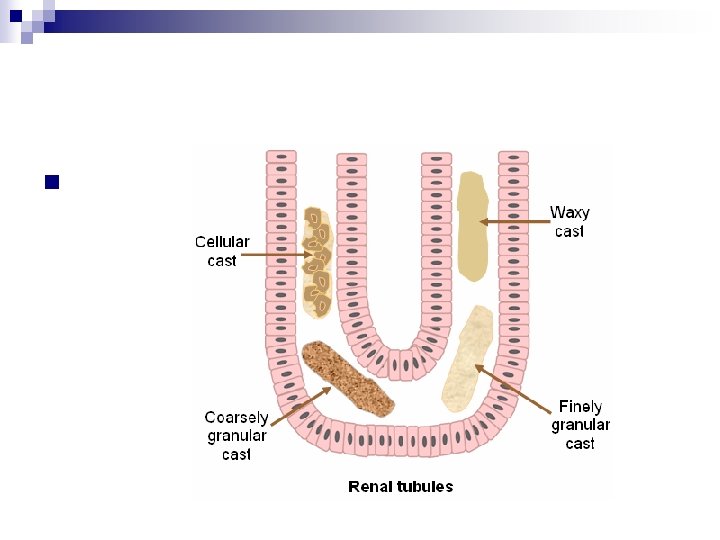
Types of casts Acellular casts Hyaline casts Granular casts Waxy casts Fatty casts Pigment casts Crystal casts n Cellular casts Red cell casts White cell casts Epithelial cell cast n
Hyaline casts The most common type of cast, hyaline casts are solidified Tamm-Horsfall mucoprotein secreted from the tubular epithelial cells n Seen in fever, strenuous exercise, damage to the glomerular capillary n
Granular casts can result either from the breakdown of cellular casts or the inclusion of aggregates of plasma proteins (e. g. , albumin) or immunoglobulin light chains n indicative of chronic renal disease n
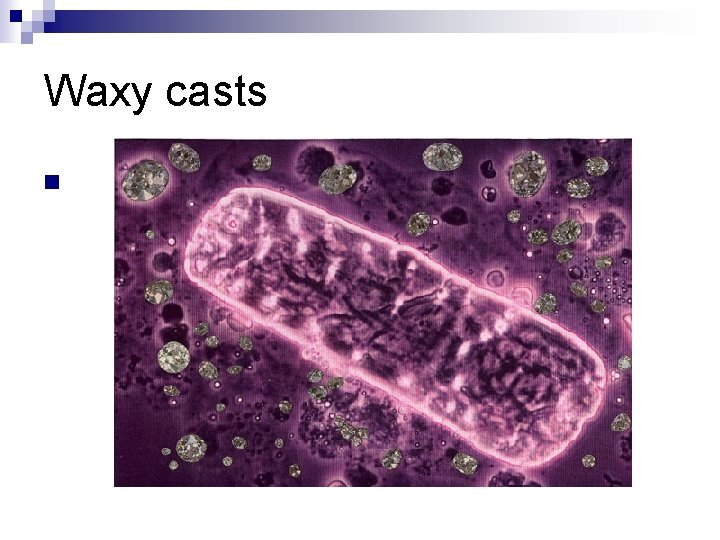
Waxy casts n waxy casts suggest severe, longstanding kidney disease such as renal failure(end stage renal disease).
Waxy casts n
n
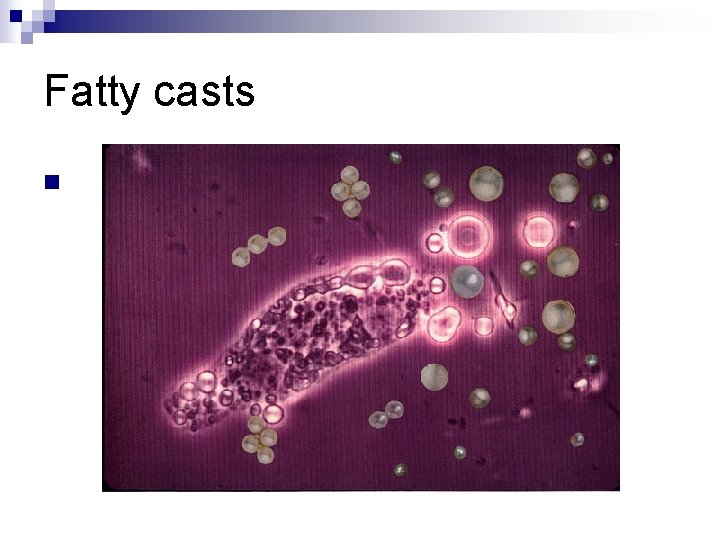
Fatty casts Formed by the breakdown of lipid-rich epithelial cells, these are hyaline casts with fat globule inclusions They can be present in various disorders, including n nephrotic syndrome, n diabetic or lupus nephropathy, n Acute tubular necrosis n
Fatty casts n
Pigment casts Formed by the adhesion of metabolic breakdown products or drug pigments n Pigments include those produced endogenously, such as n hemoglobin in hemolytic anemia, n myoglobin in rhabdomyolysis, and n bilirubin in liver disease. n
Crystal casts Though crystallized urinary solutes, such as oxalates, urates, or sulfonamides, may become enmeshed within a hyaline cast during its formation. n The clinical significance of this occurrence is not felt to be great. n
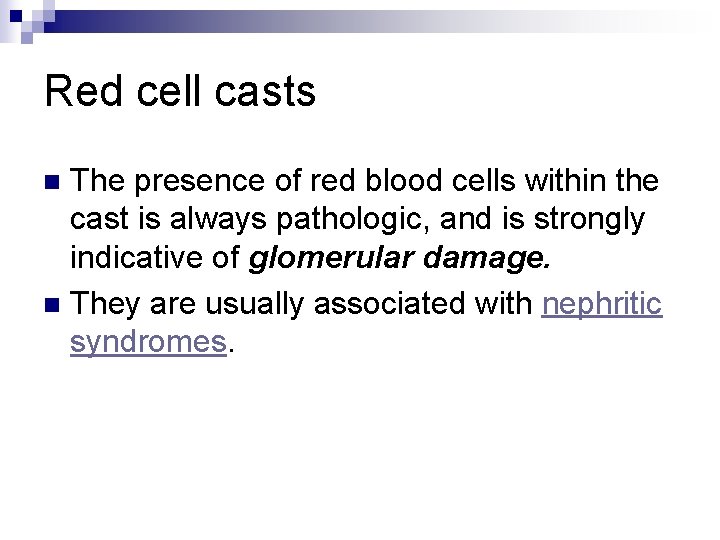
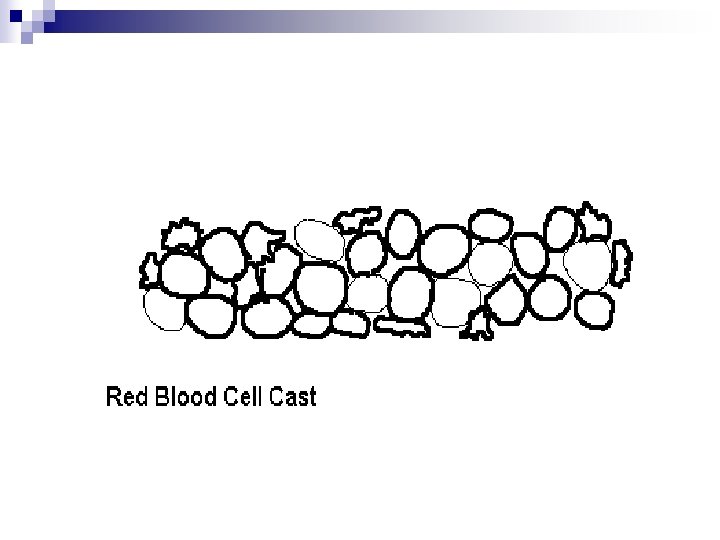
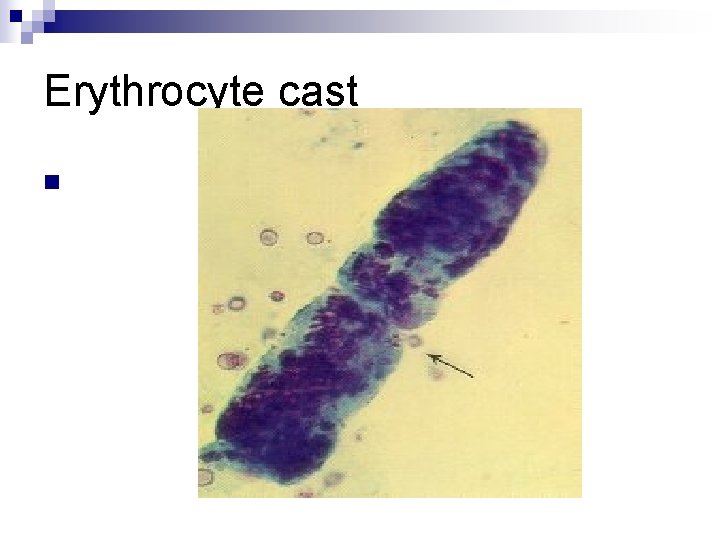
Red cell casts The presence of red blood cells within the cast is always pathologic, and is strongly indicative of glomerular damage. n They are usually associated with nephritic syndromes. n
Erythrocyte cast n
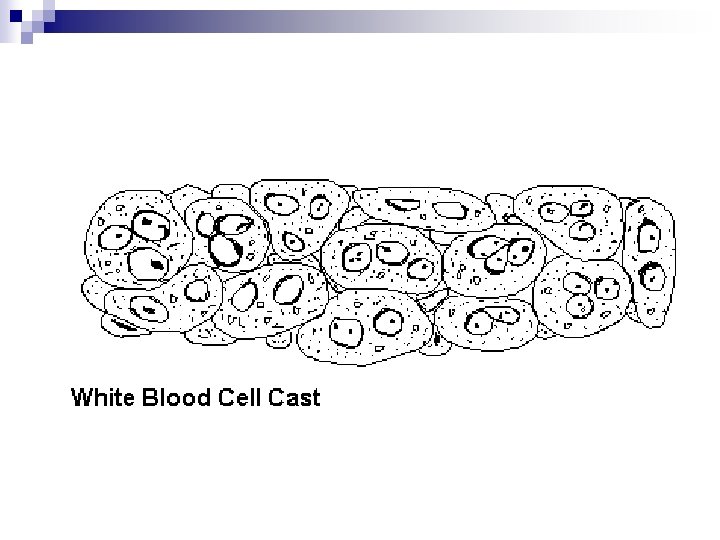
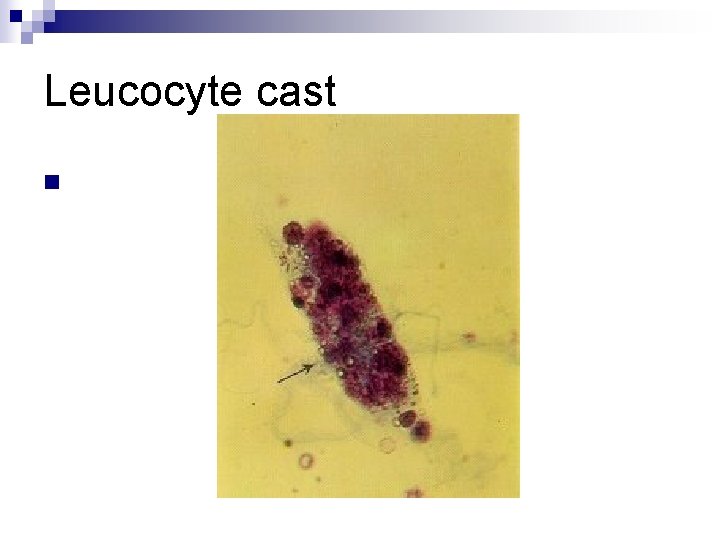
White blood cell casts Indicative of inflammation or infection, n pyelonephritis n acute allergic interstitial nephritis, n nephrotic syndrome, or n post-streptococcal acute glomerulonephritis n
Leucocyte cast n
Epithelial casts This cast is formed by inclusion or adhesion of desquamated epithelial cells of the tubule lining. These can be seen in n acute tubular necrosis and n toxic ingestion, such as from mercury, diethylene glycol, or salicylate. n
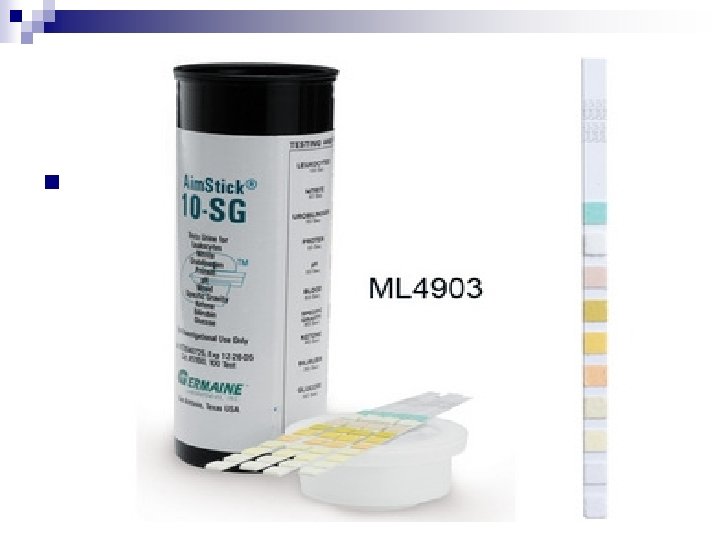
Urine dipsticks n Urine dipstick is a narrow plastic strip which has several squares of different colors attached to it. Each small square represents a component of the test used to interpret urinalysis. The entire strip is dipped in the urine sample and color changes in each square noted. The color change takes place after several seconds to a few minutes from dipping the strip. If read too early or too long after the strip is dipped, the results may not be accurate.
n
n • • n The squares on the dipstick represent the following components in the urine: specific gravity (concentration of urine), acidity of the urine (p. H), protein in the urine (mainly albumin), glucose (sugar), ketones blood bilirubin and urobilinogen
The main advantage of dipsticks is that they are 1. convenient, 2. easy to interpret, 3. and cost-effective n
The main disadvantage is that the 1. Information may not be very accurate as the test is time-sensitive. 2. It also provides limited information about the urine as it is qualitative test and not a quantitative test (for example, it does not give a precise measure of the quantity of abnormality).