
UNIVERSITY HOSPITAL of Pisa Division of Cardiovascular Diseases










- Slides: 27
UNIVERSITY HOSPITAL of Pisa Division of Cardiovascular Diseases II LEADLESS CARDIAC PACEMAKERS: WHAT IS TO BE EXPECTED? Pisa-Washington 14/12/2016 Dr. Francesca Menichetti Dr. Maria Grazia Bongiorni Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
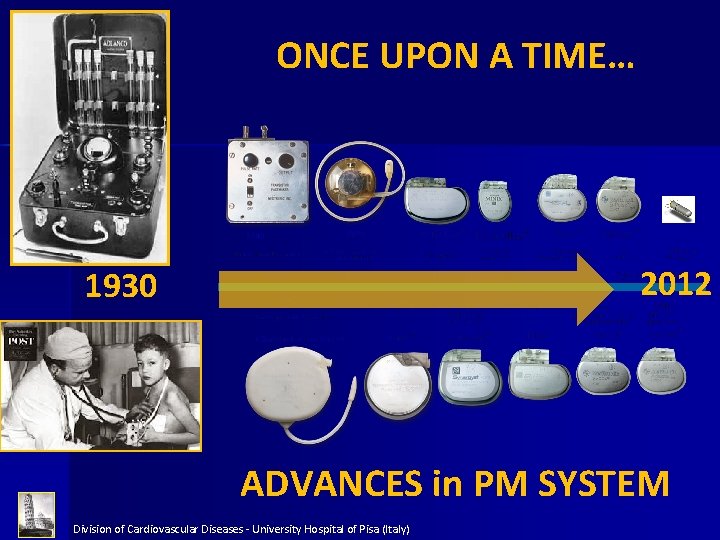
ONCE UPON A TIME… 2012 1930 ADVANCES in PM SYSTEM Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
Lead: a simple system? COMPONENTS • Electrodes • Conductors • Insulation • Fixation • Connectors ISSUES • Mechanical failure • Infection, extractions • Mobility resctrinctions • MRI incompability
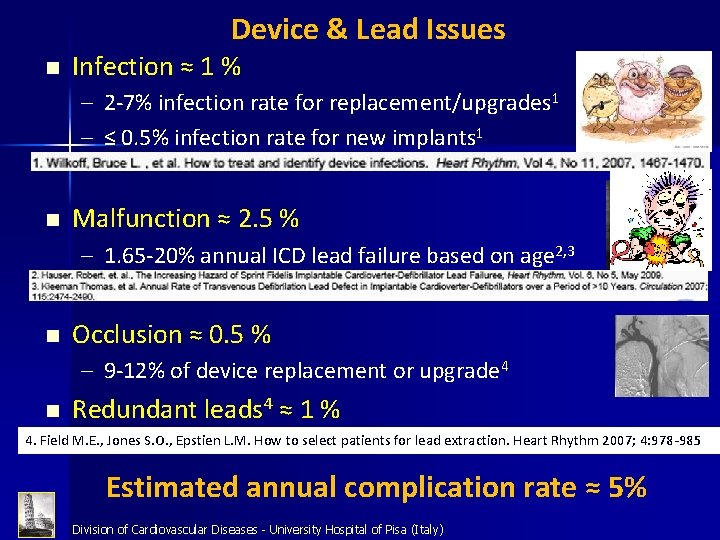
Device & Lead Issues n Infection ≈ 1 % – 2 -7% infection rate for replacement/upgrades 1 – ≤ 0. 5% infection rate for new implants 1 n Malfunction ≈ 2. 5 % – 1. 65 -20% annual ICD lead failure based on age 2, 3 n Occlusion ≈ 0. 5 % – 9 -12% of device replacement or upgrade 4 n Redundant leads 4 ≈ 1 % 4. Field M. E. , Jones S. O. , Epstien L. M. How to select patients for lead extraction. Heart Rhythm 2007; 4: 978 -985 Estimated annual complication rate ≈ 5% Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
BENEFIT OF LEADLESS APPROACH n Reduced invasiveness - Percutaneus procedure - Reduced hardware - “Invisible to the patient” n Improved Efficiency - No pocket - No system connection - Reduced procedure time n Improved Outcomes - Fewer complications Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
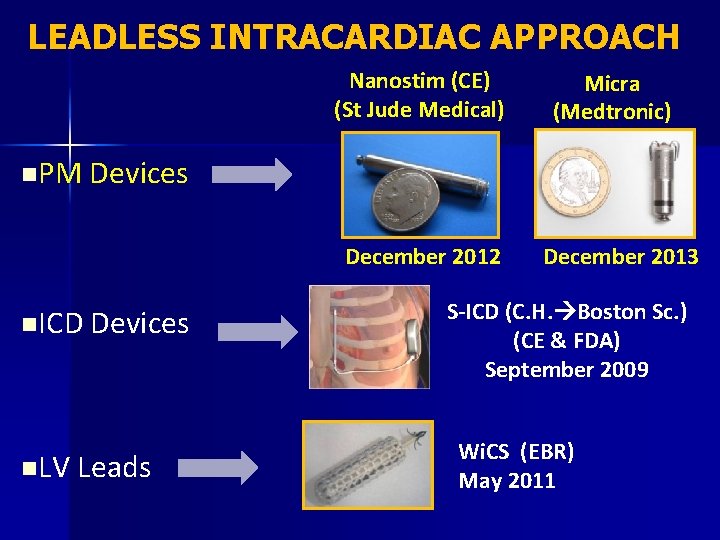
LEADLESS INTRACARDIAC APPROACH Nanostim (CE) (St Jude Medical) Micra (Medtronic) n. PM Devices December 2012 n. ICD Devices n. LV Leads December 2013 S-ICD (C. H. Boston Sc. ) (CE & FDA) September 2009 Wi. CS (EBR) May 2011
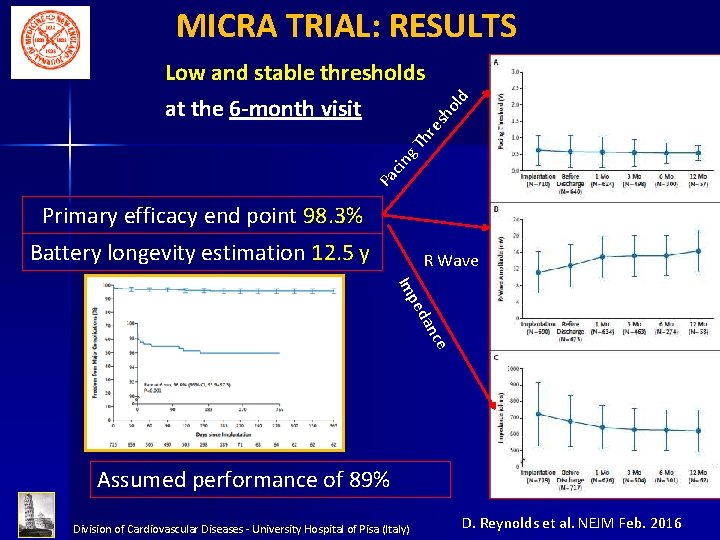
ld ho Pa c in g T hr es Low and stable thresholds at the 6 -month visit MICRA TRIAL: RESULTS Primary efficacy end point 98. 3% Battery longevity estimation 12. 5 y R Wave da pe Im nce Assumed performance of 89% Division of Cardiovascular Diseases - University Hospital of Pisa (Italy) D. Reynolds et al. NEJM Feb. 2016
MICRA Trial: comparison with standard PM Control cohort of 2667 pts with transvenous PM from 6 previously published studies n n n 51% Fewer major complications 54% Fewer Hospitalizations 87% Fewer System Revisions Division of Cardiovascular Diseases - University Hospital of Pisa (Italy) D. Reynolds et al. NEJM Feb. 2016
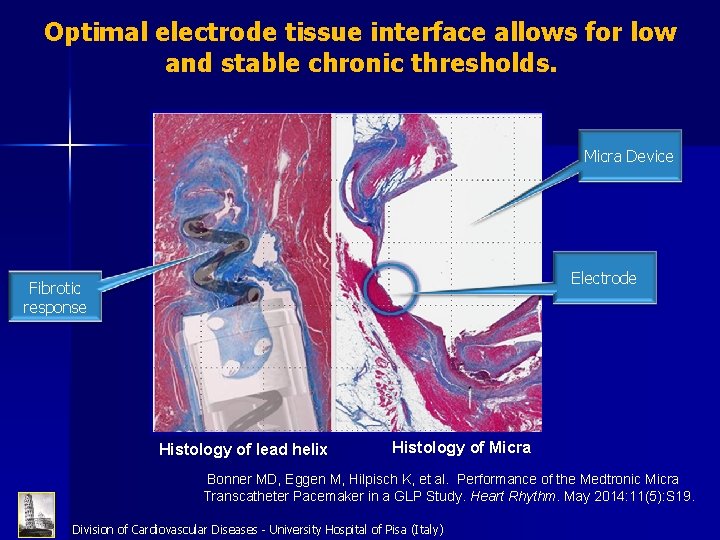
Optimal electrode tissue interface allows for low and stable chronic thresholds. Micra Device Electrode Fibrotic response Histology of lead helix Histology of Micra Bonner MD, Eggen M, Hilpisch K, et al. Performance of the Medtronic Micra Transcatheter Pacemaker in a GLP Study. Heart Rhythm. May 2014: 11(5): S 19. Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
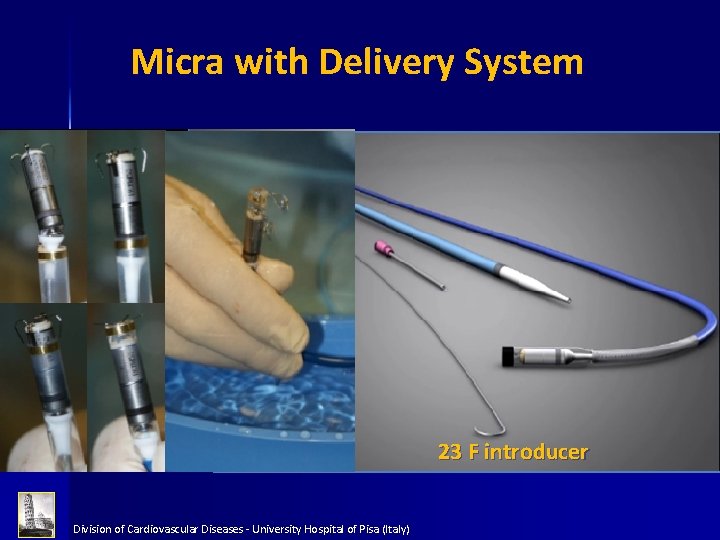
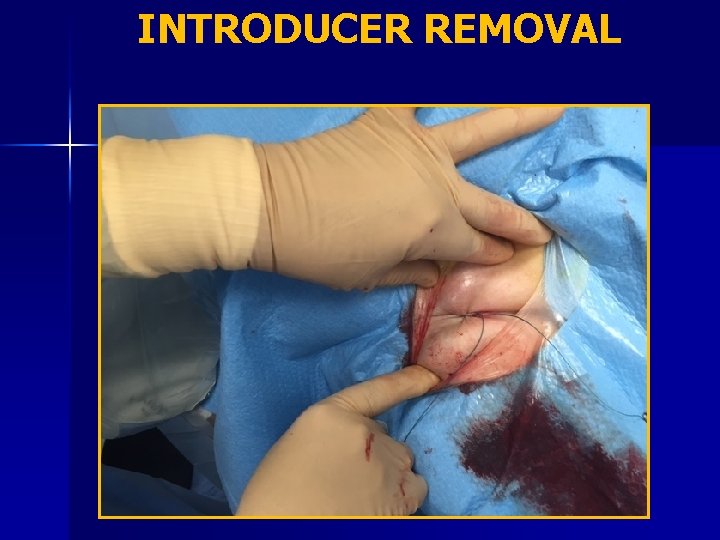
Micra with Delivery System 23 F introducer Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
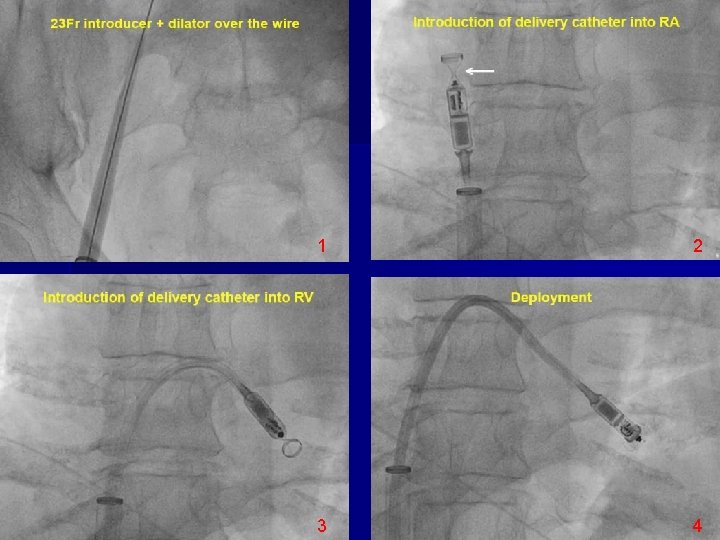
1 2 3 4
INTRODUCER REMOVAL
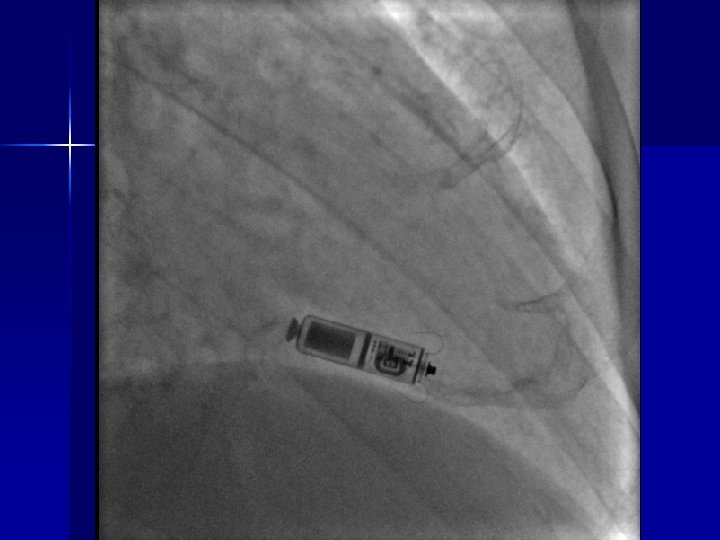
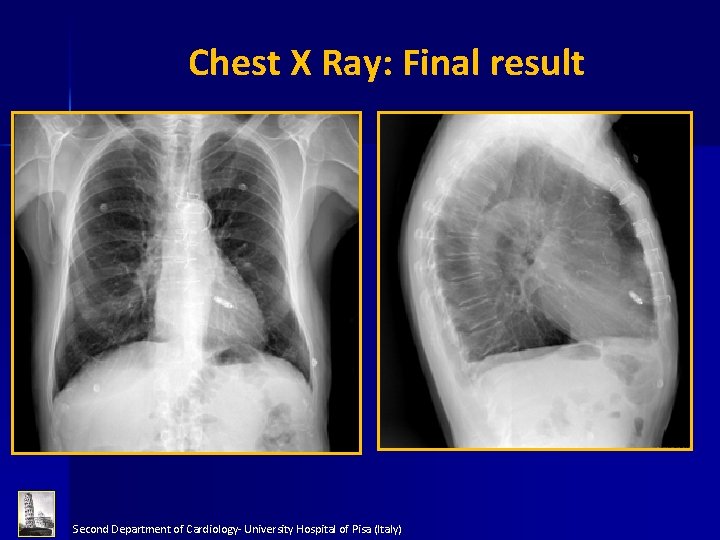
Chest X Ray: Final result Second Department of Cardiology- University Hospital of Pisa (Italy)
Unanswered questions • Will LCP match the reliability of current PM at long term FU? • Will there be any long-term thrombogenic complications? • What will be the real rates of dislodgement of LCP over time? • Which will be the strategy in the event of battery depletion? Removal or implant an additional device? Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
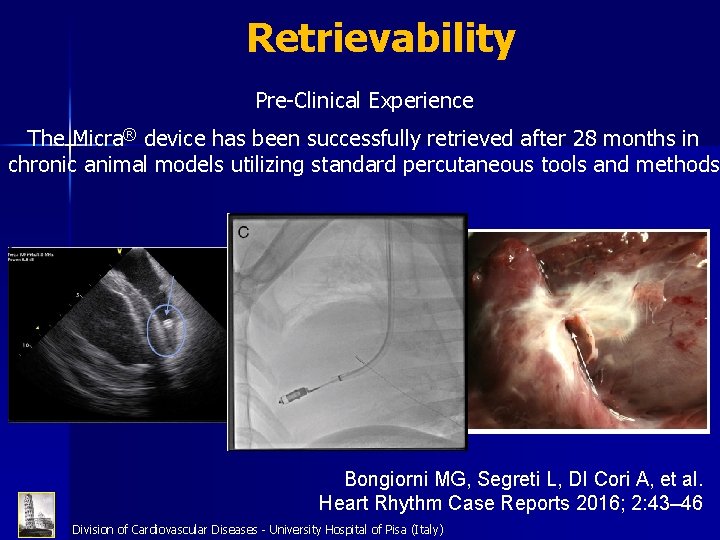
Retrievability Pre-Clinical Experience The Micra® device has been successfully retrieved after 28 months in chronic animal models utilizing standard percutaneous tools and methods Bongiorni MG, Segreti L, DI Cori A, et al. Heart Rhythm Case Reports 2016; 2: 43– 46 Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
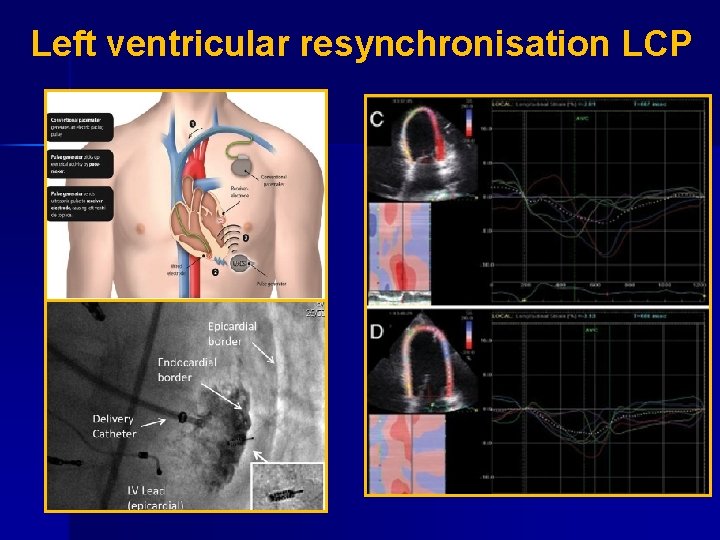
• Left ventricular resynchronisation LCP • Combination of LCP and s-ICD • Multi-chamber leadless pacing systems Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
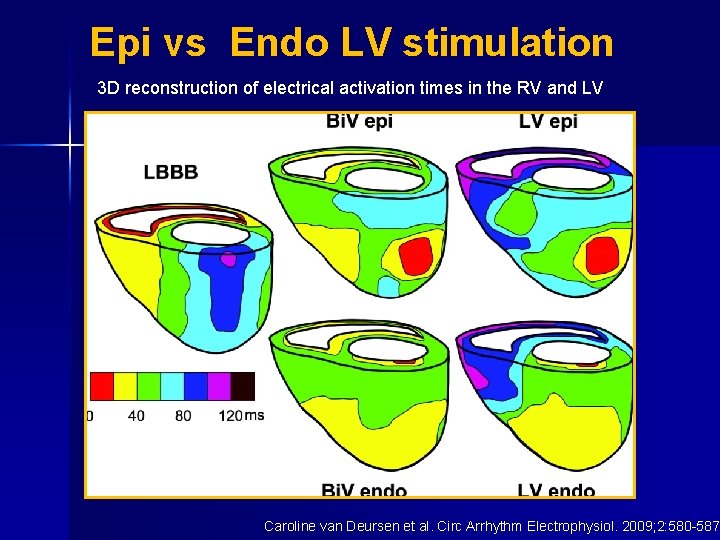
Epi vs Endo LV stimulation 3 D reconstruction of electrical activation times in the RV and LV Caroline van Deursen et al. Circ Arrhythm Electrophysiol. 2009; 2: 580 -587
Left ventricular resynchronisation LCP
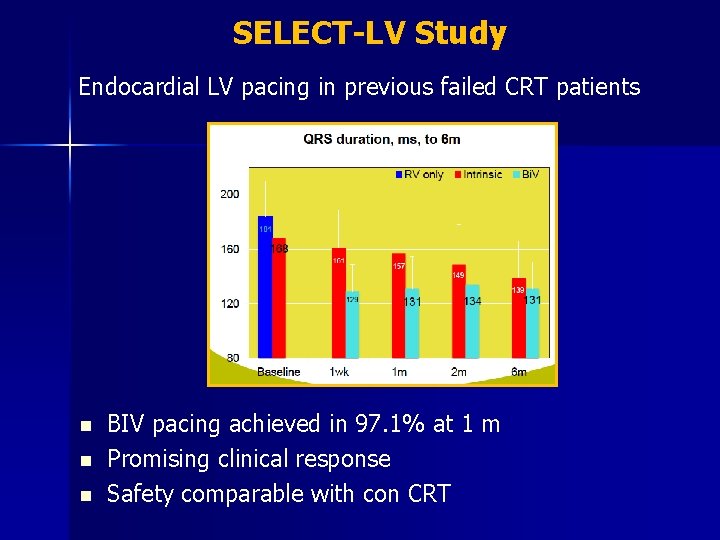
March 2012 study stopped - redesign catether - more echo guided implant Auricchio A, et al, Europace (2014) 16, 681– 688
SELECT-LV Study Endocardial LV pacing in previous failed CRT patients n n n BIV pacing achieved in 97. 1% at 1 m Promising clinical response Safety comparable with con CRT
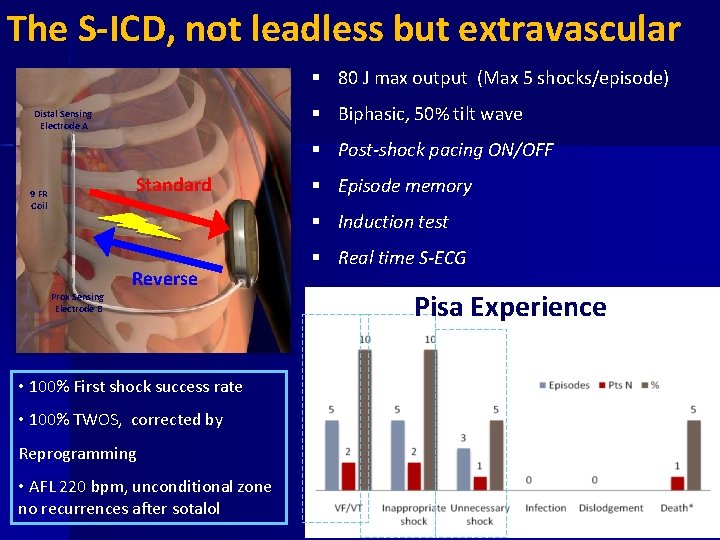
The S-ICD, not leadless but extravascular § 80 J max output (Max 5 shocks/episode) § Biphasic, 50% tilt wave Distal Sensing Electrode A § Post-shock pacing ON/OFF Standard 9 FR Coil § Episode memory § Induction test Reverse Prox Sensing Electrode B • 100% First shock success rate • 100% TWOS, corrected by Reprogramming • AFL 220 bpm, unconditional zone no recurrences after sotalol § Real time S-ECG FU 11. 4 + 10 mths (range 1 -40 mths) Pisa Experience
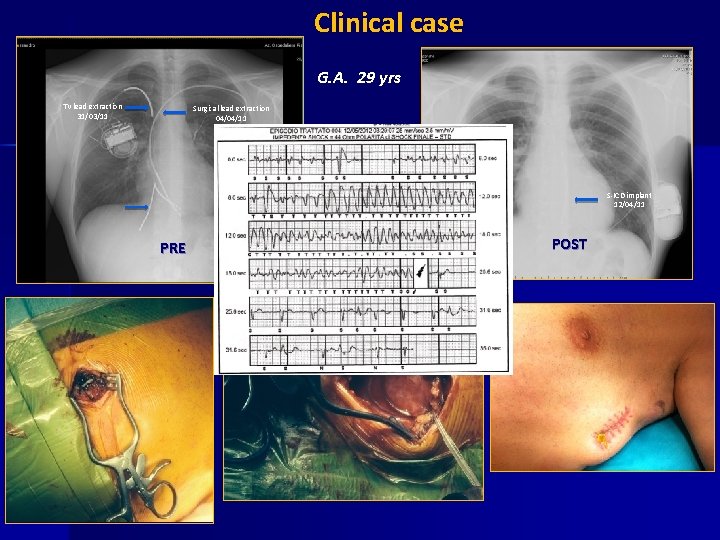
Clinical case G. A. 29 yrs TV lead extraction 31/03/11 Surgical lead extraction 04/04/11 HCM II prevention Lead endocarditis PRE Bilateral Axill-subcl. occlusion S-ICD implant 12/04/11 POST
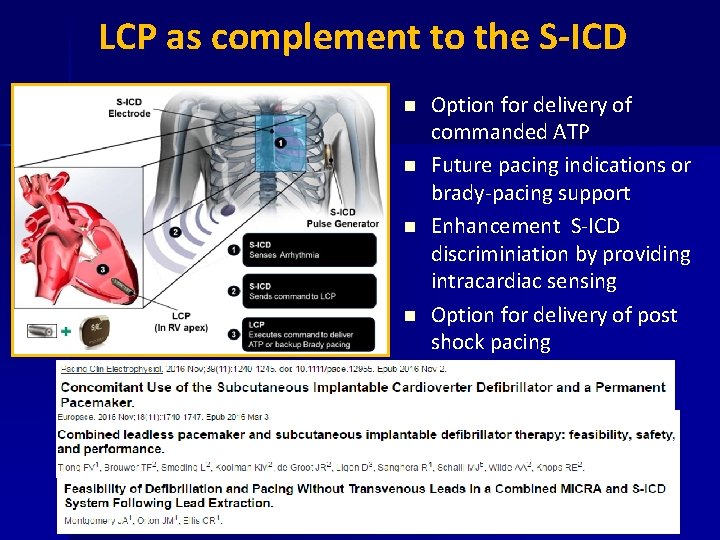
LCP as complement to the S-ICD n n Option for delivery of commanded ATP Future pacing indications or brady-pacing support Enhancement S-ICD discriminiation by providing intracardiac sensing Option for delivery of post shock pacing
CONCLUSIONS The devices of the future could be largely devoid of intravascular leads Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
“Today you don’t think of a pacemaker implantation as something sensational. Well, ladies and gentlemen, then you are all wrong. It is still a sensation-for the patient” Arne Larsson Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)
UNIVERSITY HOSPITAL of Pisa Division of Cardiovascular Diseases II LEADLESS CARDIAC PACEMAKERS: WHAT IS TO BE EXPECTED? Pisa-Washington 14/12/2016 Dr. Francesca Menichetti Dr. Maria Grazia Bongiorni Division of Cardiovascular Diseases - University Hospital of Pisa (Italy)