
Turning the tide Advancing TB Screening in Nigeria

Turning the tide Advancing TB Screening in Nigeria L. Masae Kawamura, M. D. Senior Director, Medical and Scientific Affairs, Immune and Infectious Diseases QIAGEN July 2018

DISCLAIMER I am employed by QIAGEN, maker of Quanti. FERON and other diagnostics, however the views expressed are my own in keeping with my career as a TB clinician, former TB Controller, and policy maker

Child arrives comatose from a monastery in Bhutan A preventable disaster but no policy, no program in place Diagnosis: TB meningitis After treatment: Expressive aphasia, and left-sided weakness 3

TB Control today…too little too late Consensus…. . DOTS not sufficient* • Passive detection of smear positive cases – TB already spread • Using smears under-detects TB • Stagnant incidence rates • Treatment of LTBI of young contacts and PLHIV recommended by WHO but not widely implemented TB control is a rationed approach and “waiting for TB to come” is not a logical strategy *Lonnroth et al, 2013 IJTLD 17(3): 289 -298

Global policy has changed Great shift… • • Passive TB case finding targeted active case finding Ignoring LTBI prevention essential for TB elimination Program centered PEOPLE centered STOP TB END TB 5
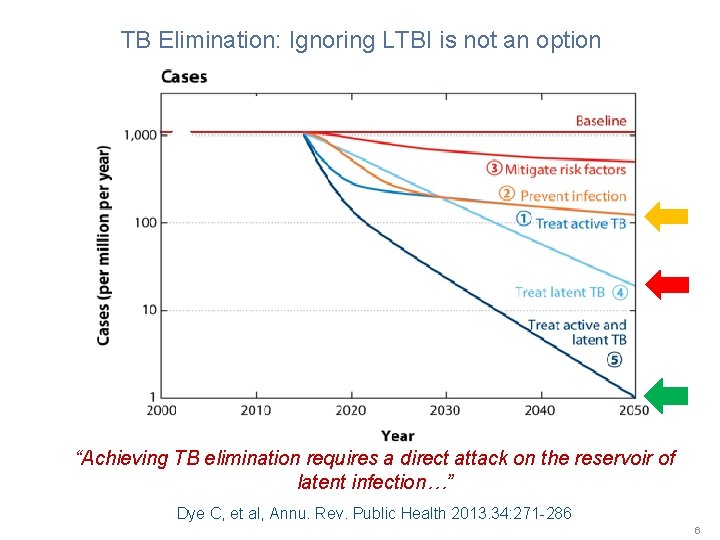
TB Elimination: Ignoring LTBI is not an option “Achieving TB elimination requires a direct attack on the reservoir of latent infection…” Dye C, et al, Annu. Rev. Public Health 2013. 34: 271 -286 6

Global policy: No more excuses All countries can apply LTBI diagnosis and treatment 7
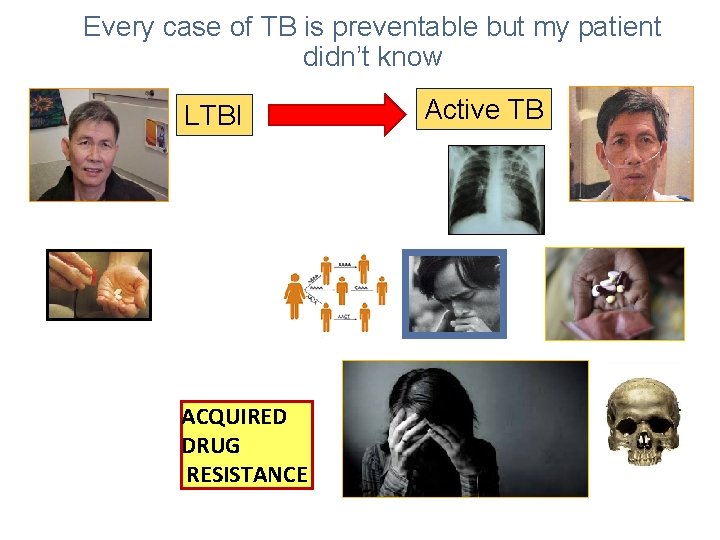
Every case of TB is preventable but my patient didn’t know LTBI ACQUIRED DRUG RESISTANCE Active TB
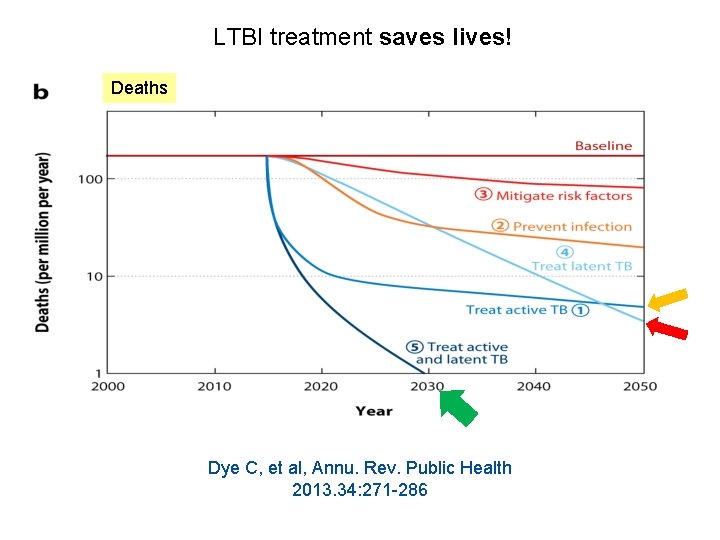
LTBI treatment saves lives! Deaths Dye C, et al, Annu. Rev. Public Health 2013. 34: 271 -286

The LTBI reservoir that ensures the future of TB HIV Diabetes migration Biologics e l p o e p n o i l l i 1. 7 b Full blown active TB ~10 -15% average lifetime risk 10
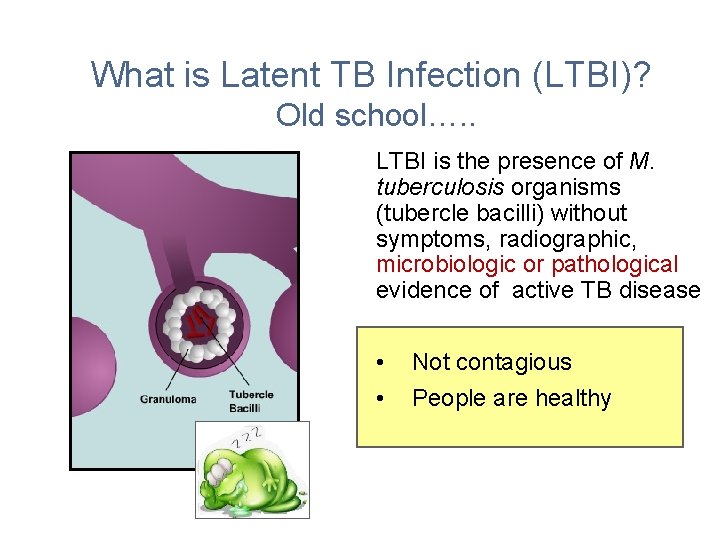
What is Latent TB Infection (LTBI)? Old school…. . LTBI is the presence of M. tuberculosis organisms (tubercle bacilli) without symptoms, radiographic, microbiologic or pathological evidence of active TB disease • • Not contagious People are healthy
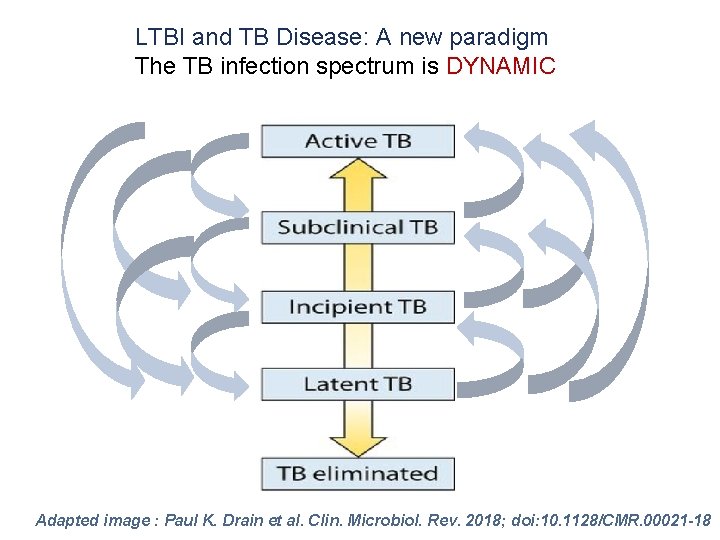
LTBI and TB Disease: A new paradigm The TB infection spectrum is DYNAMIC Adapted image : Paul K. Drain et al. Clin. Microbiol. Rev. 2018; doi: 10. 1128/CMR. 00021 -18
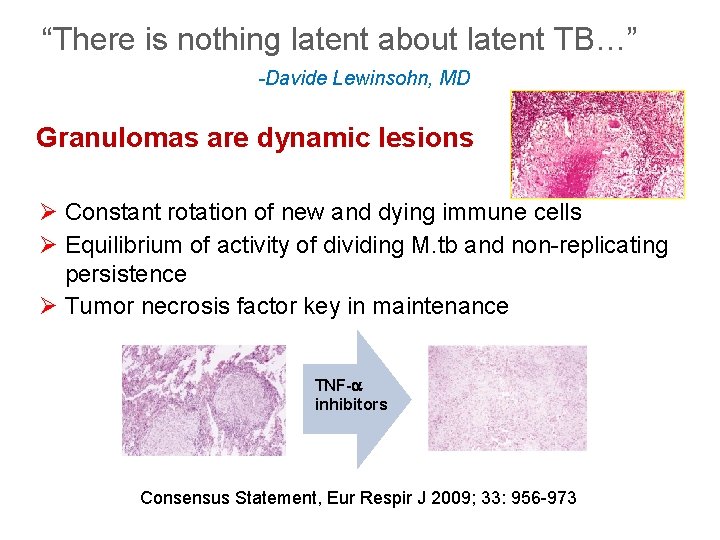
“There is nothing latent about latent TB…” -Davide Lewinsohn, MD Granulomas are dynamic lesions Ø Constant rotation of new and dying immune cells Ø Equilibrium of activity of dividing M. tb and non-replicating persistence Ø Tumor necrosis factor key in maintenance TNF- inhibitors Consensus Statement, Eur Respir J 2009; 33: 956 -973

Why should we be hopeful? 14

Call for a fundamental change The End TB Strategy and the Global Plan to End TB 2016 -2020 Launch of the Zero TB Initiative 25 July 2016 - Dubai, UAE "For a long time, we have ignored tried and tested epidemic control strategies because of a preoccupation with cost. We must ensure that people receive the care that they need regardless of where they live, “ ---Dr Salmaan Keshavjee, Director Harvard Medical School Center for Global Health Delivery http: //www. stoptb. org/news/stories/2016/ns 16_034. asp 15
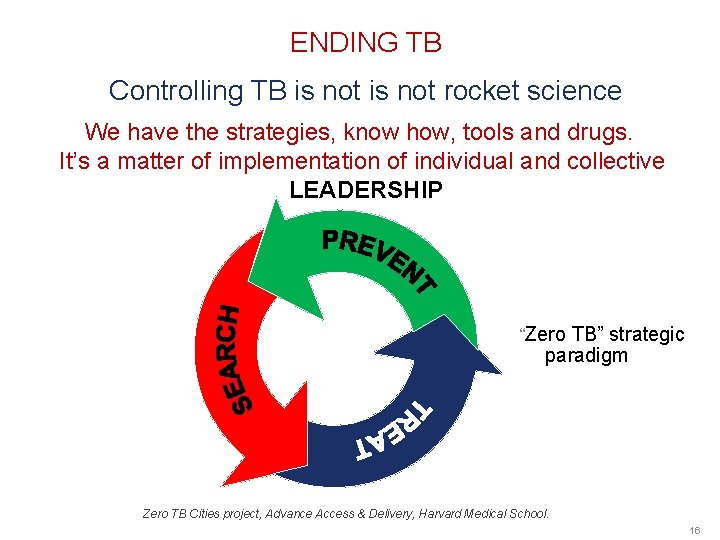
ENDING TB Controlling TB is not rocket science We have the strategies, know how, tools and drugs. It’s a matter of implementation of individual and collective LEADERSHIP “Zero TB” strategic paradigm Zero TB Cities project, Advance Access & Delivery, Harvard Medical School. 16
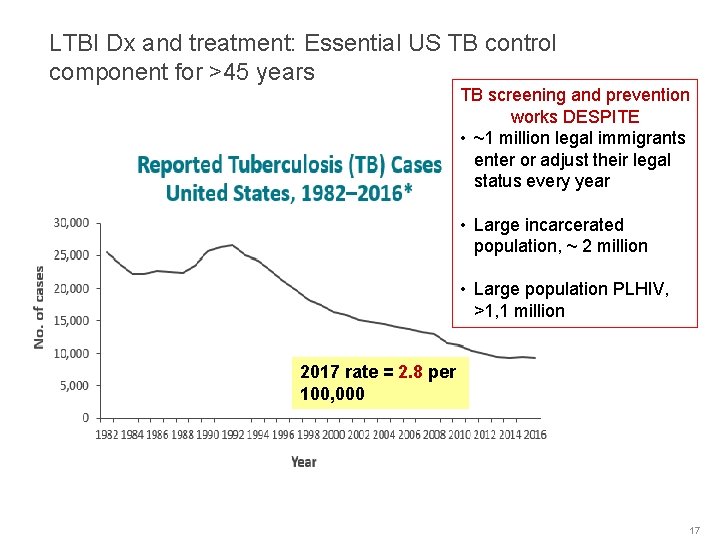
LTBI Dx and treatment: Essential US TB control component for >45 years TB screening and prevention works DESPITE • ~1 million legal immigrants enter or adjust their legal status every year • Large incarcerated population, ~ 2 million • Large population PLHIV, >1, 1 million 2017 rate = 2. 8 per 100, 000 17
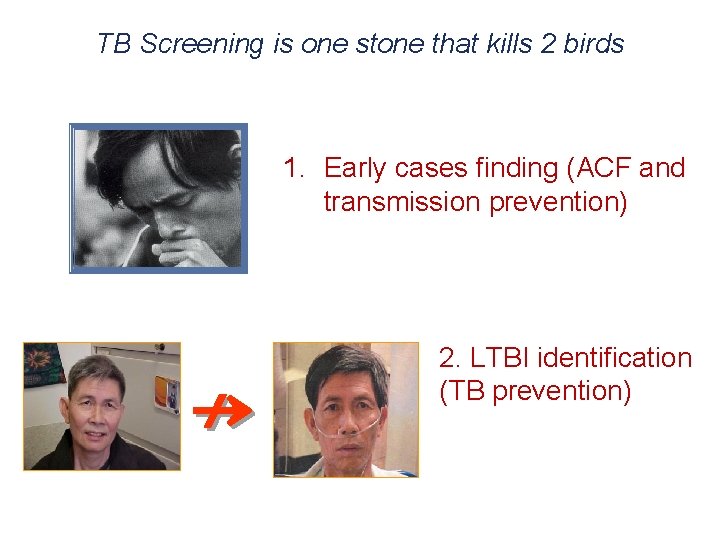
TB Screening is one stone that kills 2 birds 1. Early cases finding (ACF and transmission prevention) ↛ 2. LTBI identification (TB prevention)
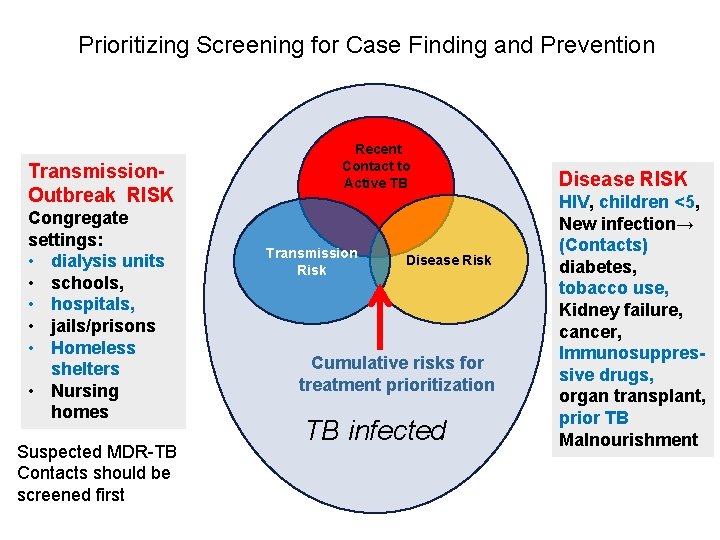
Prioritizing Screening for Case Finding and Prevention Transmission. Outbreak RISK Congregate settings: • dialysis units • schools, • hospitals, • jails/prisons • Homeless shelters • Nursing homes Suspected MDR-TB Contacts should be screened first Recent Contact to Active TB Transmission Risk Disease Risk Cumulative risks for treatment prioritization TB infected Disease RISK HIV, children <5, New infection→ (Contacts) diabetes, tobacco use, Kidney failure, cancer, Immunosuppressive drugs, organ transplant, prior TB Malnourishment
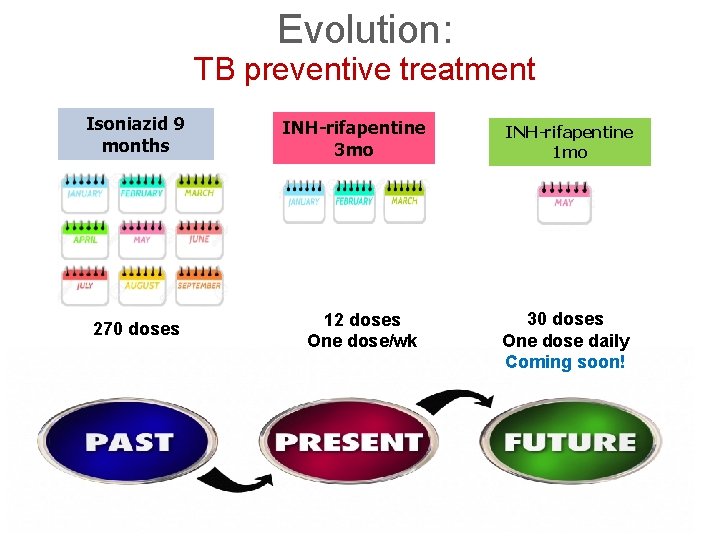
Evolution: TB preventive treatment Isoniazid 9 months 270 doses INH-rifapentine 3 mo 12 doses One dose/wk INH-rifapentine 1 mo 30 doses One dose daily Coming soon!
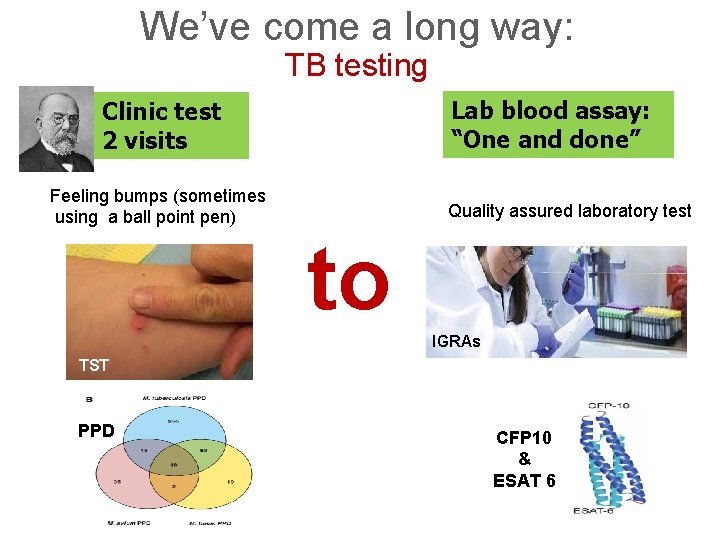
We’ve come a long way: TB testing Lab blood assay: “One and done” Clinic test 2 visits Feeling bumps (sometimes using a ball point pen) Quality assured laboratory test to IGRAs TST PPD CFP 10 & ESAT 6
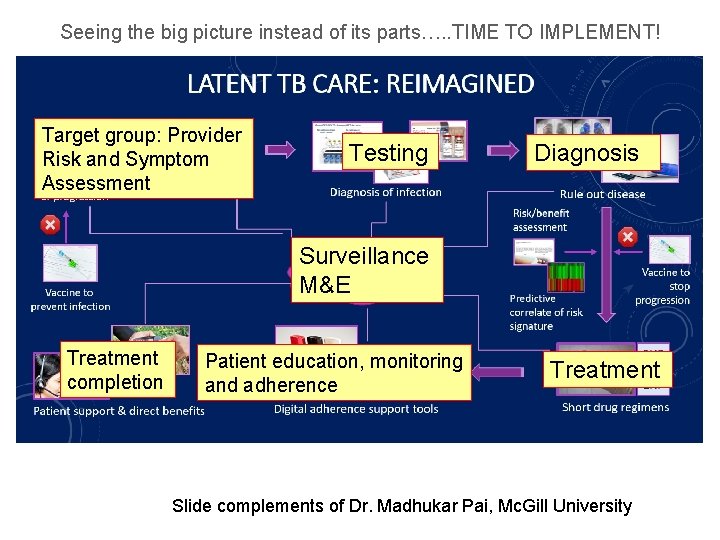
Seeing the big picture instead of its parts…. . TIME TO IMPLEMENT! Target group: Provider Risk and Symptom Assessment Testing Diagnosis Surveillance M&E Treatment completion Patient education, monitoring and adherence Treatment Slide complements of Dr. Madhukar Pai, Mc. Gill University
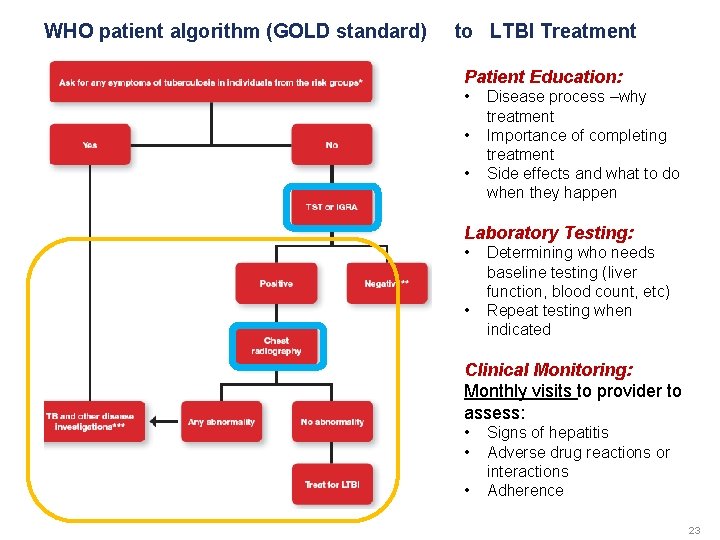
WHO patient algorithm (GOLD standard) to LTBI Treatment Patient Education: • • • Disease process –why treatment Importance of completing treatment Side effects and what to do when they happen Laboratory Testing: • • Determining who needs baseline testing (liver function, blood count, etc) Repeat testing when indicated Clinical Monitoring: Monthly visits to provider to assess: • • • Signs of hepatitis Adverse drug reactions or interactions Adherence 23
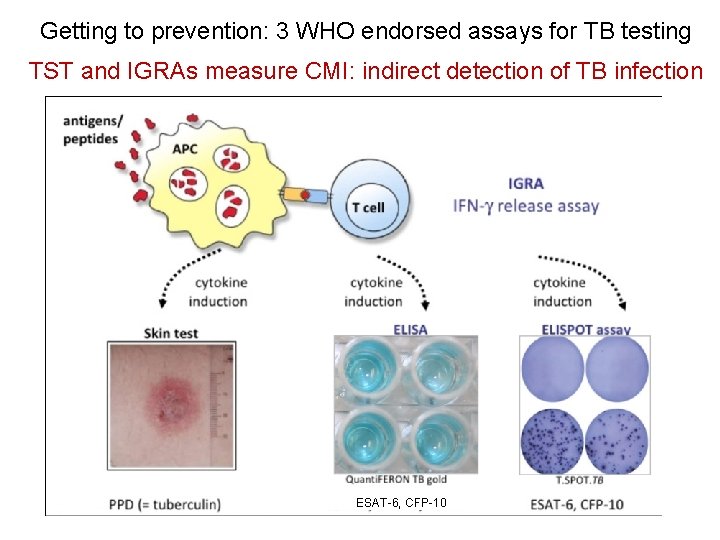
Getting to prevention: 3 WHO endorsed assays for TB testing TST and IGRAs measure CMI: indirect detection of TB infection ESAT-6, CFP-10
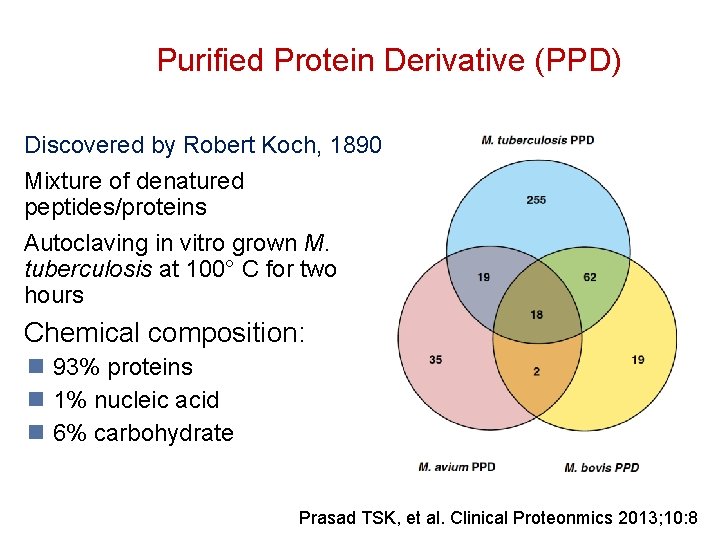
Purified Protein Derivative (PPD) Discovered by Robert Koch, 1890 Mixture of denatured peptides/proteins Autoclaving in vitro grown M. tuberculosis at 100° C for two hours Chemical composition: 93% proteins 1% nucleic acid 6% carbohydrate Prasad TSK, et al. Clinical Proteonmics 2013; 10: 8
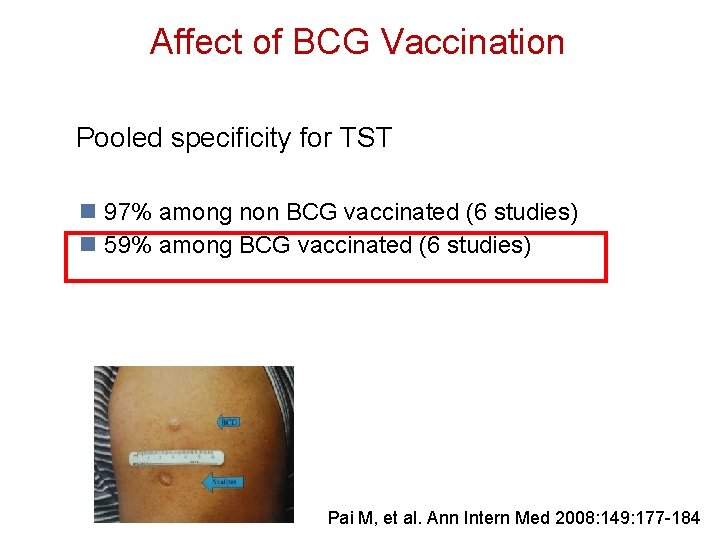
Affect of BCG Vaccination Pooled specificity for TST 97% among non BCG vaccinated (6 studies) 59% among BCG vaccinated (6 studies) Pai M, et al. Ann Intern Med 2008: 149: 177 -184

CAUTION: LIMITATIONS of IGRAs are the same as the TST …. . § CANNOT distinguish between old and new infection (however QFT-Plus may change this!) § NOT PERFECT: can be impacted by severe immunosuppression § False negatives results: CANNOT rule out active TB or LTBI in severely immunosuppressed individuals § SHOULD NOT be used to monitor treatment However, IGRAs CAN distinguish between BCG and true TB infection and most environmental NTM (Exceptions: M kansasii, M sulgai, M marinum)
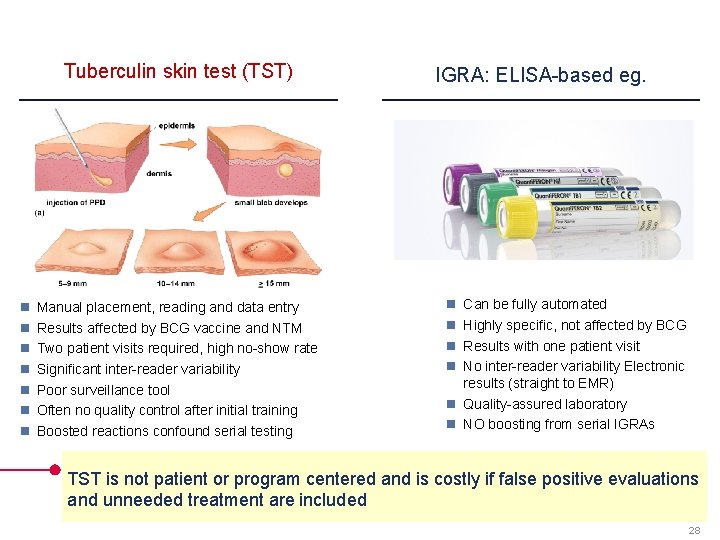
Tuberculin skin test (TST) Manual placement, reading and data entry Results affected by BCG vaccine and NTM Two patient visits required, high no-show rate Significant inter-reader variability Poor surveillance tool Often no quality control after initial training Boosted reactions confound serial testing IGRA: ELISA-based eg. Can be fully automated Highly specific, not affected by BCG Results with one patient visit No inter-reader variability Electronic results (straight to EMR) Quality-assured laboratory NO boosting from serial IGRAs TST is not patient or program centered and is costly if false positive evaluations and unneeded treatment are included 28
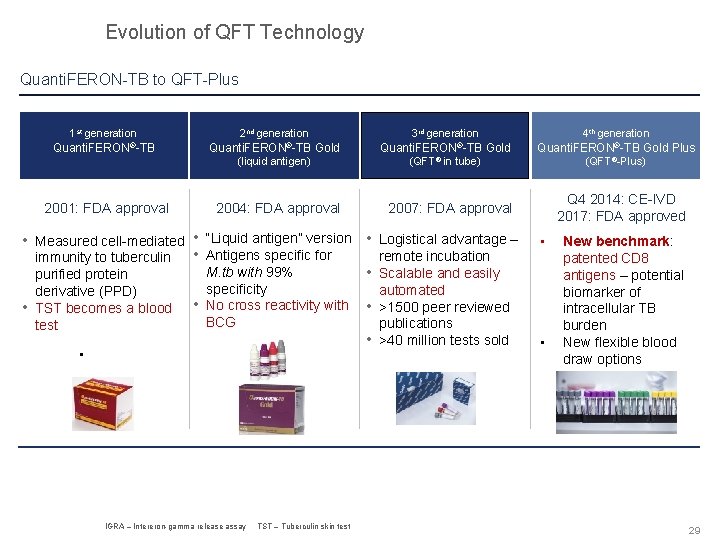
Evolution of QFT Technology Quanti. FERON-TB to QFT-Plus 2 nd generation 1 st generation Quanti. FERON®-TB 3 rd generation Gold Quanti. FERON®-TB (liquid antigen) Gold • • specificity No cross reactivity with BCG • IGRA – Intereron-gamma release assay TST – Tuberculin skin test (QFT®-Plus) Q 4 2014: CE-IVD 2017: FDA approved 2007: FDA approval • Measured cell-mediated • “Liquid antigen” version • Logistical advantage – • Antigens specific for remote incubation immunity to tuberculin M. tb with 99% • Scalable and easily purified protein derivative (PPD) TST becomes a blood test Quanti. FERON®-TB Gold Plus (QFT® in tube) 2004: FDA approval 2001: FDA approval 4 th generation • • automated >1500 peer reviewed publications >40 million tests sold • • New benchmark: patented CD 8 antigens – potential biomarker of intracellular TB burden New flexible blood draw options 29
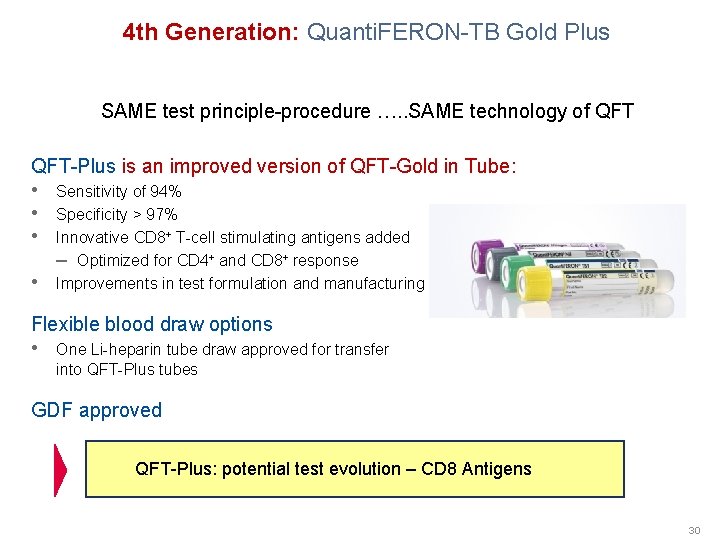
4 th Generation: Quanti. FERON-TB Gold Plus SAME test principle-procedure …. . SAME technology of QFT-Plus is an improved version of QFT-Gold in Tube: • Sensitivity of 94% • Specificity > 97% • Innovative CD 8+ T-cell stimulating antigens added – Optimized for CD 4+ and CD 8+ response • Improvements in test formulation and manufacturing Flexible blood draw options • One Li-heparin tube draw approved for transfer into QFT-Plus tubes GDF approved QFT-Plus: potential test evolution – CD 8 Antigens 30
QFT-Plus with 35 publications and growing: New benchmark and moving the field of LTBI forward… • CD 8 responses correspond to new infection in contacts, exposure and TB burden in active TB (Barcellini 2016, Petruccioli 2017, Pieterman 2017, Gurjav 2019, Lee 2019) • Compared to QFT-GIT, QFT-Plus with higher sensitivity in the elderly • Unlike QFT-GIT, QFT-Plus results do not appear impacted by HIV status and less impacted by CD 4 count (Telisinghe 2017, Walles 2018 pregnancy study, Fukushima (Chien 2018, Fukushima-2018) • In direct comparison studies in active TB and rheumatoid arthritis patients, QFT-Plus is significantly more sensitive than elispot (2018 Fukushima 2018, Igari 2018) 31
Limitations of current IGRAs (rationale for continued TST use) ■ Current IGRAs require high complexity and skilled laboratories ■ No alternative to TST in places without access to labs. But, issues associated with the TST are: • Poor specificity in BCG vaccinated • Requires 2 visits for results • Short expiration ~ 6 months unopened, 30 days if vial opened • Manual administration with specialized training • Requires established cold chain • Reading results is subjective • Poor research tool due to boosting • Global shortage of tuberculin remains an ongoing problem GAP No “field friendly” IGRA with the advantages of lab-based results 32

Quanti. FERON® TB Access (QFT Access) The field-friendly and portable IGRA solution with more advantages than the TST without the need for a laboratory No cold chain or maintenance with battery back up Single tube and simple work flow Day 2 electronic results within 20 minutes Launch: 2020 33

TB Elimination: What will it take? § Leadership, commitment, and vision May NIGERIA be the light for Africa! § Local program strengthening and investment to take on comprehensive disease control approach: SEARCHTREAT-PREVENT with current tools § Prioritization is the key. Targeting high risk groups for TB screening will have the maximum impact in reducing country TB burden (ACF and Prevention) § Go beyond status quo: Demand what is needed rather than what the program can afford § SOLIDARITY

Thank you! Title, Location, Date 35
Must read reference: Lancet 2015 4 -part series on TB Elimination • Roadmap for elimination and its scientific underpinnings • Addresses changes needed to current strategy to achieve zero deaths and reach 2015 elimination in high burden settings • Provides comprehensive disease epidemic control approach 1. 2. 3. 4. Targeting local hotspots of transmission Active case-finding Initiating correct therapy promptly Preventing future transmission by treating high-risk individuals and TB contacts with LTBI Controlling the seedbeds of tuberculosis: diagnosis and treatment of tuberculosis infection Rangaka MX, Chaison R et al, Lancet 2015; published online Oct 26. http: //dx. doi. org/10. 1016/ S 0140 -6736(15)00323 -2. 36
- Slides: 36