
Trattamento del dolore postoperatorio nel paziente grande obeso

Trattamento del dolore postoperatorio nel paziente grande obeso J P Mulier MD Ph. D David Blacoe, MD Sint Jan Brugge-Oostende www. publicationslist. org/jan. mulier JPMulier Pordenone 19 09 2009 1

Pain is not treated sufficient in obese patients P Rubens n Obesity is an independent risk factor for having post operative pain and need for extra intervention early after awakening. n retrospective study in 1736 patients under general anaesthesia. n n Mei W. et al Eur J Pain. 2009 Large gaps remains in peri operative pain treatment of obese patients. n Best practice recommendation on peri operative care and pain treatment for weight loss surgery. n Schumann R Obesity 2009 JPMulier Pordenone 19 09 2009 2

Post operative pain is a weighty problem. but more frequent in children, elderly and also in overweight patients WHY ? JPMulier Pordenone 19 09 2009 3

Insufficient pain treatment in n Elderly Paediatric Obese Because of Drug studies performed on healthy adults n Dosage difficulty, n n Afraid of hypoventilation, sleep apnoea Access difficulty, n Physician not familiar with n n Basic scientific knowledge is missing JPMulier Pordenone 19 09 2009 4

Pain treatment in elderly is different but need attention n Frequent underreporting of pain tend to under treating pain. n Pergolezi 2008 consensus meeting elderly and pain Response to mild pain is reduced, but elderly are more sensitive to severe pain. n The elderly respond better to Opiods treatment. n n Likar n et al. 2009 However we are more afraid of overdose and sedation. JPMulier Pordenone 19 09 2009 5

Dosage in geriatrics n Based on pharmacokinetics n Give less in mg/kg body weight to achieve the same plasma level n Based on pharmacodynamics n Give less as effect and side effects are stronger. n Based on metabolism and elimination n Give less frequent as elimination is slower We tend to lower too much and pain is insufficient treated 6 JPMulier Pordenone 19 09 2009

Paediatrics: Not one group Neonates n Infants n Children n Young adults n n Differences in Body water content n Serum protein composition n Capacity for hepatic biotransformation n JPMulier Pordenone 19 09 2009 7

Children n Based on pharmacokinetics n Hydrophilic drugs with a n high V(d) should be normalised to bodyweight n Low V(d) should be normalised to body surface area (BSA) n Based on developmental physiology n Give less when liver or renal function is not mature. n Individual adapted therapy JPMulier Pordenone 19 09 2009 8

Pain treatment in children n 1. 2. 3. lack of knowledge, a deficiency of standardized protocols the lack of administrative responsibility. Approach: The prevention The algorithm for analgesic treatment The evaluation of the efficiency and give extra pain medication. 9 JPMulier Pordenone 19 in 09 2009 Peri operative pain therapy children H Heinrich 2002

What do we know of pain treatment in morbid obese patients? Frequent under treatment n Stronger reaction to mild pain n n Putting an infusion line is more painful n Reaction more like a child Need more pain killers n Not one group: n n Obese – severe obese - morbid obese – super obese. n Still a lot to investigate! JPMulier Pordenone 19 09 2009 10

Obesity: body composition Dosage based on ? n Ideal body weight is not enough - total body weight is too much Increased blood volume and CO n Increased extra cellular water but not according to body weight (relative more fat ) Increased renal clearance, increased hepatic clearance. n Increased protein binding n Chumlea W body water status in obese J nutr Health Aging 11 2007 JPMulier Pordenone 19 09 2009

Local anaesthetics n Local infiltration: n Growing interest for wound infiltration and use of elastomer pumps. n However not efficient in laparoscopic surgery n Loco regional anaesthesia n Great value but difficult to puncture? n Larger loading dose, but increased spread, prolonged effects. JPMulier Pordenone 19 09 2009 12
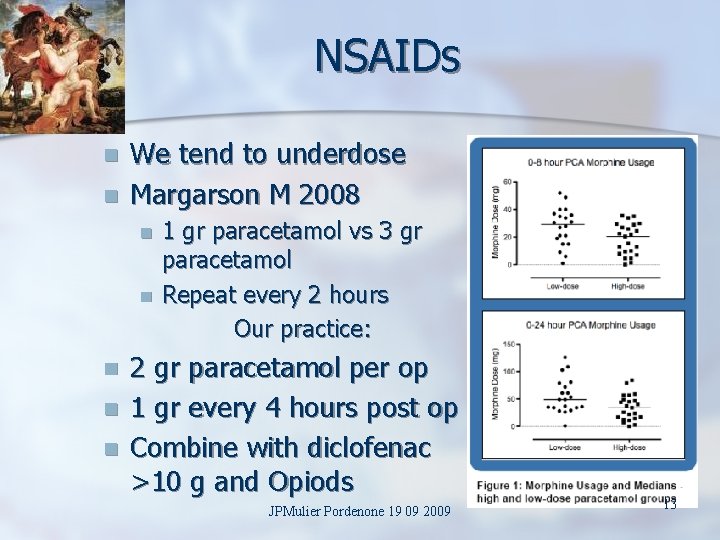
NSAIDs n n We tend to underdose Margarson M 2008 n n n 1 gr paracetamol vs 3 gr paracetamol Repeat every 2 hours Our practice: 2 gr paracetamol per op 1 gr every 4 hours post op Combine with diclofenac >10 g and Opiods JPMulier Pordenone 19 09 2009 13
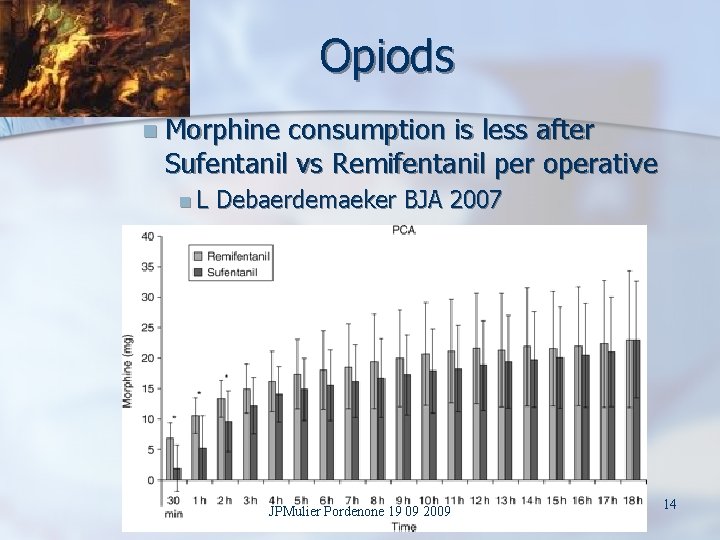
Opiods n Morphine consumption is less after Sufentanil vs Remifentanil per operative n. L Debaerdemaeker BJA 2007 JPMulier Pordenone 19 09 2009 14

Opiods n n n Use high dose of Sufentanil at start of operation (25 ug) Use Remifentanil infusion on top to improve hemodynamic stability Use post op morphine 25 % more than in non obese according to patients need. n n n Formula? Opiods are Part of a Multimodal therapy PCIA is preferable JPMulier Pordenone 19 09 2009 15

Our Results in lap RNY n 260 revision from prev RNY JPMulier Pordenone 19 09 2009 16

Conclusion Work multimodal n Use ideal body weight +25 % to calculate dose Opiods n Double NSAIDs dose n Start per operative your pain management n Combine with local infiltration and loco regional if possible n Adapt individual n JPMulier Pordenone 19 09 2009 17

Food consumption inhibits pain n Mason P Ann N Y Acad Sci. 2009 n Eating analgesia does not depend on energydepletion n sucrose is not a necessary component of analgesia-evoking ingestates early oral feeding: new pain therapy? Pieter Breughel Farmers festivity: 1500 JPMulier Pordenone 19 09 2009 18

ESPCOP Secretary Luc De baerdemaeker Treasurer Nick Kennedy President Jan P Mulier Vice-President Yigal Leykin www. publicationslsit. org/ESPCOP www. espcop. org JPMulier Pordenone 19 09 2009 19

Attend first ESPCOP meeting 14 nov 2009 Ostend Belgium n “The sea” from Georges Grard n Better known as “fat Mathilde of Ostend” JPMulier Pordenone 19 09 20

Scientific meeting JPMulier Pordenone 19 09 2009 21

Pieter Paul Rubens n n 1577 – 1640 Antwerp Belgium Flemish baroque painter with Italian influence n n Venetia, Florence, Rome Morbid obese was the ideal body shape of the rich class Naked obese woman as a sign of wealth More info: n n jan. mulier@azbrugge. be www. publicationslist. org/jan. mulier JPMulier Pordenone 19 09 2009 22
- Slides: 22