
Transient Cardiac Disease Rachel Aubrey Patient One 54

Transient Cardiac Disease Rachel Aubrey

Patient One. 54 yo man presents with chest pain Pm. Hx: T 2 DM CKD – stage IV- V kidney disease, e. GFR 15%, due to start peritoneal dialysis Medications: Insulin Inhibace plus Metoprolol HTN Aspirin Ex smoker Calcium High BMI Alu-tabs Neorecormon NKDA

Patient One. 54 yo man presents with chest pain Hx. PC: Pain is sharp located in the anterior and central chest radiating to the neck and shoulders. Onset 4 hours ago, took paracetamol at home with nil effect. Ongoing so presents to ED. Associated with dyspnoea, no nausea or diaphoresis. Worse when laying flat, with inspiration and swallowing. Chronic peripheral oedema unchanged. No calf pain or swelling, prolonged immobility/surgery, haemoptysis, history of malignancy, history of VTE. Possible fevers at home. No cough/cold/ coryza or gastrointestinal symptoms. Longstanding history of poor exertional capacity with occasional chest pain, normal ETT 3 years ago.
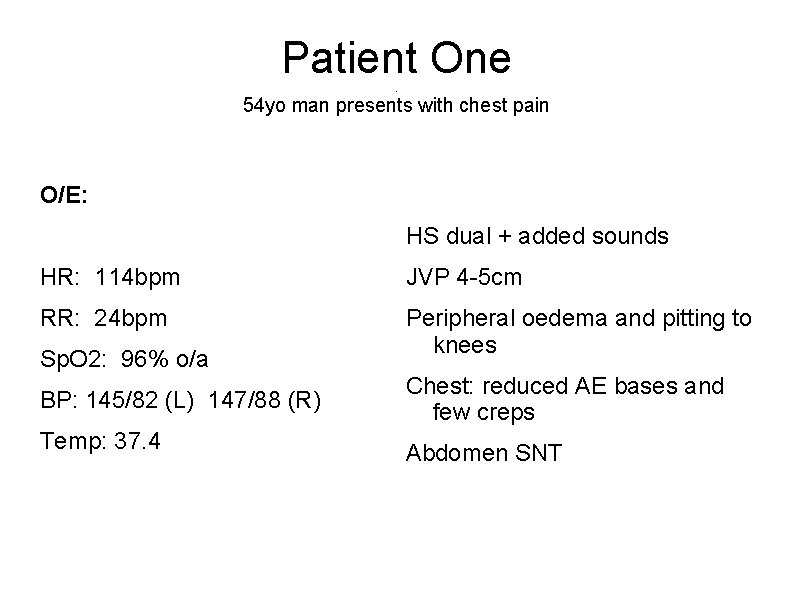
Patient One. 54 yo man presents with chest pain O/E: HS dual + added sounds HR: 114 bpm JVP 4 -5 cm RR: 24 bpm Peripheral oedema and pitting to knees Sp. O 2: 96% o/a BP: 145/82 (L) 147/88 (R) Temp: 37. 4 Chest: reduced AE bases and few creps Abdomen SNT
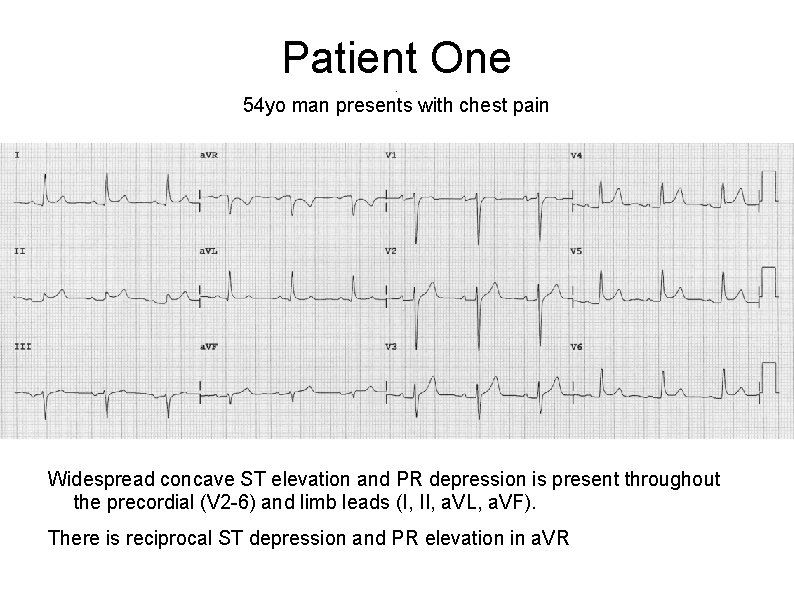
Patient One. 54 yo man presents with chest pain Widespread concave ST elevation and PR depression is present throughout the precordial (V 2 -6) and limb leads (I, II, a. VL, a. VF). There is reciprocal ST depression and PR elevation in a. VR
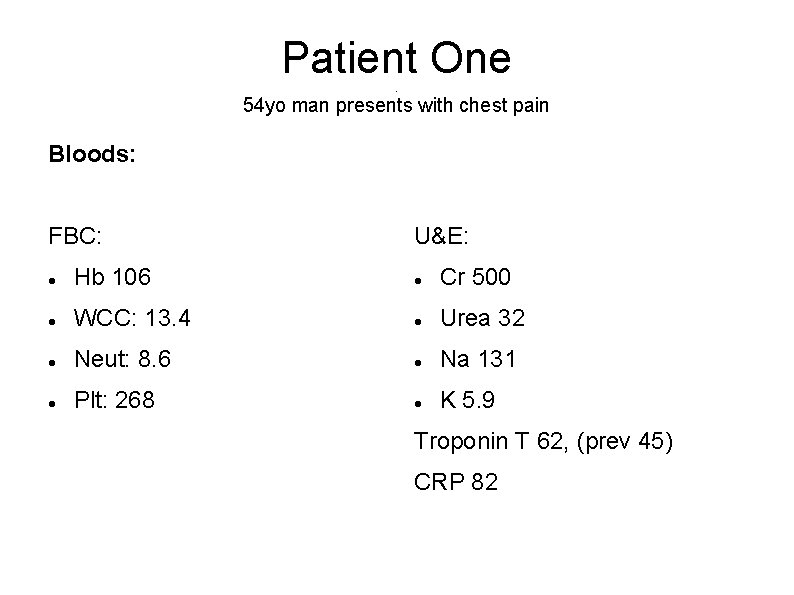
Patient One. 54 yo man presents with chest pain Bloods: FBC: U&E: Hb 106 Cr 500 WCC: 13. 4 Urea 32 Neut: 8. 6 Na 131 Plt: 268 K 5. 9 Troponin T 62, (prev 45) CRP 82
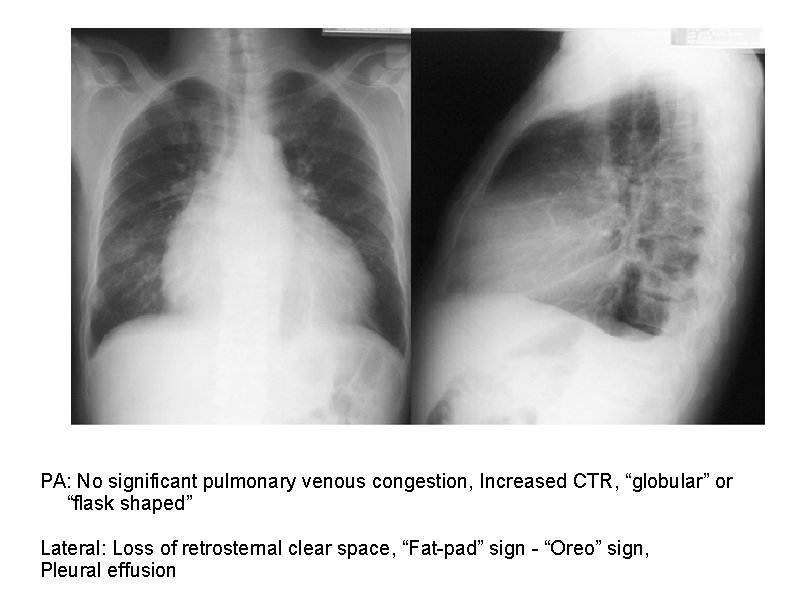
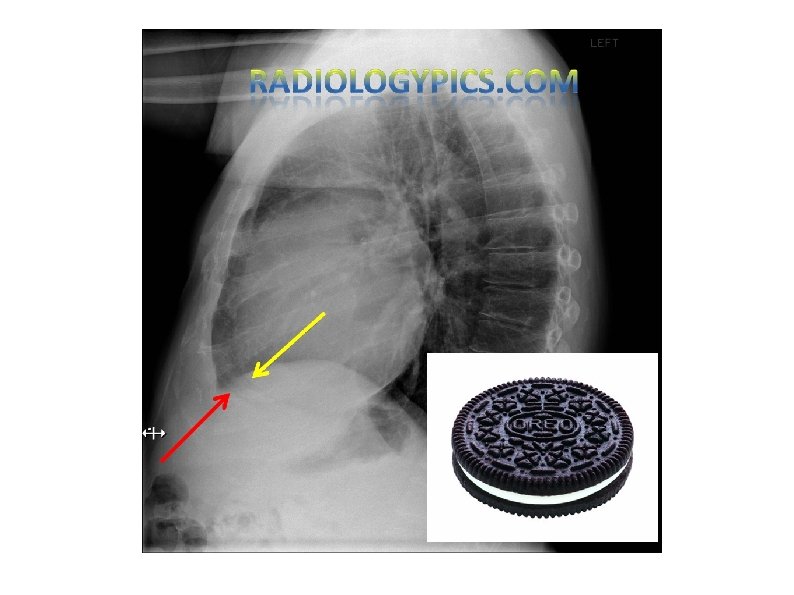
PA: No significant pulmonary venous congestion, Increased CTR, “globular” or “flask shaped” Lateral: Loss of retrosternal clear space, “Fat-pad” sign - “Oreo” sign, Pleural effusion
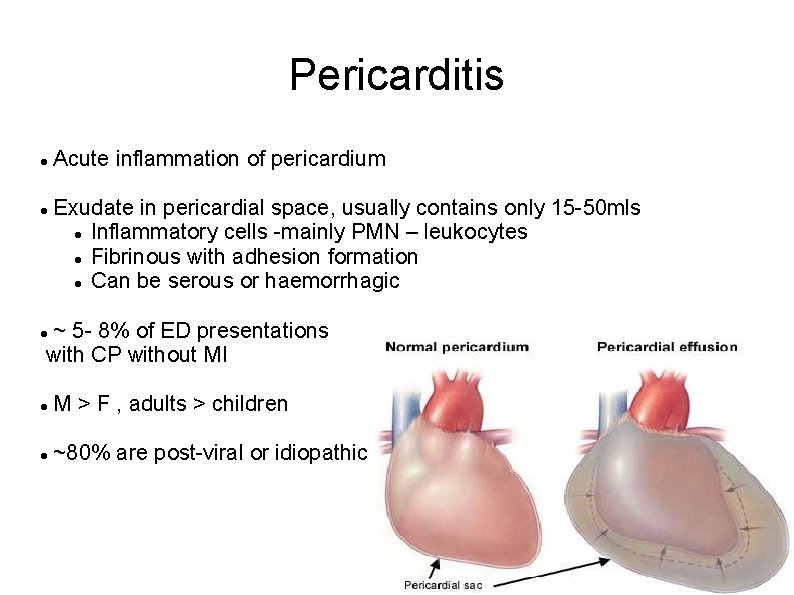
Pericarditis Acute inflammation of pericardium Exudate in pericardial space, usually contains only 15 -50 mls Inflammatory cells -mainly PMN – leukocytes Fibrinous with adhesion formation Can be serous or haemorrhagic ~ 5 - 8% of ED presentations with CP without MI M > F , adults > children ~80% are post-viral or idiopathic

Causes Infectious: Viral (HIV, CMV, coxsackie*) Bacterial (tuberculosis) Fungal Inflammatory: SLE* Scleroderma ANCA-associated vasculitis Metabolic: Hypothyroidism Neoplastic: Metastatic Primary Medications: Hydralazine* Methyldopa Procainamide* Minoxidil Other: Idiopathic (procedures) Blunt or penetrating Post-MI (Dressler’s syndrome)* Myocardial infarction Uraemia * * Common causes
Uraemic Pericarditis Manifestations of pericarditis before RRT or within 8 weeks of starting (dialysis pericarditis affects those on RRT for > 8 weeks) Common at autopsy 50% or uraemic patients have pericarditis. More common in younger patients and in women. Higher incidence of haemorrhagic effusion Caused by accumulation of uraemic toxins. Good response from dialysis – 76% recover. [ Dialysis – Due to inadequate dialysis, possibly substrates of dialysis, poorer response to dialysis and more likely to be subacute, more likely to be complicated by adhesions]
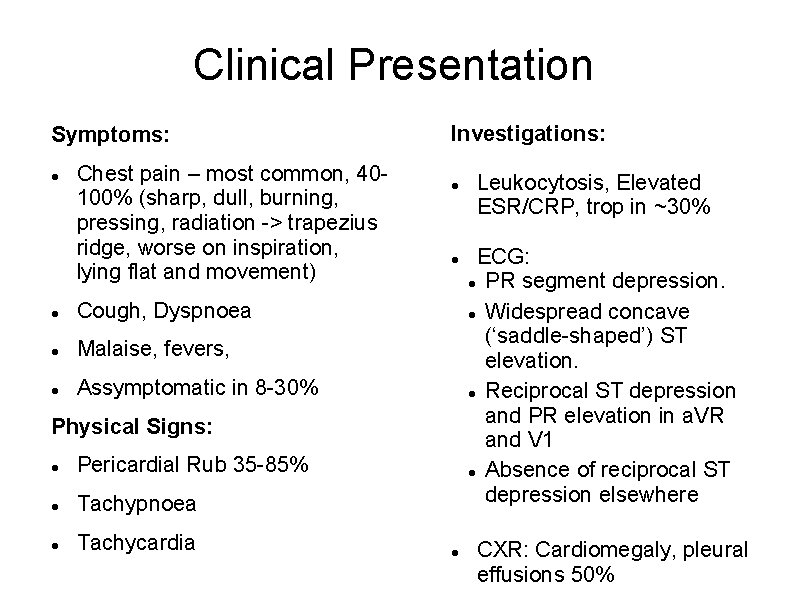
Clinical Presentation Symptoms: Chest pain – most common, 40100% (sharp, dull, burning, pressing, radiation -> trapezius ridge, worse on inspiration, lying flat and movement) Cough, Dyspnoea Malaise, fevers, Assymptomatic in 8 -30% Investigations: Physical Signs: Pericardial Rub 35 -85% Tachypnoea Tachycardia Leukocytosis, Elevated ESR/CRP, trop in ~30% ECG: PR segment depression. Widespread concave (‘saddle-shaped’) ST elevation. Reciprocal ST depression and PR elevation in a. VR and V 1 Absence of reciprocal ST depression elsewhere CXR: Cardiomegaly, pleural effusions 50%
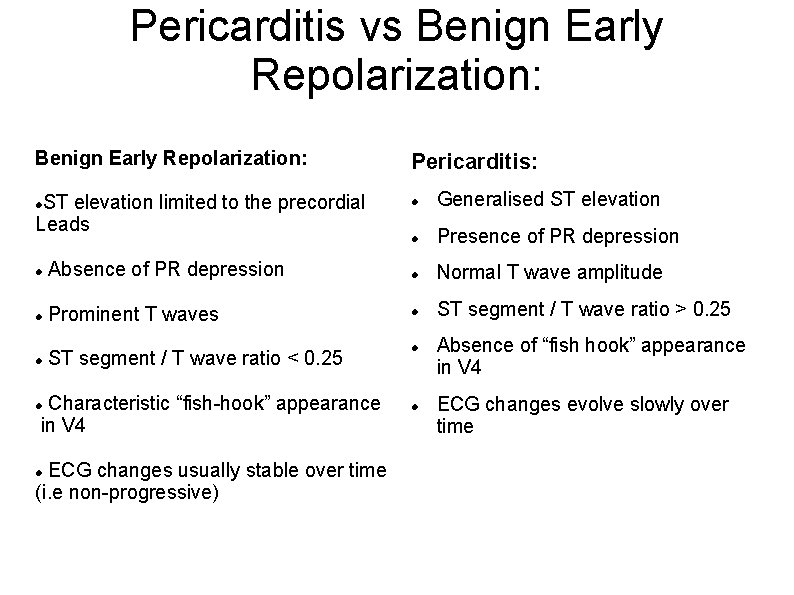
Pericarditis vs Benign Early Repolarization: ST elevation limited to the precordial Leads Pericarditis: Generalised ST elevation Presence of PR depression Normal T wave amplitude ST segment / T wave ratio > 0. 25 Absence of PR depression Prominent T waves ST segment / T wave ratio < 0. 25 Characteristic “fish-hook” appearance in V 4 ECG changes usually stable over time (i. e non-progressive) Absence of “fish hook” appearance in V 4 ECG changes evolve slowly over time
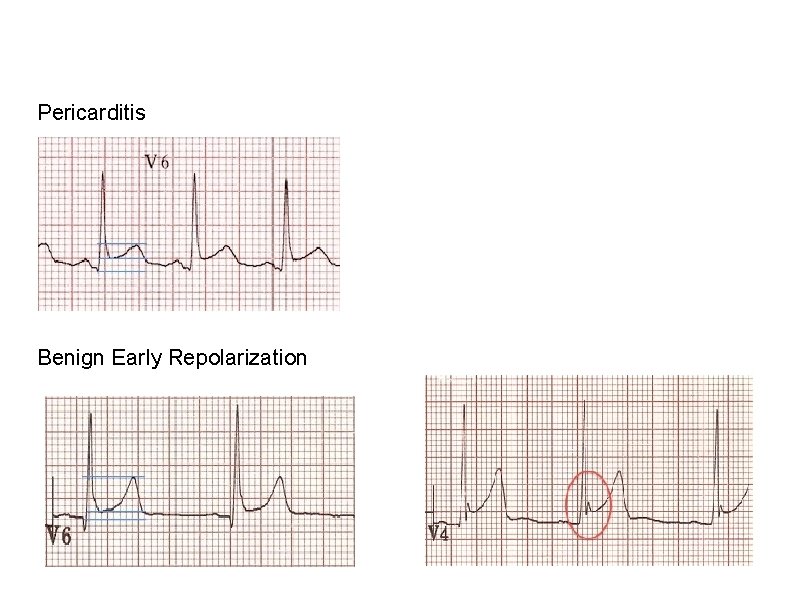
Pericarditis Benign Early Repolarization
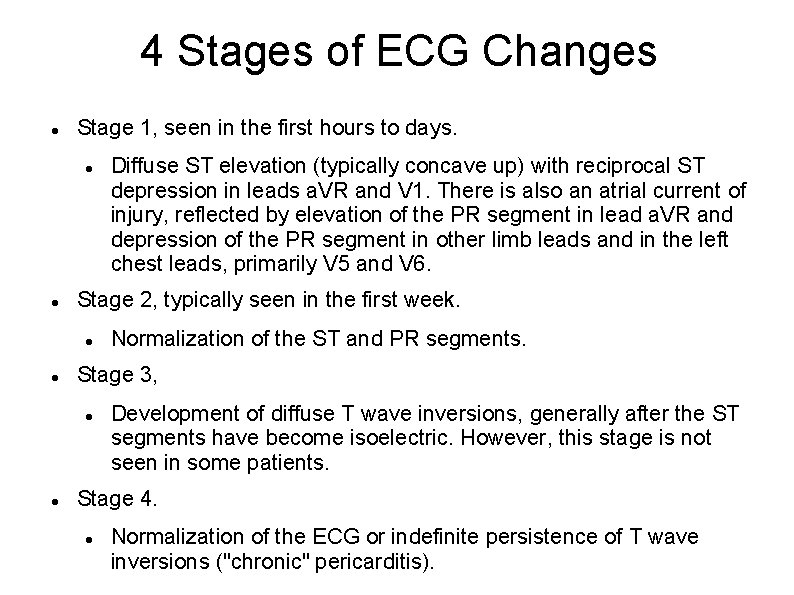
4 Stages of ECG Changes Stage 1, seen in the first hours to days. Stage 2, typically seen in the first week. Normalization of the ST and PR segments. Stage 3, Diffuse ST elevation (typically concave up) with reciprocal ST depression in leads a. VR and V 1. There is also an atrial current of injury, reflected by elevation of the PR segment in lead a. VR and depression of the PR segment in other limb leads and in the left chest leads, primarily V 5 and V 6. Development of diffuse T wave inversions, generally after the ST segments have become isoelectric. However, this stage is not seen in some patients. Stage 4. Normalization of the ECG or indefinite persistence of T wave inversions ("chronic" pericarditis).
Diagnosis Acute pericarditis is diagnosed by the presence of at least two of the following criteria: Typical chest pain (sharp and pleuritic, improved by sitting up and leaning forward) Pericardial friction rub (a superficial scratchy or squeaking sound best heard with the diaphragm of the stethoscope over the left sternal border) – may need repeat exams. Suggestive changes on the electrocardiogram (typically widespread ST segment elevation) New or worsening pericardial effusion Investigations: bloods inc CRP, ESR, Trop and cultures if febrile, ECG – all CXR – all Echo – tamponade, purrulent infection, myocarditis

Management: Rule out differential causes Stable → Outpatient mx: NSAIDs +/- colchicine If persistent >1 week need further investigation Management of complications: If tamponade is suspected → Echo (gold std) R/V meds – anti coagulants, contributing meds Admit if: Effusion – large, tamponade Fever, leukocytosis, immunocompromised On warfarin Traumatic Trop rise – (myopericarditis) > 1 week, not responding to NSAIDs Tachycardia, tachypnoea, hypotension, signs of hypoperfusion, distended neck veins, muffled heart sounds, pulsus paradoxus, 'Becks triad' Pericardiocentesis – subxiphoid if emergent. Restrictive pericarditis requires resection. Persistent (>1 week) requires further investigation.

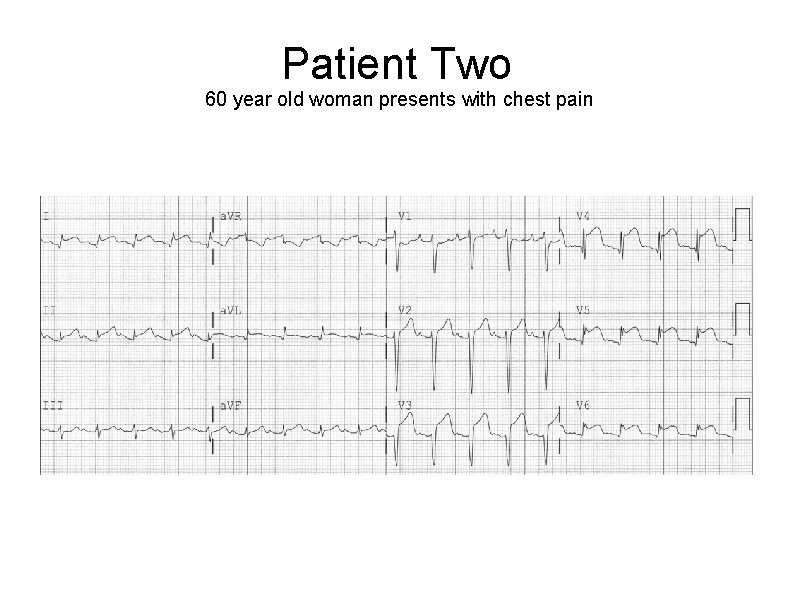
Patient Two Hx. PC: 60 year old woman presents with chest pain 60 yr old woman was upstairs with her husband who is a patient on a medical ward. During a family meeting she began to report central chest pain and presents to ED immediately. She looks unwell and is taken into monitored. On arrival she reports: - Ongoing retrosternal chest heaviness - Non radiating - Associated nausea and dyspnoea, nil other associated symptoms - Has been otherwise well. Pm. Hx: Hypothyroidism on thyroxine, hyperlipidaemia, No cardiac hx, HTN, T 2 DM, non smoker and no family hx of IHD
Patient Two 60 year old woman presents with chest pain

Patient Two 60 year old woman presents with chest pain Management: Moved to Resus and activate STEMI protocol Quick bedside examination: BP 140/90, HR 80, Sp. O 2 98%, HS dual non added, chest clear . IVL placed on the ward and bloods return with troponin T of 140, Given aspirin, heparin bolus and ticagrelor Transferred to Cath Lab
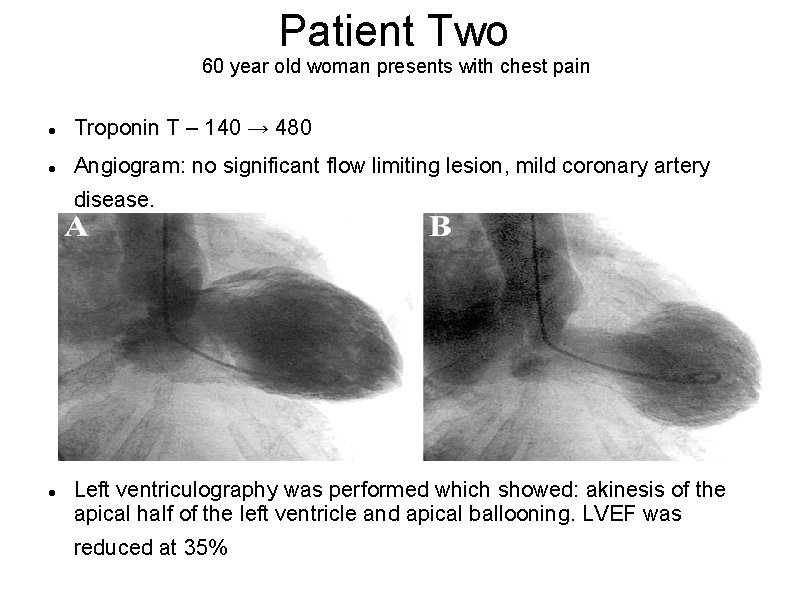
Patient Two 60 year old woman presents with chest pain Troponin T – 140 → 480 Angiogram: no significant flow limiting lesion, mild coronary artery disease. Left ventriculography was performed which showed: akinesis of the apical half of the left ventricle and apical ballooning. LVEF was reduced at 35%
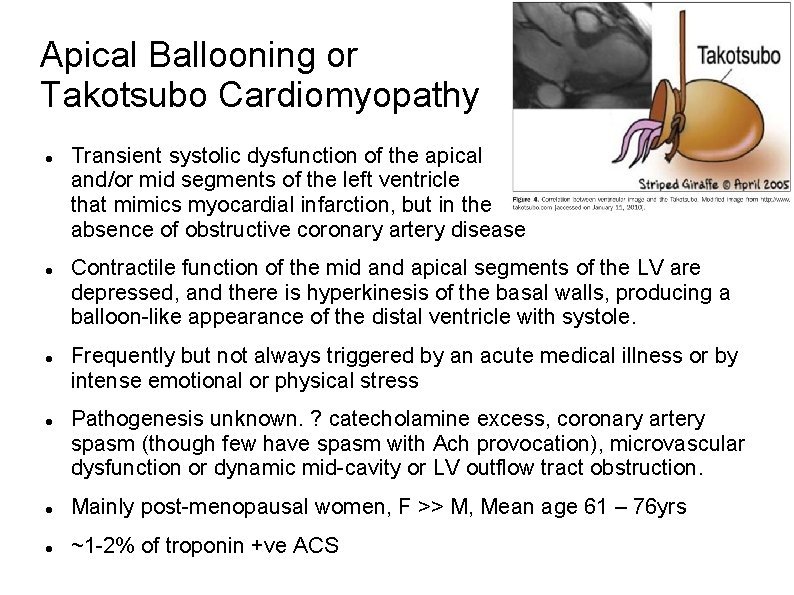
Apical Ballooning or Takotsubo Cardiomyopathy Transient systolic dysfunction of the apical and/or mid segments of the left ventricle that mimics myocardial infarction, but in the absence of obstructive coronary artery disease Contractile function of the mid and apical segments of the LV are depressed, and there is hyperkinesis of the basal walls, producing a balloon-like appearance of the distal ventricle with systole. Frequently but not always triggered by an acute medical illness or by intense emotional or physical stress Pathogenesis unknown. ? catecholamine excess, coronary artery spasm (though few have spasm with Ach provocation), microvascular dysfunction or dynamic mid-cavity or LV outflow tract obstruction. Mainly post-menopausal women, F >> M, Mean age 61 – 76 yrs ~1 -2% of troponin +ve ACS
Clinical Features Presentation – same as AMI CP, dyspnoea, ECG changes – often ST elevation and usually in anterior pre-cordial leads 35 -55%. Other changes include: deep T wave inversion, QT prolongation, abnormal Q waves, non-specific abnormalities or normal. (Can't distinguish AMI) Also syncope, arrhythmia, CHF, cardiogenic shock. Acute HF is more likely in >70 yrs, LVEF <40%, presence of physical stressor. Troponin elevated in 75 -85%, usually out of proportion to haemodynamic compromise. Usually affect LV only. Diagnosis made on Echo or ventriculography or cardiac MRI – typical appearance. Absence of CAD on angiogram
Management: Treat as ACS in ED Primary PCI or fibrinolytic therapy LV impairement treated as normal – ACEi, B-blockers. If shock present → USS to look for LVOT obstruction If present (~15%): NO inotropes, B-blockers, fluid resus If absent: Cautious use of inotropes -dobutamine & DA Most recover well over a period of weeks (with regain of normal systolic function), increased risk of recurrance (figure unknown) and long term adreno-receptor blockade may reduce risk of this.

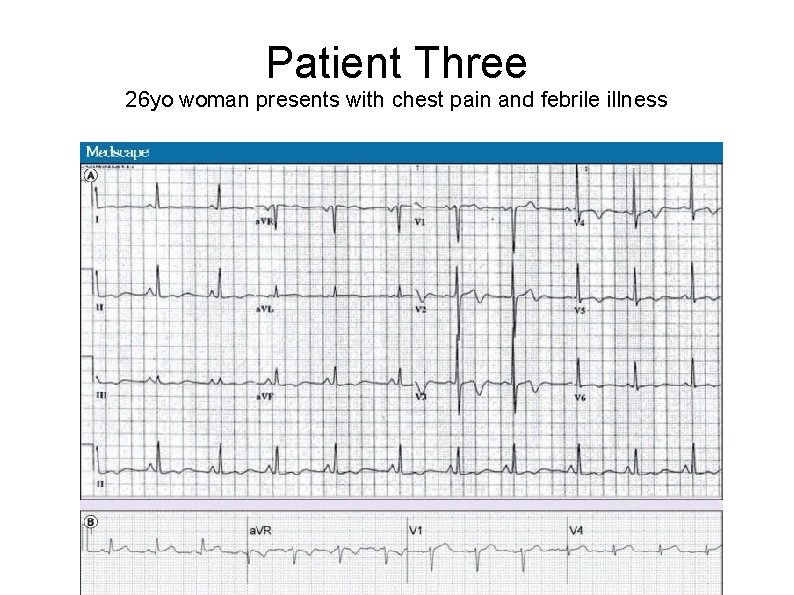
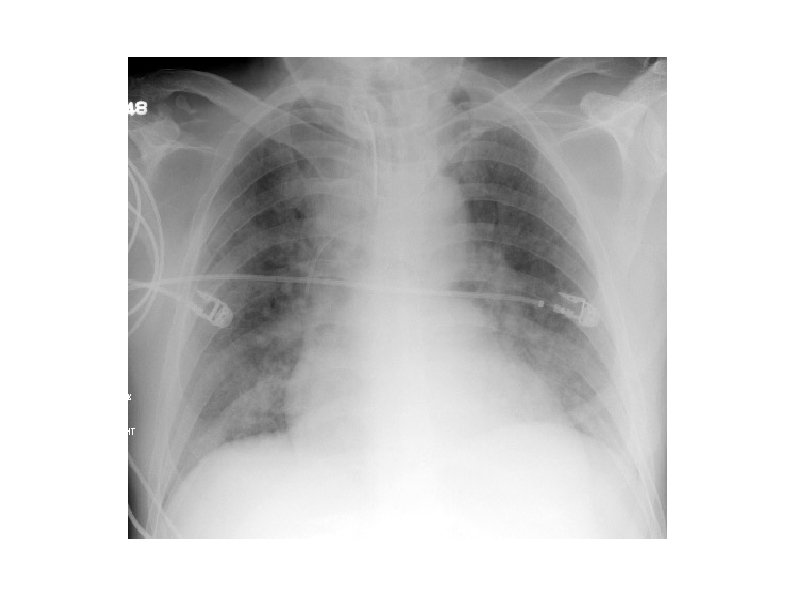
Patient Three 26 yo woman presents with chest pain and febrile illness Hx. PC: Unwell 8 days with fevers, cough, coryza, myalgias and fatigue. Others at home are unwell with the same – daughter currently admitted with bronchiolitis. Onset of chest pain 2/7 ago. The pain is anterior, central, sometimes radiating to shoulders and worse with cough and deep inspiration. Cough with green phlegm. No palpitations. SOB has noticed a reduced exertional capacity. Has been sleeping on 3 pillows for the past 2 days. No leg swelling. Amoxycillin by GP 4/7 ago, not improving. Previously fit and well
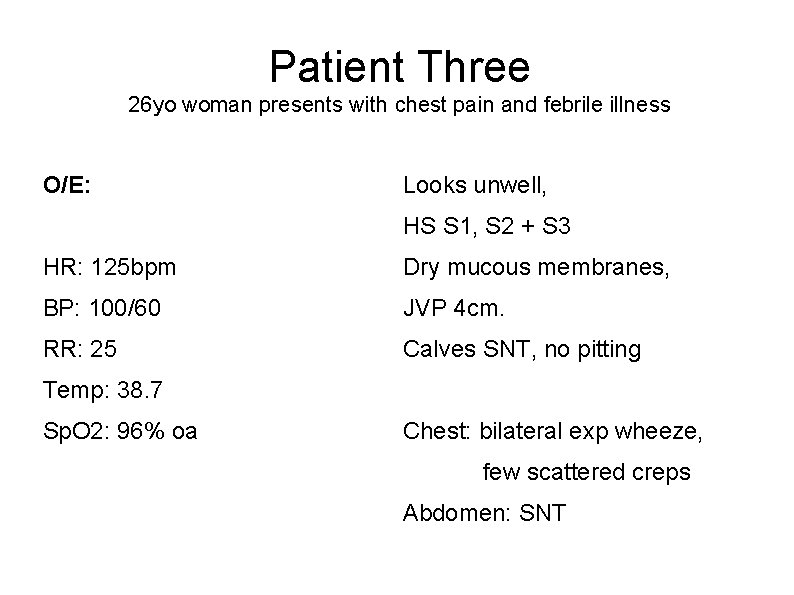
Patient Three 26 yo woman presents with chest pain and febrile illness O/E: Looks unwell, HS S 1, S 2 + S 3 HR: 125 bpm Dry mucous membranes, BP: 100/60 JVP 4 cm. RR: 25 Calves SNT, no pitting Temp: 38. 7 Sp. O 2: 96% oa Chest: bilateral exp wheeze, few scattered creps Abdomen: SNT
Patient Three 26 yo woman presents with chest pain and febrile illness
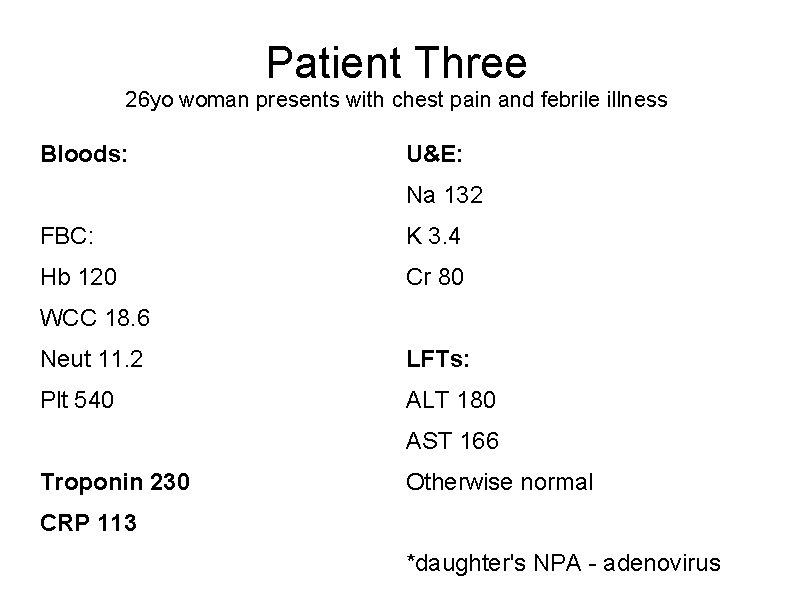
Patient Three 26 yo woman presents with chest pain and febrile illness Bloods: U&E: Na 132 FBC: K 3. 4 Hb 120 Cr 80 WCC 18. 6 Neut 11. 2 LFTs: Plt 540 ALT 180 AST 166 Troponin 230 Otherwise normal CRP 113 *daughter's NPA - adenovirus
Myocarditis Inflammatory infiltrate of the myocardium with necrosis and/or degeneration of adjacent myocytes not typical of the ischemic damage associated with coronary heart disease. Incidence is unknown. One study suggested that myocarditis is the cause of sudden cardiac death in 8. 6% of cases and is identified in up to 9% of routine post-mortem examinations Multiple causes (see next slide) Can be acute or chronic Focal or diffuse (viral usually diffuse, more likely to cause CHF) Spectrum of disease – assymptomatic → fulminant heart failure (Children more likely to have fulminant, and men more likely to have severe viral myocarditis, fulminant = better prognosis)

Causes Infectious Giant cell, SLE, sarcoidosis, IBD, Kawasaki, + many more Drug – hypersenstitivity Diptheria, fungal, parasitic and rickettsial Immune mediated Viral infection – most common cause, Coxsackie, adenovirus, parvovirus B 19, enterovirus. [less common EBV, Hep, CMV] Clozapine, isoniazid, phenytoin, thiazides + many more Toxic causes Drugs: ethanol, cocaine, lithium, Heavy metal poisoning: lead, copper, iron. Others: arsenic, insect stings and bites, CO Physical Electrical injury, radiation
Clinical Features Findings: Presentation: fever chest pain tachycardia fatigue S 3 and S 4 SOB pericardial rub palpitations signs of biventricular failure fever cardiogenic shock malaise Arthralgias Arrhyrthmia or sudden death Elevated WCC, CRP, ESR, LFTs ECG: ST, ST elevation, Tw changes – inversion CXR: normal, cardiomegaly or pulm oedema

Diagnosis Requires high level of suspicion as variable presentation. Elevated troponin ECG suggesting myocardial injury or pericarditis Arrhythmia New or unexplained altered cardiac function Particularly in younger patients 20 -50 yrs +/- viral/infective history – many do not have Initial testing: ECG Troponin/CK Routine labs – though non-specific BNP if uncertain whether CHF present.
Diagnosis Differentials: IHD, valvular heart disease, pulmonary disease Echo, CMRI +/- angiogram can be useful in distinguishing Echo: LV dilation, more spheroidal shape, RWMAs, usually global systolic dysfunction, can be focal. +/- pericardial effusion. CMRI – inflammation, hyperaemia, oedema, necrosis, scar, systolic dysfunction Definitive Diagnosis Pathological diagnosis Endomyocardial biopsy – histology “ Dallas Criteria” Immunohistochemical stains, PCR for viral genomes
Management: Treat as ACS if features are indistinguishable – troponin elevation, ischaemic changes on ECG, risk factors for CAD or history of same. Urgent Echo if large effusion or compromise CHF Usual therapies: diuresis, fluid and Na restriction, ACEi, Bblockers. May require balloon pump Arrhythmias Need monitoring, Tachy. C can precipitate CHF – amiodarone, cautious BB, CCB Brady. C pacing – usually only with temporary wire Anticoagulation

Management: Specific therapies: Anti-virals: usually outside of treatment window – don't often see early myocarditis. Immunosuppressive agents: Inflammation exceeds infection, effective in some animal studies but difficult to assess response in people due to rapid spontaneous recovery. Corticosteroids, cylcophosphamide, azathioprine – may exacerbate viral causes. Immunoglobulin – may be useful NOT NSAIDs Cardiac transplant → chronic myocarditis with persistent CHF Bed rest during acute phase – fevers and infective symptoms Reduction in alcohol intake Follow up 1 -3 monthly with regular Echo

Prognosis Mild cases unclear as only most unwell get EMB and diagnosis. Dependent on cause Fulminant myocarditis – much better prognosis, most return to normal LV systolic function. Idiopathic Giant cell myocarditis usually fatal Usually inflammation is self limiting without long term sequelae Poorer prognosis if: ECG: BBB, high degree AV block, Q waves LVEF < 40% Pulmonary hypertension
- Slides: 38