
The Salivary Glands diseases Clinical Anatomy of the






























































- Slides: 144
The Salivary Glands diseases
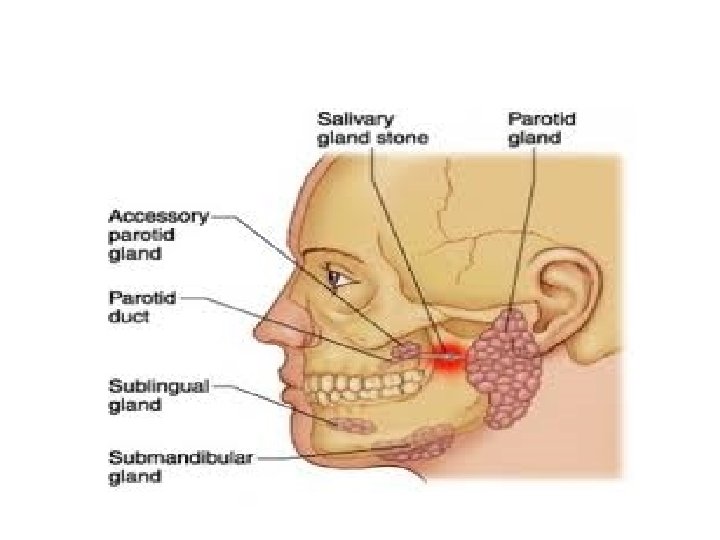
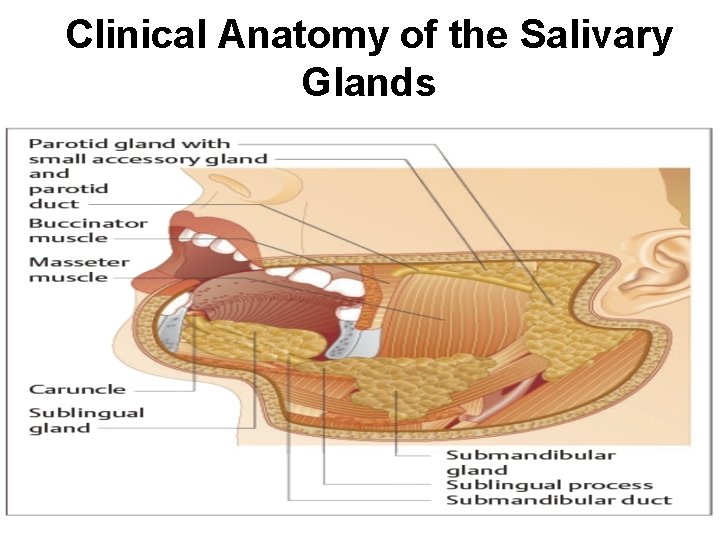
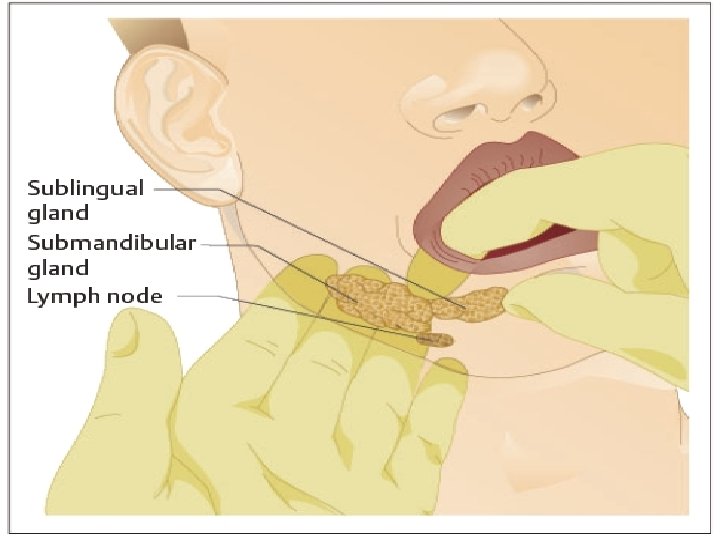
Clinical Anatomy of the Salivary Glands
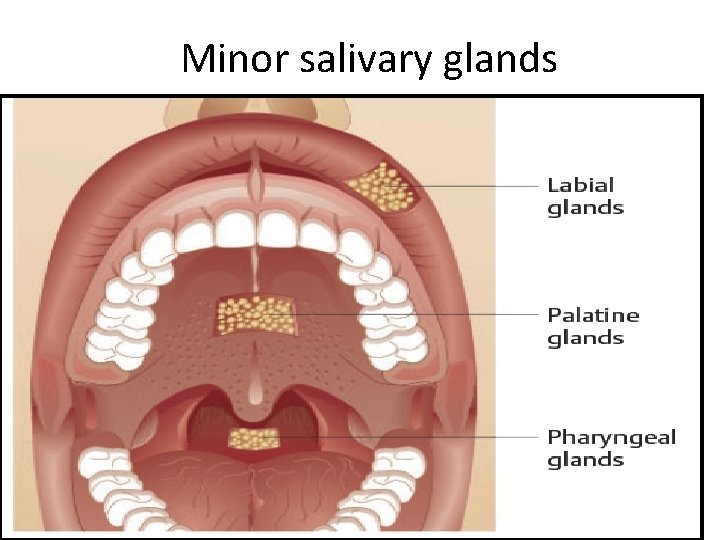
Minor salivary glands
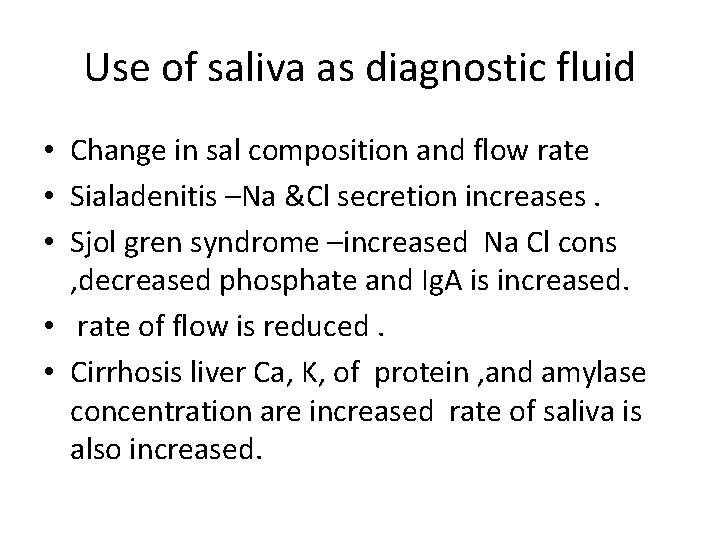
Use of saliva as diagnostic fluid • Change in sal composition and flow rate • Sialadenitis –Na &Cl secretion increases. • Sjol gren syndrome –increased Na Cl cons , decreased phosphate and Ig. A is increased. • rate of flow is reduced. • Cirrhosis liver Ca, K, of protein , and amylase concentration are increased rate of saliva is also increased.
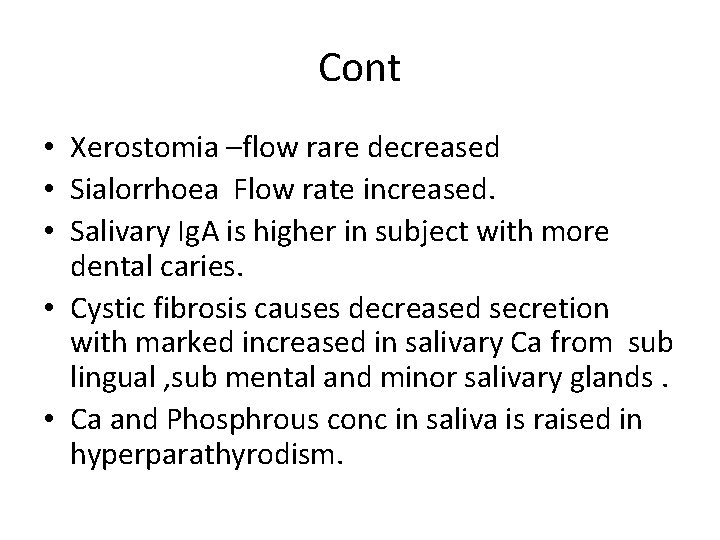
Cont • Xerostomia –flow rare decreased • Sialorrhoea Flow rate increased. • Salivary Ig. A is higher in subject with more dental caries. • Cystic fibrosis causes decreased secretion with marked increased in salivary Ca from sub lingual , sub mental and minor salivary glands. • Ca and Phosphrous conc in saliva is raised in hyperparathyrodism.
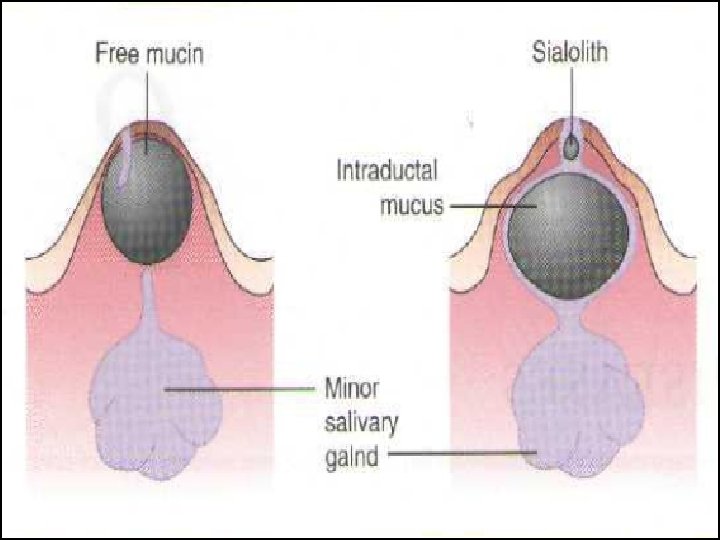
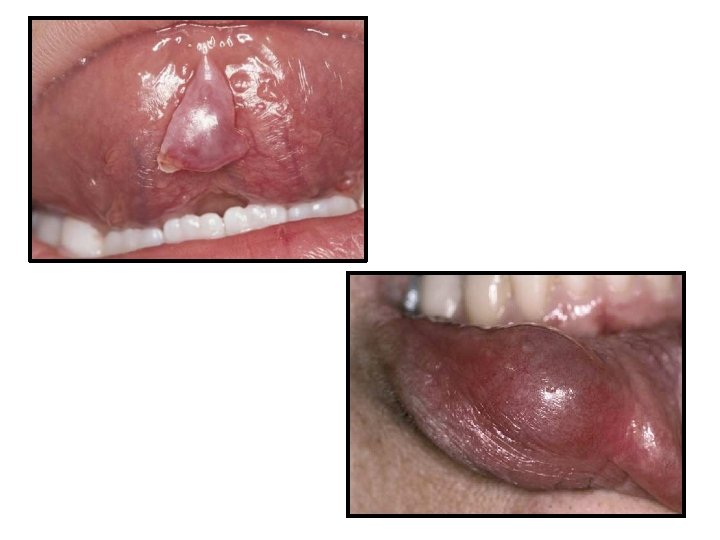
Reactive lesions • Mucocele is a clinical term that includes mucus extravasation phenomenon and mucus retention cyst.
Mucocele Etiology Extravasation type • Physical‐traumatic injury to minor gland excretory duct • Mucus extravasation into periductal soft tissue produces a local inflammatory response and granulation tissue “encapsulation. ”
Clinical Presentation Lower lip most common site; also buccal mucosa, anterior ventral tongue Painless bluish hue when mucin is near surface Often waxes and wanes in size Microscopic Findings Mucus pool surrounded by granulation tissue Macrophage and neutrophil response to free mucin Focal chronic sialadenitis
Diagnosis • Presentation • Microscopic findings Differential Diagnosis • • Hemangioma Pyogenic granuloma Salivary neoplasm Connective tissue neoplasm
Treatment • Excision with associated local minor salivary glands Prognosis • Occasional recurrence
Mucus Retention Cyst Etiology • Represents dilatation of salivary excretory duct due to obstruction • Duct obstruction may be due to a mucous plug or sialolith formation
Clinical Presentation • Major or minor salivary glands affected in adulthood • Asymptomatic, soft mucosal swelling • Can occur at any intraoral minor salivary gland site, especially upper lip
Microscopic Findings Thin, dilated, epithelial‐lined salivary excretory duct Lining is cuboidal to columnar with occasional mucus‐ producing cells present Adjacent salivary gland lobules minimally altered but may show obstructive inflammatory changes Diagnosis Microscopic findings Differential Diagnosis Extravasational mucocele Salivary gland neoplasm, especially mucoepidermoid carcinoma
Treatment • Excision of cyst with adjacent gland(s) Prognosis • Recurrence is rare.
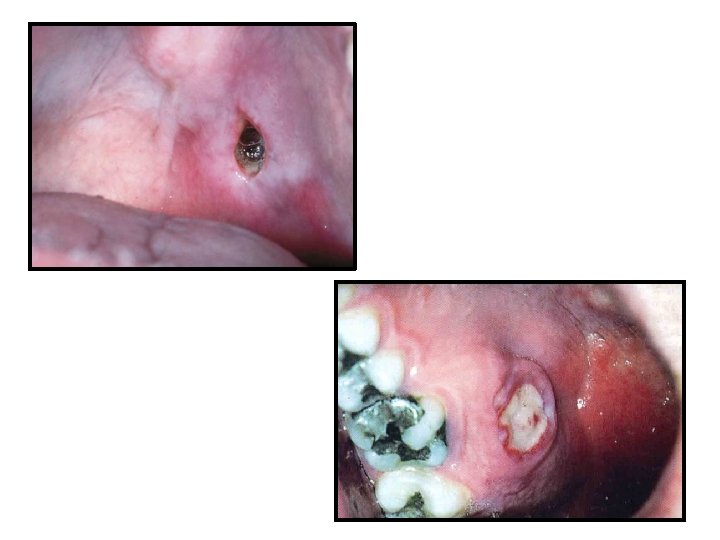
Necrotizing Sialometaplasia Etiology • Local ischemic injury of salivary gland lobules • May be preceded by trauma or local anesthetic injury, or it may appear spontaneously
Clinical Presentation • Both major and minor salivary glands can be affected. • Hard palate most common site, usually unilateral • Initially a painful to dysesthetic submucosal swelling • Ultimately, a central necrotic crater develops. • May extend to and involve deep soft tissue and palatal bone
Microscopic Findings Salivary gland inflammation and lobular necrosis (necrosis is not always demonstrable on biopsy) • Ductal squamous metaplasia (bland cytology) • Lobular architecture of salivary glands persists •
Diagnosis • Microscopic findings Differential Diagnosis • Salivary gland neoplasm • Squamous cell carcinoma • Granulomatous disease
Treatment • Follow‐up only Prognosis • Excellent
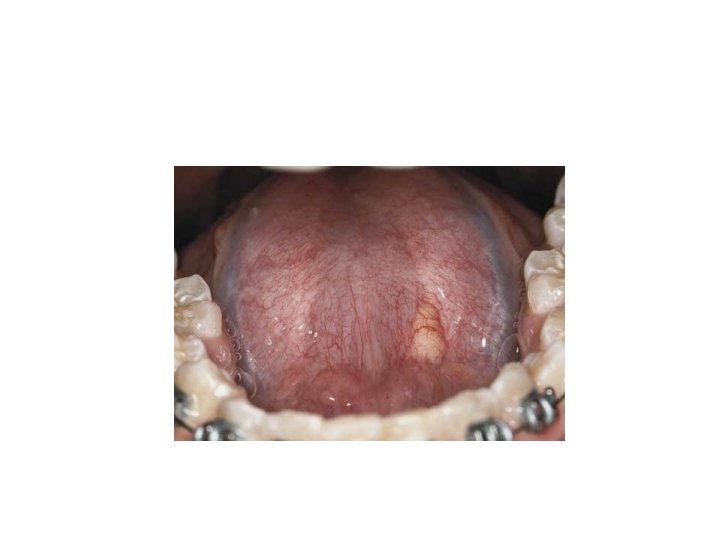
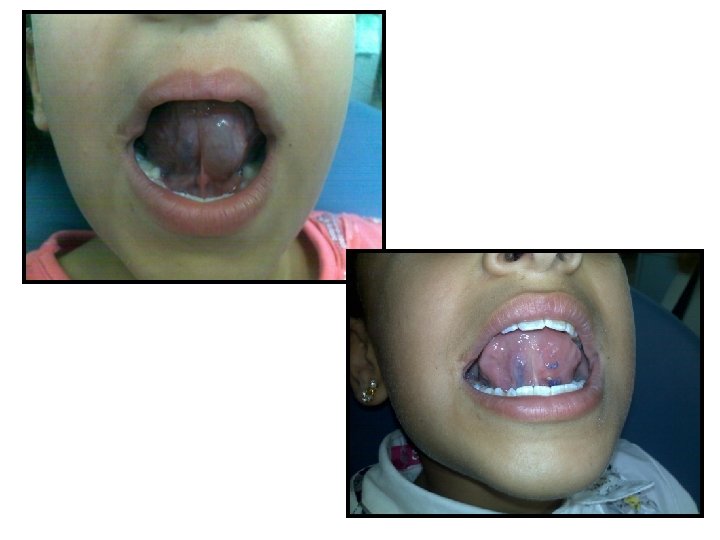
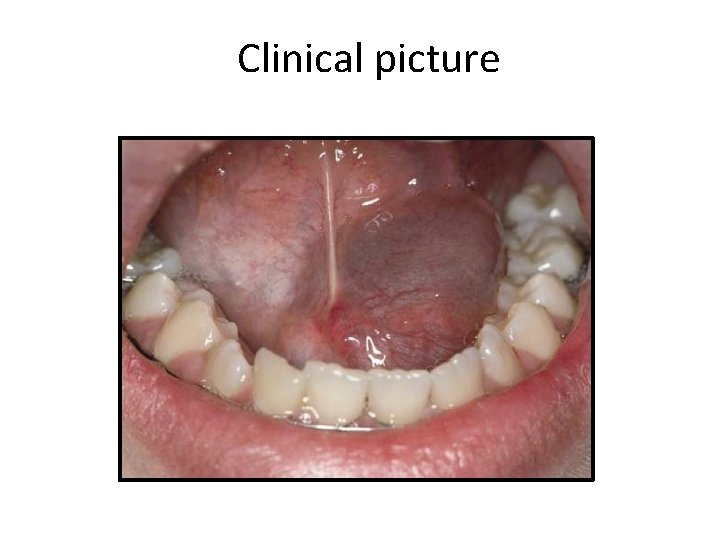
Ranula Etiology • Obstruction of the sublingual (usually) or submandibular salivary gland by a sialolith or by trauma • Secondary to obstruction, extravasation of saliva into the soft tissue of the floor of the mouth
Clinical Presentation Unilateral, fluctuant, soft tissue mass on the floor of the mouth Usually has a bluish, slightly translucent quality When above the mylohyoid muscle, presentation is intraoral. If extravasation extends below the mylohyoid muscle, a plunging ranula forms. Occlusal radiographs may demonstrate a suspected sialolith.
Clinical picture
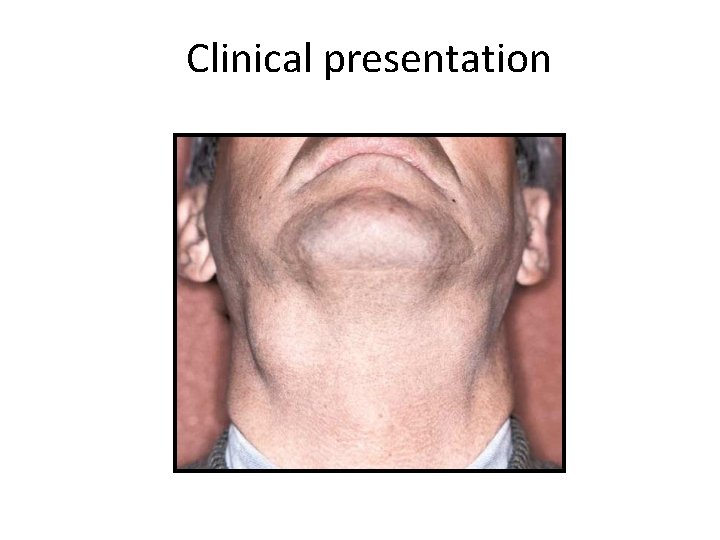
Plunging ranula • An unusual clinical variant, the plunging or cervical ranula, occurs when the spilled mucin dissects through the mylohyoid muscle and produces swelling within the neck.
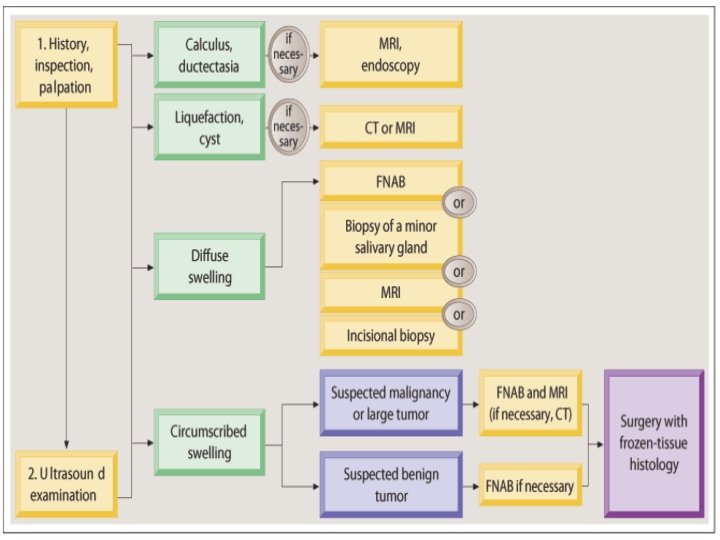
Diagnosis • Demonstration of sialolith • Soft tissue imaging (T 2‐weighted magnetic resonance image) • Aspiration of mucinous salivary fluid • Excised tissue with granulation tissue lining around mucin pool
Differential Diagnosis • • • Dermoid cyst Salivary gland tumor Soft tissue tumor Cystic hygroma Thymic cyst
Treatment • Marsupialization as an initial procedure • Excision of the involved gland (extravasation type) • Sialolithectomy (in obstructive type) Prognosis • No recurrence with sialadenectomy • Recurrence risk with sialolithectomy secondary to duct scarring or reformation of stone
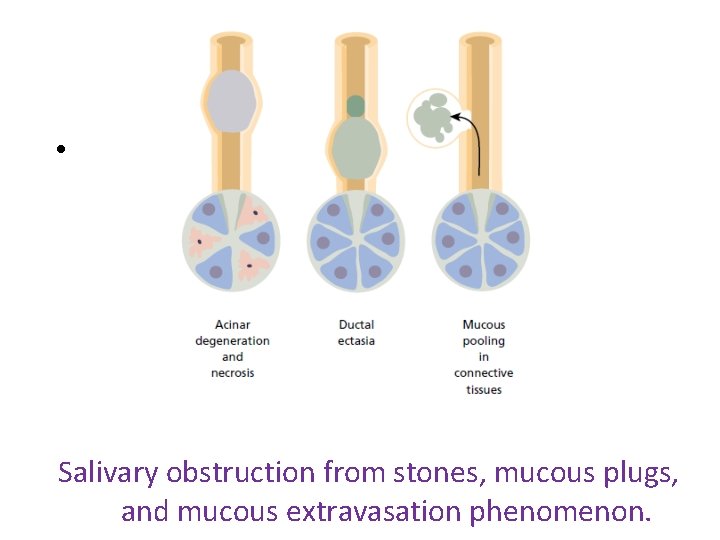
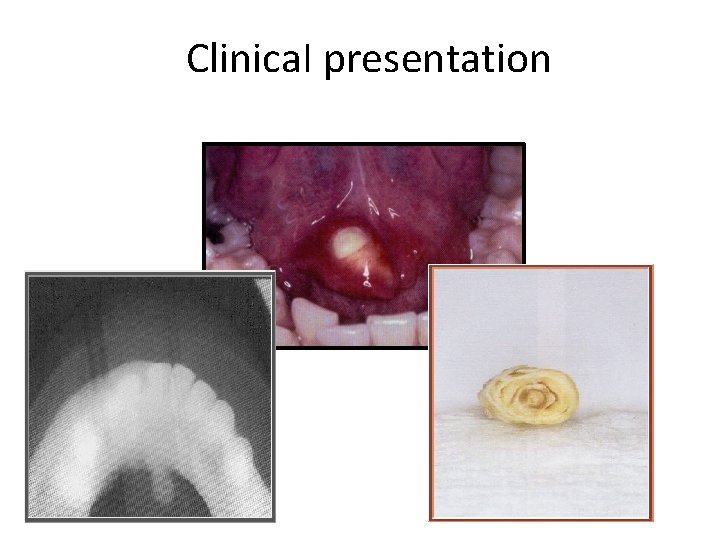
Sialolithiasis Etiology Sialoliths are calcified structures that develop within the salivary ductal system. They are believed to arise from deposition of calcium salts around a nidus of debris within the duct lumen. This debris may include inspissated mucus, bacteria, ductal epithelial cells, or foreign bodies. The cause of sialoliths is unclear, but their formation can be promoted by chronic sialadenitis and partial obstruction. Their development is not related to any systemic derangement in calcium and phosphorus metabolism.
• Salivary obstruction from stones, mucous plugs, and mucous extravasation phenomenon.
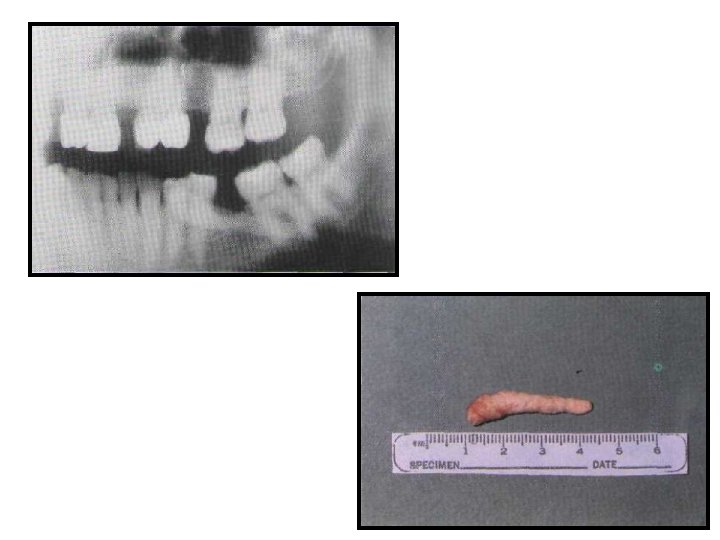
Clinical Presentation • Sialolithiasis can form in all of the salivary glands, including minor salivary glands, but the gland that most commonly produces such stones is the submandibular gland. • The so‐called stones that form in the parotid duct system are rarely calcified and are actually mucous plugs that do not appear on radiographs. • Stones that form in the submandibular duct system are almost always radiopaque because they are composed of calcium carbonate and calcium phosphate.
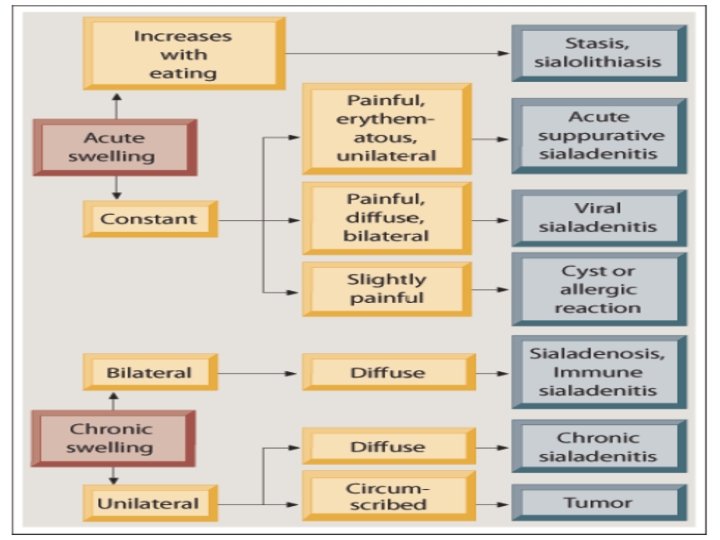
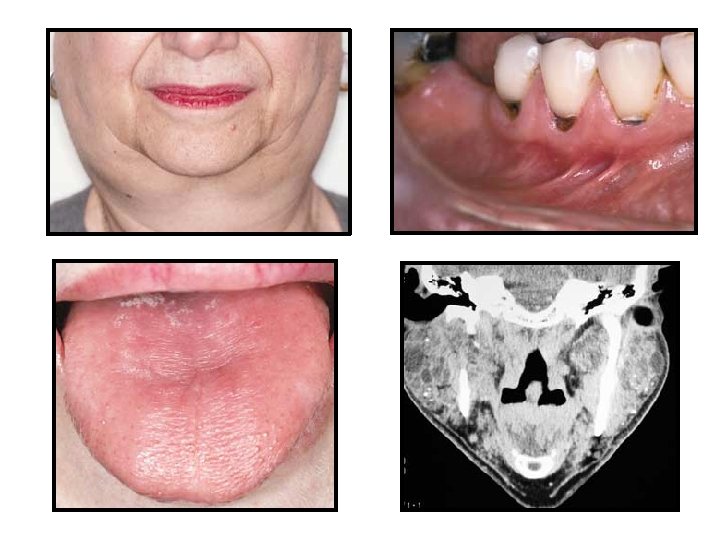
C/F They can occur along any part of the duct and are most frequent at anatomic bends. In the submandibular duct, stones are often found at the duct's bend around the posterior edge of the mylohyoid muscle. When sialoliths form, they will obstruct the duct either partially or completely. Therefore, individuals present with a painful swelling of the gland usually with signs of secondary infection, including a suppurative exudate from the duct, fever, and mild to moderate leukocytosis. Individuals will report an increase in pain and swelling upon eating. The gland will be palpably firm and anywhere from mildly tender to very painful.
Clinica. I presentation
Diagnosis • CT scan with 2‐ to 3‐mm cuts to identify the location of the stone. • Most obstructed submandibular glands will have both inflammation and fibrosis in a homogeneous pattern throughout the gland.
Differential Diagnosis • Calcified lymph nodes from previously resolved tuberculosis • Phleboliths (particularly if an old cavernous hemangioma were present) • Tonsoliths • Calcifications of the carotid bifurcation.
Treatment • Stones that are accessible in the floor of the mouth are removed via a direct approach, and the damaged duct is sutured to the mucosa of the floor of the mouth (sialodochoplasty). • Parotid stones usually do not produce a long‐term clinical problem. Most are passed with parotid flow, and a few require removal from the duct with either a repair or duct transposition.
Prognosis • If the sialolith has been present for a short time, the gland may recover after sialolith removal. • If the sialolith is of long standing, the gland may harbor irreversible inflammation and fibrosis, so that it cannot recover even if the sialolith is removed.
Sialorrhea (Sialosis) Etiology • Varied; may include idiopathic paroxysmal sialorrhea, parkinsonism, stomatitis (acute), newly inserted oral appliances, expectorants, neostigmine, and others
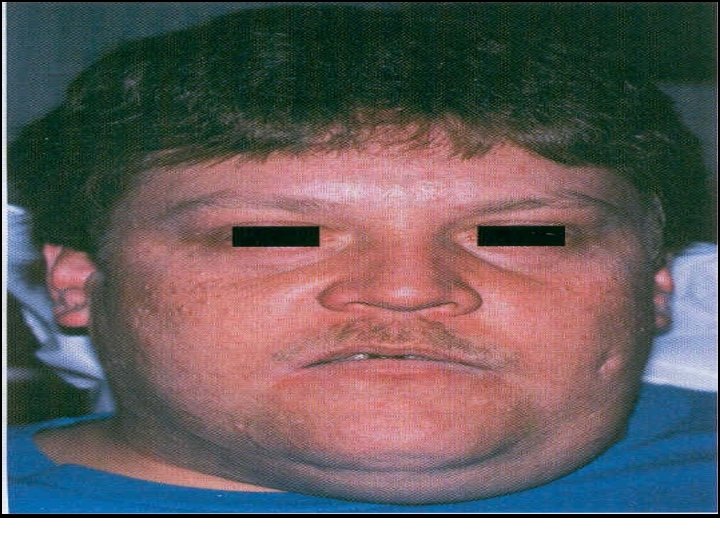
Clinical Presentation • Excess saliva resulting in drooling • Angular cheilosis • Diffuse parotid/submandibular salivary gland enlargement
Clinical presentation
Diagnosis • Direct observation and analysis of history • Flow‐rate measurement
Treatment • Scopolamine • If related to medication use, an alternate medication should be chosen, if possible. Prognosis • Guarded/indeterminate
Adenomatoid hyperplasia Etiology • It is a nonneoplastic enlargement of the minor salivary glands of the hard palate. • The cause is unknown, although there is some evidence to suggest that trauma plays a role.
Clinical Presentation The palate is the chief site of involvement of this salivary gland hyperplasia. There is a male predominance, and age ranges from 24 to 63 years. The clinical presentation is a unilateral swelling of the hard and/or soft palate. This lesion is asymptomatic, broad based, and covered with intact mucosa of normal color and quality.
Differential Diagnosis • Salivary neoplasms • Lymphoma • Extension of nasopharyngeal or sinonasal disease into the oral cavity.
Treatment • Subsequent to identification by means of an incisional biopsy, no treatment is necessary, given the purely benign nature of this process. Prognosis • There is no neoplastic potential.
Sjögren’s Syndrome Etiology An autoimmune disease resulting in exocrine gland dysfunction secondary to mononuclear cell infiltration Increased prevalence of human leukocyte antigen DR/DQ alleles Autoantibody production against nuclear antigens SS‐A and SS‐B No specific agent identified; postulations include the following: Potential role for viruses/retroviruses as cofactors Possible role of cytokine and hormonal influence on signal transduction and secretion
Clinical Presentation Decrease in exocrine gland function Ø Xerostomia Ø Xerophthalmia/keratoconjunctivitis sicca Salivary and lacrimal gland enlargement (one‐third of cases) Secondary effects of exocrine dysfunction are as follows: Ø Dental caries Ø Oral candidiasis Ø Ocular/corneal discomfort Primary form: exocrine dysfunction dominates Secondary form: exocrine dysfunction; other associated autoimmune conditions—usually rheumatoid arthritis, less often lupus erythematosus
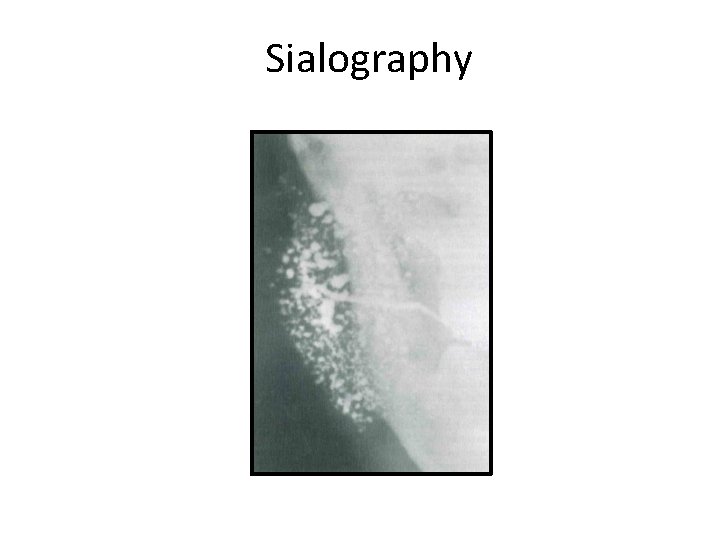
Sialography
Diagnosis • Demonstration of objective xerostomia and xerophthalmia • Serologic demonstration of associated SS‐A or SS‐B antibodies • Correlation of clinical and serologic findings with labial salivary gland biopsy; demonstration of presence of periductal lymphocytic sialadenitis
Differential Diagnosis (Xerostomia/Parotid Gland Swelling) • • Sarcoidosis • Depression • • HIV‐ associated • Autonomic neuropathy exocrinopathy • Graft‐versus‐host disease • • Drug side effects • Alcoholism • • Lymphoma • Diabetes mellitus • • Bulimia
Treatment Directed at associated connective tissue or autoimmune disease Systemic corticosteroids if acute symptoms arise Frequent dental/ophthalmic examinations
Treatment Usually symptomatic and preventative therapies are used, including the following: Ø Reduction of oral dryness Ø Pilocarpine Ø Cemiveline Ø Oral moisturizing agents (saliva substitutes) Ø Gustatory stimulation Ø Ocular moisture replacement Ø Saline Ø Synthetic glycoprotein solutions Ø Carboxymethylcellulose sodium Ø Ocular punctual occlusion
Prognosis Guarded • High risk of lymphoma compared with risk in those without autoimmune disease.
Salivary Gland Neoplasms • Benign Neoplasms • Malignant Neoplasms • Controversial Issues
Salivary Gland Neoplasms • Diverse histopathology • Relatively uncommon – 2% of head and neck neoplasms • Distribution – Parotid: 80% overall; 80% benign – Submandibular: 15% overall; 50% benign – Sublingual/Minor: 5% overall; 40% benign
Tumors of the salivary glands • • Benign tumors. Pleomorphic adenoma Warthins tumors. Basal cell adenoma Canalicular adenoma Oxyphilic adenoam Myepithelial ductul adenoma
Tumors of the salivary glands • Malignant tumors ( major and minor salivary glands. } • Mucoepidermoid carcinoma. • Adenoid cystic carcinoma • Malignant mixed tumour • Acinic cell carcinaoma.
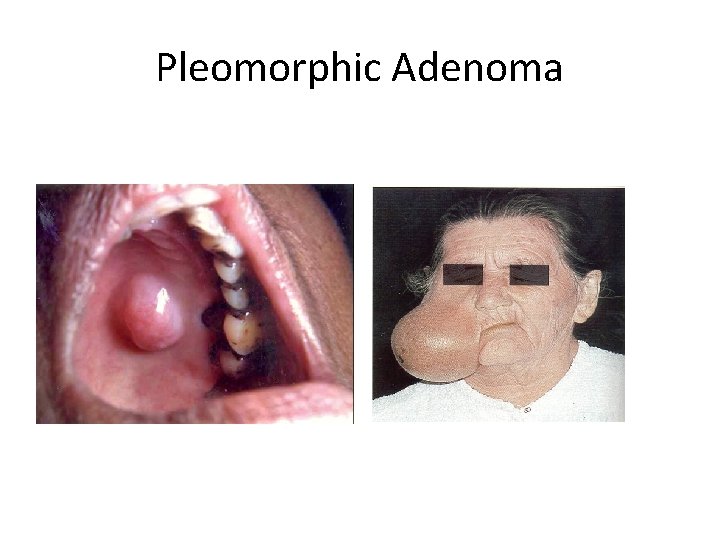
Pleomorphic adenoma (mixed tumor) • More than 50% of all tumors and 90%of benign tumors. • Major and minor salivary glands but commonly parotid gland • Both epithelial and connective tissue elements so it is mixed tumor. • Clinical features • Parotid and minor salivary gland tumor of palate, lip.
Pleomorphic Adenoma
Pleomorphic adenoma (mixed tumor) • Less frequently affects submandibular glands. • Between 4 th to 6 th decade of life. • More common in female. • Small painless nodule either at the angle on mandible of beneath the ear lobe. • Slowly growing , intermittent growth , firm in consistency , well circumscribed encapsulated , may show area of degenerations.
Pleomorphic adenoma • Intra oral pleomorphic adenoma are noticed early because of location on the palate. • May show fixity to underlying bone but does not invade the bone. • D/D • Hyperplastic lymph nodes • Neurilemmoma of facial nerve.
Cont‐ • Most common of all salivary gland neoplasms • • 70% of parotid tumors 50% of submandibular tumors 45% of minor salivary gland tumors 6% of sublingual tumors • 4 th‐ 6 th decades • F: M = 3‐ 4: 1
Pleomorphic Adenoma • Slow‐growing, painless mass • Parotid: 90% in superficial lobe, most in tail of gland • Minor salivary gland: lateral palate, submucosal mass • Solitary vs. synchronous/metachronous neoplasms
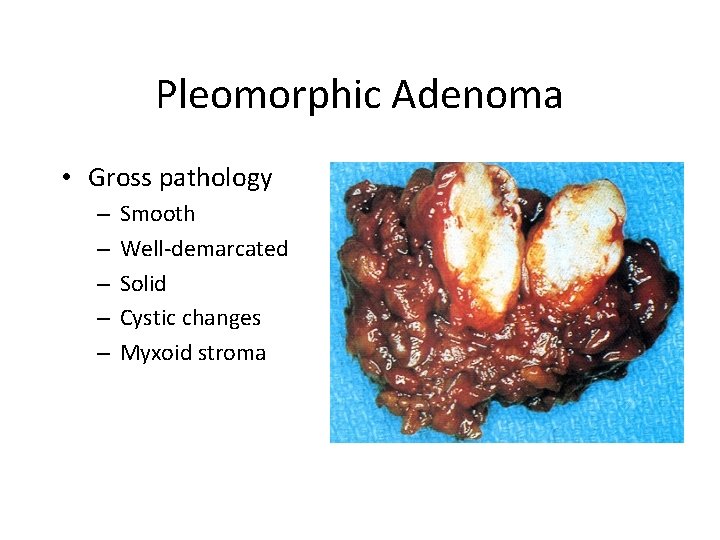
Pleomorphic Adenoma • Gross pathology – – – Smooth Well‐demarcated Solid Cystic changes Myxoid stroma
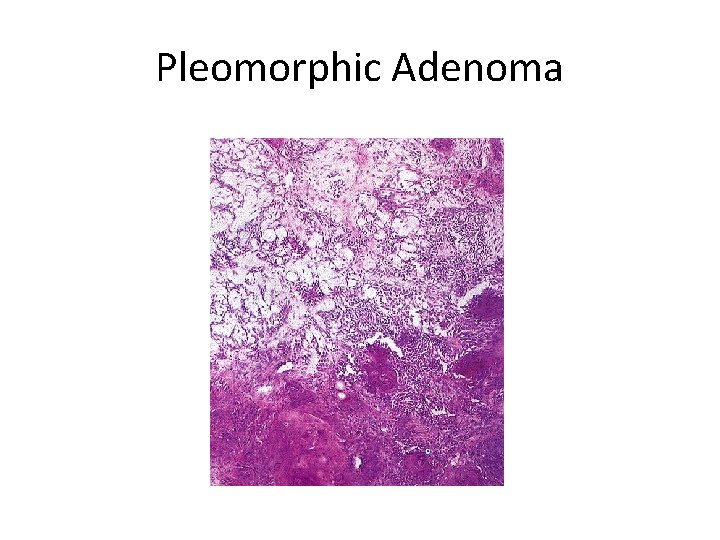
Pleomorphic Adenoma • Histology – Mixture of epithelial, myopeithelial and stromal components – Epithelial cells: nests, sheets, ducts, trabeculae – Stroma: myxoid, chrondroid, fibroid, osteoid – No true capsule – Tumor pseudopods
Pleomorphic Adenoma
Pleomorphic Adenoma • Treatment: complete surgical excision – Parotidectomy with facial nerve preservation – Submandibular gland excision – Wide local excision of minor salivary gland • Avoid enucleation and tumor spill. • Irradiation is contra indicated. (radio resistant
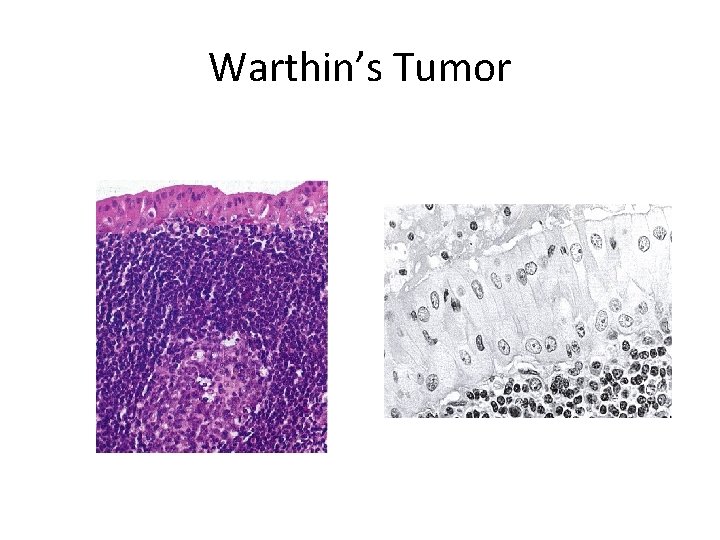
Warthin’s Tumor • • • AKA: papillary cystadenoma lymphomatosum 6‐ 10% of parotid neoplasms Older, Caucasian, males 10% bilateral or multicentric 3% with associated neoplasms Presentation: slow‐growing, painless mass
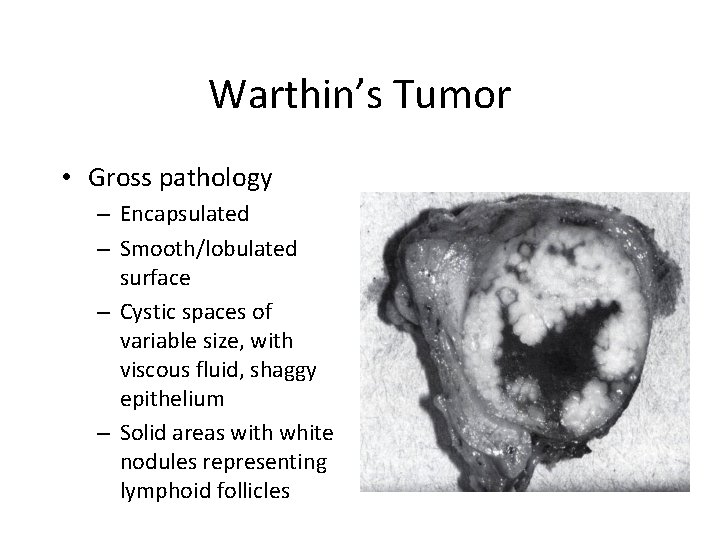
Warthin’s Tumor • Gross pathology – Encapsulated – Smooth/lobulated surface – Cystic spaces of variable size, with viscous fluid, shaggy epithelium – Solid areas with white nodules representing lymphoid follicles
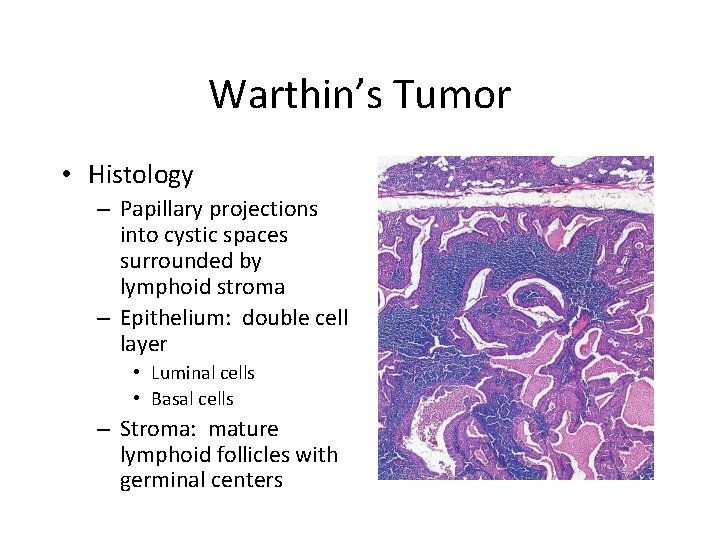
Warthin’s Tumor • Histology – Papillary projections into cystic spaces surrounded by lymphoid stroma – Epithelium: double cell layer • Luminal cells • Basal cells – Stroma: mature lymphoid follicles with germinal centers
Warthin’s Tumor
Oncocytoma • • • Rare: 2. 3% of benign salivary tumors 6 th decade M: F = 1: 1 Parotid: 78% Submandibular gland: 9% Minor salivary glands: palate, buccal mucosa, tongue
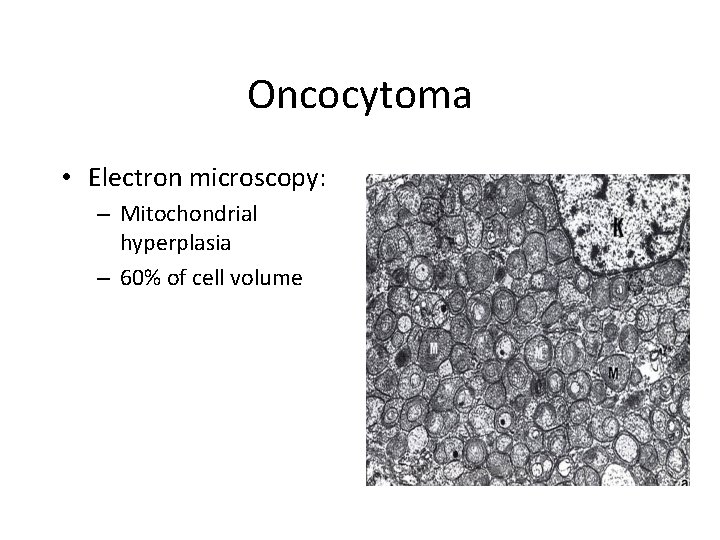
Oncocytoma • Presentation – Enlarging, painless mass • Technetium‐ 99 m pertechnetate scintigraphy – Mitochondrial hyperplasia
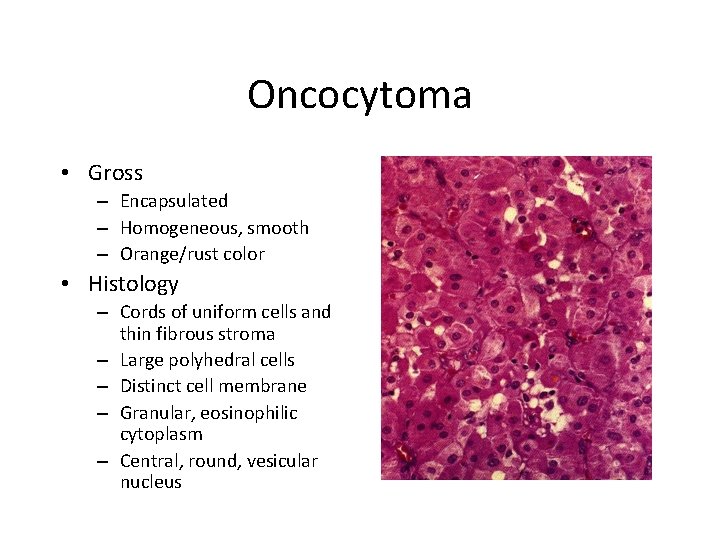
Oncocytoma • Gross – Encapsulated – Homogeneous, smooth – Orange/rust color • Histology – Cords of uniform cells and thin fibrous stroma – Large polyhedral cells – Distinct cell membrane – Granular, eosinophilic cytoplasm – Central, round, vesicular nucleus
Oncocytoma • Electron microscopy: – Mitochondrial hyperplasia – 60% of cell volume
Monomorphic Adenomas • Basal cell, canalicular, sebaceous, glycogen‐ rich, clear cell • Basal cell is most common: 1. 8% of benign epithelial salivary gland neoplasms • 6 th decade • M: F = approximately 1: 1 • Caucasian > African American • Most common in parotid
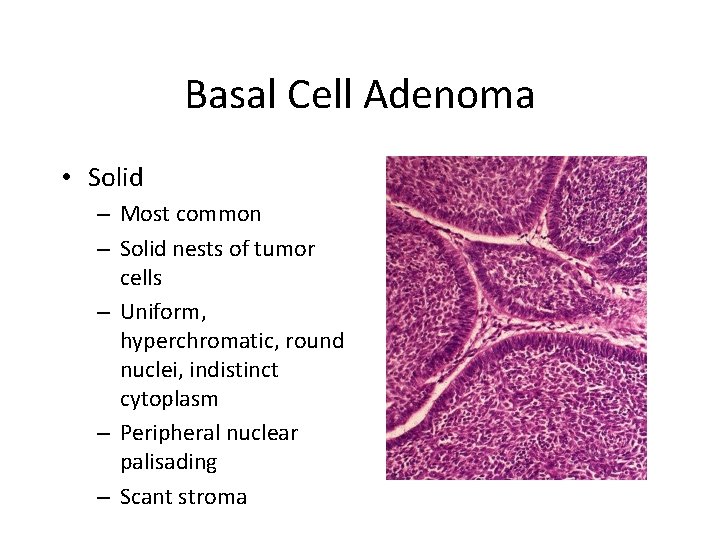
Basal Cell Adenoma • Solid – Most common – Solid nests of tumor cells – Uniform, hyperchromatic, round nuclei, indistinct cytoplasm – Peripheral nuclear palisading – Scant stroma
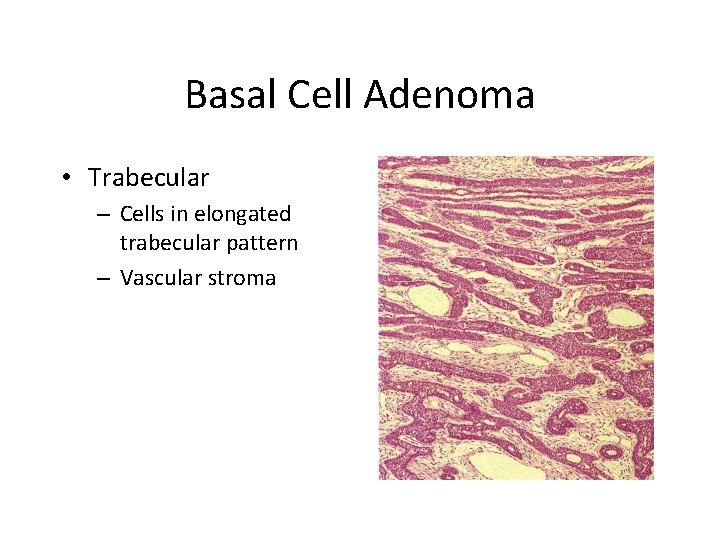
Basal Cell Adenoma • Trabecular – Cells in elongated trabecular pattern – Vascular stroma
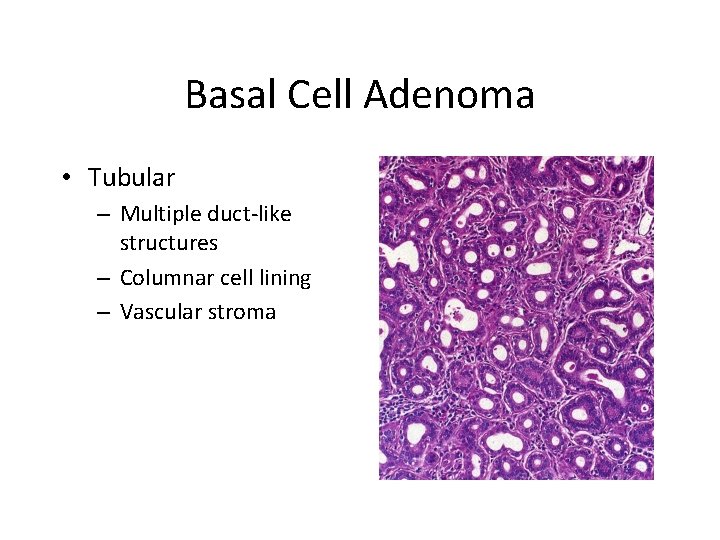
Basal Cell Adenoma • Tubular – Multiple duct‐like structures – Columnar cell lining – Vascular stroma
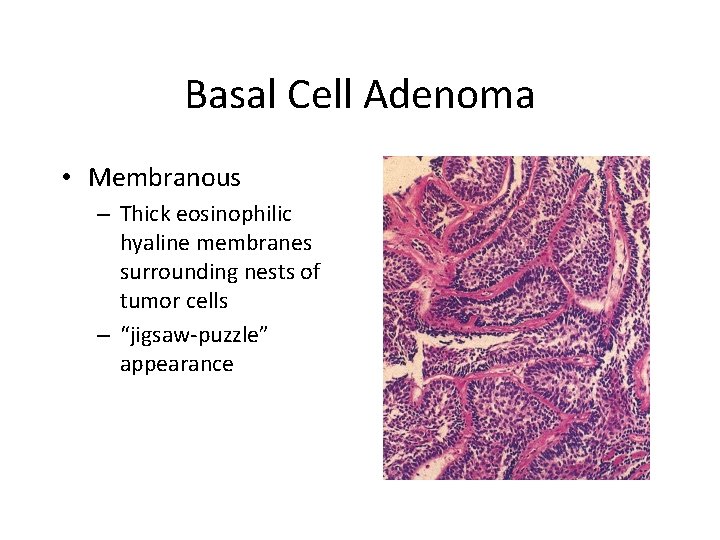
Basal Cell Adenoma • Membranous – Thick eosinophilic hyaline membranes surrounding nests of tumor cells – “jigsaw‐puzzle” appearance
Monomorphic Adenomas • Canalicular adenoma – 7 th decade – F: M – 1. 8: 1 – Most common in minor salivary glands of the upper lip (74%) – Painless submucosal mass
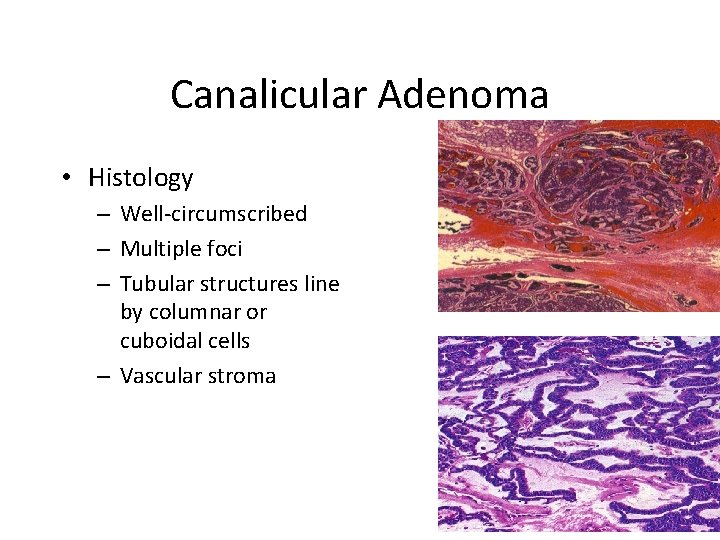
Canalicular Adenoma • Histology – Well‐circumscribed – Multiple foci – Tubular structures line by columnar or cuboidal cells – Vascular stroma
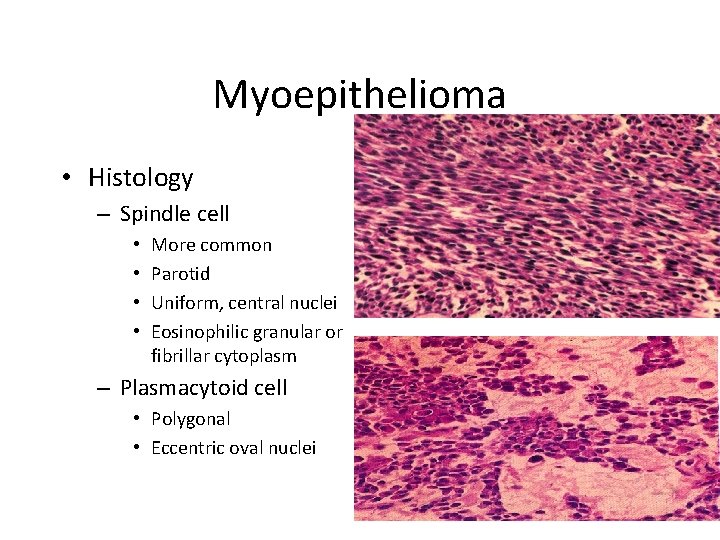
Myoepithelioma <1% of all salivary neoplasms 3 rd‐ 6 th decades F>M Minor salivary glands > parotid > submandibular gland • Presentation: asymptomatic mass • •
Myoepithelioma • Histology – Spindle cell • • More common Parotid Uniform, central nuclei Eosinophilic granular or fibrillar cytoplasm – Plasmacytoid cell • Polygonal • Eccentric oval nuclei
Mucoepidermoid Carcinoma • • Most common salivary gland malignancy 5‐ 9% of salivary neoplasms Parotid 45‐ 70% of cases Palate 18% 3 rd‐ 8 th decades, peak in 5 th decade F>M Caucasian > African American
Mucoepidermoid Carcinoma • Presentation – Low‐grade: slow growing, painless mass – High‐grade: rapidly enlarging, +/‐ pain – **Minor salivary glands: may be mistaken for benign or inflammatory process • Hemangioma • Papilloma • Tori
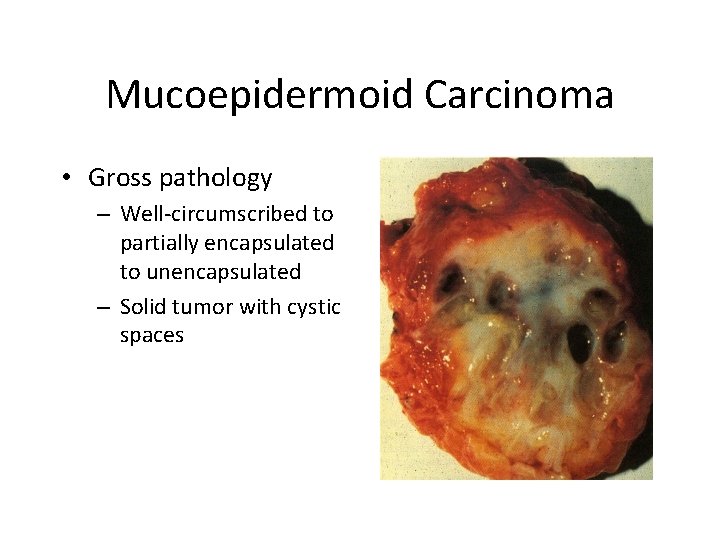
Mucoepidermoid Carcinoma • Gross pathology – Well‐circumscribed to partially encapsulated to unencapsulated – Solid tumor with cystic spaces
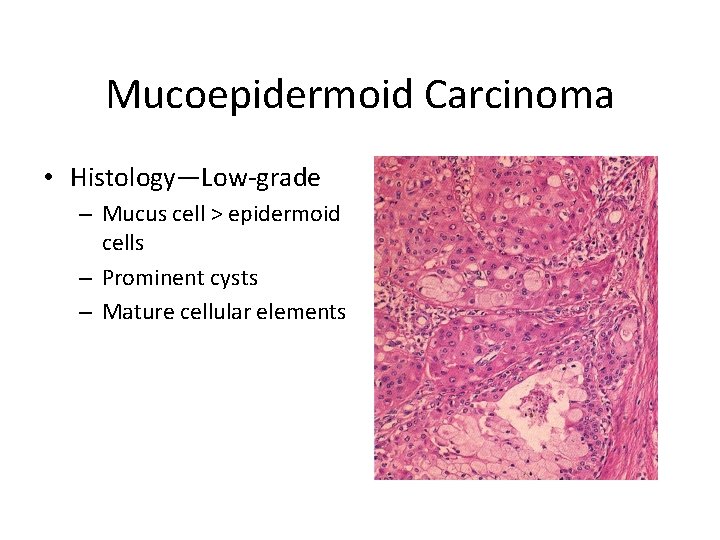
Mucoepidermoid Carcinoma • Histology—Low‐grade – Mucus cell > epidermoid cells – Prominent cysts – Mature cellular elements
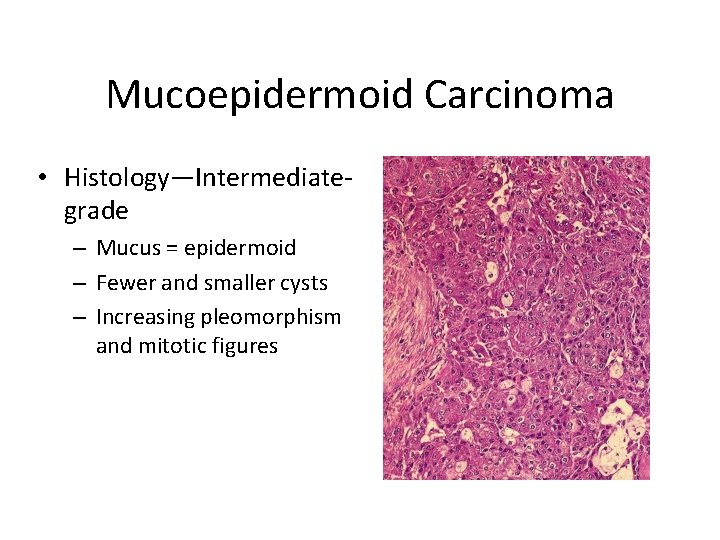
Mucoepidermoid Carcinoma • Histology—Intermediate‐ grade – Mucus = epidermoid – Fewer and smaller cysts – Increasing pleomorphism and mitotic figures
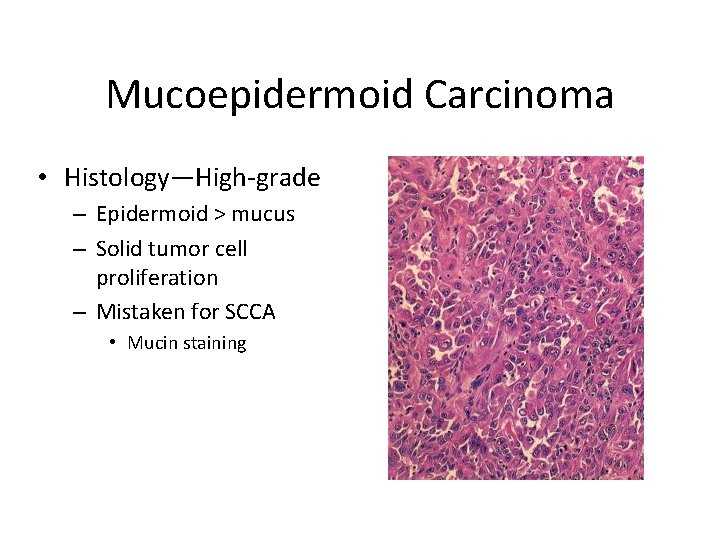
Mucoepidermoid Carcinoma • Histology—High‐grade – Epidermoid > mucus – Solid tumor cell proliferation – Mistaken for SCCA • Mucin staining
Mucoepidermoid Carcinoma • Treatment – Influenced by site, stage, grade – Stage I & II • Wide local excision – Stage III & IV • Radical excision • +/‐ neck dissection • +/‐ postoperative radiation therapy
Adenoid Cystic Carcinoma • Overall 2 nd most common malignancy • Most common in submandibular, sublingual and minor salivary glands • M=F • 5 th decade • Presentation – Asymptomatic enlarging mass – Pain, paresthesias, facial weakness/paralysis
Adenoid Cystic Carcinoma • Gross pathology – Well‐circumscribed – Solid, rarely with cystic spaces – infiltrative
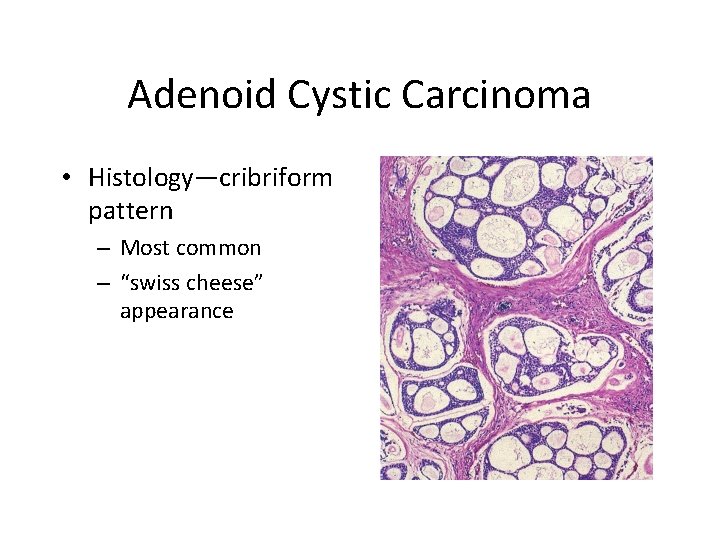
Adenoid Cystic Carcinoma • Histology—cribriform pattern – Most common – “swiss cheese” appearance
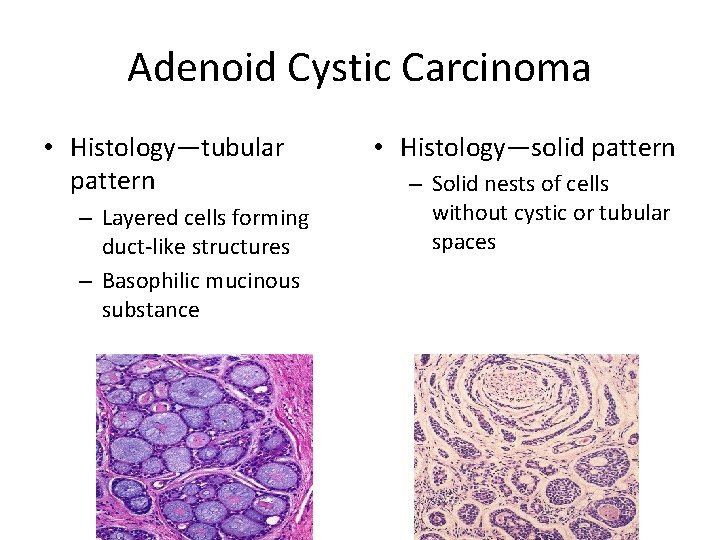
Adenoid Cystic Carcinoma • Histology—tubular pattern – Layered cells forming duct‐like structures – Basophilic mucinous substance • Histology—solid pattern – Solid nests of cells without cystic or tubular spaces
Adenoid Cystic Carcinoma • Treatment – Complete local excision – Tendency for perineural invasion: facial nerve sacrifice – Postoperative XRT • Prognosis – Local recurrence: 42% – Distant metastasis: lung – Indolent course: 5‐year survival 75%, 20‐year survival 13%
Acinic Cell Carcinoma • 2 nd most common parotid and pediatric malignancy • 5 th decade • F>M • Bilateral parotid disease in 3% • Presentation – Solitary, slow‐growing, often painless mass
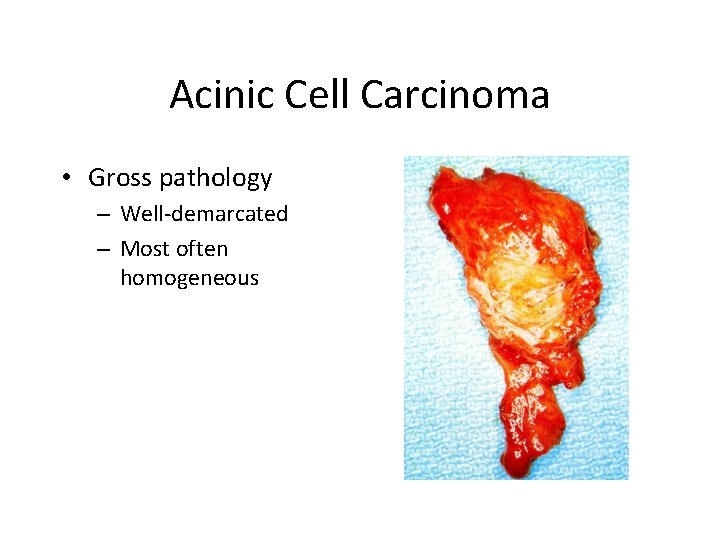
Acinic Cell Carcinoma • Gross pathology – Well‐demarcated – Most often homogeneous
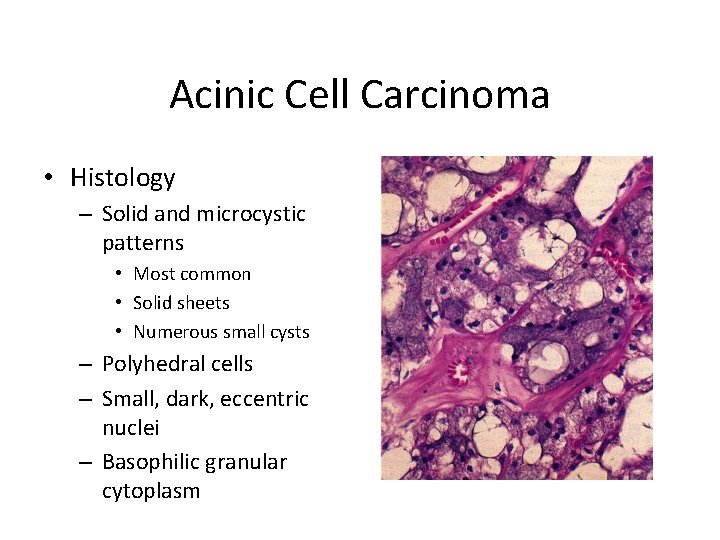
Acinic Cell Carcinoma • Histology – Solid and microcystic patterns • Most common • Solid sheets • Numerous small cysts – Polyhedral cells – Small, dark, eccentric nuclei – Basophilic granular cytoplasm
Acinic Cell Carcinoma • Treatment – Complete local excision – +/‐ postoperative XRT • Prognosis – 5‐year survival: 82% – 10‐year survival: 68% – 25‐year survival: 50%
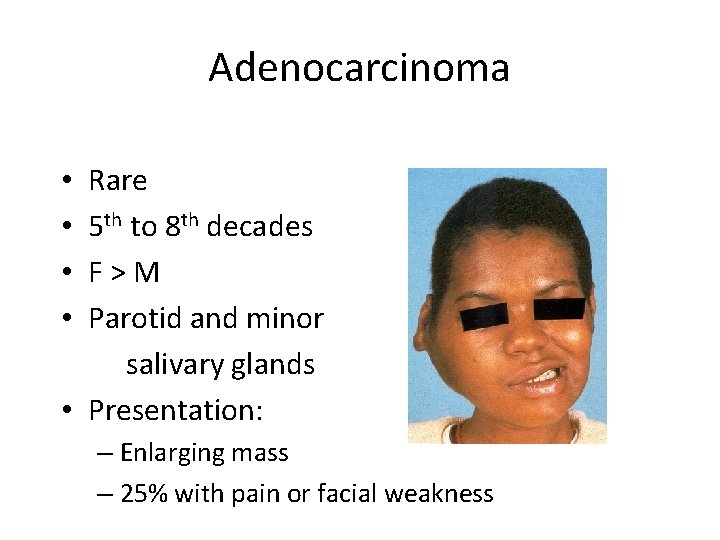
Adenocarcinoma Rare 5 th to 8 th decades F>M Parotid and minor salivary glands • Presentation: • • – Enlarging mass – 25% with pain or facial weakness
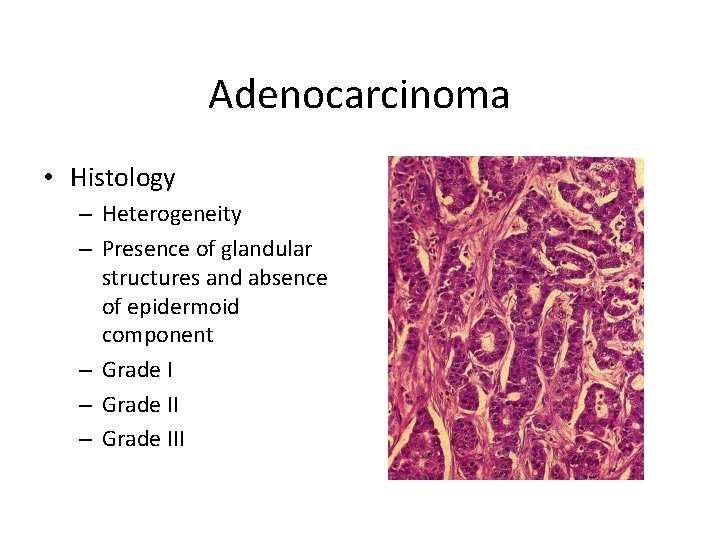
Adenocarcinoma • Histology – Heterogeneity – Presence of glandular structures and absence of epidermoid component – Grade III
Adenocarcinoma • Treatment – Complete local excision – Neck dissection – Postoperative XRT • Prognosis – – Local recurrence: 51% Regional metastasis: 27% Distant metastasis: 26% 15‐year cure rate: – Stage I = 67% – Stage II = 35% – Stage III = 8%
Malignant Mixed Tumors • Carcinoma ex‐pleomorphic adenoma • Carcinoma developing in the epithelial component of preexisting pleomorphic adenoma • Carcinosarcoma • True malignant mixed tumor—carcinomatous and sarcomatous components • Metastatic mixed tumor • Metastatic deposits of otherwise typical pleomorphic adenoma
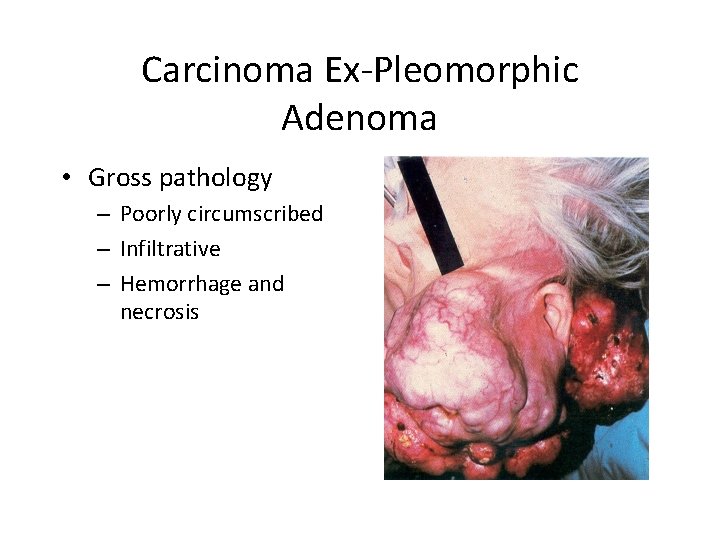
Carcinoma Ex‐Pleomorphic Adenoma • • • 2‐ 4% of all salivary gland neoplasms 4‐ 6% of mixed tumors 6 th‐ 8 th decades Parotid > submandibular > palate Risk of malignant degeneration • 1. 5% in first 5 years • 9. 5% after 15 years • Presentation • Longstanding painless mass that undergoes sudden enlargement
Carcinoma Ex‐Pleomorphic Adenoma • Gross pathology – Poorly circumscribed – Infiltrative – Hemorrhage and necrosis
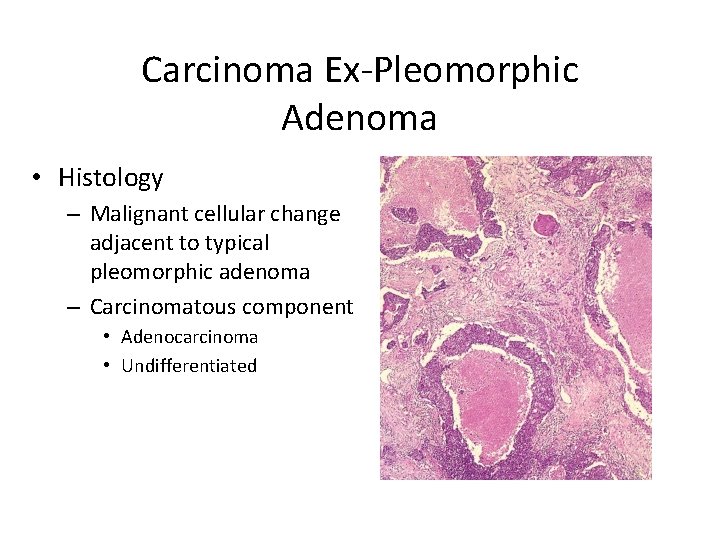
Carcinoma Ex‐Pleomorphic Adenoma • Histology – Malignant cellular change adjacent to typical pleomorphic adenoma – Carcinomatous component • Adenocarcinoma • Undifferentiated
Carcinoma Ex‐Pleomorphic Adenoma • Treatment – Radical excision – Neck dissection (25% with lymph node involvement at presentation) – Postoperative XRT • Prognosis – Dependent upon stage and histology
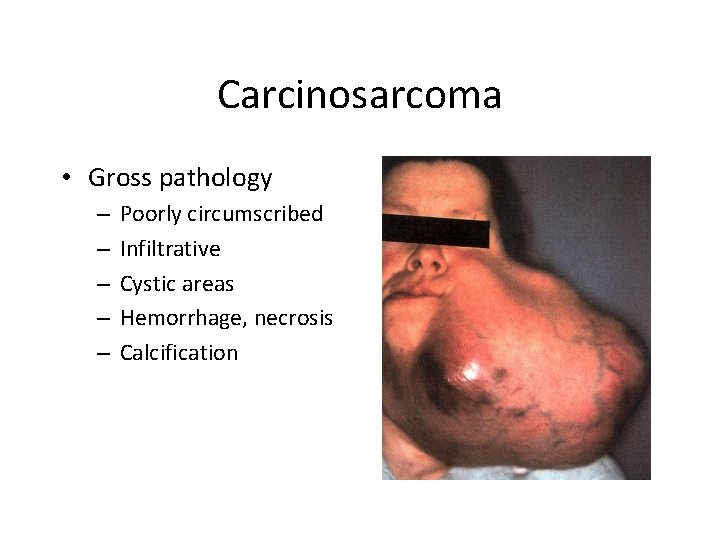
Carcinosarcoma Rare: <. 05% of salivary gland neoplasms 6 th decade M=F Parotid History of previously excised pleomorphic adenoma, recurrent pleomorphic adenoma or recurring pleomorphic treated with XRT • Presentation • • •
Carcinosarcoma • Gross pathology – – – Poorly circumscribed Infiltrative Cystic areas Hemorrhage, necrosis Calcification
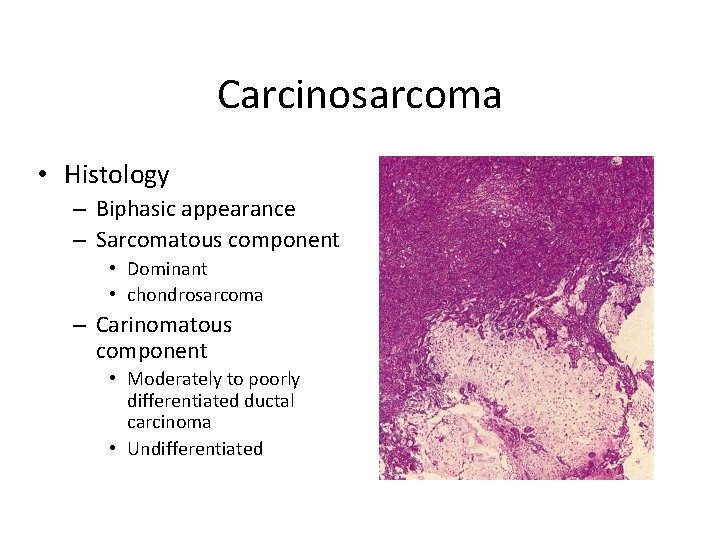
Carcinosarcoma • Histology – Biphasic appearance – Sarcomatous component • Dominant • chondrosarcoma – Carinomatous component • Moderately to poorly differentiated ductal carcinoma • Undifferentiated
Carcinosarcoma • Treatment – Radical excision – Neck dissection – Postoperative XRT – Chemotherapy (distant metastasis to lung, liver, bone, brain) • Prognosis – Poor, average survival less than 2 ½ years
Squamous Cell Carcinoma • • 1. 6% of salivary gland neoplasms 7 th‐ 8 th decades M: F = 2: 1 MUST RULE OUT: • High‐grade mucoepidermoid carcinoma • Metastatic SCCA to intraglandular nodes • Direct extension of SCCA
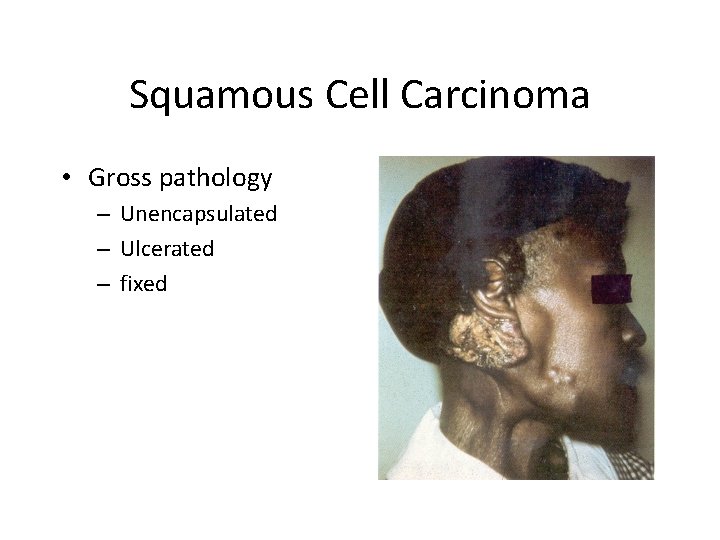
Squamous Cell Carcinoma • Gross pathology – Unencapsulated – Ulcerated – fixed
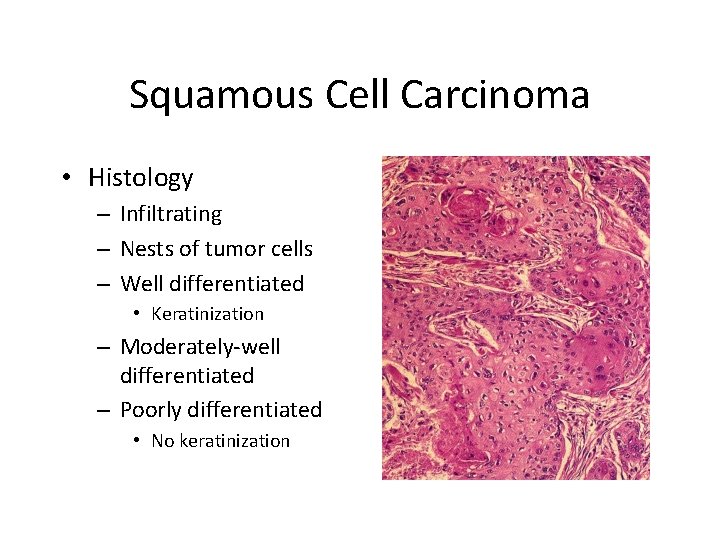
Squamous Cell Carcinoma • Histology – Infiltrating – Nests of tumor cells – Well differentiated • Keratinization – Moderately‐well differentiated – Poorly differentiated • No keratinization
Squamous Cell Carcinoma • Treatment – Radical excision – Neck dissection – Postoperative XRT • Prognosis – 5‐year survival: 24% – 10‐year survival: 18%
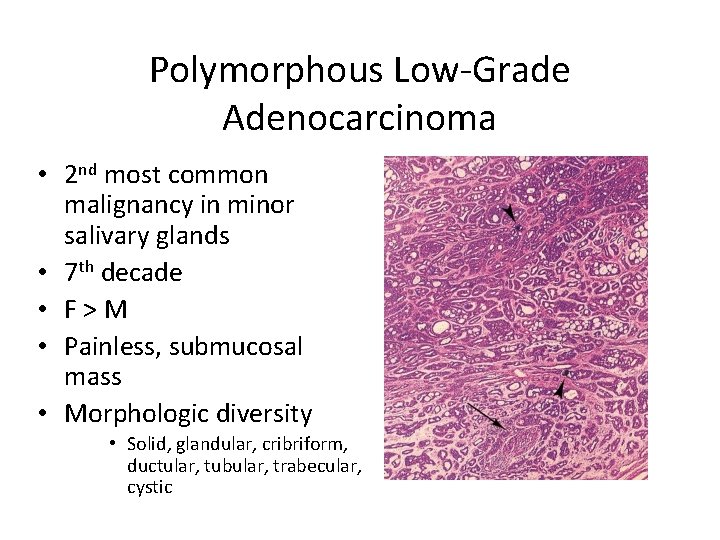
Polymorphous Low‐Grade Adenocarcinoma • 2 nd most common malignancy in minor salivary glands • 7 th decade • F>M • Painless, submucosal mass • Morphologic diversity • Solid, glandular, cribriform, ductular, tubular, trabecular, cystic
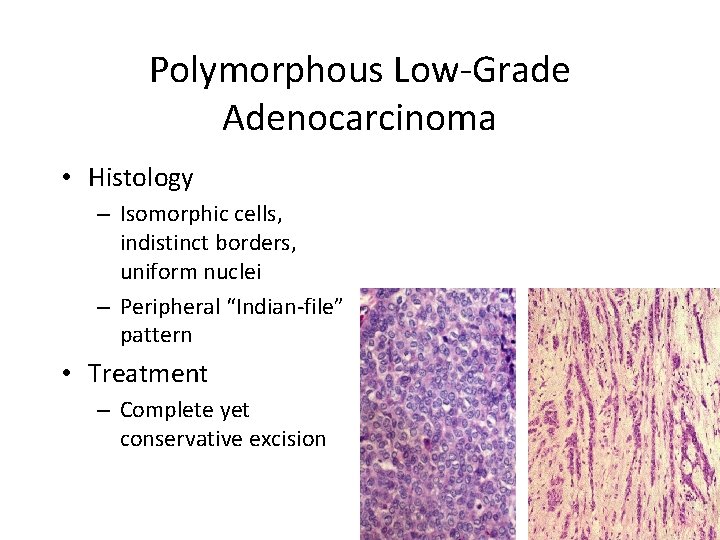
Polymorphous Low‐Grade Adenocarcinoma • Histology – Isomorphic cells, indistinct borders, uniform nuclei – Peripheral “Indian‐file” pattern • Treatment – Complete yet conservative excision
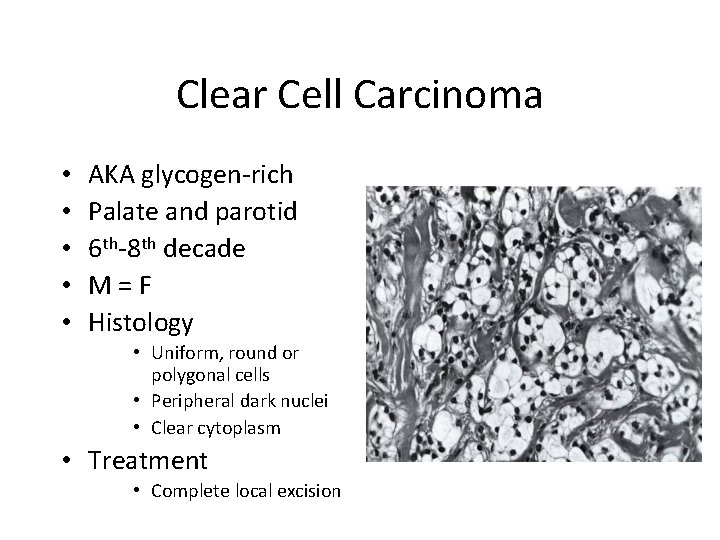
Clear Cell Carcinoma • • • AKA glycogen‐rich Palate and parotid 6 th‐ 8 th decade M=F Histology • Uniform, round or polygonal cells • Peripheral dark nuclei • Clear cytoplasm • Treatment • Complete local excision
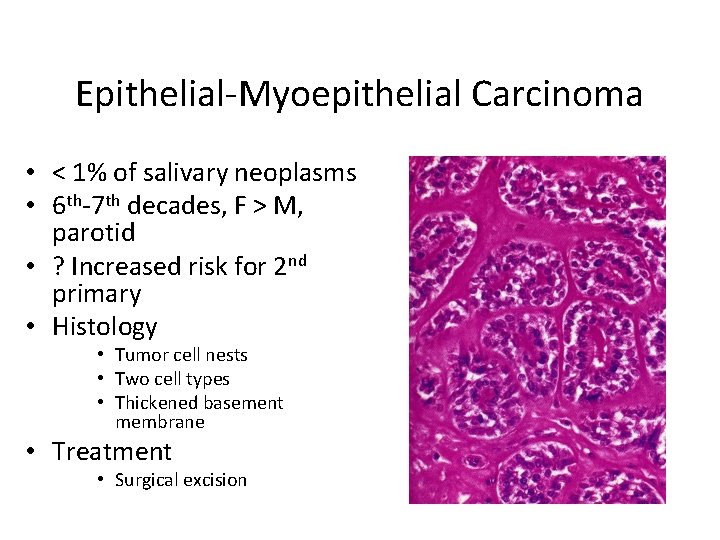
Epithelial‐Myoepithelial Carcinoma • < 1% of salivary neoplasms • 6 th‐ 7 th decades, F > M, parotid • ? Increased risk for 2 nd primary • Histology • Tumor cell nests • Two cell types • Thickened basement membrane • Treatment • Surgical excision
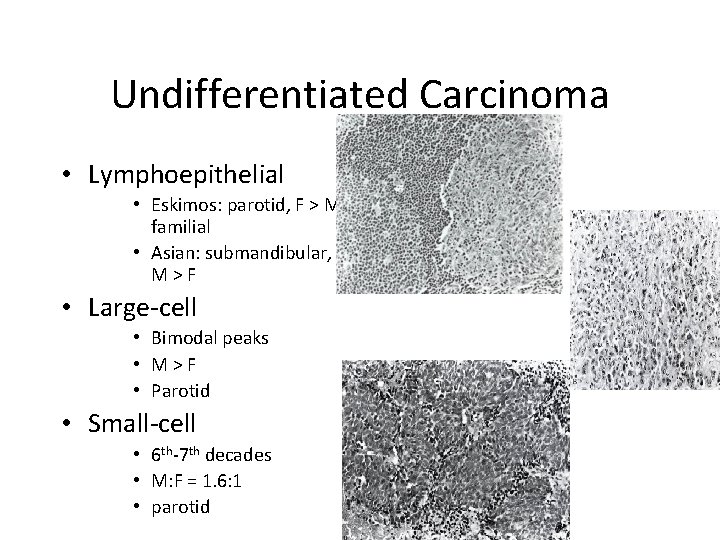
Undifferentiated Carcinoma • Lymphoepithelial • Eskimos: parotid, F > M, familial • Asian: submandibular, M>F • Large‐cell • Bimodal peaks • M>F • Parotid • Small‐cell • 6 th‐ 7 th decades • M: F = 1. 6: 1 • parotid
Controversial Issues • Management of the N 0 Neck – Recurrence in the neck = low likelihood of salvage – Parotid: clinical neck disease, 16% • N‐ disease = 74% 5‐year survival • N+ disease = 9% 5‐year survival – Submandibular: clinical neck disease, 8% • N‐ disease = 41% 5‐year survival • N+ disease = 9% 5‐year survival
Management of the N 0 Neck • Increase risk of occult neck metastasis – **High‐grade malignancies – **Advanced primary tumor stage (T 3‐T 4) – High risk histology – Undifferentiated, SCCA, adenocarcinoma, high‐grade mucoepidermoid, salivary duct carcinoma – Tumor size > 3 cm – Patient > 54 years of age – Facial paralysis – Extracapsular, perilymphatic spread
Management of the N 0 Neck • Neck Dissection – Advantages – Pathologic staging – Improved counseling and prediction of prognosis – Disadvantages – Longer OR time, increase complications, increased cost – Functional deficits, cosmetic effects – Type • Parotid: levels II‐IV • Submandibular: levels I‐III
Management of the N 0 Neck • Radiation Therapy – Advantage – Avoids surgical sequlae – Disadvantages – Radiation effect on normal tissue – Radiation induced malignancies – Proponents argument: the same factors that increase the risk of occult neck disease also increase the risk for local recurrence and necessitate postoperative XRT to the primary so it is reasonable to treat the neck with XRT as well
Fine‐Needle Aspiration Biopsy • Efficacy is well established • Accuracy = 84‐ 97% • Sensitivity = 54‐ 95% • Specificity = 86=100% • Safe, well tolerated
Fine‐Needle Aspiration Biopsy • Opponents argument: – Doesn’t change management • Surgery regardless of reported diagnosis – Obscuring final pathologic diagnosis – Frequency of “inadequate” sampling, requires multiple biopsies, prolongs course until definitive treatment, increases cost
Fine‐Needle Aspiration Biopsy • Proponent’s argument: – Important to distinguish benign vs. malignant nature of neoplasm – Preoperative patient counseling – Surgical planning – Differentiate between neoplastic and non‐ neoplastic processes • Avoid surgery in large number of patients
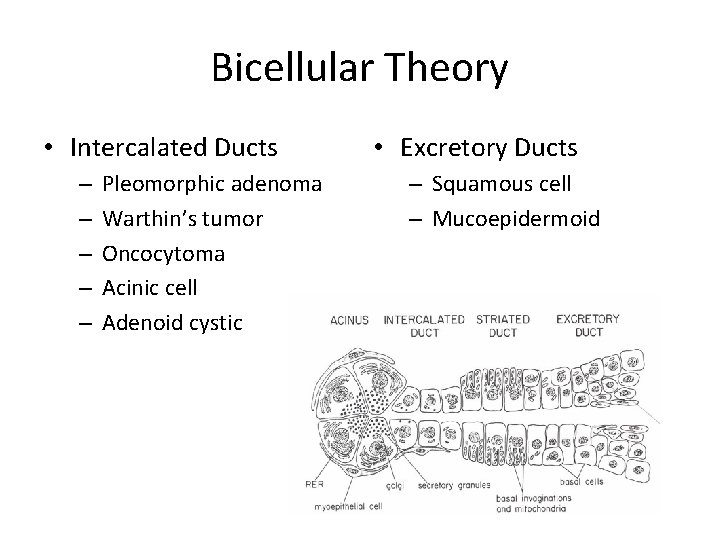
Bicellular Theory • Intercalated Ducts – – – Pleomorphic adenoma Warthin’s tumor Oncocytoma Acinic cell Adenoid cystic • Excretory Ducts – Squamous cell – Mucoepidermoid
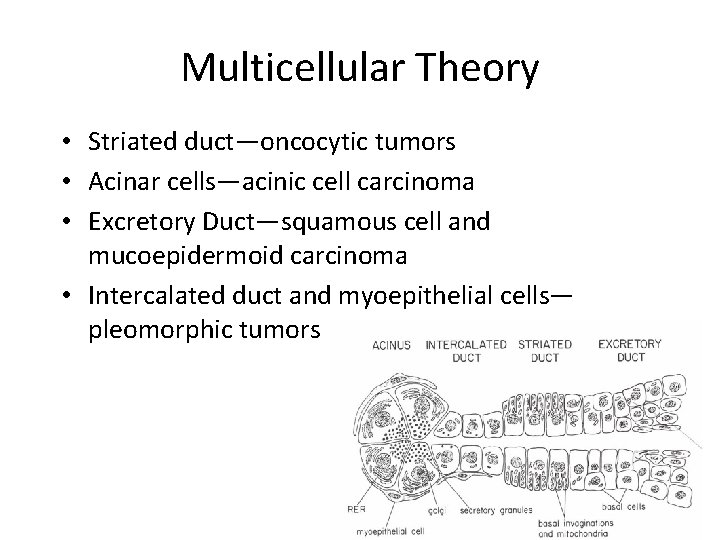
Multicellular Theory • Striated duct—oncocytic tumors • Acinar cells—acinic cell carcinoma • Excretory Duct—squamous cell and mucoepidermoid carcinoma • Intercalated duct and myoepithelial cells— pleomorphic tumors
Tumorigenesis • Contradictory evidence: – Luminal cells are readily capable of replication – Acinar cells participate in gland regeneration – Immunohistochemical staining of S‐ 100 protein • Present in many salivary gland neoplasms • Not present in normal ductal cells
Conclusions • Hugely diverse histopathology • Accurate pathologic diagnosis does influence management • Relatively rare malignancies • Utilize preoperative studies when indicated • Don’t believe everything you read!