
THE RED EYE EM Rounds Colleen Carey BA

THE RED EYE EM Rounds Colleen Carey, BA, MD, CCFP (EM) July 31, 2008 Thanks to Dr. Jean Chuo, UBC Ophthalmology Resident

Goals � � � Hx Exam Most common etiologies � Traumatic versus atraumatic � Diagnosis � Treatment � When to get help
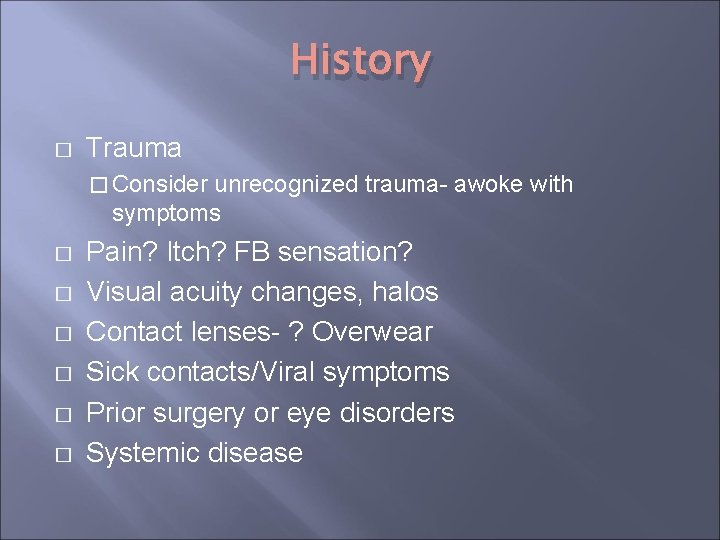
History � Trauma � Consider unrecognized trauma- awoke with symptoms � � � Pain? Itch? FB sensation? Visual acuity changes, halos Contact lenses- ? Overwear Sick contacts/Viral symptoms Prior surgery or eye disorders Systemic disease

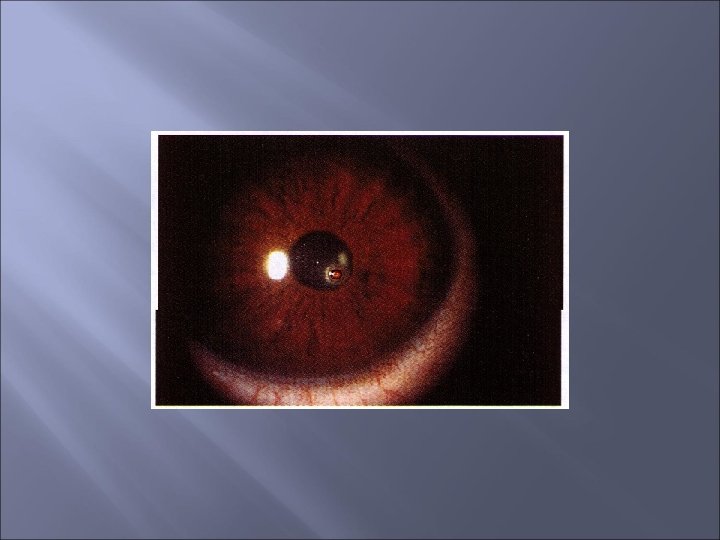
Red eye exam � � � Visual acuity Visual fields Pupil shape and reactivity Lid closure Foreign bodies Ciliary flare Foggy cornea (edema) Corneal infiltrate Fluorescein- corneal defects, Sidel’s sign Anterior chamber cells Intraocular pressure

Foreign body � Projectile metallic FB � Get � orbital Xray Rust ring � Visual axis involved? - refer if unable to completely remove � Burr � � Tetanus status Antibiotic prophylaxis?
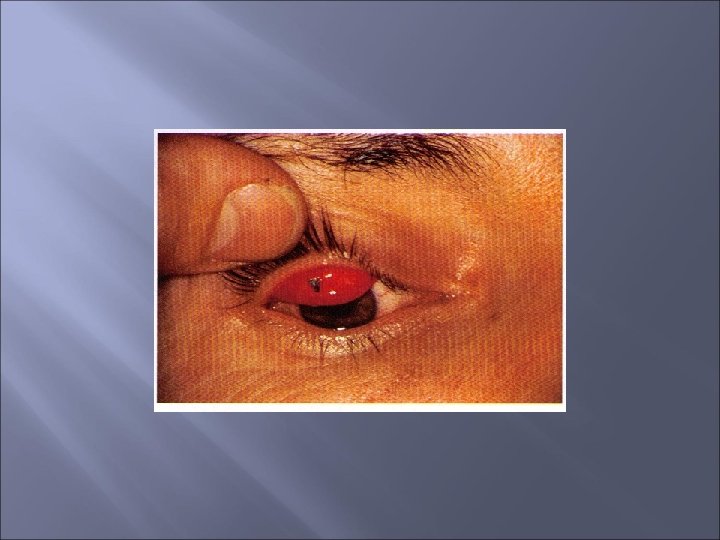

Corneal abrasion � Get help if � not healing � corneal ulcer � large surface area � infringing on visual axis
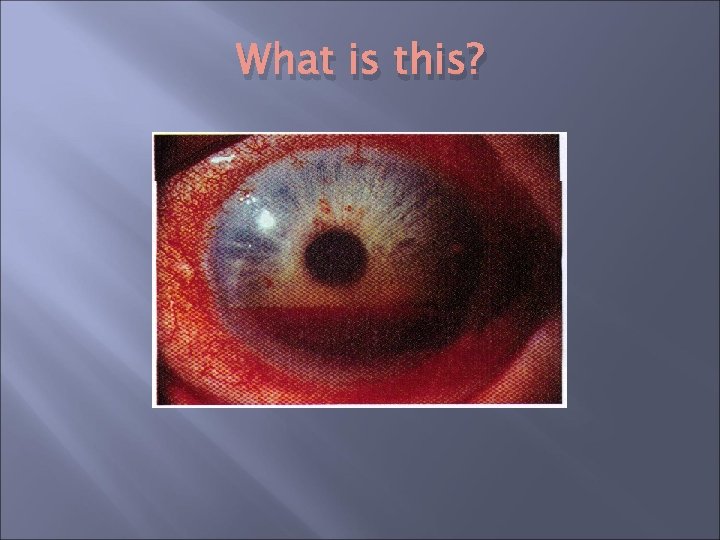
What is this?

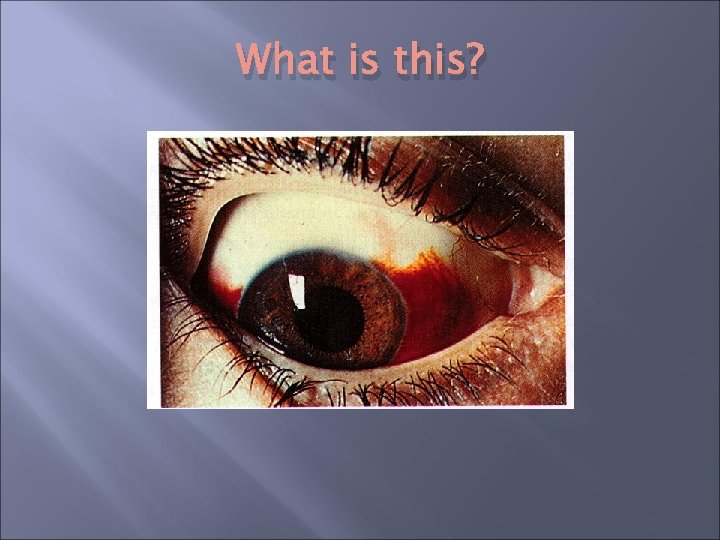
Hyphema � � � Usually due to blunt trauma and immediate Gross: layers out Microscopic: cells in anterior chamber Always refer Tx: cycloplegics, steroids, serial IOP monitoring, sleep sitting upright, avoid valsalva, avoid anticoagulants, hard shield, avoid exertion Complications: � Iritis � Synechiae, glaucoma � Rebleeding
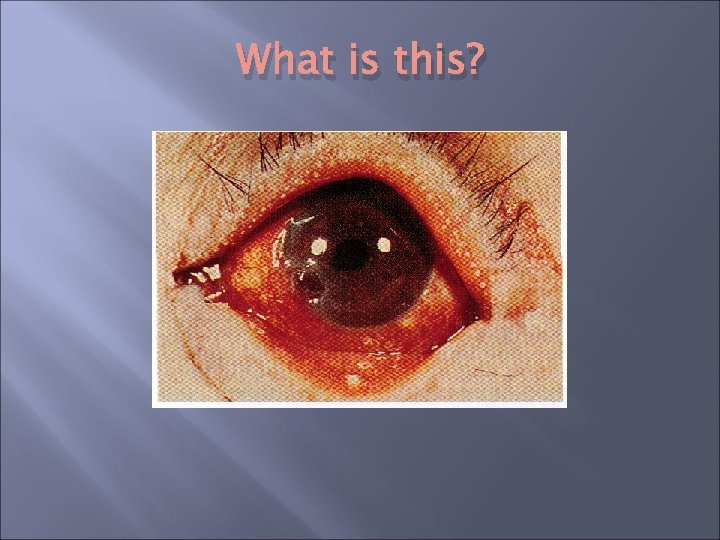
What is this?

Globe rupture � � � � Penetrating FB Blunt trauma by an object smaller than a fist Blunt trauma with an orbital fracture Prior open globe surgery All must be repaired to prevent sympathetic ophthalmia Need a hard shield. Emergency referral, poor prognosis
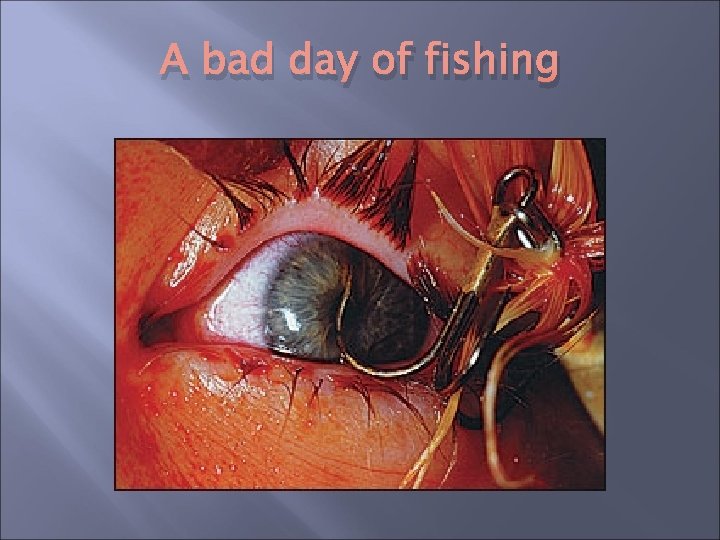
A bad day of fishing

Endophthalmitis � � � Red, painful, decreased vision Anterior chamber cells+/- hypopion Almost exclusively post-surgical complication Rare: 1: 100, 000 cataract surgeries Urgent referral
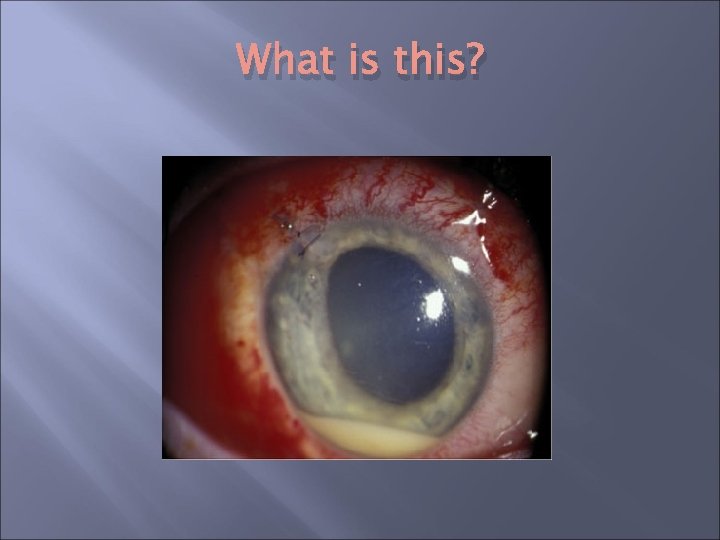
What is this?

What is this?

Superficial punctate keratitis � � � Very common problem Mild itch, dry, gritty sandpaper sensation Many causes: � Contact lens overwear � Dry Calgary air � Preservatives, antibiotic eye drops � Incomplete lid closure � � Rule out other problems Discontinue cause, moisturize, follow up in ER
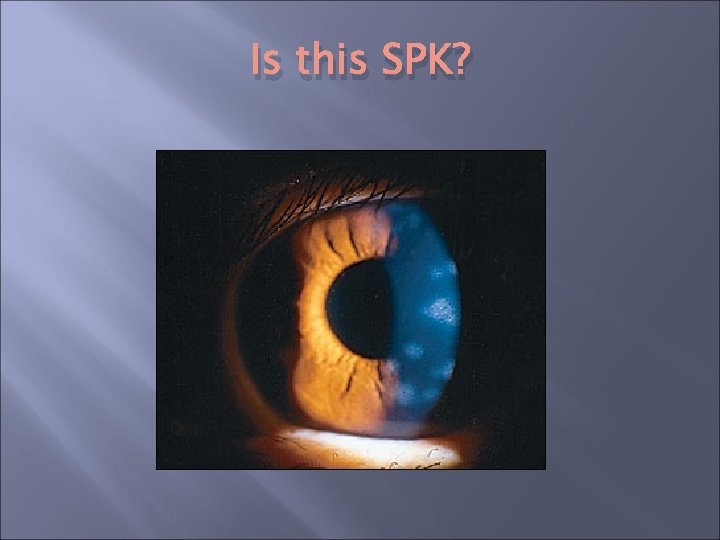
Is this SPK?

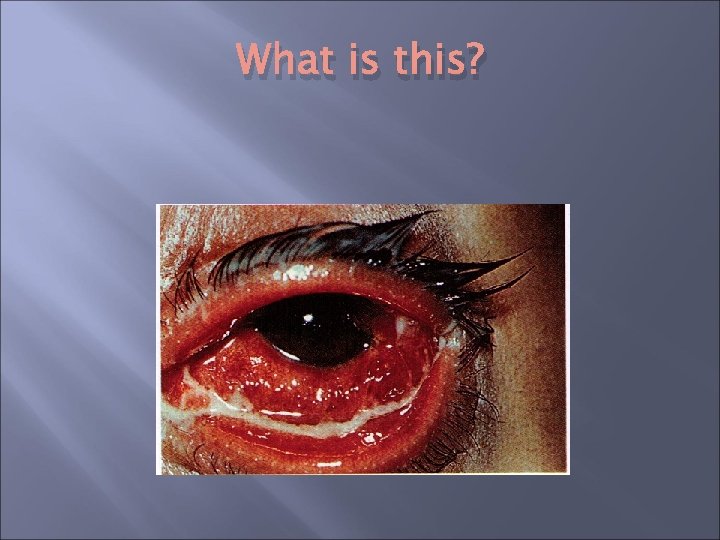
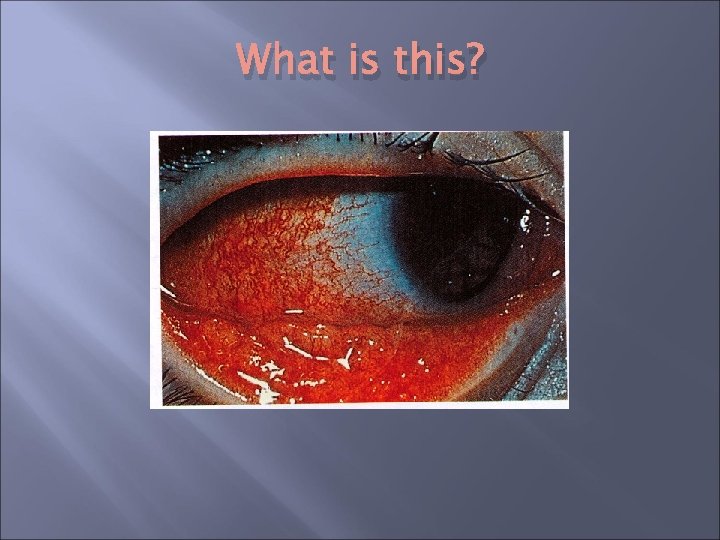
Conjunctivitis/keratoconjunctivitis � � � � Allergic Viral Bacterial Irritative Treat bacterial conjunctivitis with flouroquinolone or erythromycin drops. Treat allergic with antihistamines, nasal steroid spray, allergen avoidance, cromolyn drops Refer any keratitis
What is this?
What is this?

What is this? � Short fat branches with bulbs

Herpes Simplex Virus � HSV keratitis � Dendritic fluoroscein enhancing lesion � Hypoesthetic cornea � +/- periocular HSV vesicles • Tx is acyclovir +/- viroptic drops • HSV can affect any part of the eye • Next day referral as long as Tx started
What is this? � Long thin tapered branches

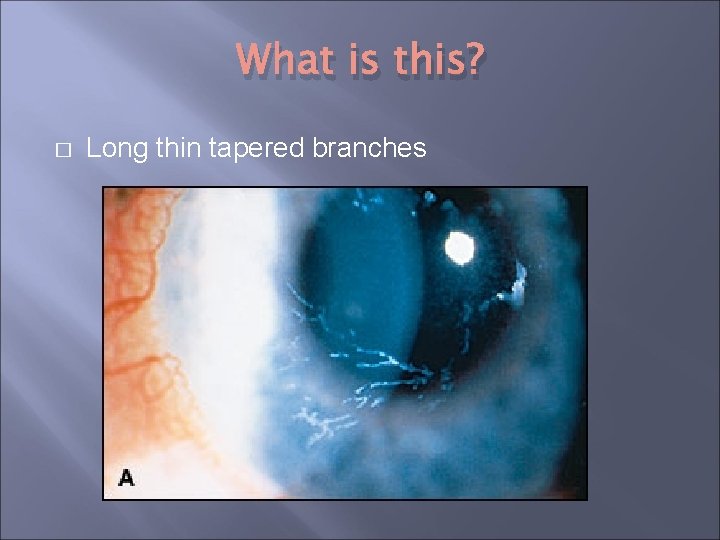
Herpes Zoster Ophthalmicus � � HHV 3 (VZV) V 1 (opthalmic branch of CN V) � Macular � � � rash =>vesicular lesions Conjunctivitis Keratitis Uveitis/iritis +/- retinal necrosis Cranial nerve palsies 3, 4, 6 Cxns: Chronic ocular inflammation, vision loss, neuralgia, late corneal sequelae

Acute angle closure glaucoma � � � Risk Fx: Family Hx, contralateral eye, hyperopia, Asian race, age Hx: Sudden eye pain, photophobia, halos PE: Shallow anterior chamber, iris bombe, middilated pupil, hazy cornea, elevated IOP Tx: one drop each of: 0. 5% timolol 1%, apraclonidine, and 2% pilocarpine. Oral acetazolamide, IV mannitol Ensure pressure drops within an hour
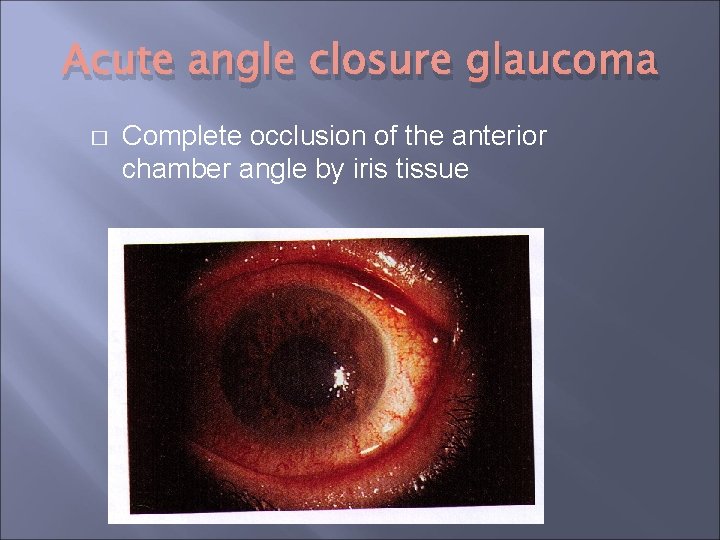
Acute angle closure glaucoma � Complete occlusion of the anterior chamber angle by iris tissue

Iritis � � � Causes: Infections, eye disorders, systemic disorders Trauma, autoimmune disorders, VZV, lyme disease, leukemia/lymphoma, idiopathic Photophobia and dull ache Urgent referral to ophtho Get baseline IOP and start Predforte drops and cycloplegics
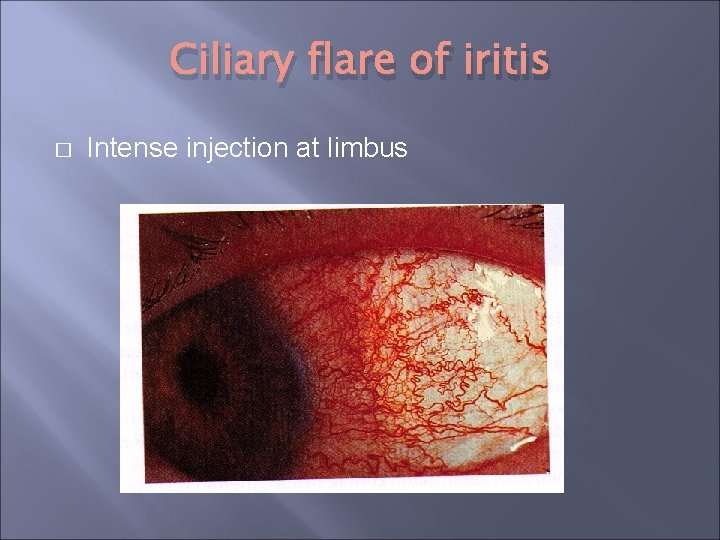
Ciliary flare of iritis � Intense injection at limbus
What is this?

Subconjunctival hemorrhage � Causes � Valsalva � Coagulopathy � Presentation � Visual acuity � Absence of pain � Absence of photophobia � Absence of discharge � Should resorb in 1 -2 weeks
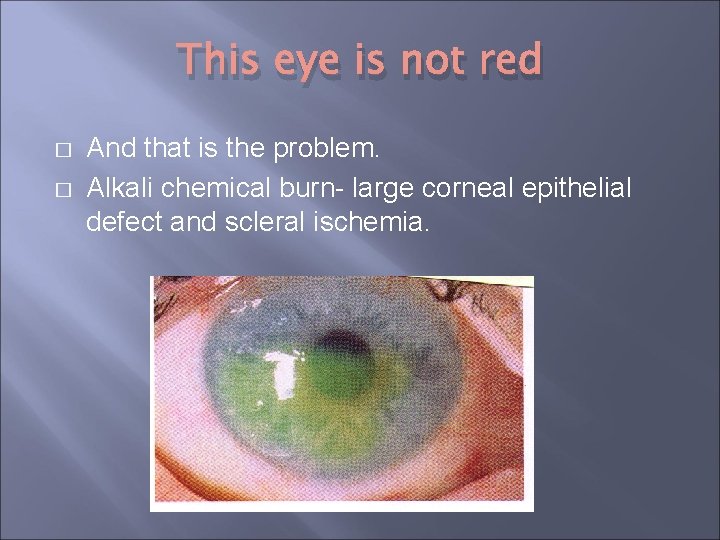
This eye is not red � � And that is the problem. Alkali chemical burn- large corneal epithelial defect and scleral ischemia.

� � Of all the conditions you have seen today, this is the fastest to destroy an eye, and can have the worst prognosis You have only minutes to diagnose and irrigate Morgan lens, many litres Afterward: confirm p. H, slit lamp exam for corneal defect, r/o deposits in conjunctival recesses.
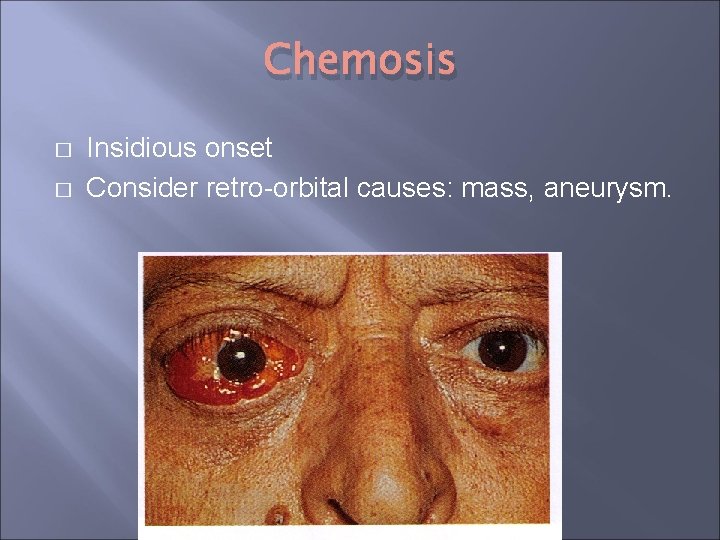
Chemosis � � Insidious onset Consider retro-orbital causes: mass, aneurysm.
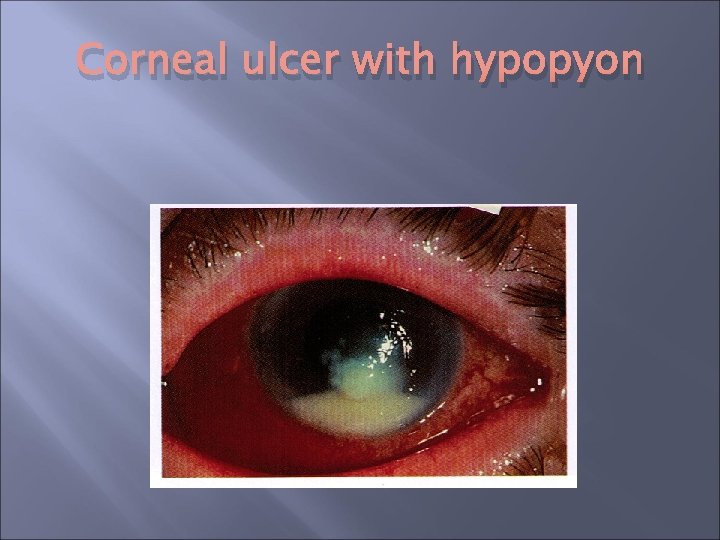
Corneal ulcer with hypopyon
What is this?
What is this?

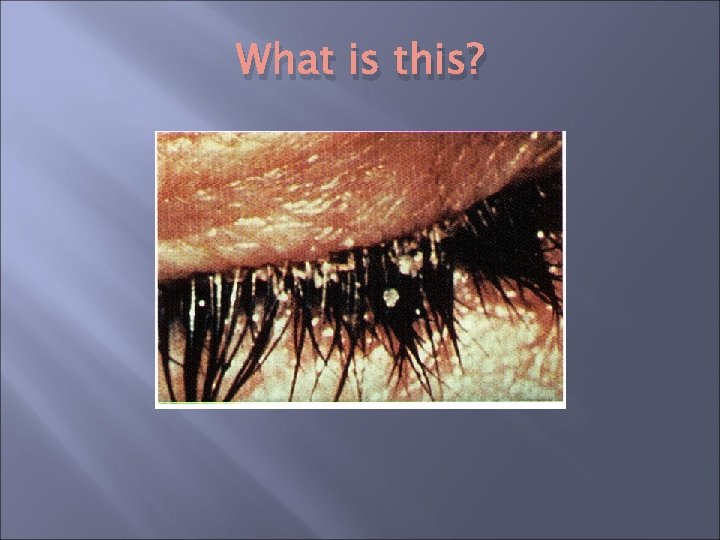
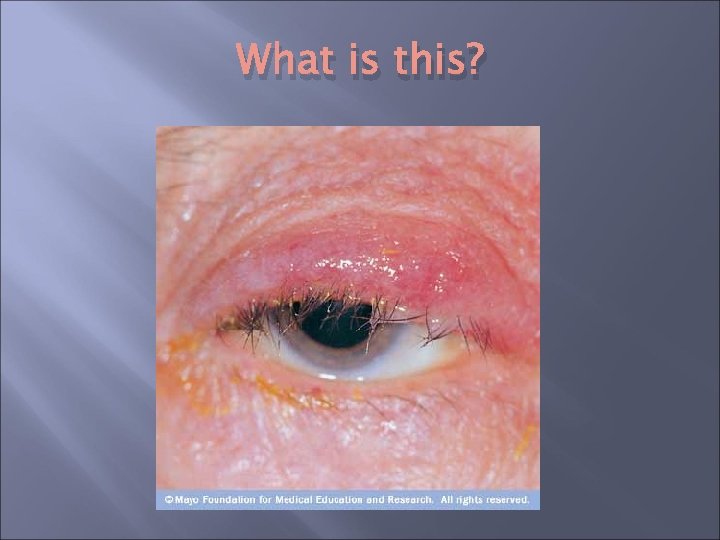
Blepharitis � � � Chronic recurrent eyelid inflammation Staph aureus or seborrhea (pityrosporum) Warm lid compresses Topical antibiotic eyedrops+/- ointment Dandruff shampoos to scalp to eradicate pityrosporum Slow response
What is this?

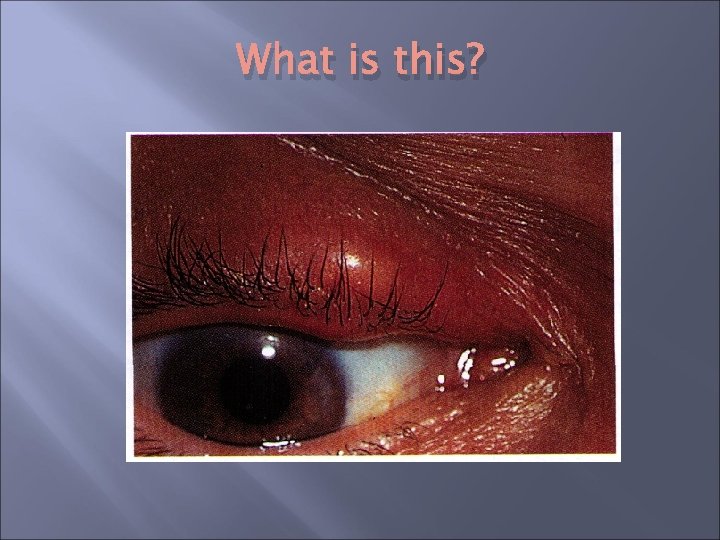
Stye � � � Hordeolum- acute, painful Chalzion- chronic, non painful Hot compresses, milking Refer if not resolving for I+C Chronic lesions- ? Biopsy to r/o CA
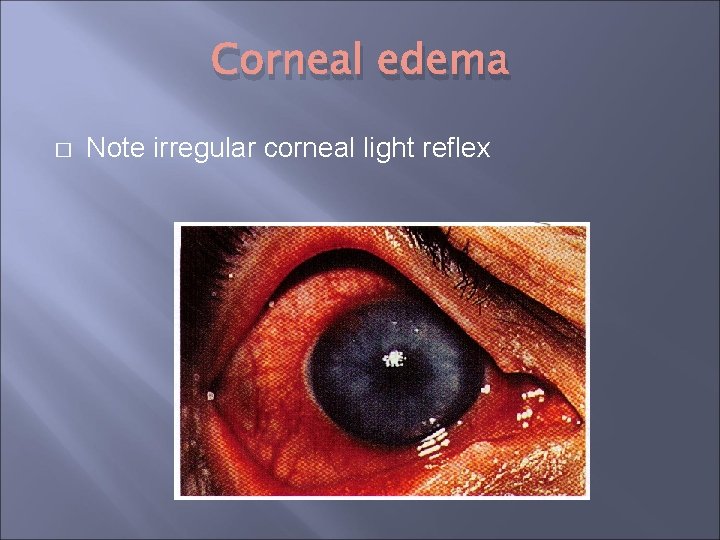
Corneal edema � Note irregular corneal light reflex
- Slides: 41