
THE CARDIOVASCULAR EFFECTS OF COCAINE BRYAN SCHWARTZ MD

THE CARDIOVASCULAR EFFECTS OF COCAINE BRYAN SCHWARTZ, MD, SHEREIF REZKALLA, MD, ROBERT KLONER, MD, PHD

Why should cardiologists care about cocaine? Cocaine accounted for 31% of ER visits related to drug misuse or abuse. Volkow ND. National Institute on Drug Abuse. 2009. Of 233 ER visits by cocaine-using patients: 56% presented with cardiovascular complaints, 40% presented with chest pain. Brody SL. Am J Med 1990; 88: 325. Cocaine users have higher incidence of MI (OR 3. 86. 9). Aslibekyan S. Am J Cardiol. 2008; 102: 966. Mittleman ST MA. Circulation. 1999; 99: 2737. Risk of MI increases by 24 -fold in 1 hr after cocaine use. Qureshi AI. Circulation. 2001; 103: 502.
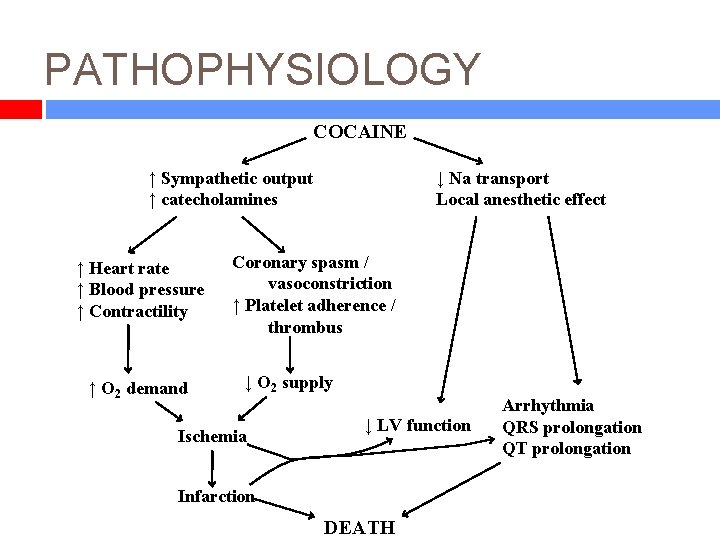
PATHOPHYSIOLOGY COCAINE ↑ Sympathetic output ↑ catecholamines ↑ Heart rate ↑ Blood pressure ↑ Contractility ↑ O 2 demand ↓ Na transport Local anesthetic effect Coronary spasm / vasoconstriction ↑ Platelet adherence / thrombus ↓ O 2 supply Ischemia ↓ LV function Infarction DEATH Arrhythmia QRS prolongation QT prolongation
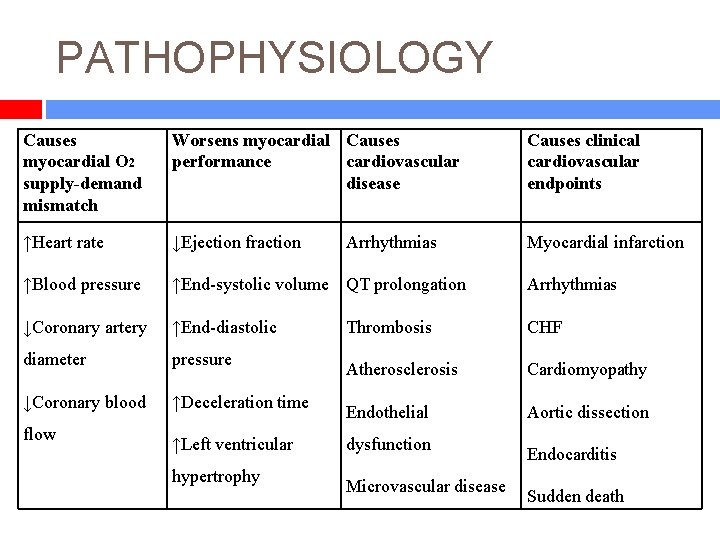
PATHOPHYSIOLOGY Causes myocardial O 2 supply-demand mismatch Worsens myocardial Causes performance cardiovascular disease Causes clinical cardiovascular endpoints ↑Heart rate ↓Ejection fraction Myocardial infarction ↑Blood pressure ↑End-systolic volume QT prolongation Arrhythmias ↓Coronary artery ↑End-diastolic Thrombosis CHF diameter pressure Atherosclerosis Cardiomyopathy ↓Coronary blood ↑Deceleration time Endothelial Aortic dissection flow ↑Left ventricular hypertrophy Arrhythmias dysfunction Microvascular disease Endocarditis Sudden death
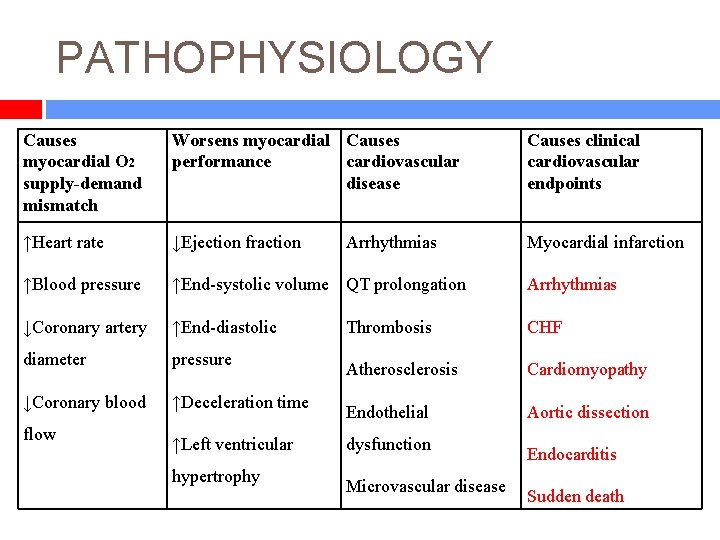
PATHOPHYSIOLOGY Causes myocardial O 2 supply-demand mismatch Worsens myocardial Causes performance cardiovascular disease Causes clinical cardiovascular endpoints ↑Heart rate ↓Ejection fraction Myocardial infarction ↑Blood pressure ↑End-systolic volume QT prolongation Arrhythmias ↓Coronary artery ↑End-diastolic Thrombosis CHF diameter pressure Atherosclerosis Cardiomyopathy ↓Coronary blood ↑Deceleration time Endothelial Aortic dissection flow ↑Left ventricular hypertrophy Arrhythmias dysfunction Microvascular disease Endocarditis Sudden death
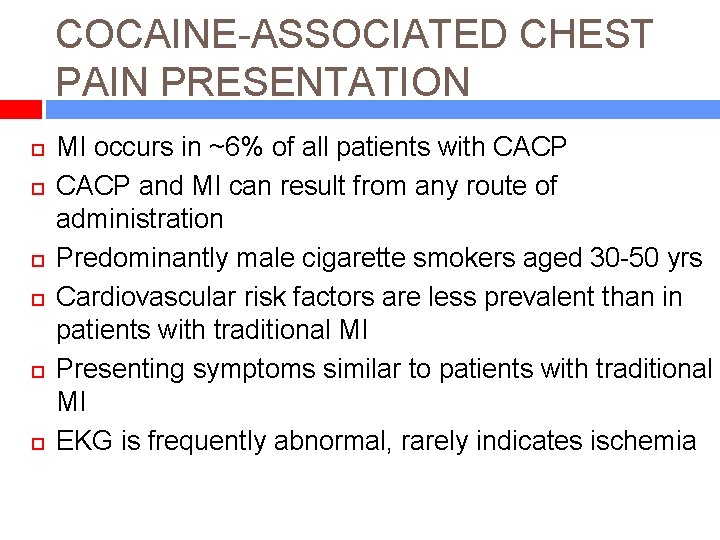
COCAINE-ASSOCIATED CHEST PAIN PRESENTATION . MI occurs in ~6% of all patients with CACP and MI can result from any route of administration Predominantly male cigarette smokers aged 30 -50 yrs Cardiovascular risk factors are less prevalent than in patients with traditional MI Presenting symptoms similar to patients with traditional MI EKG is frequently abnormal, rarely indicates ischemia
COCAINE-ASSOCIATED CHEST PAIN PRESENTATION MI occurs in ~6% of all patients with CACP and MI can result from any route of administration Predominantly male cigarette smokers aged 30 -50 yrs Cardiovascular risk factors are less prevalent than in patients with traditional MI Presenting symptoms similar to patients with traditional MI EKG is frequently abnormal, rarely indicates ischemia . NOTHING DIFFERENTIATES PATIENTS WITH CACP

COCAINE ASSOCIATED CHEST PAIN DIAGNOSIS High-risk patients (42/344; 12%) directly admitted Non high-risk cocaine using patients (302) were enrolled in a 12 -hour observation protocol: Troponin at presentation and after 3, 6, and 9 hours Continuous 12 -lead ST-segment monitoring None of 302 developed MI, arrhythmias or CHF in the observation unit and all were discharged from the unit. At 30 days: None died of CV causes 25% experienced recurrent chest pain 1. 3% developed nonfatal MI (all 4 continued to use Weber JE. Nfactors). Engl J Med. 2003; 348: 510. cocaine and had at least 2 cardiac risk
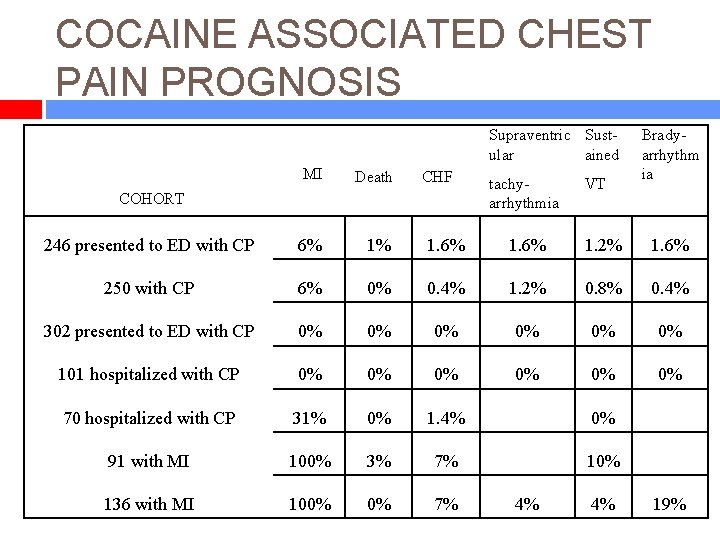
COCAINE ASSOCIATED CHEST PAIN PROGNOSIS Supraventric Sustular ained Bradyarrhythm ia MI Death 246 presented to ED with CP 6% 1% 1. 6% 1. 2% 1. 6% 250 with CP 6% 0% 0. 4% 1. 2% 0. 8% 0. 4% 302 presented to ED with CP 0% 0% 0% 101 hospitalized with CP 0% 0% 0% 70 hospitalized with CP 31% 0% 1. 4% 0% 91 with MI 100% 3% 7% 10% 136 with MI 100% 0% 7% CHF COHORT tachyarrhythmia 4% VT 4% 19%

AVOID BETA-BLOCKERS IN COCAINE USING PATIENTS Beta-blockade can leave alpha-stimulation unopposed → pronounced systemic and coronary vasoconstriction. In animal studies of acute cocaine toxicity, Catravas JD. J Pharmacol Exp Ther. 1981; 217: 350. propranolol worsened the seizure threshold and expedited death. Lange RA. Ann Intern Med. 1990; 112: 897. In humans, propranolol exacerbated cocaineinduced coronary artery vasoconstriction Sand IC. Am J Emerg Med. 1991; 9: 161. Esmolol increased blood pressure in 2 of 7 cocaine-using patients (in 1 from 200/120 to
AVOID BETA-BLOCKERS IN COCAINE-USING PATIENTS Labetalol and carvedilol offer theoretical advantage of blocking both α- and β -receptors. Labetalol did not reverse cocaine-induced coronary artery vasoconstriction. Boehrer JD. Am J Med. 1993; 94: 608. In pheochromocytoma labetalol caused severe Briggs RS. Lancet. 1978; 1: 1045. hypertension. Combined with cocaine, carvedilol 25 mg tended to increase BP. Sofuoglu M. Drug Alcohol Depend. 2000; 60: 69.
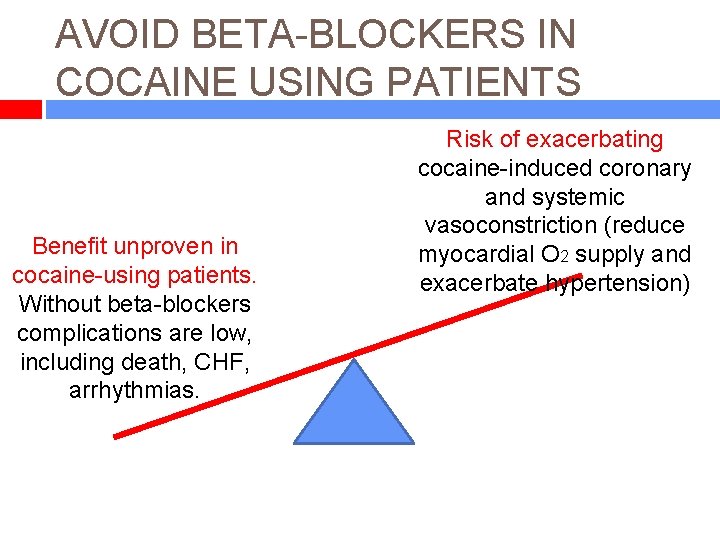
AVOID BETA-BLOCKERS IN COCAINE USING PATIENTS Benefit unproven in cocaine-using patients. Without beta-blockers complications are low, including death, CHF, arrhythmias. Risk of exacerbating cocaine-induced coronary and systemic vasoconstriction (reduce myocardial O 2 supply and exacerbate hypertension)
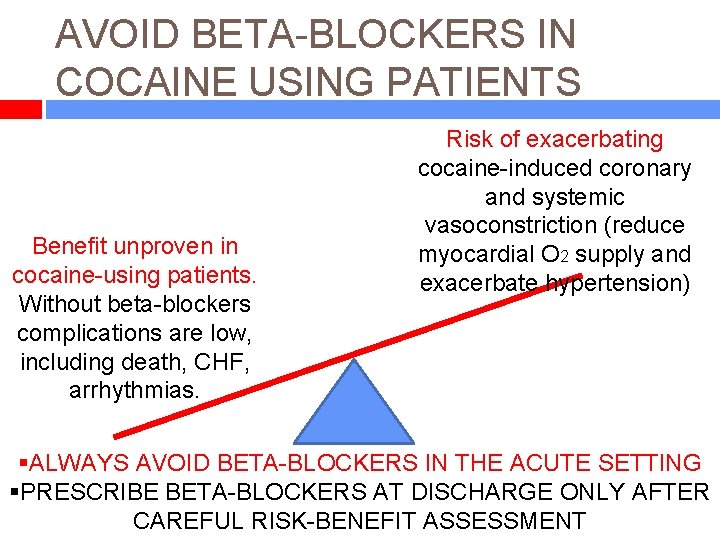
AVOID BETA-BLOCKERS IN COCAINE USING PATIENTS Benefit unproven in cocaine-using patients. Without beta-blockers complications are low, including death, CHF, arrhythmias. Risk of exacerbating cocaine-induced coronary and systemic vasoconstriction (reduce myocardial O 2 supply and exacerbate hypertension) §ALWAYS AVOID BETA-BLOCKERS IN THE ACUTE SETTING §PRESCRIBE BETA-BLOCKERS AT DISCHARGE ONLY AFTER CAREFUL RISK-BENEFIT ASSESSMENT
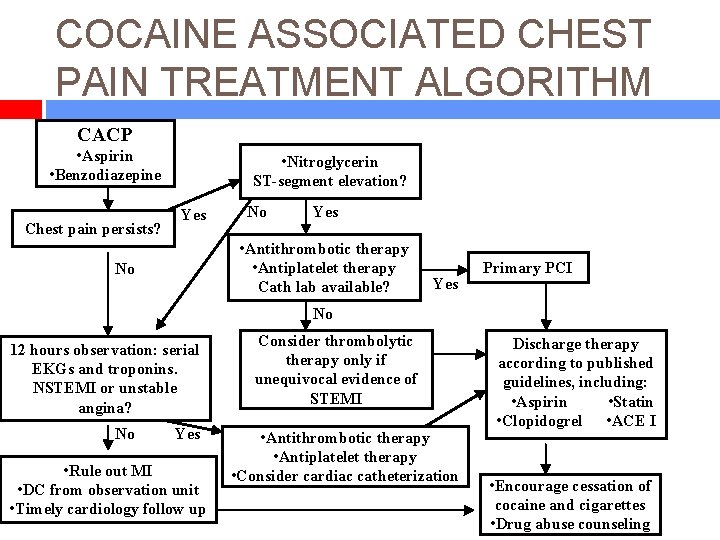
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
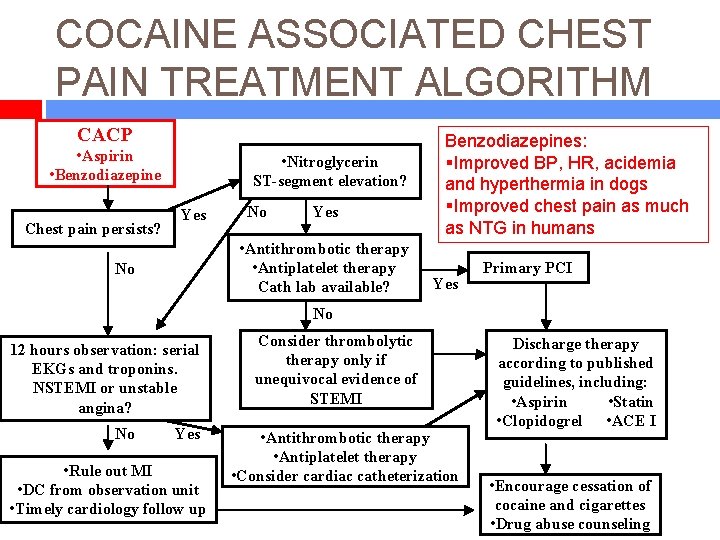
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No Benzodiazepines: §Improved BP, HR, acidemia and hyperthermia in dogs §Improved chest pain as much as NTG in humans Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
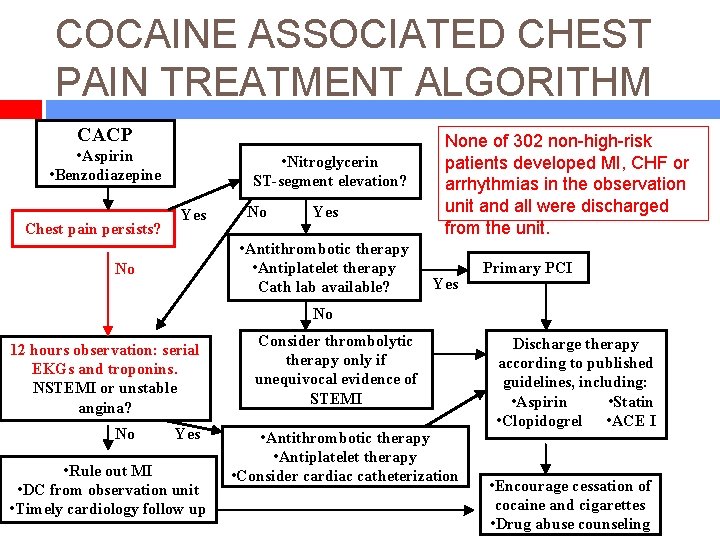
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No None of 302 non-high-risk patients developed MI, CHF or arrhythmias in the observation unit and all were discharged from the unit. Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
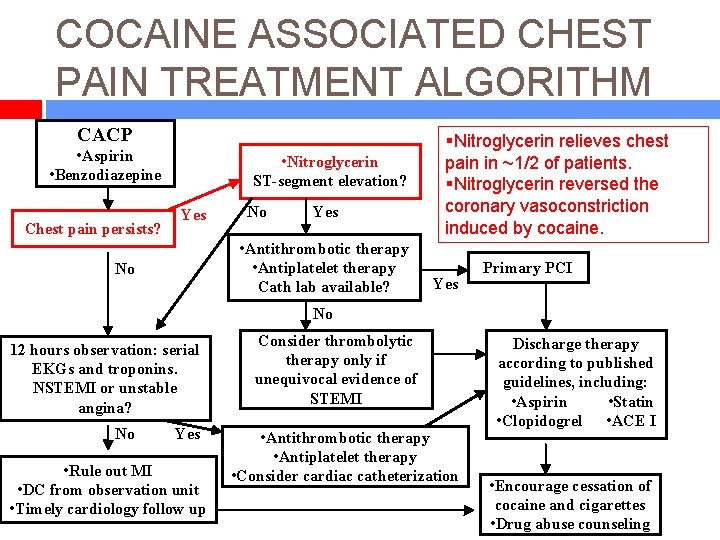
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No §Nitroglycerin relieves chest pain in ~1/2 of patients. §Nitroglycerin reversed the coronary vasoconstriction induced by cocaine. Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
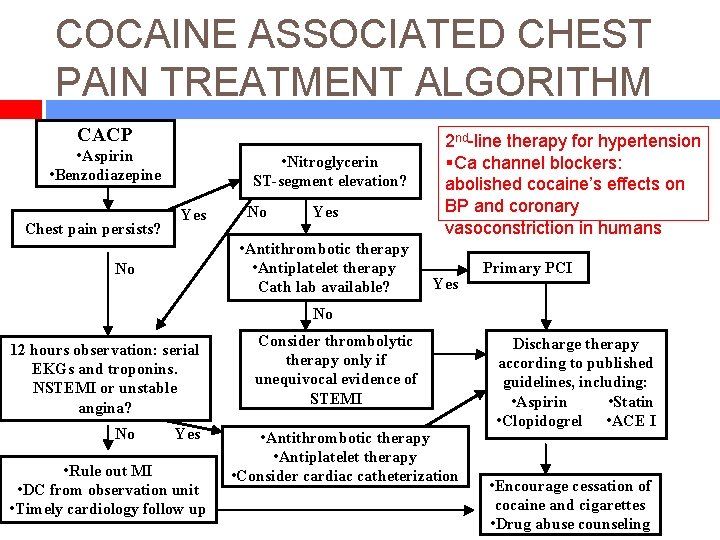
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No 2 nd-line therapy for hypertension §Ca channel blockers: abolished cocaine’s effects on BP and coronary vasoconstriction in humans Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
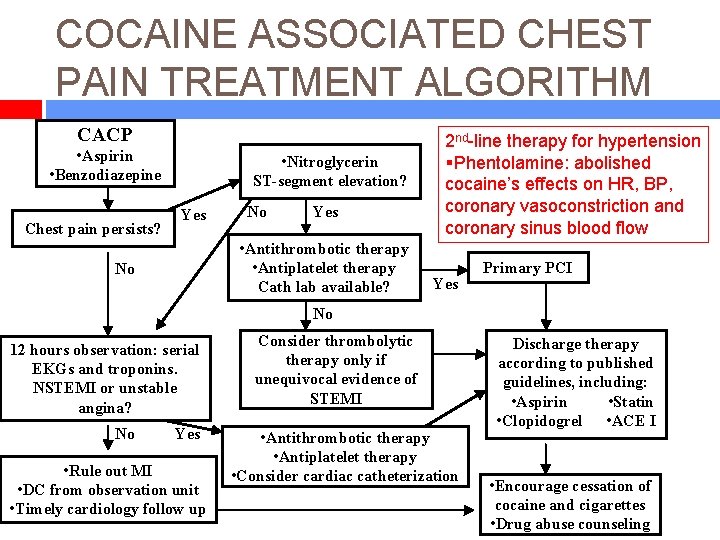
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No 2 nd-line therapy for hypertension §Phentolamine: abolished cocaine’s effects on HR, BP, coronary vasoconstriction and coronary sinus blood flow Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
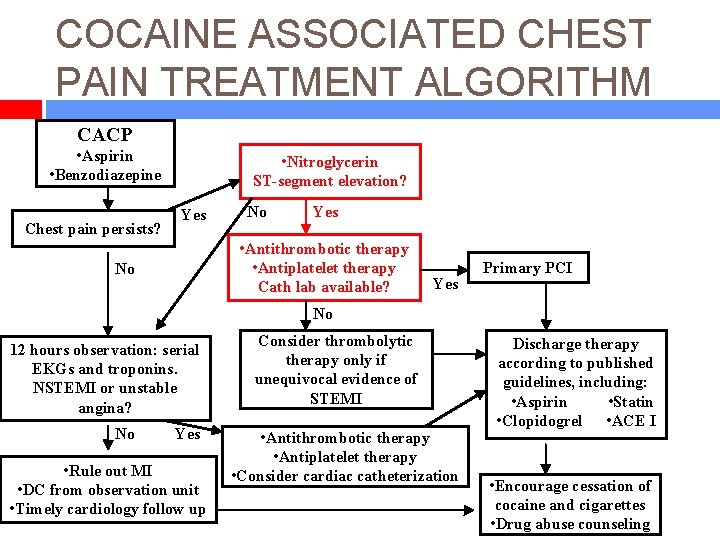
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
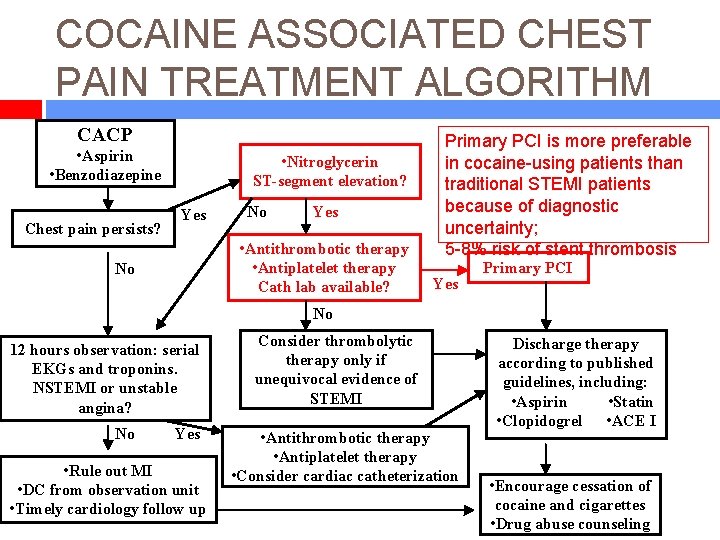
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No Primary PCI is more preferable in cocaine-using patients than traditional STEMI patients because of diagnostic uncertainty; 5 -8% risk of stent thrombosis Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
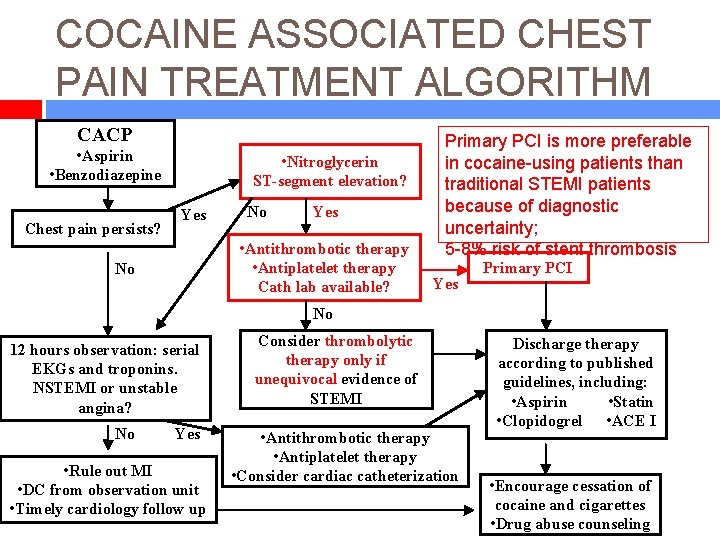
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No Primary PCI is more preferable in cocaine-using patients than traditional STEMI patients because of diagnostic uncertainty; 5 -8% risk of stent thrombosis Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
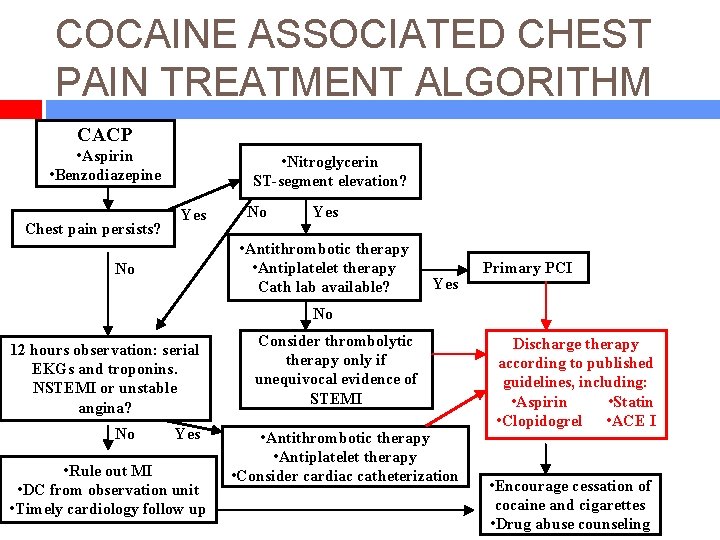
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling
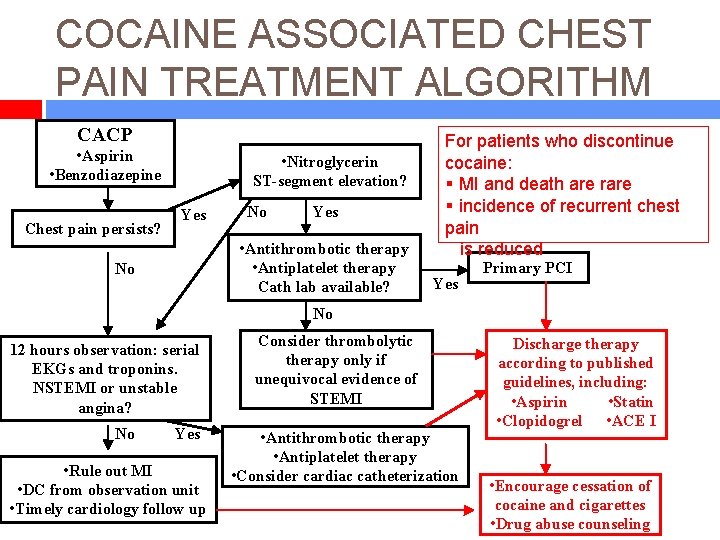
COCAINE ASSOCIATED CHEST PAIN TREATMENT ALGORITHM CACP • Aspirin • Benzodiazepine Chest pain persists? • Nitroglycerin ST-segment elevation? Yes No Yes • Antithrombotic therapy • Antiplatelet therapy Cath lab available? No For patients who discontinue cocaine: § MI and death are rare § incidence of recurrent chest pain is reduced Yes Primary PCI No 12 hours observation: serial EKGs and troponins. NSTEMI or unstable angina? No Yes • Rule out MI • DC from observation unit • Timely cardiology follow up Consider thrombolytic therapy only if unequivocal evidence of STEMI • Antithrombotic therapy • Antiplatelet therapy • Consider cardiac catheterization Discharge therapy according to published guidelines, including: • Aspirin • Statin • Clopidogrel • ACE I • Encourage cessation of cocaine and cigarettes • Drug abuse counseling

COCAINE ASSOCIATED CHEST PAIN CONCLUSION Predominantly young male cigarette smokers Of patients in ER with CACP: ~6% have MI Evaluate non-high-risk patients with 12 hr observation Cocaine-induced MI: complications are very low, including death, CHF, arrhythmias Avoid all beta-blockers in the acute setting Treat CACP with benzodiazepines, NTG, standard Tx PCI even more preferable than in traditional
- Slides: 25