
TATALAKSANA HIPERTENSI OPTIMAL UNTUK MENCEGAH STROKE Dr Sapto












- Slides: 33
TATALAKSANA HIPERTENSI OPTIMAL UNTUK MENCEGAH STROKE Dr. Sapto Priatmo, Sp. PD RS BETHESDA YOGYAKARTA 4 November 2017
HIPERTENSI Suatu keadaan klinis dimana tekanan darah seseorang lebih tinggi daripada tekanan darah normal (>140/90 mm. Hg) • Epidemiologi : • Jumlah penderita hipertensi di seluruh dunia : 1 milyar • USA : 65 juta • Indonesia: 27, 6% (SKRT, 2004) Conlin PR, Int J Clin Pract 2005; 59(2): 214 -24
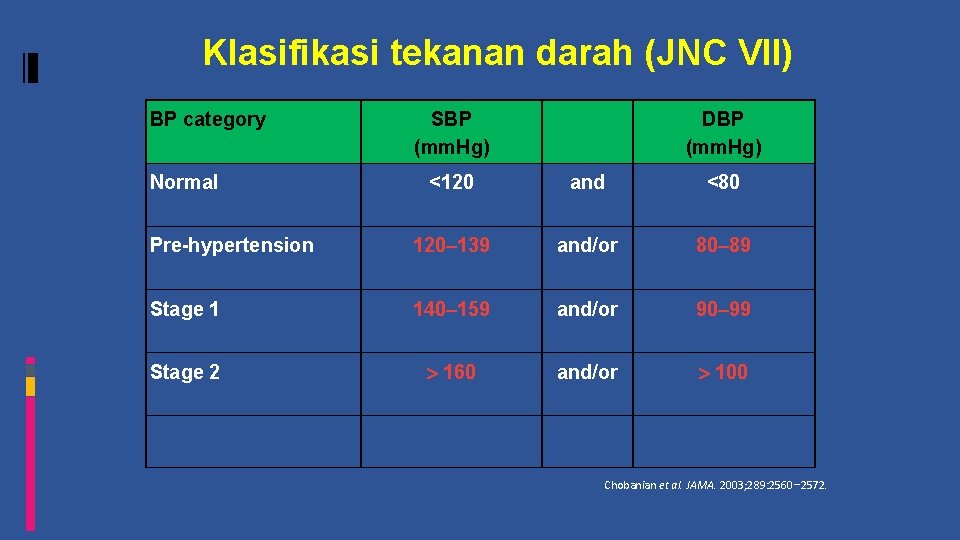
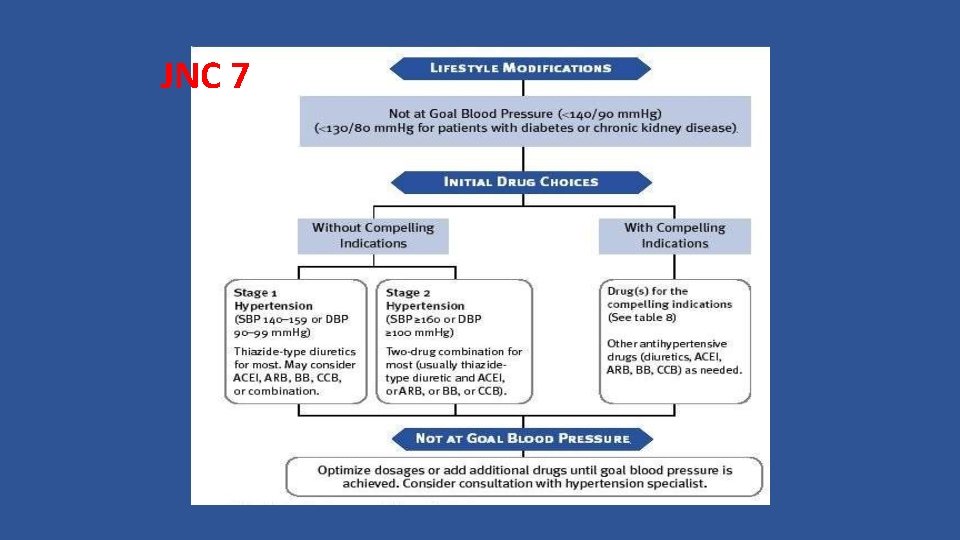
Klasifikasi tekanan darah (JNC VII) BP category Normal SBP (mm. Hg) DBP (mm. Hg) <120 and <80 Pre-hypertension 120– 139 and/or 80– 89 Stage 1 140– 159 and/or 90– 99 Stage 2 > 160 and/or > 100 Chobanian et al. JAMA. 2003; 289: 2560− 2572.
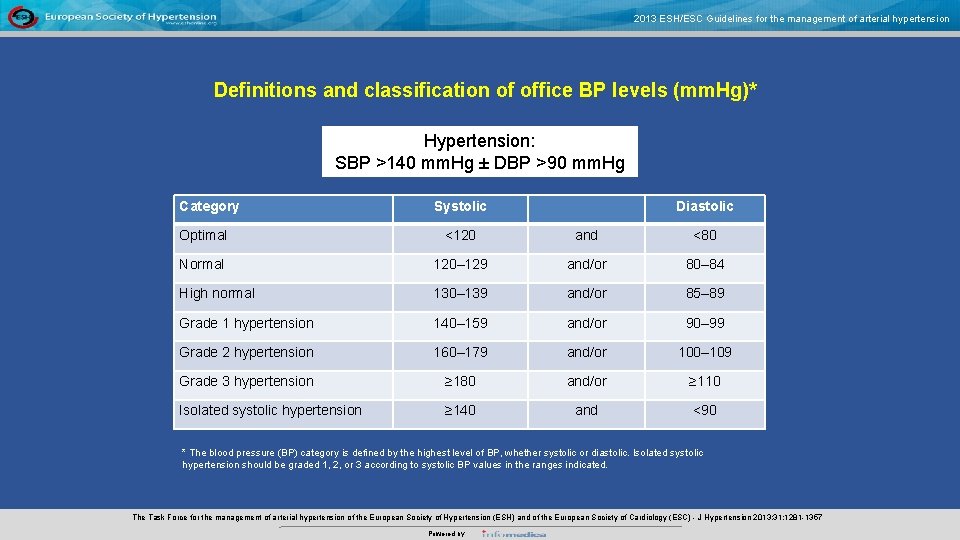
2013 ESH/ESC Guidelines for the management of arterial hypertension Definitions and classification of office BP levels (mm. Hg)* Hypertension: SBP >140 mm. Hg ± DBP >90 mm. Hg Category Systolic Diastolic Optimal <120 and <80 Normal 120– 129 and/or 80– 84 High normal 130– 139 and/or 85– 89 Grade 1 hypertension 140– 159 and/or 90– 99 Grade 2 hypertension 160– 179 and/or 100– 109 Grade 3 hypertension ≥ 180 and/or ≥ 110 Isolated systolic hypertension ≥ 140 and <90 * The blood pressure (BP) category is defined by the highest level of BP, whether systolic or diastolic. Isolated systolic hypertension should be graded 1, 2, or 3 according to systolic BP values in the ranges indicated. The Task Force for the management of arterial hypertension of the European Society of Hypertension (ESH) and of the European Society of Cardiology (ESC) - J Hypertension 2013; 31: 1281 -1357 Medical Education & Information – for all Media, all Disciplines, from all over the World Powered by
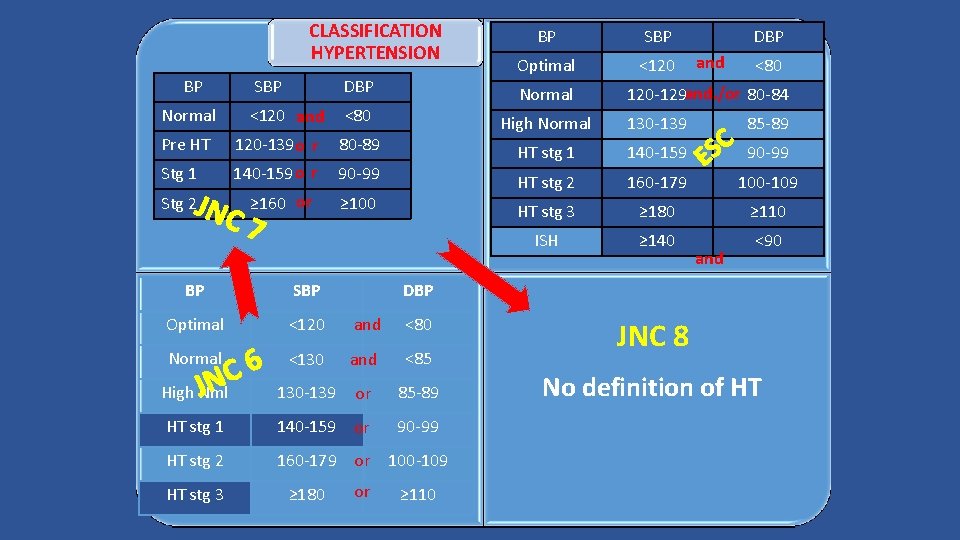
CLASSIFICATION HYPERTENSION BP Normal SBP DBP <120 and <80 Pre HT 120 -139 o r 80 -89 Stg 1 140 -159 o r 90 -99 Stg 2 ≥ 160 or ≥ 100 SBP Optimal <120 and <80 Normal <130 and <85 High Nml 130 -139 or 85 -89 HT stg 1 140 -159 or 90 -99 HT stg 2 160 -179 or ≥ 180 SBP Optimal <120 Normal BP HT stg 3 BP DBP and <80 120 -129 and. /or 80 -84 High Normal 130 -139 85 -89 HT stg 1 140 -159 90 -99 HT stg 2 160 -179 100 -109 HT stg 3 ≥ 180 ≥ 110 ISH ≥ 140 <90 and DBP or 100 -109 ≥ 110 JNC 8 No definition of HT
Prevalence of hypertension (%) Prevalensi hipertensi dunia US Italy Sweden England Spain Finland Japan* Germany Adults aged 35– 64 years (data are age- and sex-adjusted), except* (adults aged ≥ 30 years) Hypertension defined as BP ≥ 140/90 mm. Hg or on treatment Wolf-Maier et al. JAMA. 2003; 289: 2363− 2369; Sekikawa, Hayakawa. J Hum Hypertens. 2004; 18: 911– 912.
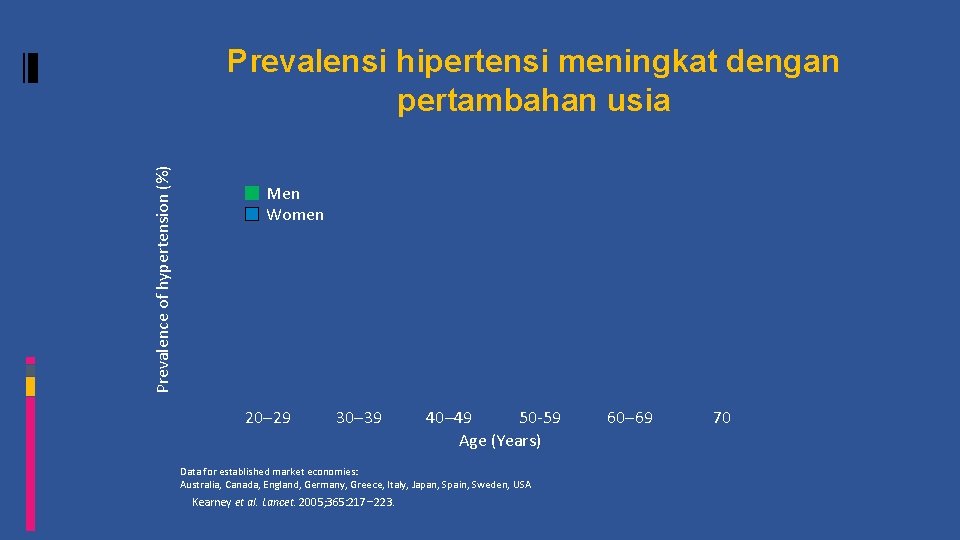
Prevalence of hypertension (%) Prevalensi hipertensi meningkat dengan pertambahan usia Men Women 20 -29 30 -39 40 -49 50 -59 Age (Years) Data for established market economies: Australia, Canada, England, Germany, Greece, Italy, Japan, Spain, Sweden, USA Kearney et al. Lancet. 2005; 365: 217− 223. 60 -69 70
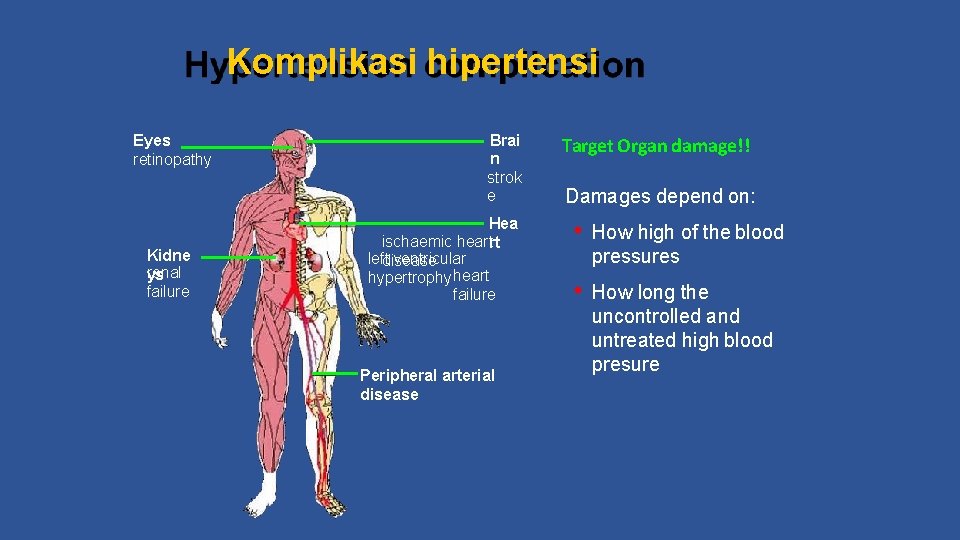
Komplikasi hipertensi Eyes retinopathy Kidne renal ys failure Brai n strok e Hea ischaemic heartrt leftdisease ventricular hypertrophy heart failure Peripheral arterial disease Target Organ damage!! Damages depend on: • How high of the blood pressures • How long the uncontrolled and untreated high blood presure
© Continuing Medical Implementation …. . . bridging the care gap
Fold increase in relative CV risk Risiko mortalitas meningkat 2 x dengan peningkatan tekanan darah 20/10 mm. Hg SBP/DBP (mm. Hg) 8 X 8 -fold 4 X 2 X 115/75 135/85 155/95 • Meta-analysis of 61 prospective, observational studies • 1 million adults aged 40– 69 years with BP > 115/75 mm. Hg • 12. 7 million person–years Lewington et al. Lancet. 2002; 360: 1903– 1913. 175/105
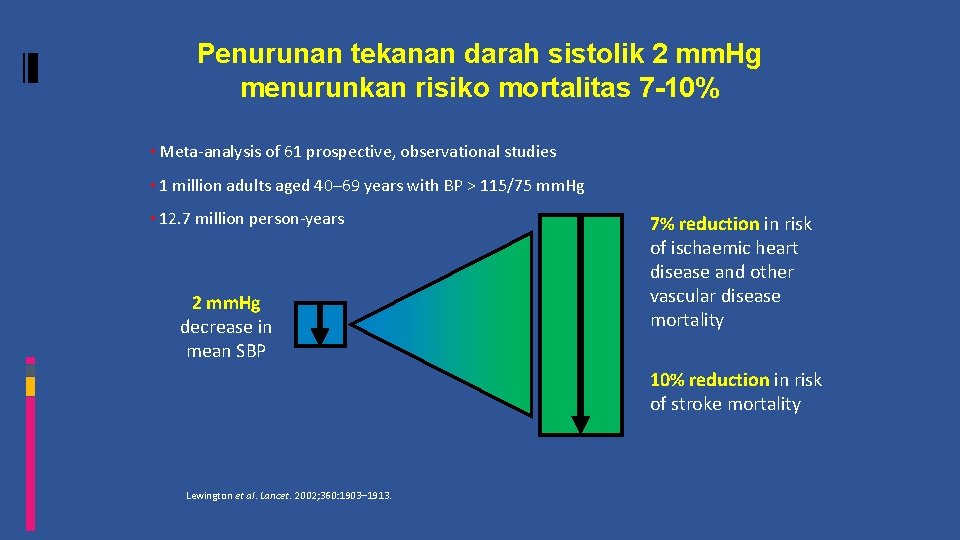
Penurunan tekanan darah sistolik 2 mm. Hg menurunkan risiko mortalitas 7 -10% • Meta-analysis of 61 prospective, observational studies • 1 million adults aged 40– 69 years with BP > 115/75 mm. Hg • 12. 7 million person-years 2 mm. Hg decrease in mean SBP 7% reduction in risk of ischaemic heart disease and other vascular disease mortality 10% reduction in risk of stroke mortality Lewington et al. Lancet. 2002; 360: 1903– 1913.
FAKTA HIPERTENSI PADA STROKE
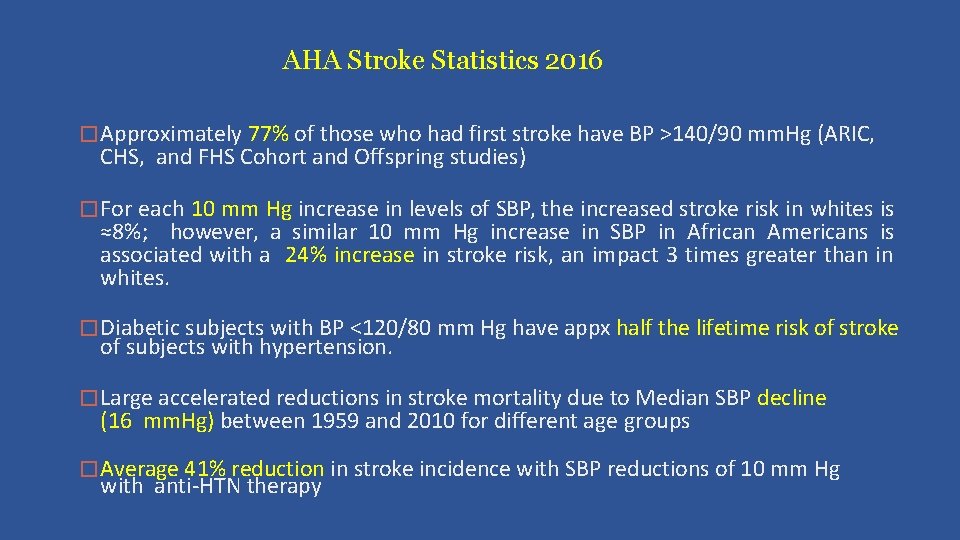
AHA Stroke Statistics 2016 � Approximately 77% of those who had first stroke have BP >140/90 mm. Hg (ARIC, CHS, and FHS Cohort and Offspring studies) � For each 10 mm Hg increase in levels of SBP, the increased stroke risk in whites is ≈8%; however, a similar 10 mm Hg increase in SBP in African Americans is associated with a 24% increase in stroke risk, an impact 3 times greater than in whites. � Diabetic subjects with BP <120/80 mm Hg have appx half the lifetime risk of stroke of subjects with hypertension. � Large accelerated reductions in stroke mortality due to Median SBP decline (16 mm. Hg) between 1959 and 2010 for different age groups � Average 41% reduction in stroke incidence with SBP reductions of 10 mm Hg with anti-HTN therapy
AHA Stroke Statistics 2016 �Several studies have shown significantly lower rates of recurrent stroke with lower BPs. Most recently, the BP- reduction component of the SPS 3 trial showed that targeting an SBP <130 mm. Hg was likely to reduce recurrent stroke by ≈20% (P=0. 08) and significantly reduced ICH by two thirds.
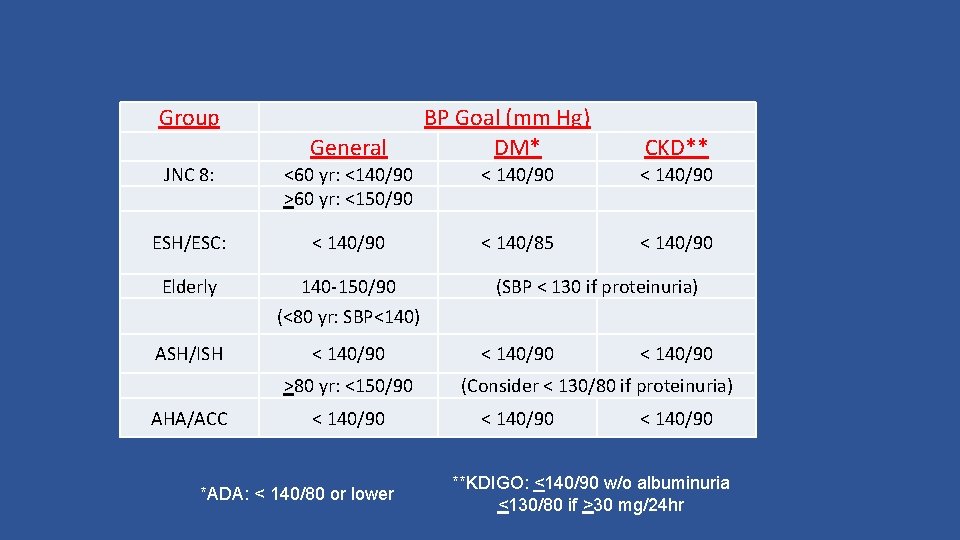
What is the goal BP?
Group General JNC 8: <60 yr: <140/90 >60 yr: <150/90 ESH/ESC: < 140/90 Elderly 140 -150/90 (<80 yr: SBP<140) ASH/ISH < 140/90 >80 yr: <150/90 AHA/ACC < 140/90 *ADA: < 140/80 or lower BP Goal (mm Hg) DM* CKD** < 140/90 < 140/85 < 140/90 Goal BP (SBP < 130 if proteinuria) < 140/90 (Consider < 130/80 if proteinuria) < 140/90 **KDIGO: <140/90 w/o albuminuria <130/80 if >30 mg/24 hr
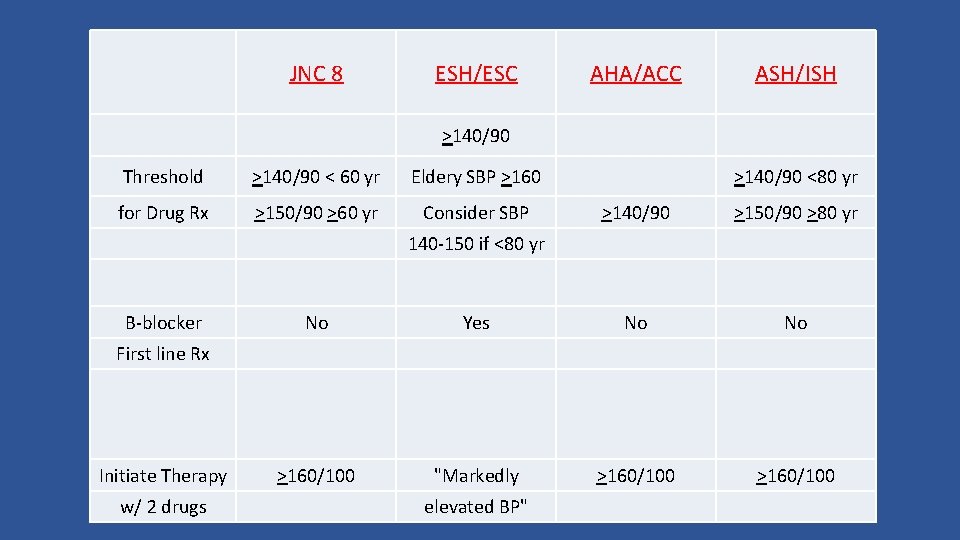
JNC 8 ESH/ESC AHA/ACC ASH/ISH >140/90 Threshold >140/90 < 60 yr for Drug Rx >150/90 >60 yr Eldery SBP >160 Comparison of Recent Consider SBP >140/90 Guideline Statements >140/90 <80 yr >150/90 >80 yr 140 -150 if <80 yr B-blocker No Yes No No >160/100 "Markedly >160/100 First line Rx Initiate Therapy w/ 2 drugs elevated BP"
TATALAKSANA HIPERTENSI
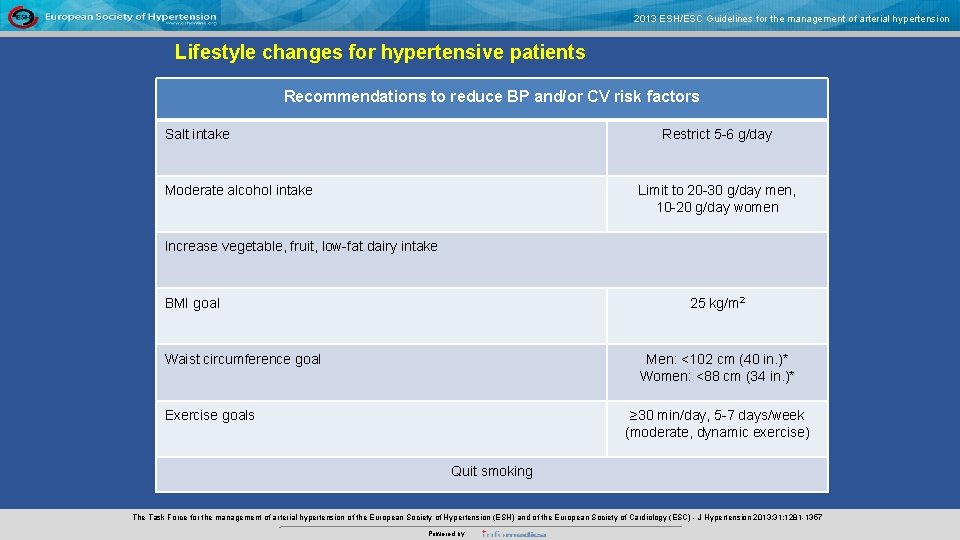
2013 ESH/ESC Guidelines for the management of arterial hypertension Lifestyle changes for hypertensive patients Recommendations to reduce BP and/or CV risk factors Salt intake Restrict 5 -6 g/day Moderate alcohol intake Limit to 20 -30 g/day men, 10 -20 g/day women Increase vegetable, fruit, low-fat dairy intake BMI goal 25 kg/m 2 Waist circumference goal Men: <102 cm (40 in. )* Women: <88 cm (34 in. )* Exercise goals ≥ 30 min/day, 5 -7 days/week (moderate, dynamic exercise) * Unless contraindicated. BMI, body mass index. Quit smoking The Task Force for the management of arterial hypertension of the European Society of Hypertension (ESH) and of the European Society of Cardiology (ESC) - J Hypertension 2013; 31: 1281 -1357 Medical Education & Information – for all Media, all Disciplines, from all over the World Powered by
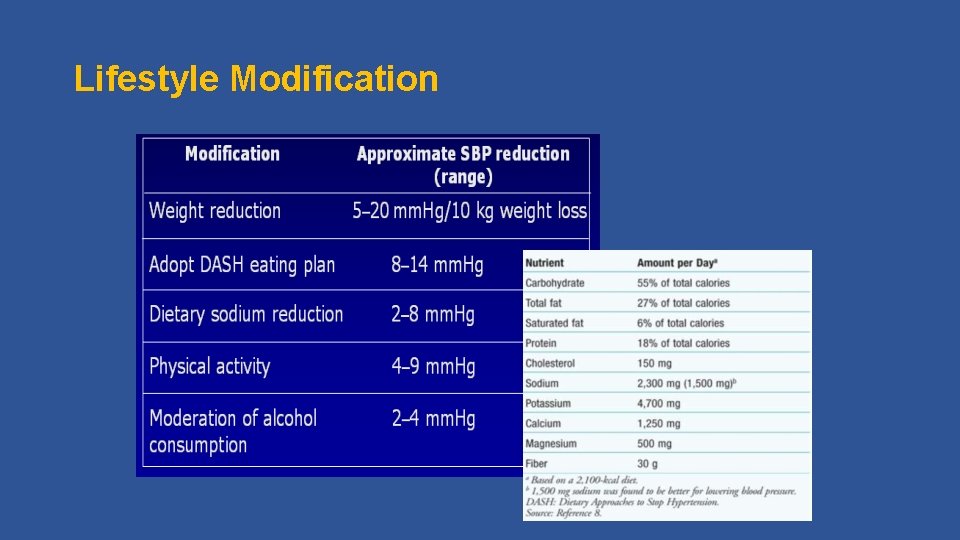
Lifestyle Modification
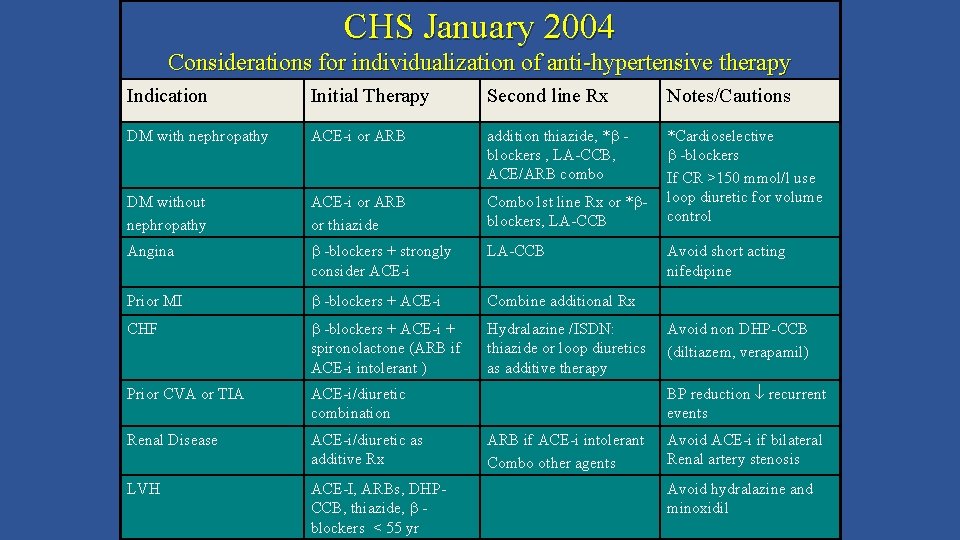
CHS January 2004 Considerations for individualization of anti-hypertensive therapy Indication Initial Therapy Second line Rx Notes/Cautions DM with nephropathy ACE-i or ARB addition thiazide, * blockers , LA-CCB, ACE/ARB combo DM without nephropathy ACE-i or ARB or thiazide Combo 1 st line Rx or * blockers, LA-CCB *Cardioselective -blockers If CR >150 mmol/l use loop diuretic for volume control Angina -blockers + strongly consider ACE-i LA-CCB Prior MI -blockers + ACE-i Combine additional Rx CHF -blockers + ACE-i + spironolactone (ARB if ACE-i intolerant ) Hydralazine /ISDN: thiazide or loop diuretics as additive therapy Prior CVA or TIA ACE-i/diuretic combination Renal Disease ACE-i/diuretic as additive Rx LVH ACE-I, ARBs, DHPCCB, thiazide, blockers < 55 yr Avoid short acting nifedipine Avoid non DHP-CCB (diltiazem, verapamil) BP reduction recurrent events ARB if ACE-i intolerant Combo other agents Avoid ACE-i if bilateral Renal artery stenosis Avoid hydralazine and minoxidil
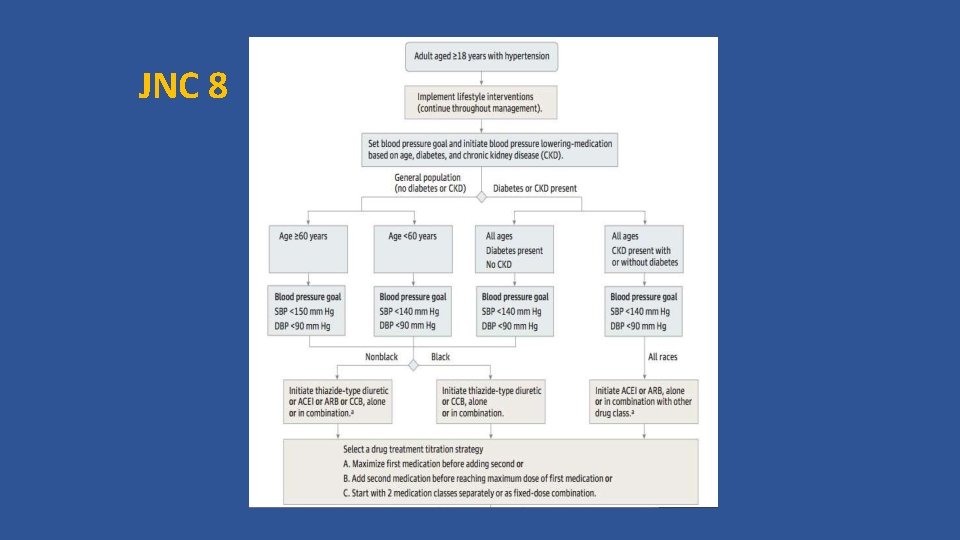
JNC 8
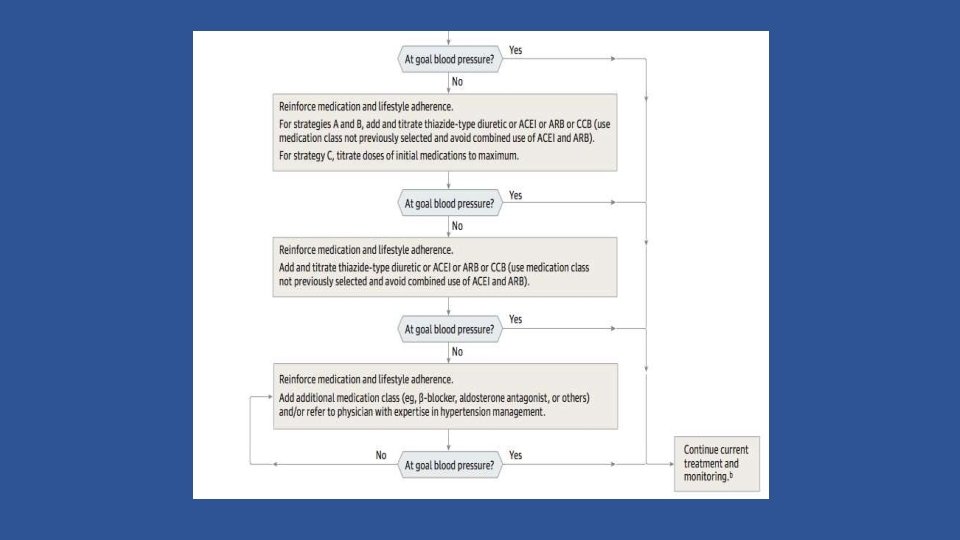
Strategies to Dose Antihypertensive Drugs Strategies Description Details A Mulai 1 obat naikan sp dosis maksimum, kemudian tambahkan obat ke-2 Jika target BP blm tercapai naikkan dosis obat 1 sp dosis maksimum sblm menambahkan obat ke-2 dan ke-3. B Mulai 1 obat kemudian tambahkan obat ke-2 sblm dosis maksimum Tambahkan obat ke-2 sblm obat 1 mencapai dosis maks. Jk Target BP blm tercapai, tambahkan obat ke-3 dan titrasi sp dosis maks. C Mulai dengan 2 obat (separate or single combination) • Mulai dg 2 obat • Bbrp committee merekomendasi: ≥ 2 obat SBP >160 dan/atau DBP >100, atau SBP >20 mm. Hg diatas target dan/atau DBP >10 mm. Hg Jika target BP tdk tercapai (2 drugs), tambahkan obat ke-3 dan titrasi.
JNC 7
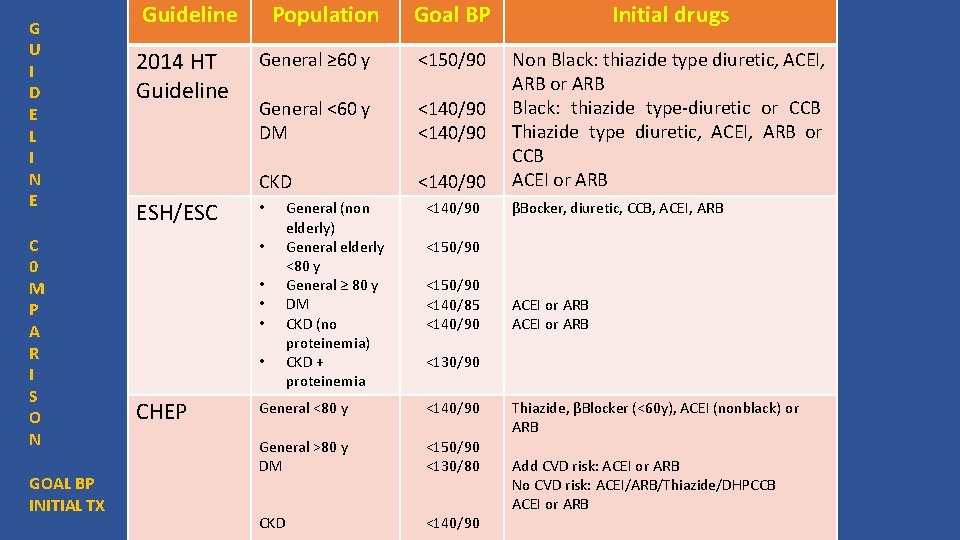
G U I D E L I N E C 0 M P A R I S O N GOAL BP INITIAL TX Guideline 2014 HT Guideline ESH/ESC Population Goal BP Initial drugs General ≥ 60 y <150/90 General <60 y DM <140/90 CKD <140/90 Non Black: thiazide type diuretic, ACEI, ARB or ARB Black: thiazide type-diuretic or CCB Thiazide type diuretic, ACEI, ARB or CCB ACEI or ARB • • • CHEP General (non elderly) General elderly <80 y General ≥ 80 y DM CKD (no proteinemia) CKD + proteinemia <140/90 βBocker, diuretic, CCB, ACEI, ARB <150/90 <140/85 <140/90 ACEI or ARB <130/90 General <80 y <140/90 General >80 y DM <150/90 <130/80 CKD <140/90 Thiazide, βBlocker (<60 y), ACEI (nonblack) or ARB Add CVD risk: ACEI or ARB No CVD risk: ACEI/ARB/Thiazide/DHPCCB ACEI or ARB
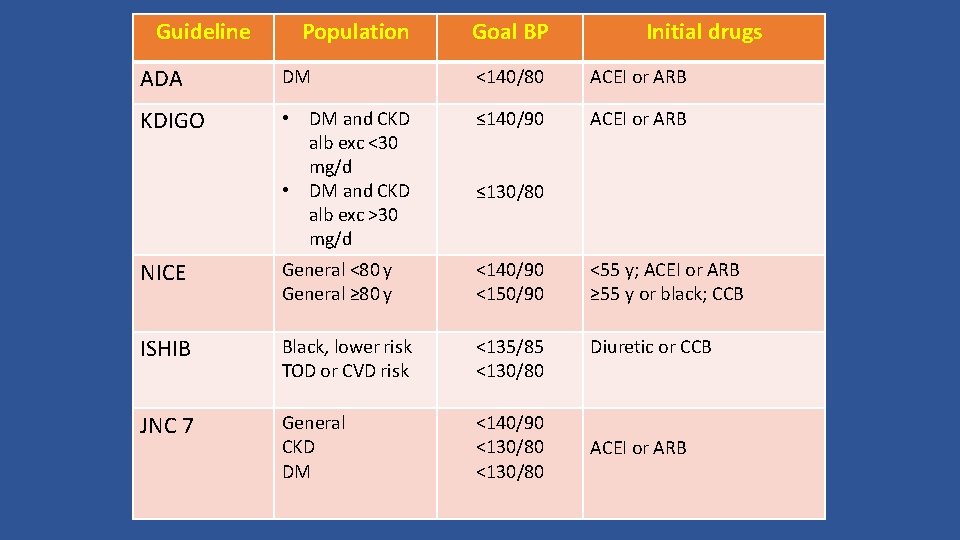
Guideline Population Goal BP Initial drugs ADA DM <140/80 ACEI or ARB KDIGO • DM and CKD alb exc <30 mg/d • DM and CKD alb exc >30 mg/d ≤ 140/90 ACEI or ARB NICE General <80 y General ≥ 80 y <140/90 <150/90 <55 y; ACEI or ARB ≥ 55 y or black; CCB ISHIB Black, lower risk TOD or CVD risk <135/85 <130/80 Diuretic or CCB JNC 7 General CKD DM <140/90 <130/80 ≤ 130/80 ACEI or ARB
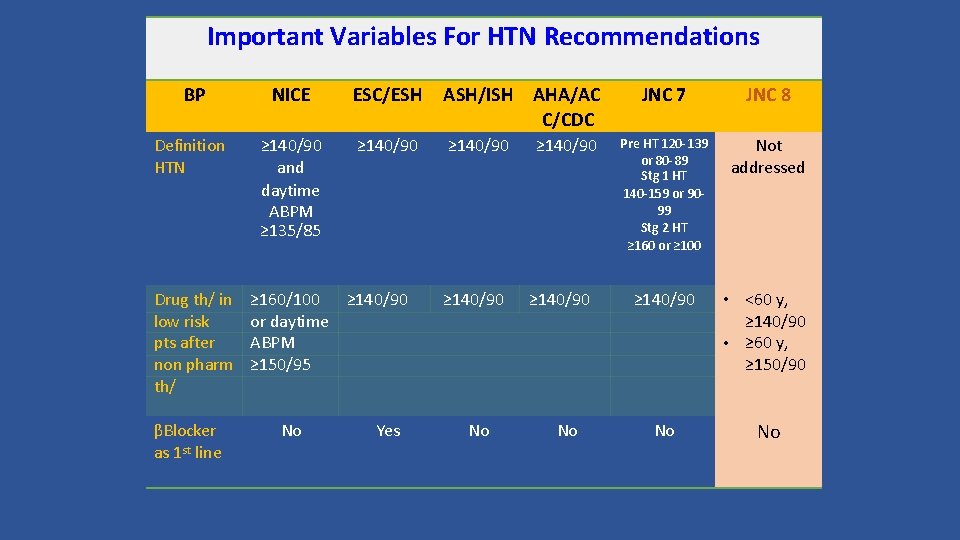
Important Variables For HTN Recommendations BP NICE ESC/ESH ASH/ISH AHA/AC C/CDC Definition HTN ≥ 140/90 and daytime ABPM ≥ 135/85 ≥ 140/90 Drug th/ in low risk pts after non pharm th/ βBlocker as 1 st line ≥ 160/100 ≥ 140/90 or daytime ABPM ≥ 150/95 No Yes ≥ 140/90 No JNC 7 JNC 8 Pre HT 120 -139 or 80 -89 Stg 1 HT 140 -159 or 9099 Stg 2 HT ≥ 160 or ≥ 100 Not addressed ≥ 140/90 • <60 y, ≥ 140/90 • ≥ 60 y, ≥ 150/90 No No
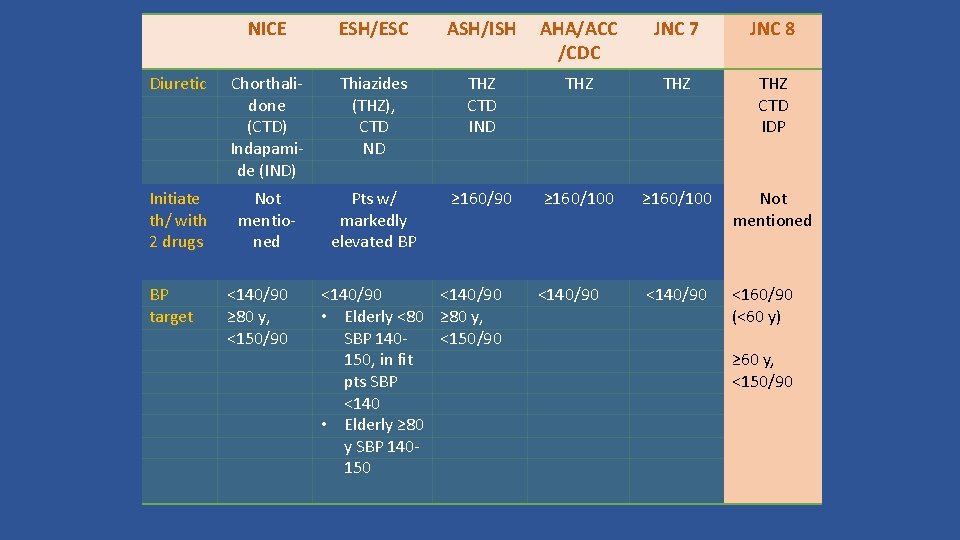
NICE ESH/ESC ASH/ISH AHA/ACC /CDC JNC 7 JNC 8 Diuretic Chorthalidone (CTD) Indapamide (IND) Thiazides (THZ), CTD ND THZ CTD IND THZ THZ CTD IDP Initiate th/ with 2 drugs Not mentioned Pts w/ markedly elevated BP ≥ 160/90 ≥ 160/100 Not mentioned <140/90 <160/90 (<60 y) BP target <140/90 ≥ 80 y, <150/90 <140/90 • Elderly <80 ≥ 80 y, SBP 140<150/90 150, in fit pts SBP <140 • Elderly ≥ 80 y SBP 140150 <140/90 ≥ 60 y, <150/90
Under JNC 8, in all cases, targets BP should be reached within a month of starting treatment either by increasing the dose or by using a combination drugs In patients ≥ 60 yrs who do not have DM or CKD, the goal BP level is <150/90 mm Hg In pts 18 - 59 yrs without major comorbidities target BP <140/90, and in patient ≥ 60 yrs without DM, CKD, or both, the new goal BP is <150/90 mm Hg JNC 8 panel recommended thiazide-type diuretics as initial therapy for most patients (include newly diagnosed HTN)
JNC 8 also recommend lifestyle interventions include use of the DASH eating plan, weight loss, reduction in sodium intake to <2. 4 gr/day, and at least 30 minutes of aerobic activity most days of the week Under the JNC 8 guidelines, patients would receive a dosage adjustment and combinations of the 4 first-line & later line therapies ACEI/ARB, CCB, and thiazide-type diuretic The JNC 8 does not recommend β-blockers and α-blockers as 1 st therapy due to 1 trial that showed a higher rate of CV events with use of βB compared with use of an ARB, and another trial in which αB resulted in inferior CV outcomes compared with use of a diuretic
When initiating therapy, patients of African descent without CKD should use CCBs and thiazides instead of ACE inhibitors and ARBs should not be used in the same patient simultaneously