
Spirochetes Dr Jyotsna Agarwal Dept Microbiology KGMU Classification

Spirochetes Dr. Jyotsna Agarwal Dept. Microbiology KGMU

Classification of spirochetes • Spirochetes are thin, elongated, spirally twisted, Gram negative bacteria • There are 11 genera in this group • Some are pathogens, but most are free-living, and are actually pretty common in the environment.

3 genera have human pathogens Treponema, Borrelia, leptospira Treponema (25 species)Relatively short, slender, fine spirals. Associated with venereal and non venereal diseases, some are non pathogenic Treponema pallidum causes syphilis- venereal disease- STD.

Syphilis - T. pallidum • History- ancient disease, Columbus crew • Reservoir- humans only known natural host. • Name syphilis from a poem describing a shepherd boy

• Transmission- sexual route- venereal • Syphilis is not very contagious; a person has 1/10 chance of becoming infected after contact with an infected person • In some stages, it is less contagious

• Syphilis is conventionally divided into following stages: Primary, Secondary, Latent, Tertiary – Staging has prognostic and therapeutic implications.

Primary syphilis • 5 to 80 days after contact (sexual), a chancre develops at point of contactexternal genitalia • Chancre is an inflammatory lesion containing spirochetes & lymphocytes. • It is painless, well circumscribed, indurated, heals spontaneously after ~10 – 40 days leaving a thin scar. (also called hard chancre)

• Regional lymph nodes are enlarged and non tender • Even before appearance of chancre, treponema spread from site of entry via blood/lymph. • Multiple chancre may be seen in immunodefficient patients. • Once this heals patient remains asymptomatic till secondary stage

Secondary syphilis • 2 - 12 weeks after primary lesion heals, generalized symptoms of disseminated infection occur due to multiplication and dissemination of treponemes • Fever, headache, sore throat and enlarged lymph nodes develop • Papular skin rash develops on body and lesions appear on palms and soles of feet also

• Abundant spirochetes in skin lesionsmost infectious stage • Intensity of lesions in secondary syphilis varies • Can Heal spontaneously in months to years • Variable course spontaneous cure latent stage go to 3 rd stage

Latent Syphilis • Absence of clinical symptoms • 3 possible outcomes Persist for life Tertiary syphilis Cure

Tertiary syphilis • 2 -20 years later • Steady tissue destruction- Chronic granulomata formation- Gumma, lesions contain very few treponema • Cardiovascular system/CNS • ~1/3 die

Late tertiary or quaternary syphilis- • Tabes dorsalis- dorsal column of spinal cord • GPI- dementia

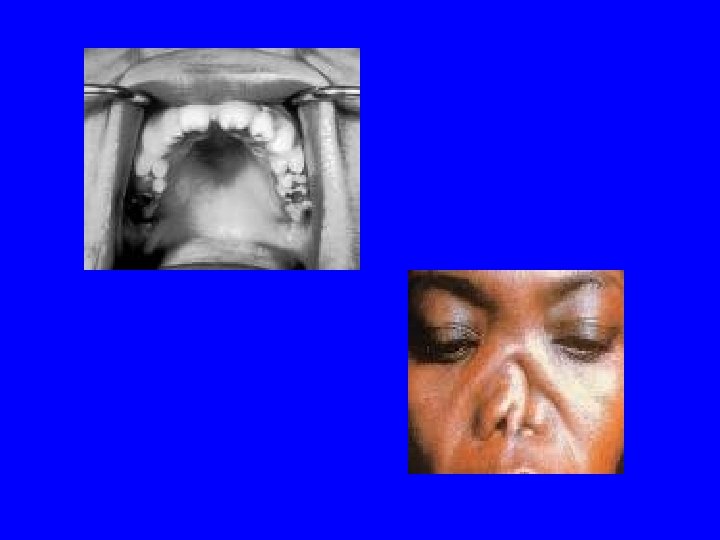
Congenital Syphilis • Fetus susceptible after 4 th month IU life • 40% fetal death • Hutchinson's Triad peg teeth interstitial keratitis 8 th nerve destruction- deafness

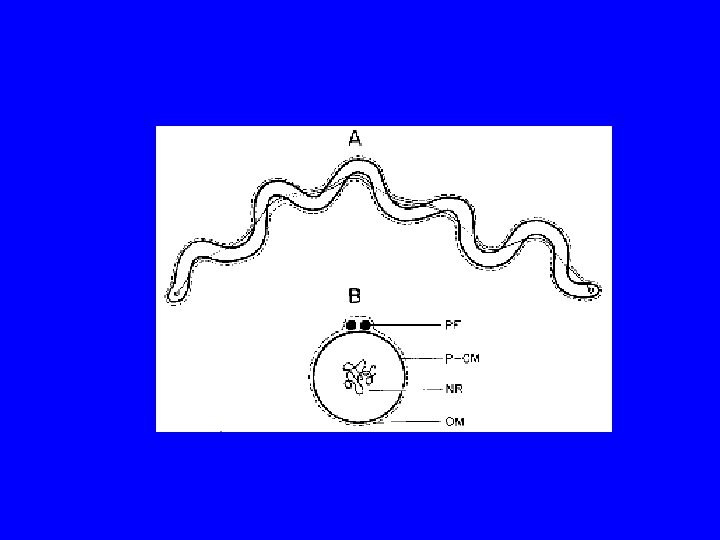
Treponema pallidum bacteria • It is slender and tightly coiled, measuring 5 to 15 µm long by 0. 09 to 0. 18µm wide • They have a characteristic motility on dark field microscopy- cork screw • This is due to axial fibrils, similar to flagella, varying numbers

• T. pallidum has not been cultured in vivo. • It is rapidly inactivated by: Drying, Heat, Cold • Transmission is by direct contact or congenitally
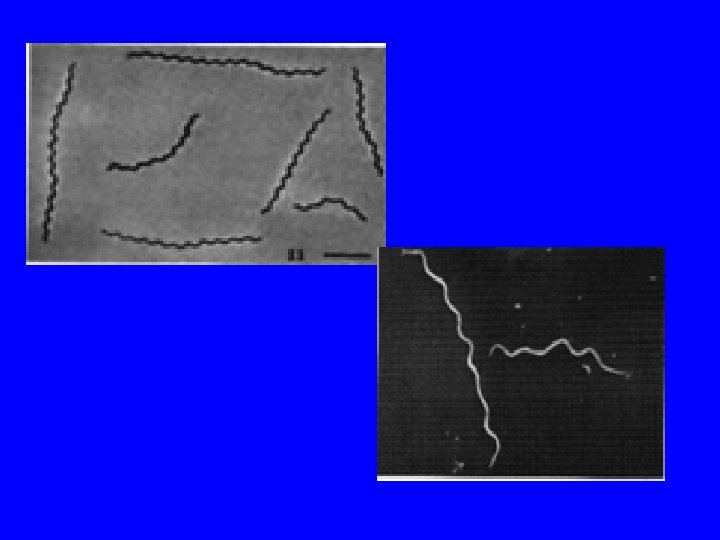

Diagnosis Clinical- based on symptoms, history Laboratory • Darkfield examination Wear gloves, Clean the lesion with saline gauze, press it gently and collect exudate on a slide and examine in darkground microscope.

Serologic tests Non Specific/Non treponemal • A reactive material from beef heart called cardiolipin is used as antigen • It reacts with “reagin” antibodies that develop in syphilis • Also called Standard test for Syphilis (STS)
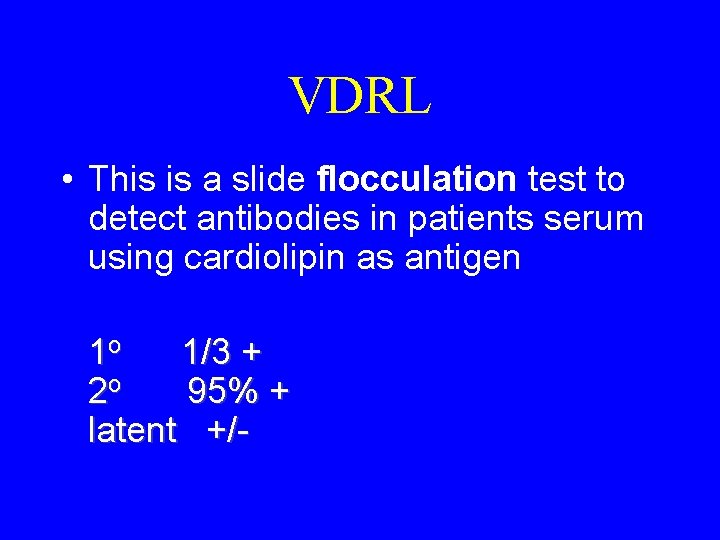
VDRL • This is a slide flocculation test to detect antibodies in patients serum using cardiolipin as antigen 1 o 1/3 + 2 o 95% + latent +/-

Other Non treponemal tests • Kahn’s- Tube flocculation test • Wasserman test- Complement fixation • RPR- rapid plasma reagin test Biological false positives- BFP • Acute infections, major trauma, autoimmune conditions like SLE, • Leprosy, malaria
Specific - treponemal tests Using T. pallidum antigen to detect antibodies in patients serum • Treponema pallidum immobilization- TPI • Fluorescent treponemal Antibody (FTA) • T pallidum haemagglutination (TPHA) 1 o 80% + 2 o & 3 o >95% + latent >99% +

Treatment • Penicillin is drug of choice • Duration of tretment varies according to clinical stage of disease • If allergic to penicillin- Ceftriaxone

Summary • • • Treponema pallidum bacteria: characters Syphilis disease: mode of transmissison Clinical stages Diagnostic tests: STS / Specific tests Utility of tests / BFP
- Slides: 26