
Somatoform and Dissociative Disorders Chapter 5 Basic definitions

Somatoform and Dissociative Disorders Chapter 5
Basic definitions • Somatoform disorders – pathological concern of individuals with the appearance or functioning of their bodies when there is no identifiable medical condition causing the physical complaints • Dissociative disorders – individuals feel detached from themselves or their surroundings, and reality, experience, and identity may disintegrate • Historically, both somatoform and dissociative disorders used to be categorized as hysterical neurosis – in psychoanalytic theory neurotic disorders result from underlying unconscious conflicts, anxiety that resulted from those conflicts and ego defense mechanisms

Somatoform Disorders • Soma – Meaning Body – Preoccupation with health and/or body appearance and functioning – No identifiable medical condition causing the physical complaints • Types of DSM-IV Somatoform Disorders – Hypochondriasis – Somatization disorder – Conversion disorder – Pain disorder – Body dysmorphic disorder
Somatoform Disorders • Hypochondriasis – severe anxiety focused on the possibility of having a serious disease – shares age of onset, personality characteristics anf running in families with panic disorder – illness phobia vs. hypochondriasis – 60% of patients with illness phobia develop hypochondriasis – 1% to 14% of medical patients – treatment usually invoves cognitive-behavioral therapy and general stress management treatment (gain retained after 1 year follow-up)
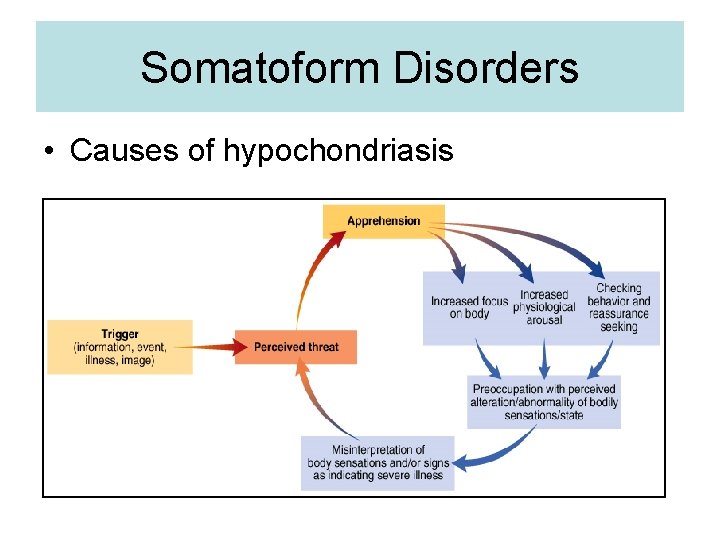
Somatoform Disorders • Causes of hypochondriasis

Somatoform Disorders • Somatization disorder – Briquet’s syndrome (100 years ago) – patients have a history of many physical complaints that can not be explained by a medical condition, the complaints are not intentionally produced – 20% of patients in primary care setting – develops during adolescence (majority women) – may be connected to Antisocial personality disorder – difficult to treat (reassurance, stress reduction, more adoptive methods of interacting with family are encouraged)

Somatoform Disorders • Conversion Disorder – Physical malfunctioning without any physical or organic pathology – Malfunctioning often involves sensory-motor areas – Persons show la belle indifference – Retain most normal functions, but without awareness of this ability – Statistics • Rare condition, with a chronic intermittent course • Seen primarily in females, with onset usually in adolescence • Not uncommon in some cultural and/or religious groups

Somatoform Disorders • Conversion disorder (cont. ) – Freudian psychodynamic view is still popular (anxiety converted into physical symptoms) – Emphasis on the role of trauma (stress), conversion, and primary/secondary gain – Detachment from the trauma and negative reinforcement seem critical – Different from factitious disorder (intentional) – Treatment • Similar to somatization disorder • Core strategy is attending to the trauma • Remove sources of secondary gain • Reduce supportive consequences of talk about physical symptoms

Somatoform Disorders • Body Dysmorphic Disorder – Preoccupation with imagined defect in appearance – Either fixation or avoidance of mirrors – Previously known as dysmorphophobia – Suicidal ideation and behavior are common – Often display ideas of reference for imagined defect – Statistics • More common than previously thought • Usually runs a lifelong chronic course • Seen equally in males and females, with onset usually in early 20 s • Most remain single, and many seek out plastic surgeons
Somatoform Disorders • Body Dysmorphic Disorder (cont. ) – Causes • Little is known – Disorder tends to run in families • Shares similarities with obsessive-compulsive disorder – Treatment • Treatment parallels that for obsessive compulsive disorder • Medications (i. e. , SSRIs) that work for OCD provide some relief • Exposure and response prevention are also helpful • Plastic surgery is often unhelpful

Dissociative Disorders • Derealization – Loss of sense of the reality of the external world • Depersonalization – Loss of sense of your own reality • 5 types – – – Depesonalization disorder Dissociative amnesia Dissociative fugue Dissociative trance disorder Dissociative identity disorder

Dissociative Disorders • Depersonalization disorder – Severe feelings of depersonalization dominate the individual’s life and prevent normal functioning – It is chronic – 50% suffer from additional mood anxiety disorders – Cognitive profile (cognitive deficits in attention, STM, spatial reasoning, perception (3 D))

Dissociative Disorders • Dissociative Amnesia – Inability to recall personal information, usually of a stressful or traumatic nature – Generalized vs. selective amnesia • Dissociative Fugue – Sudden, unexpected travel away from home, along with an inability to recall one’s past (new identity) – Occur in adulthood and usually end abruptly

Dissociative Disorders • Dissociative trance disorder – Altered state of consciousness in which the person believes firmly that he or she is possessed by spirits; considered a disorder only where there is distress and dysfunction – Trance and possession are a common part of some traditional religious and cultural practices and are not considered abnormal in that context – Only undesirable trance considered pathological within that culture is characterized as disorder

Dissociative Disorders • Dissociative Identity Disorder – Formerly multiple personality disorder – Many personalities (alters) or fragments of personalities coexist within one body – The personalities or fragments are dissociated – Switch (transition form one personality to another, includes physical changes) – Can be simulated by malingers are usually eager to demonstrate their symptoms whereas individuals with DID attempt to hide symptoms – Very high comorbidity – Prevalence about 3%

Dissociative Disorders • Dissociative Identity Disorder – Auditory hallucinations (coming from inside their heads) – 97% severe child abuse – Extreme subtype of PTSD – Onset – approximately 9 years – Suggestible people may use dissociation as defense against severe trauma – Real and false memories – Temporal lobe pathology (out of body experiences)

Dissociative Disorders • Treatment – Dissociative amnesia and fugue • Get better on their own • Coping mechanisms to prevent future episodes – DID • • Reintegration of identities Neutralization of cues Confrontation of early trauma hypnosis
- Slides: 17