
Rheumatolgic Emergencies Conflicts None Errors Mine Thanks to
















- Slides: 42
Rheumatolgic Emergencies
Conflicts None Errors - Mine. Thanks to: Dr. Walker Dr. Hadley Dr. Del Castilho
Table of Contents What is that!? What unites them all? Questions/Discussion
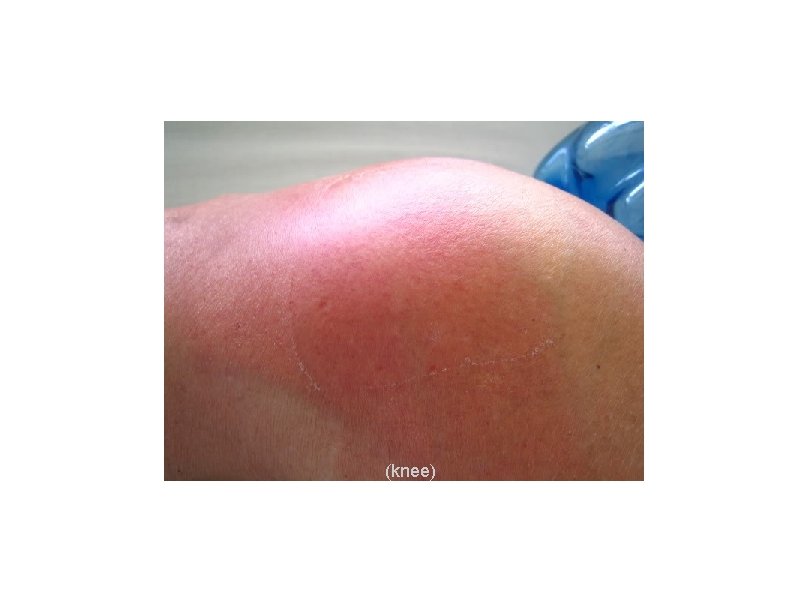
(knee)
Acute Monoarthritis Non-Inflammatory Trauma Hb. S Osteonecrosis Inflammatory Crystals Bacteria Rheumatiod Arthritis Spondyloarthropathy SLE Sarcoidosis Bursitis
Acute Monoarthritis Septic joint in RA – overlooked Delay of Dx 1 -3 weeks Significant joint damage Mortality 20 - 33%
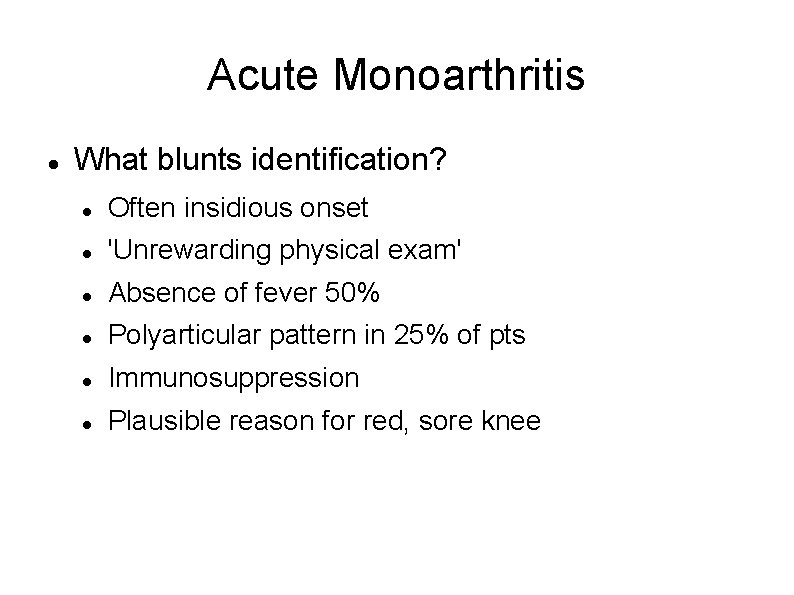
Acute Monoarthritis What blunts identification? Often insidious onset 'Unrewarding physical exam' Absence of fever 50% Polyarticular pattern in 25% of pts Immunosuppression Plausible reason for red, sore knee
Red and Hot 'The most important laboratory test in evaluating monarticular joint pain is synovial fluid analysis. ' UTDOL.
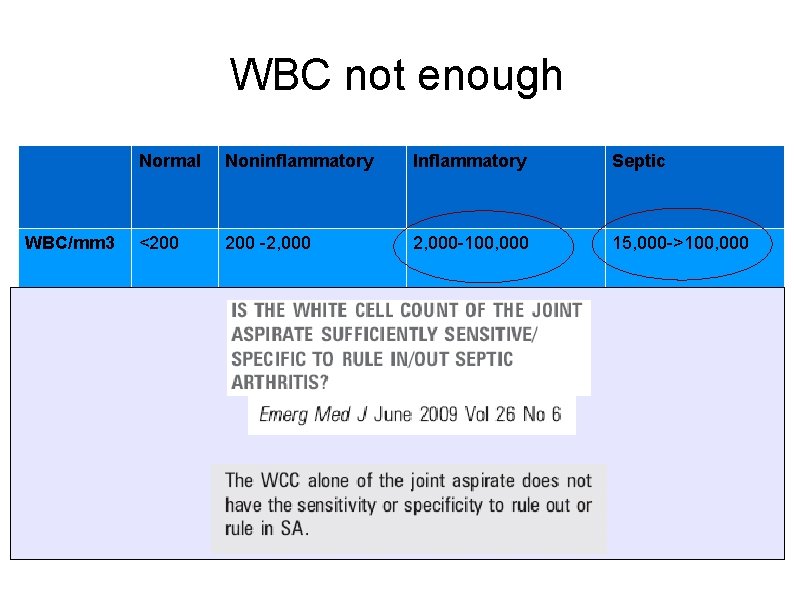
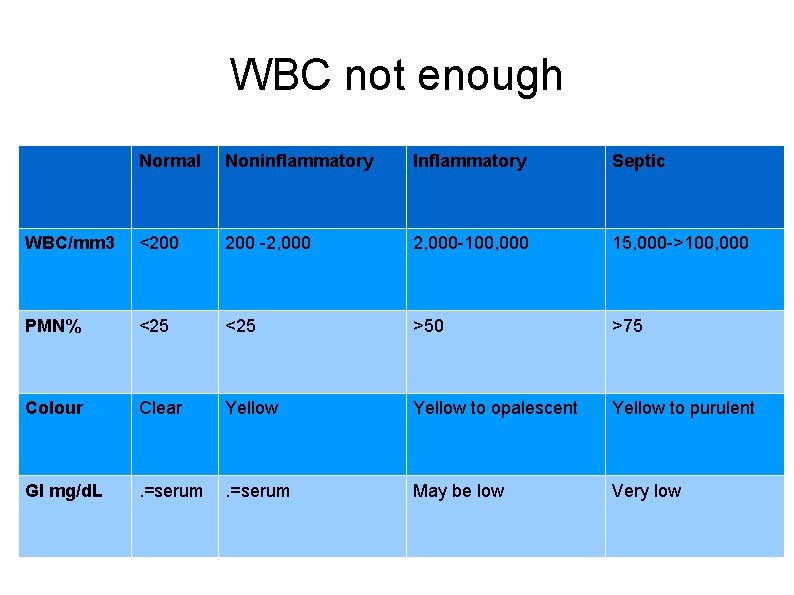
WBC not enough Normal Noninflammatory Inflammatory Septic WBC/mm 3 <200 -2, 000 -100, 000 15, 000 ->100, 000 PMN% <25 >50 >75 Colour Clear Yellow to opalescent Yellow to purulent Gl mg/d. L . =serum May be low Very low
What to order Look at it Xantho, clear, cloudy, purulent Total leukocyte count and diff Gram stain and culture Crystals (polarizing micro) Glucose
WBC not enough Normal Noninflammatory Inflammatory Septic WBC/mm 3 <200 -2, 000 -100, 000 15, 000 ->100, 000 PMN% <25 >50 >75 Colour Clear Yellow to opalescent Yellow to purulent Gl mg/d. L . =serum May be low Very low
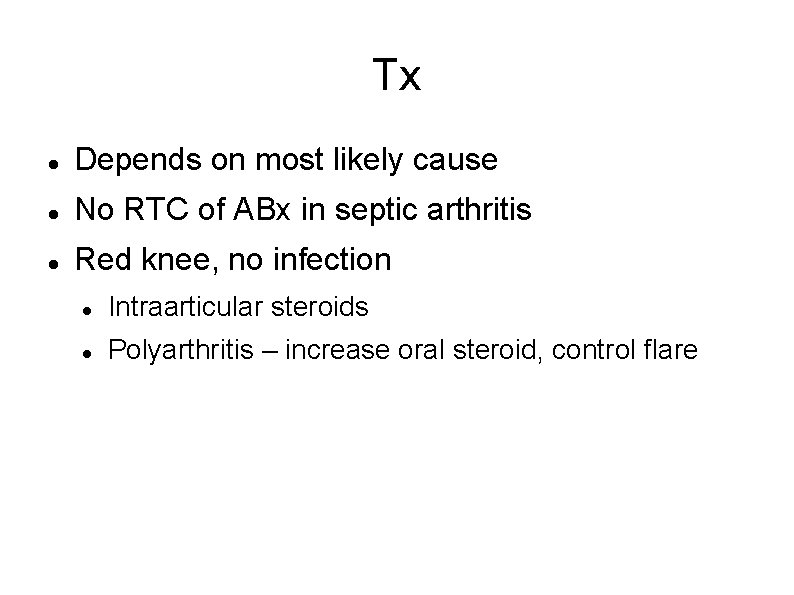
Tx Depends on most likely cause No RTC of ABx in septic arthritis Red knee, no infection Intraarticular steroids Polyarthritis – increase oral steroid, control flare
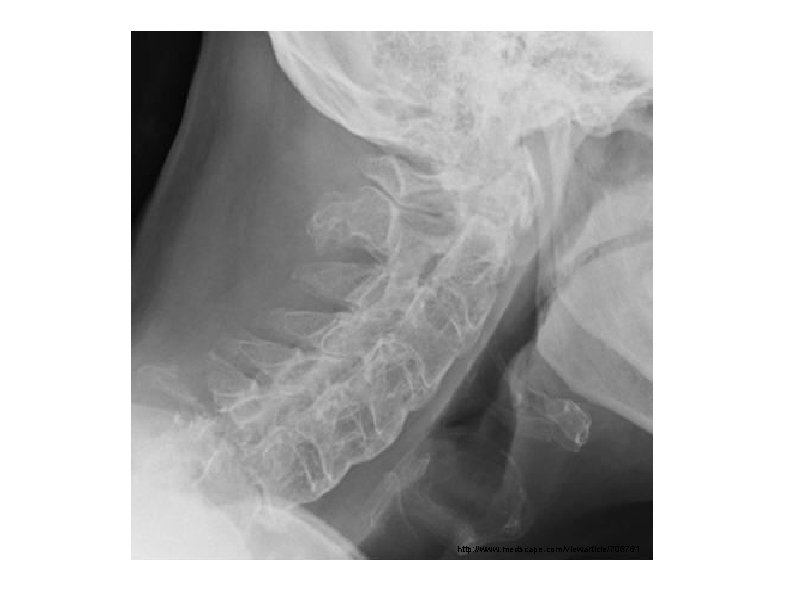
http: //www. medscape. com/viewarticle/706761
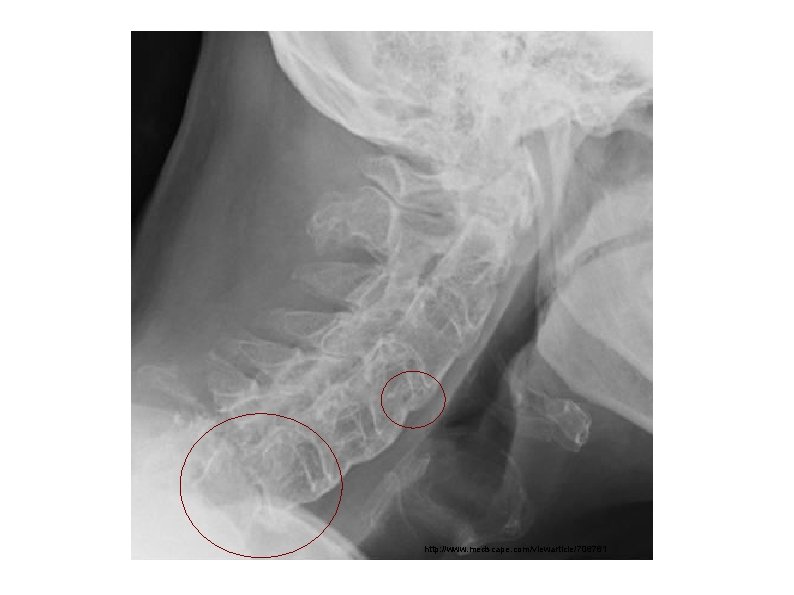
http: //www. medscape. com/viewarticle/706761
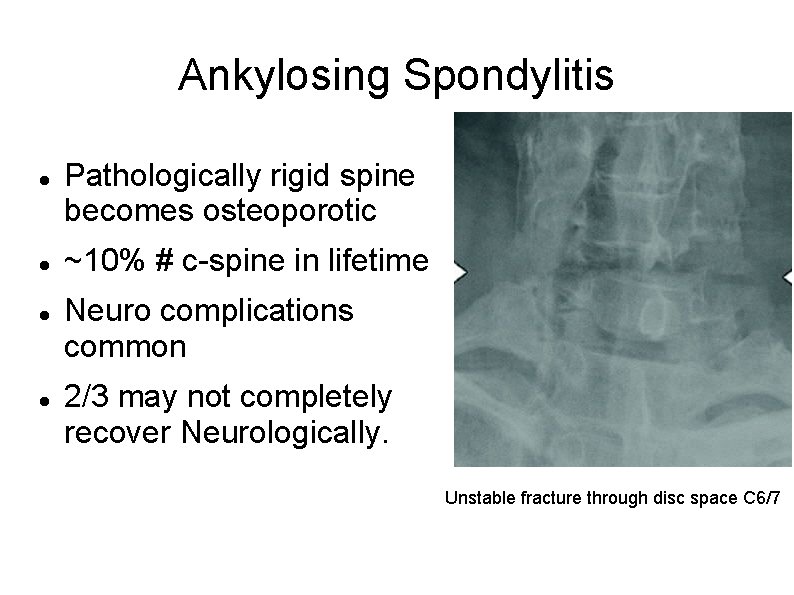
Ankylosing Spondylitis Pathologically rigid spine becomes osteoporotic ~10% # c-spine in lifetime Neuro complications common 2/3 may not completely recover Neurologically. Unstable fracture through disc space C 6/7
Ankylosing Spondylitis Most common presentation: Pain, usu localized. Aggravated by movement. Different from inflammatory pain of AS. Mass effect: Bleeding and edema May present as radiculopathy and myleopathy.
Ankylosing Spondylitis MC Site? C 6 -7 How is it missed? Not considered. Plainfilm XR No Hx major spinal trauma 50%! Nature of #: Often non-displaced Small size (Syndesmophytes)
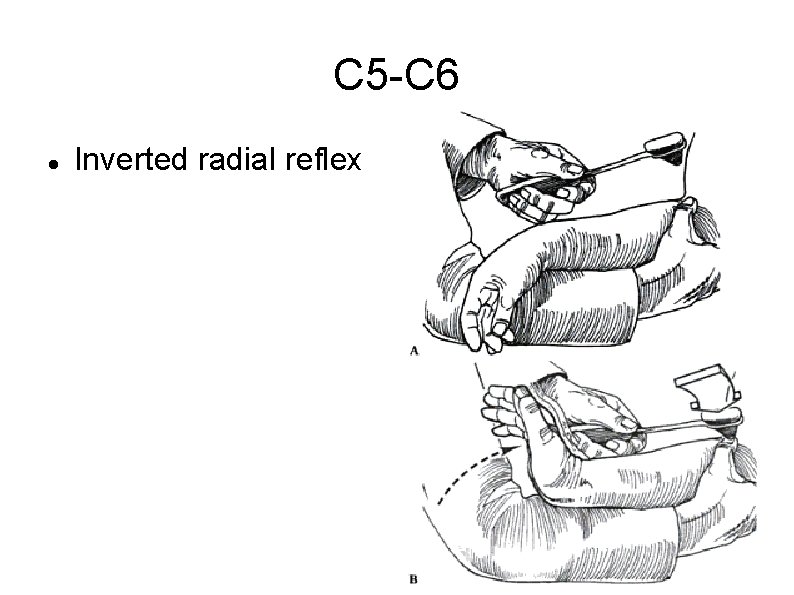
C 5 -C 6 Inverted radial reflex
Predicted Problems
Ankylosing Spondylitis When to order Imaging? If pain is new, out of ordinary. Neurologic complaints or findings. XR, CT +/- MRI What to do? Cautious immobilization. Ortho.
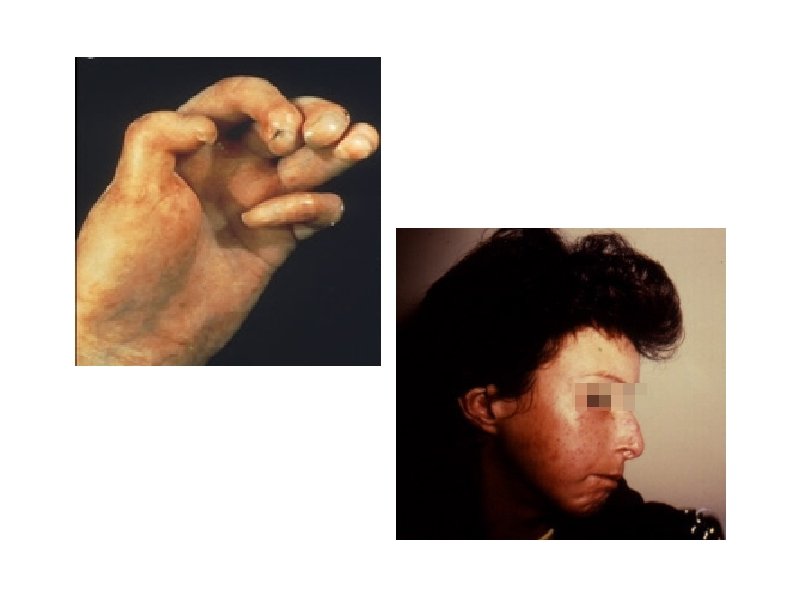
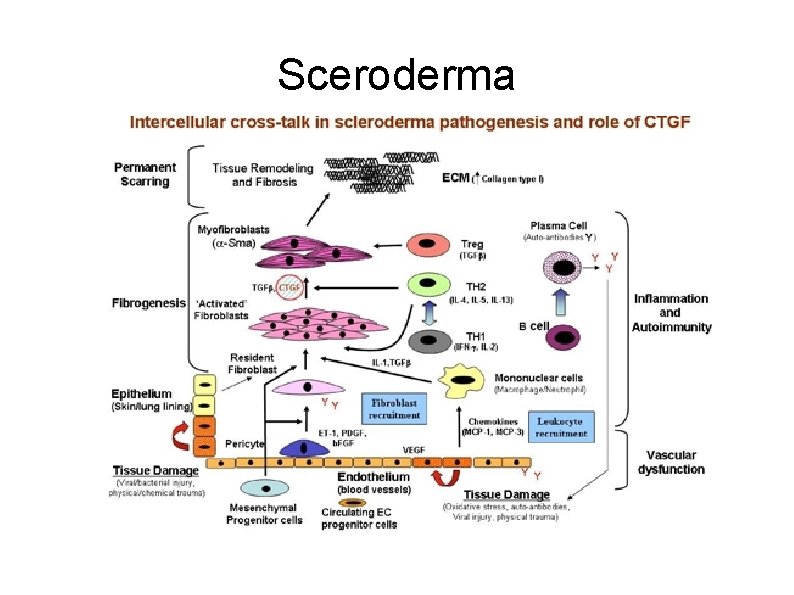
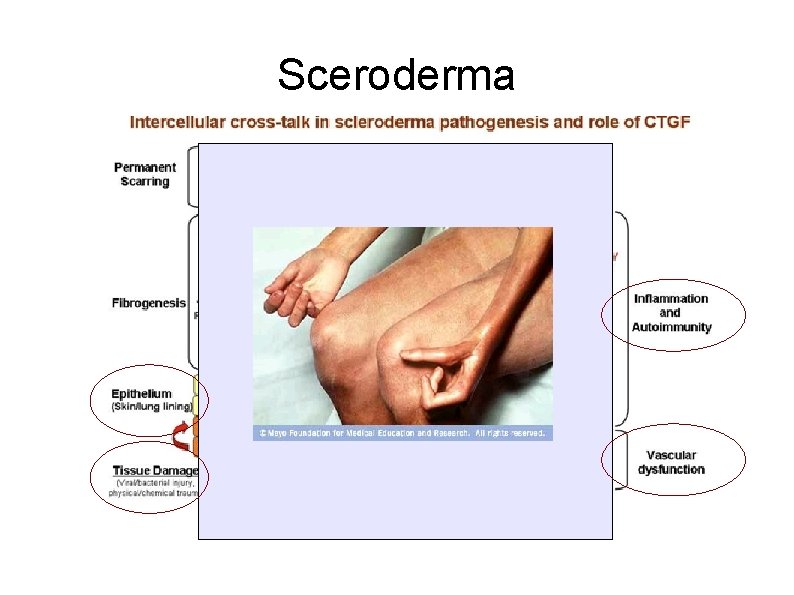
Sceroderma
Sceroderma
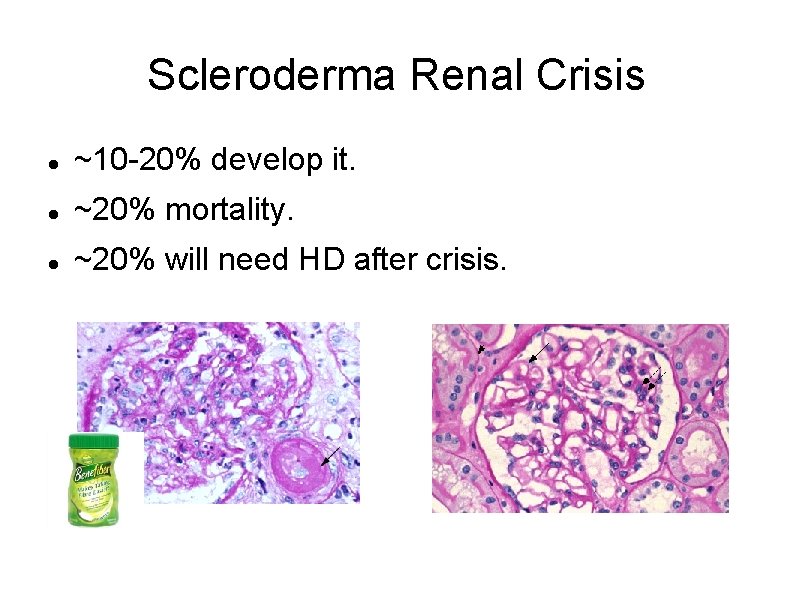
Scleroderma Renal Crisis ~10 -20% develop it. ~20% mortality. ~20% will need HD after crisis.
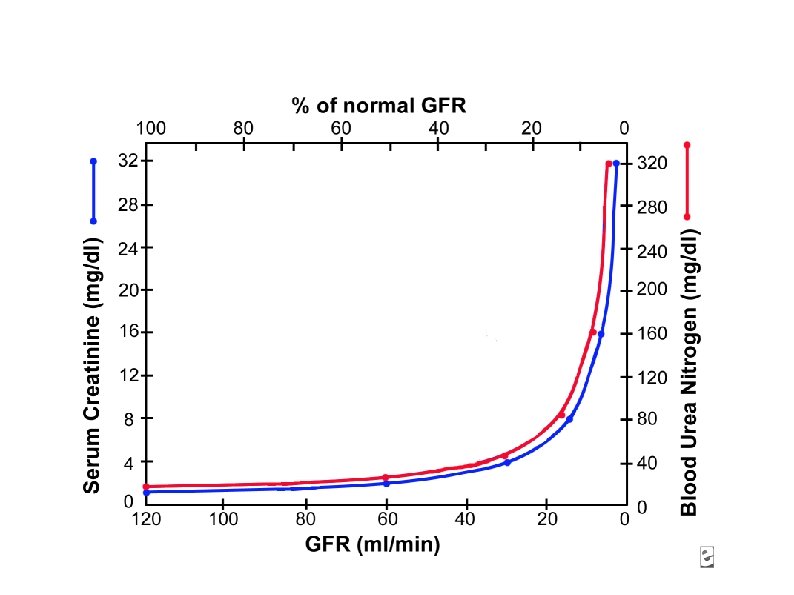
Scleroderma Renal Crisis How to identify it? Acute onset renal failure, progressive azotemia. New HTN (from normal to malignant). >150/85 2 x/24 hrs, mean peak 178/102. Headache Microangiopathic anemia c thrombocytopenia Urine – normal or mild prot c cells or casts +/- Flash pulmonary edema
Scleroderma Renal Crisis Steroids?
Scleroderma Renal Crisis What to do? ACEi (Grade 1 A). Captopril (Grade 2 B) – no CNS s/s. Add Nitroprusside – WITH CNS s/s. Nephro.
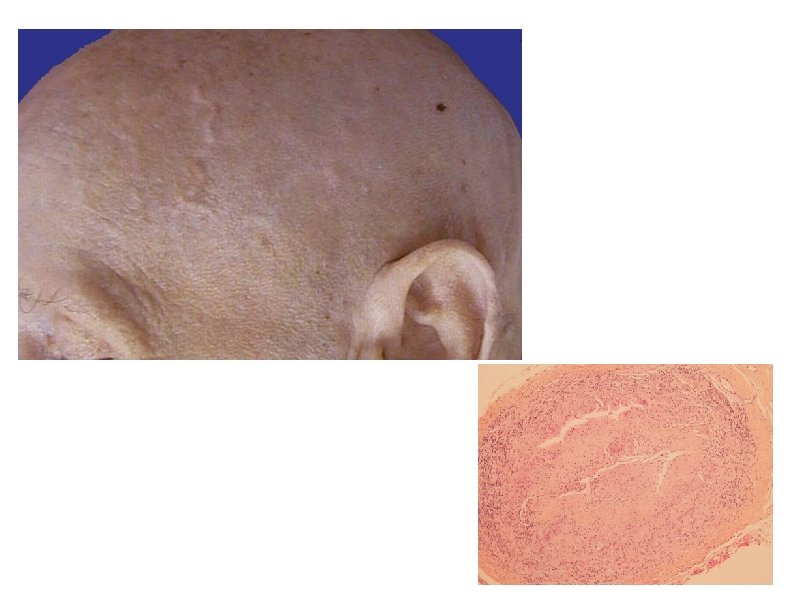
Giant Cell Arteritis Granulomatous arteritis of thoracic aorta and its branches. Classic symptoms: Temporal artertis Usu >50, new headache, tender scalp, fluctuating vision, jaw claudication, constitutional symptoms. Prednisone 60 mg/d biopsy within 1 week Polymyalgia Rheumatica
Lit review up to 2004 23 studies, 2036 pts, 5 languages. May be helpful, caution with test results. The future
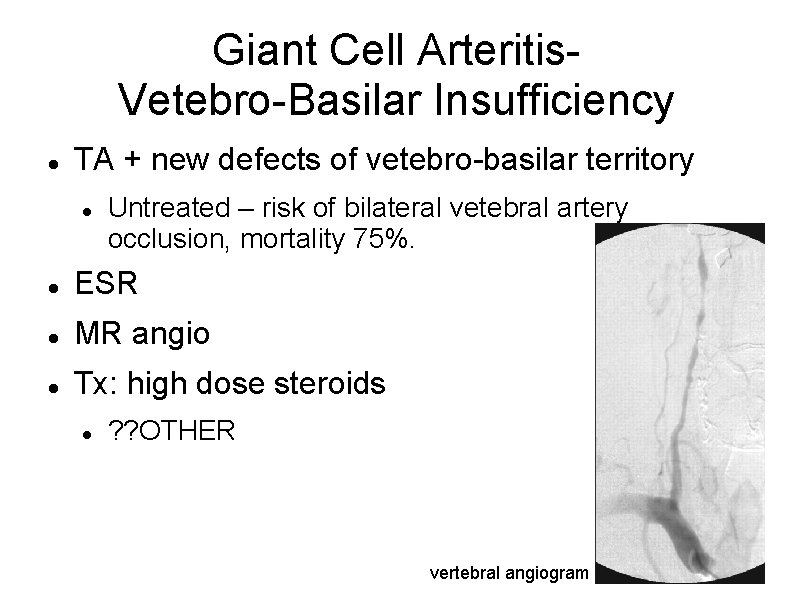
Giant Cell Arteritis. Vetebro-Basilar Insufficiency TA + new defects of vetebro-basilar territory Untreated – risk of bilateral vetebral artery occlusion, mortality 75%. ESR MR angio Tx: high dose steroids ? ? OTHER vertebral angiogram
Giant Cell Arteritis. Aortitis GCA – 27% pt large artery complications. Ascending aortic aneurysms 17 x AAA 2. 5 x Suspect it Hx, RF CT / MRI
Instability of C-Spine 71% of pts with RA have C-spine involvement 70% may have subluxation 25% of these -> frank dislocation 11% cord compression 5 yr survival – 80% 10 yr survival - 28%
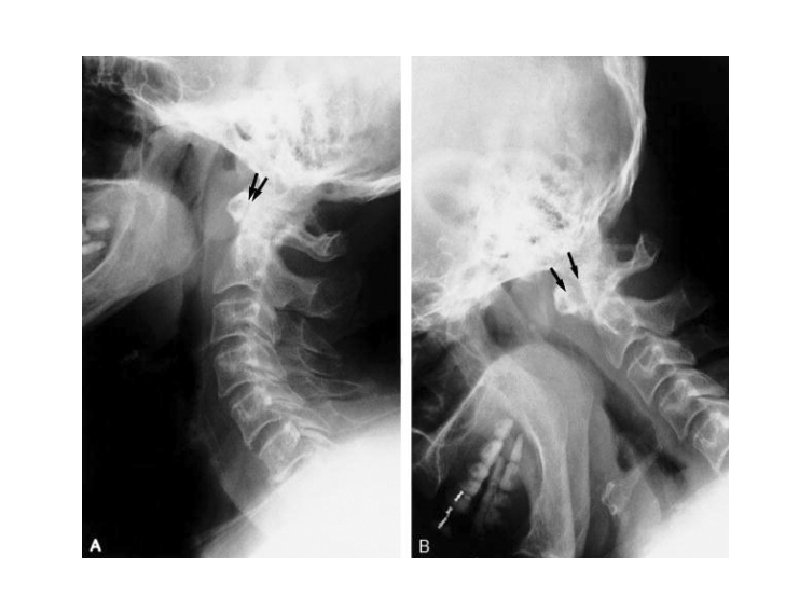
Atlantoaxial subluxation MCC: Neck/occiput/forehead pain in RA? Atlantoaxial subluxation MCC: Atlantoaxial subluxation ~70% Synovium of C 1 -C 2 articulation Synovial C 2 – Transverse ligament articulation Subaxial subluxation ~20% Synovium below C 2 Decision making in spinal care By Alexander R. Vaccaro, D. Greg Anderson
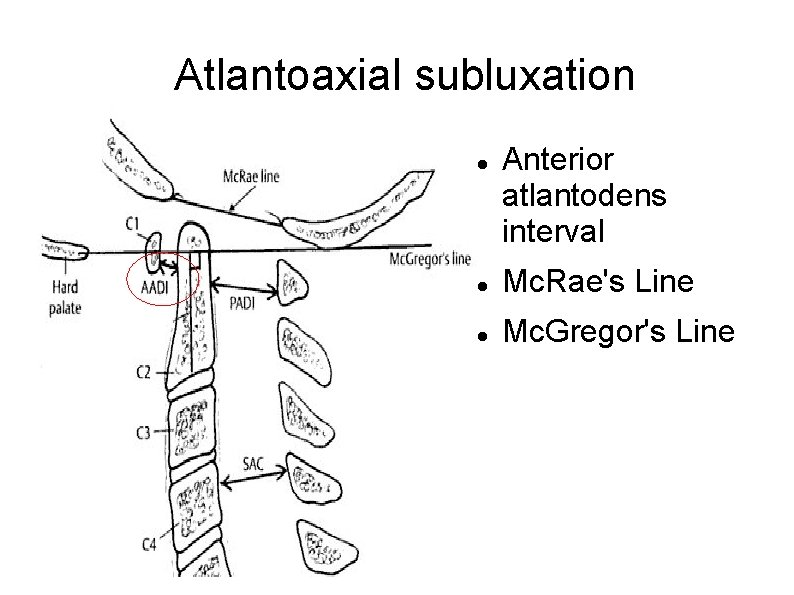
Atlantoaxial subluxation Anterior atlantodens interval Mc. Rae's Line Mc. Gregor's Line
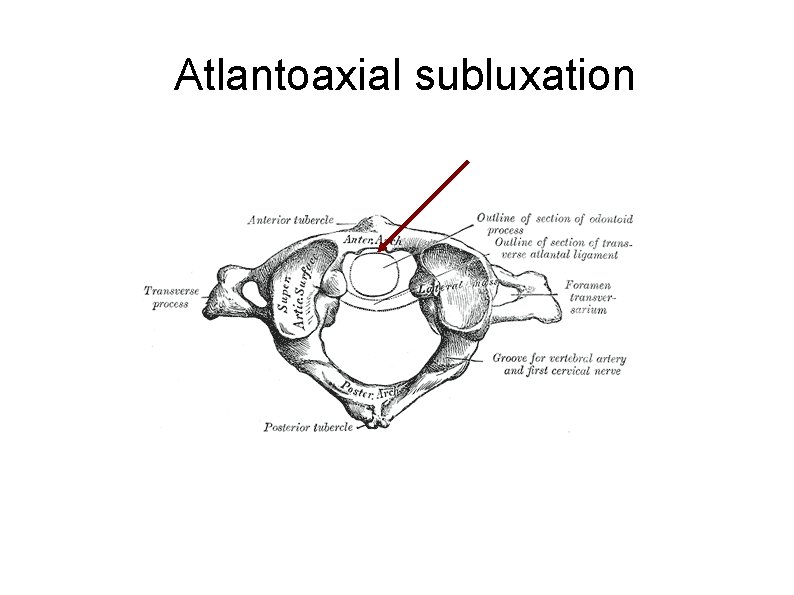
Atlantoaxial subluxation
Atlantoaxial subluxation General Precautions? Suspect it: RA pt with new onset occipital pain and/or tingling of fingers. Caution with Passive flexion of C-Spine. Caution with intubation. (Stabilize) When to order Flex/Ex? What to do if >3. 5 mm ADI?
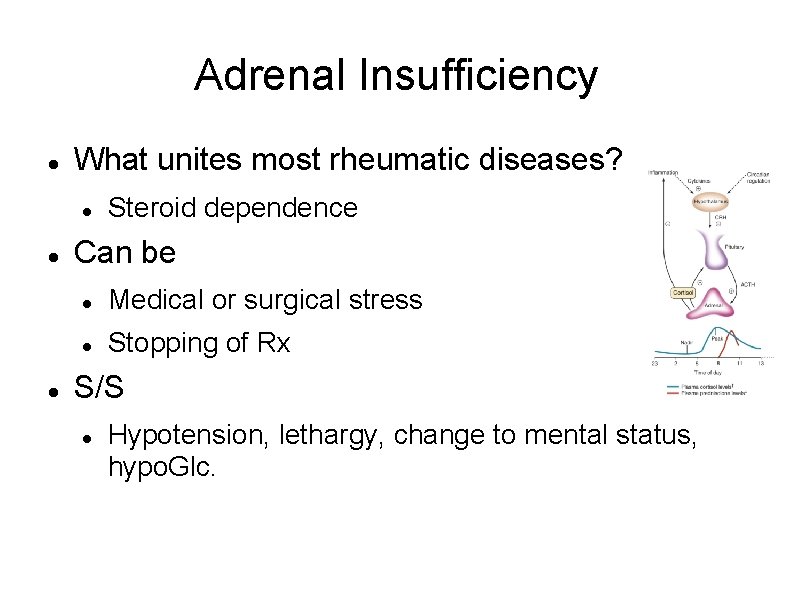
Adrenal Insufficiency What unites most rheumatic diseases? Steroid dependence Can be Medical or surgical stress Stopping of Rx S/S Hypotension, lethargy, change to mental status, hypo. Glc.
Adrenal Insufficiency Tx NS Glc Hydrocortisone 100 mg IV Or: (dexamethasone 4 mg IV – no impact on ACTH test or cortisol level)
Questions Bibliography Adam: Grainger & Allison's Diagnostic Radiology, 5 th ed Barr, W et al. Principles of Critical Care - 3 rd Ed. (2005), Ch 104 Current Diagnosis & Treatment in Orthopedics - 4 th Ed. (2006) Firestein: Kelley's Textbook of Rheumatology, 8 th ed. Fotini B. Karassa et al. Meta-Analysis: Test Performance of Ultrasonography for Giant-Cell Arteritis. Ann Intern Med. 2005; 142: 359 -369. Ginsberg Lawrence E, "Chapter 13. Imaging of the Spine" (Chapter). Chen MYM, Pope TL, Jr. , Ott DJ: Basic Radiology: http: //www. accessmedicine. com/content. aspx? a. ID=2271105. Mettler: Essentials of Radiology, 2 nd ed. P A Nee, J Benger and R M Walls. Airway management doi: 10. 1136/emj. 2005. 030635. Emerg. Med. J. 2008; 25; 98 -102 Physical examination of the spine By Todd J. Albert, Alexander R. Vaccaro Steen, VD, Medsger, TA. Case-control study of corticosteroids and other drugs that either precipitate or protect from the development of scleroderma renal crisis. Arthritis Rheum 1998; 41: 1613. http: //emedicine. medscape. com/article/238545 -overview http: //education. yahoo. com/reference/gray/illustrations/figure; _ylt=Ai. Xw. KBJ 25 LQJ 0 A 7 br. Q 1 WBY 9 t. Hok. C? id=86 http: //www. ucl. ac. uk/news-articles/07092002 http: //emedicine. medscape. com/article/331864 -media http: //www 0. sun. ac. za/ortho/webct-ortho/arthritis/aspirate-knee-s. jpg https: //www. bcbsri. com/BCBSRIWeb/images/mayo_popup/Scleroderma. jsp http: //emedicine. medscape. com/article/1265682 -overview