
RESISTANT HYPERTENSION Prof Dr Sarma VSN Rachakonda M



















- Slides: 45
RESISTANT HYPERTENSION Prof. Dr. Sarma VSN Rachakonda M. D (Internal Medicine). , M. Sc. , (Canada), FCGP, FICP, FIMSA, FRCP (G), FCCP (USA), FACP (USA) Hon. National Professor of Medicine, IMA – CGP, India Senior Consultant Physician & Cardio-metabolic Specialist Adjunct Professor, Tamilnadu Dr. MGR Medical University, Chennai www. drsarma. in
Essential Hypertension Uncontrolled Pseudo Hypertension Resistant Hypertension Refractory Hypertension Secondary Hypertension Reno Vascular Hypertension Malignant Hypertension UNDERSTAND THESE KEY WORDS
Sitting and standing recording of BP, Contralateral Two readings five minutes apart, rarely lower limb BP After resting, preferably same time of day – morning Korotkoff’s Standard cuff size -12 x 26 cm, Large cuff 13 x 36 cm Calibration Cuff of the instrument from time to time should encircle 80% of the arm - very thin clothing Quite No phase V – disappearance for diastolic environment, relaxed doctor and patient smoking, alcohol or caffeine by the patient Auscultatory gap, recollect Korotkoff’s phases, Phase IV? B. P MEASUREMENT ISSUES REVISITED
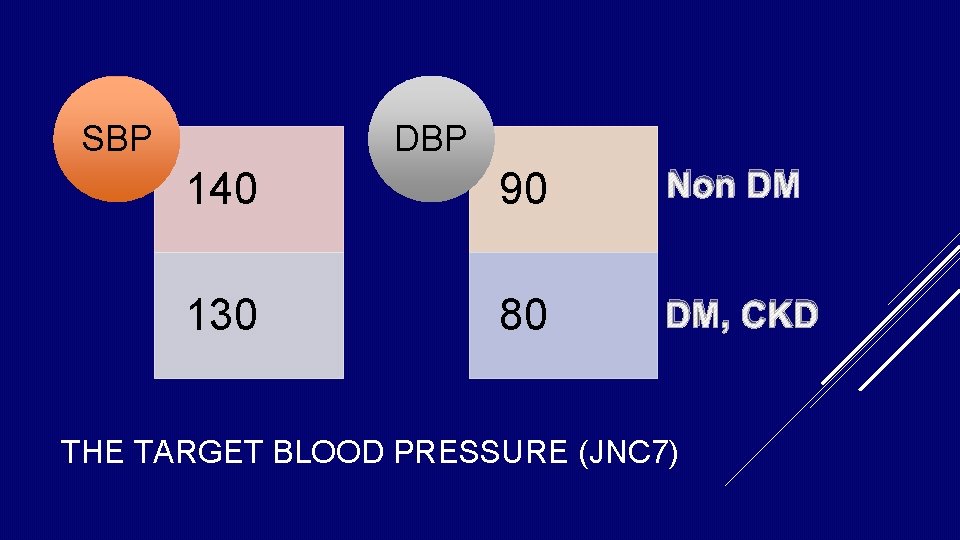
SBP DBP 140 90 Non DM 130 80 DM, CKD THE TARGET BLOOD PRESSURE (JNC 7)
“White TOD Coat” hypertension (not without risk) is minimal in White Coat hypertension Uncompressible Measurement BP arteries of old age(Osler’s Pseudo HT) issues – small cuff (< 80% of arm) Recorded without 5 -10 minutes of rest Non-compliance 40% with drug treatment patients discontinue Rx in the first year No life style modification practiced Be cautious to a patient as label pseudo hypertension PSEUDO RESISTANT HYPERTENSION
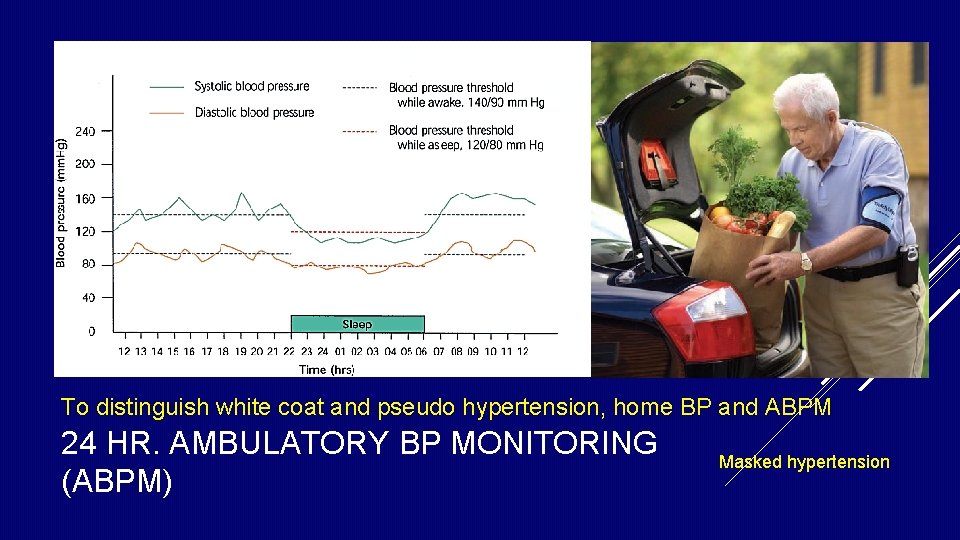
To distinguish white coat and pseudo hypertension, home BP and ABPM 24 HR. AMBULATORY BP MONITORING (ABPM) Masked hypertension
Hypertension in most patients is asymptomatic TOD and complications are often occult Side effects of the drugs, Cost, Combinations Complexity Multiple Lack of the regimens, timings medications for comorbidities of understanding of gravity of the disease, TOD False belief that hypertension got “cured” Social, economic and personal factors NON COMPLIANCE FOR RX. OF HYPERTENSION
Stop and Start Drugs Admit and Administer HOW TO EVALUATE FOR NON COMPLIANCE
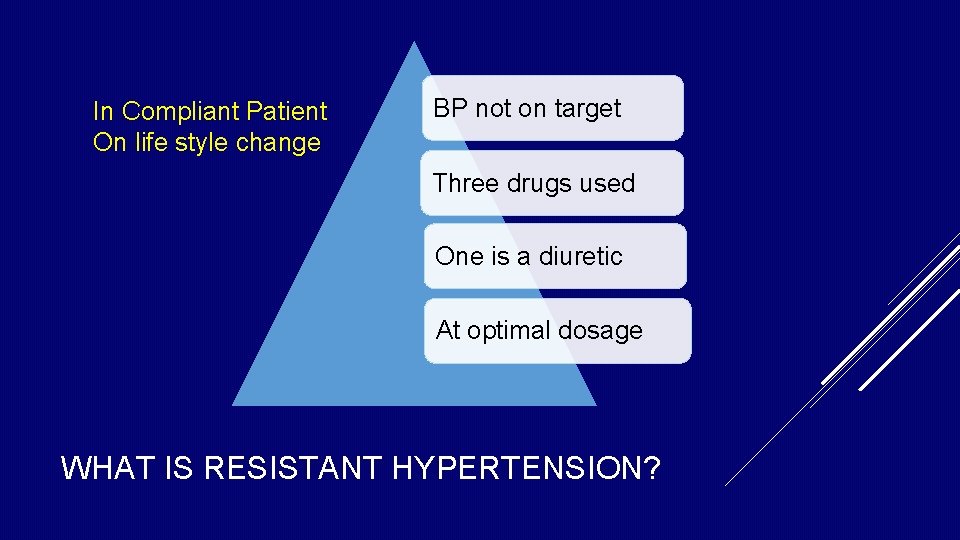
In Compliant Patient On life style change BP not on target Three drugs used One is a diuretic At optimal dosage WHAT IS RESISTANT HYPERTENSION?
Advancing High Base line Blood Pressure Obesity and Over Weight Excessive Chronic Dietary Salt Intake, Alcoholism Kidney Disease (CKD) Diabetes Left age Mellitus (Type II) Ventricular Hypertrophy (LVH) Black Race, Female Gender CLINICAL MARKERS FOR RESISTANT HYPERTENSION
Non narcotic analgesics, NSAIDs, Aspirin Selective COX-2 inhibitors (Celecoxib) Sympathomimetic Diet pills, Cocaine, Ephedrine Stimulants Alcohol Oral agents (decongestants) (Methylphenidate, Amphetamine) (binge drinking, >30 ml/day) Contraceptive Pills (OCP), Steroids, Anabolics Cyclosporine, Liquorice, Erythropoietin herbal compounds (ephedra) MEDICATIONS INTERACTION FOR BP CONTROL
Mostly Polygenic ACE Gene CYP 3 A 5 Most Esta. ENa. C β, γ Liddle’s GENETICS AND RESISTANT HYPERTENSION
Young Hypertensive First Time Hypertension after 60 yrs. Well Controlled - Now out of control WHOM WE SHOULD WATCH FOR SEC HT?
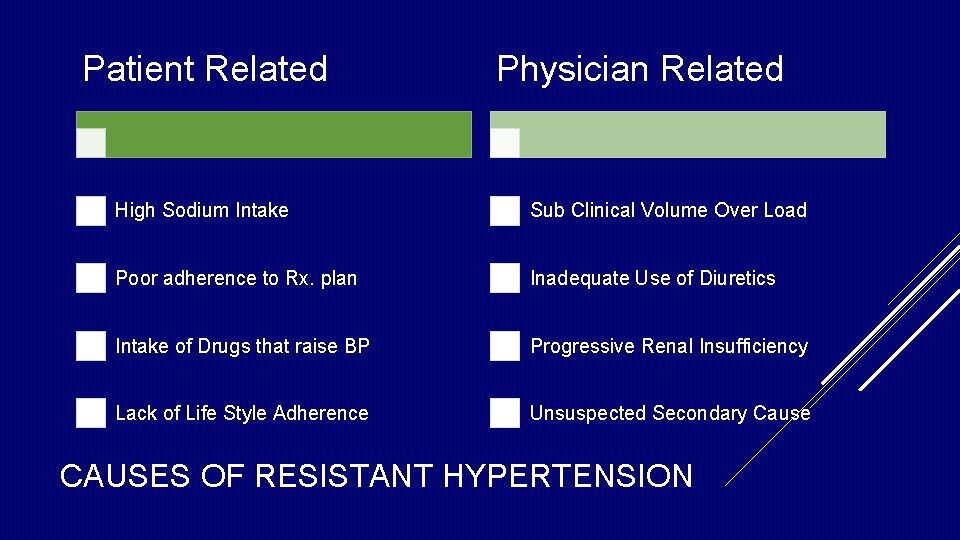
Patient Related Physician Related High Sodium Intake Sub Clinical Volume Over Load Poor adherence to Rx. plan Inadequate Use of Diuretics Intake of Drugs that raise BP Progressive Renal Insufficiency Lack of Life Style Adherence Unsuspected Secondary Cause CAUSES OF RESISTANT HYPERTENSION
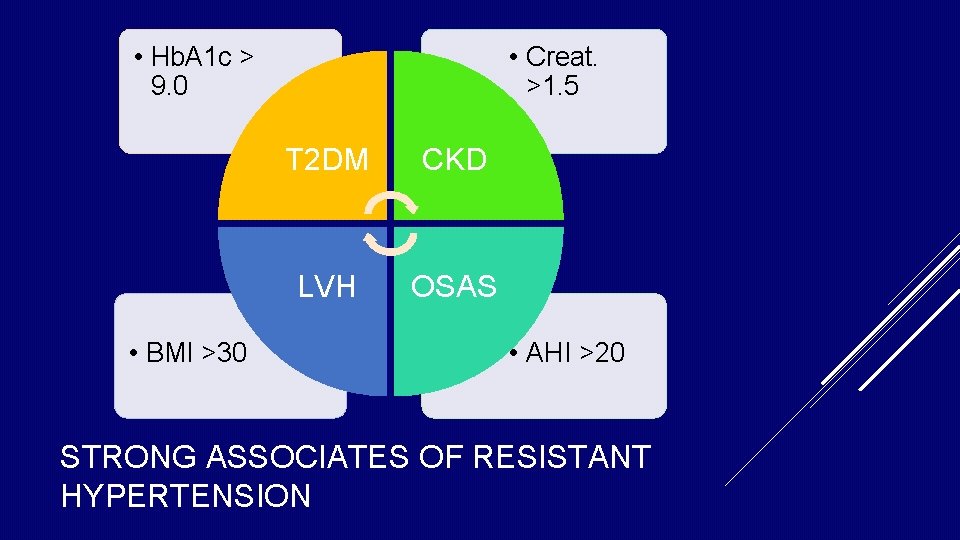
• Hb. A 1 c > 9. 0 • BMI >30 • Creat. >1. 5 T 2 DM CKD LVH OSAS • AHI >20 STRONG ASSOCIATES OF RESISTANT HYPERTENSION
Systolic BP difficult control Diastolic BP in old age PROBLEMS OF RESISTANT HYPERTENSION
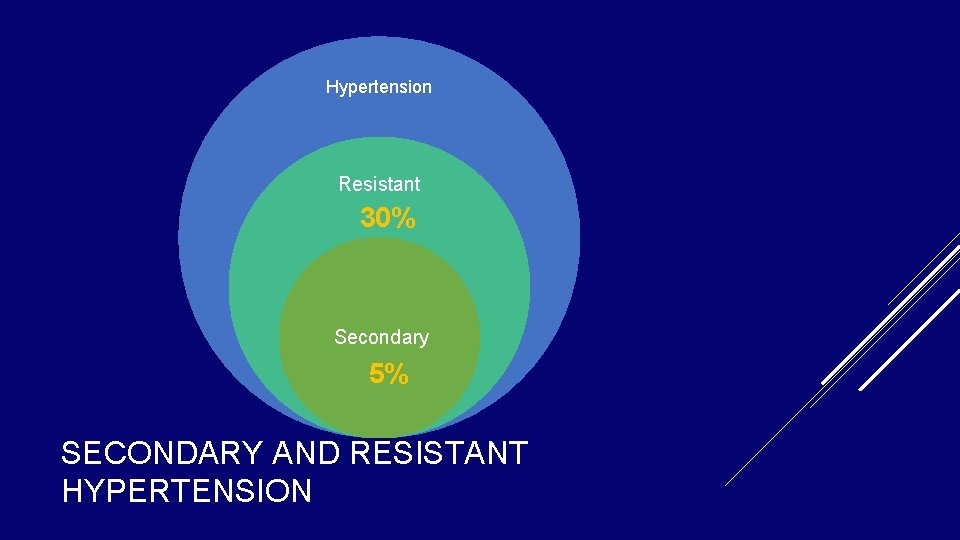
Hypertension Resistant 30% Secondary 5% SECONDARY AND RESISTANT HYPERTENSION
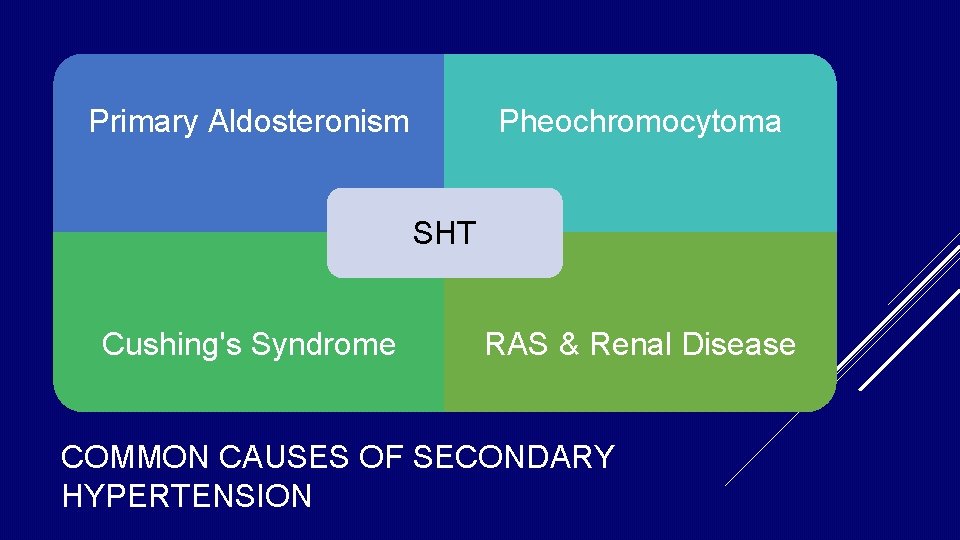
Primary Aldosteronism Pheochromocytoma SHT Cushing's Syndrome RAS & Renal Disease COMMON CAUSES OF SECONDARY HYPERTENSION
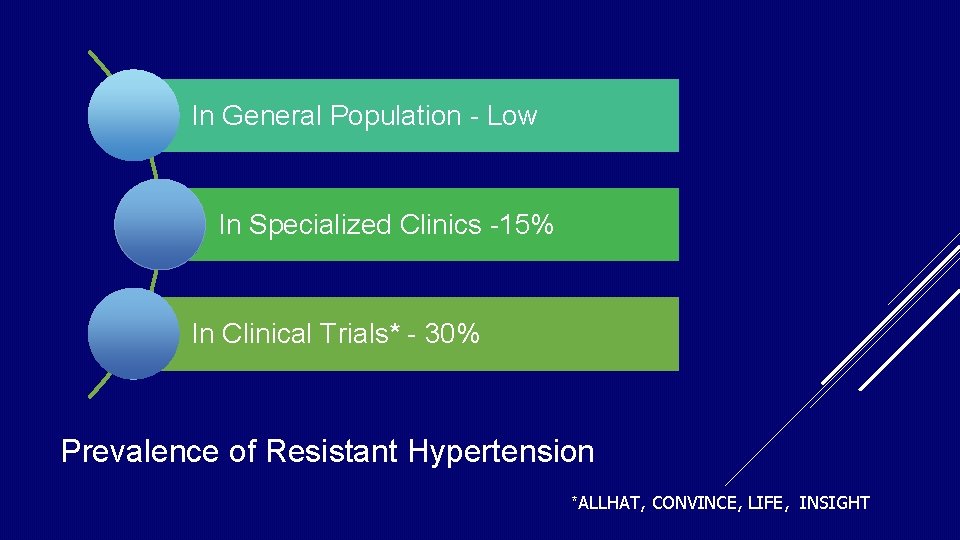
In General Population - Low In Specialized Clinics -15% In Clinical Trials* - 30% Prevalence of Resistant Hypertension *ALLHAT, CONVINCE, LIFE, INSIGHT
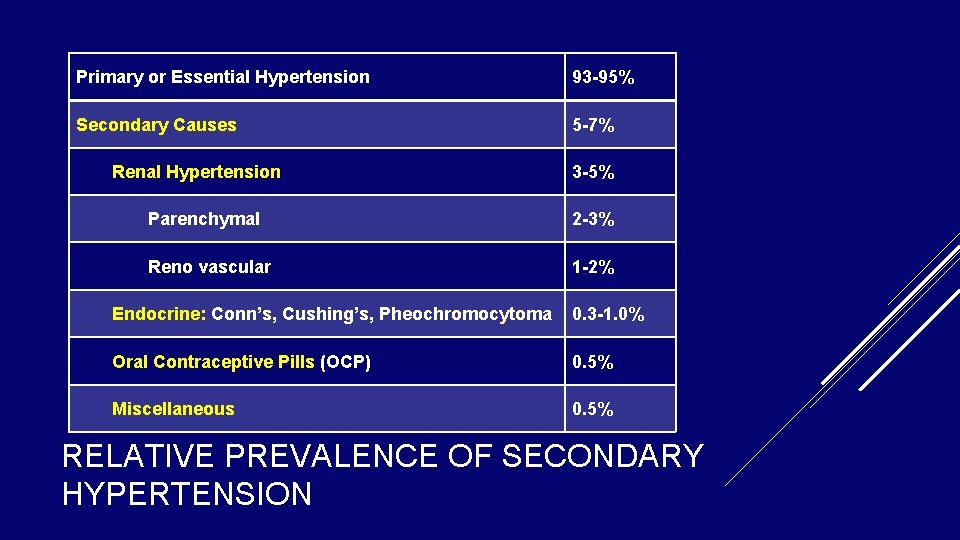
Primary or Essential Hypertension 93 -95% Secondary Causes 5 -7% Renal Hypertension 3 -5% Parenchymal 2 -3% Reno vascular 1 -2% Endocrine: Conn’s, Cushing’s, Pheochromocytoma 0. 3 -1. 0% Oral Contraceptive Pills (OCP) 0. 5% Miscellaneous 0. 5% RELATIVE PREVALENCE OF SECONDARY HYPERTENSION
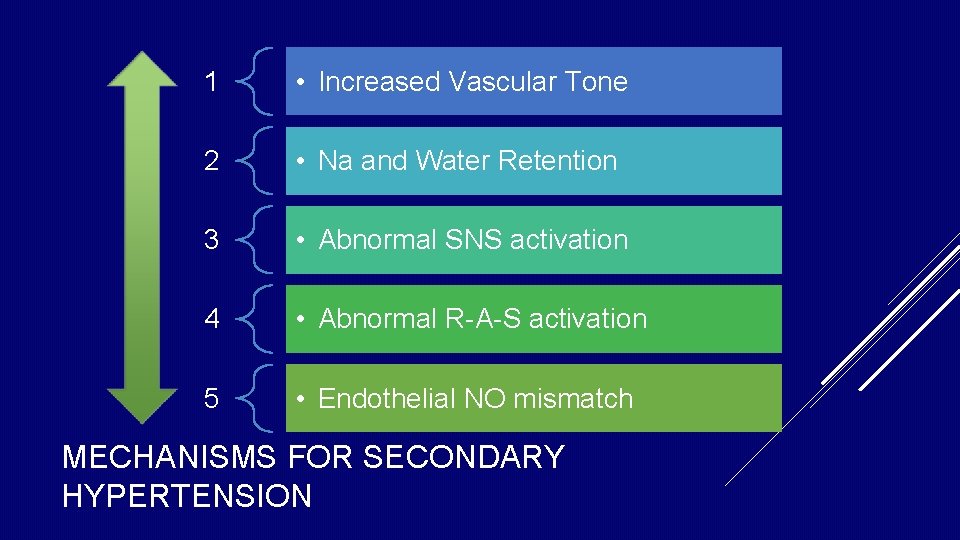
1 • Increased Vascular Tone 2 • Na and Water Retention 3 • Abnormal SNS activation 4 • Abnormal R-A-S activation 5 • Endothelial NO mismatch MECHANISMS FOR SECONDARY HYPERTENSION
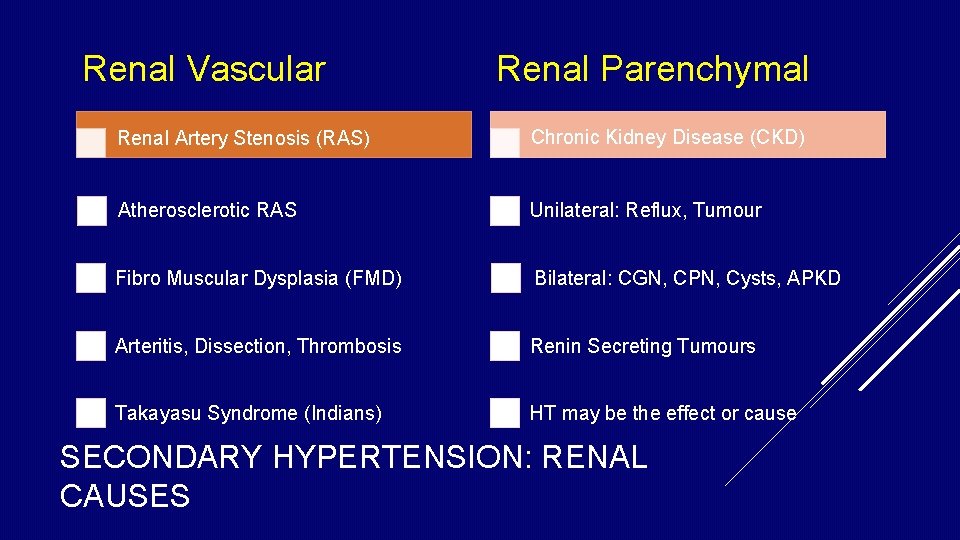
Renal Vascular Renal Parenchymal Renal Artery Stenosis (RAS) Chronic Kidney Disease (CKD) Atherosclerotic RAS Unilateral: Reflux, Tumour Fibro Muscular Dysplasia (FMD) Bilateral: CGN, CPN, Cysts, APKD Arteritis, Dissection, Thrombosis Renin Secreting Tumours Takayasu Syndrome (Indians) HT may be the effect or cause SECONDARY HYPERTENSION: RENAL CAUSES
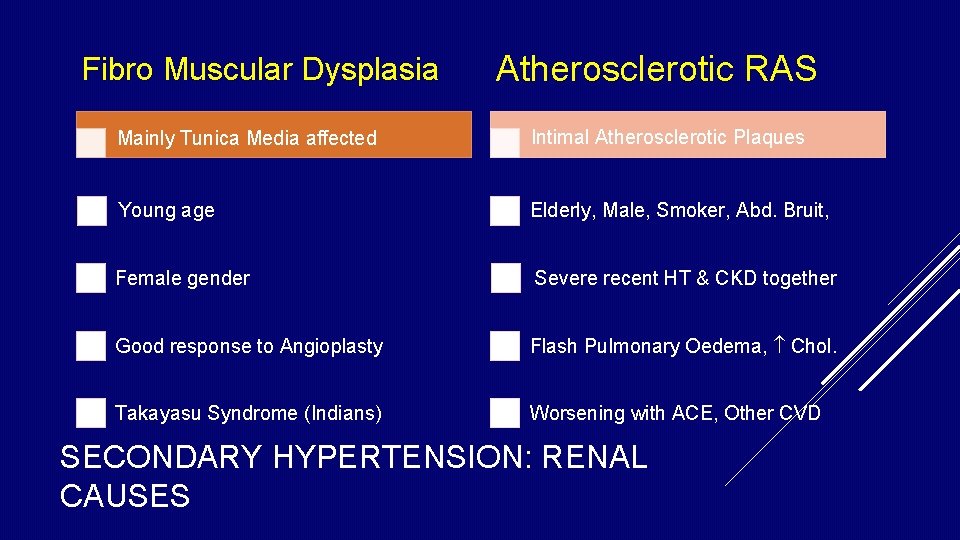
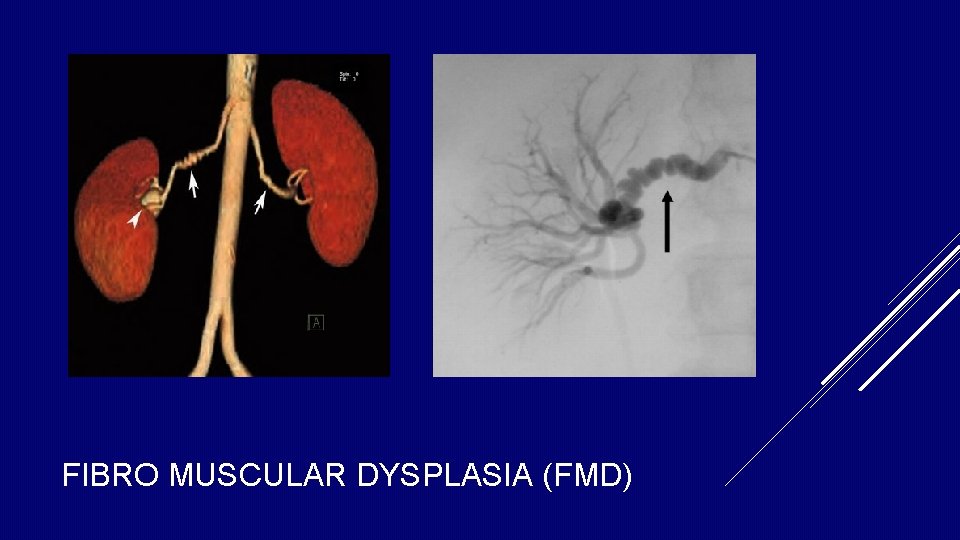
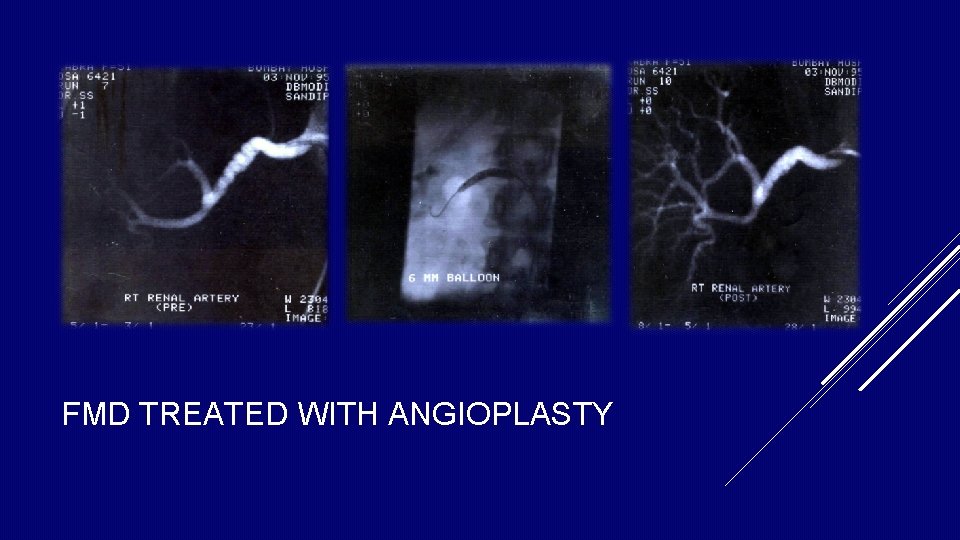
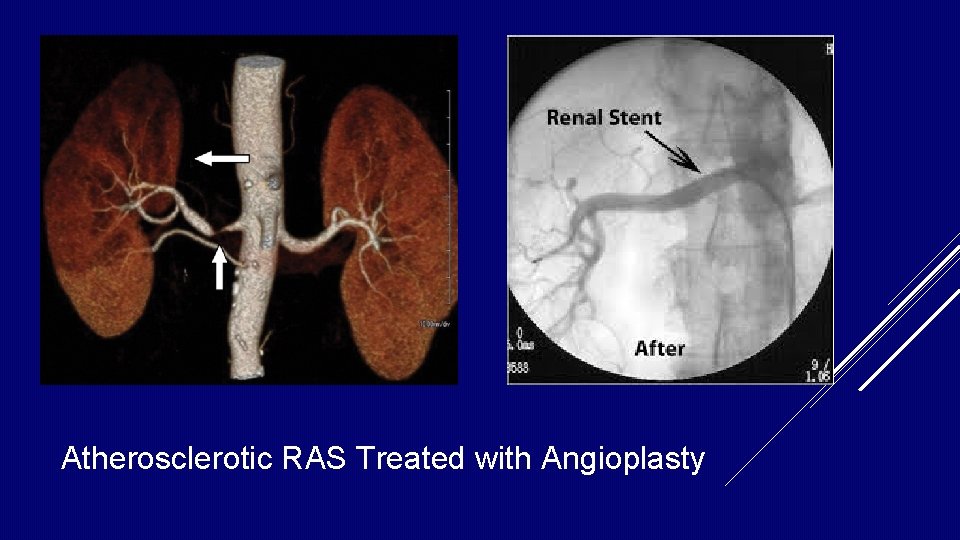
Fibro Muscular Dysplasia Atherosclerotic RAS Mainly Tunica Media affected Intimal Atherosclerotic Plaques Young age Elderly, Male, Smoker, Abd. Bruit, Female gender Severe recent HT & CKD together Good response to Angioplasty Flash Pulmonary Oedema, Chol. Takayasu Syndrome (Indians) Worsening with ACE, Other CVD SECONDARY HYPERTENSION: RENAL CAUSES
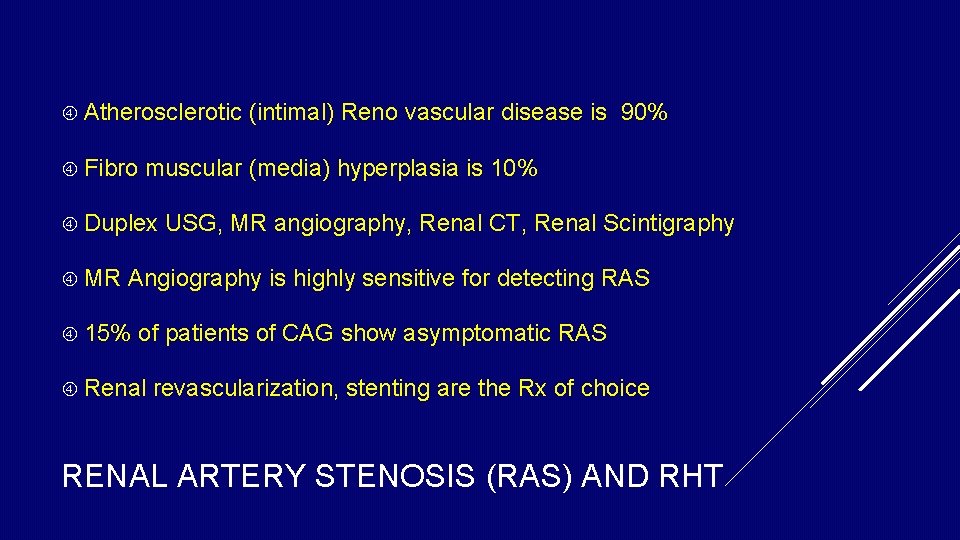
Atherosclerotic Fibro muscular (media) hyperplasia is 10% Duplex MR (intimal) Reno vascular disease is 90% USG, MR angiography, Renal CT, Renal Scintigraphy Angiography is highly sensitive for detecting RAS 15% of patients of CAG show asymptomatic RAS Renal revascularization, stenting are the Rx of choice RENAL ARTERY STENOSIS (RAS) AND RHT
FIBRO MUSCULAR DYSPLASIA (FMD)
FMD TREATED WITH ANGIOPLASTY
Atherosclerotic RAS Treated with Angioplasty
CKD is a common cause and complication of RHT Serum creatinine of >1. 5 mg% can cause RHT Increased sodium and fluid retention Expansion CKD of intravascular volume – fluid overload is strong predictor of poor outcomes and RHT RENAL PARENCHYMAL DISEASE AND RHT
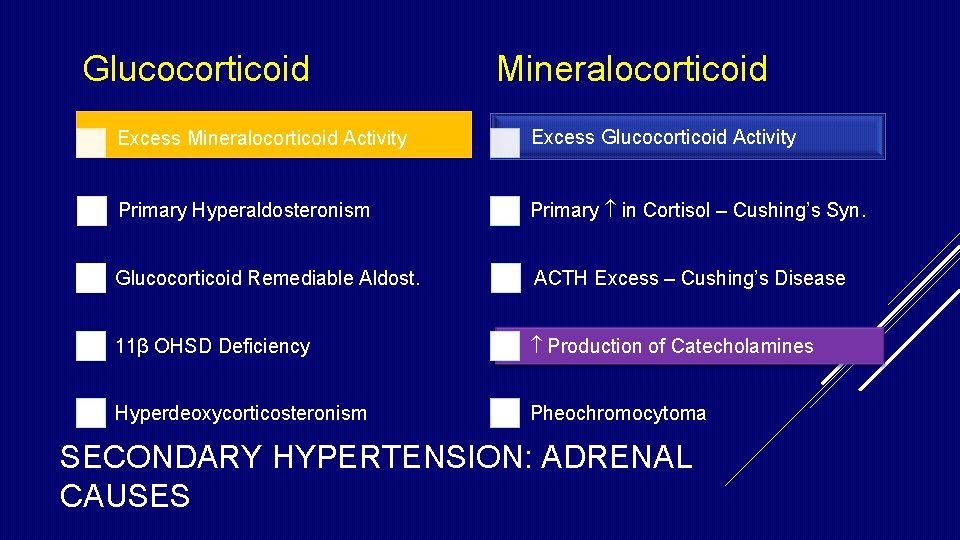
Glucocorticoid Mineralocorticoid Excess Mineralocorticoid Activity Excess Glucocorticoid Activity Primary Hyperaldosteronism Primary in Cortisol – Cushing’s Syn. Glucocorticoid Remediable Aldost. ACTH Excess – Cushing’s Disease 11β OHSD Deficiency Production of Catecholamines Hyperdeoxycorticosteronism Pheochromocytoma SECONDARY HYPERTENSION: ADRENAL CAUSES
20% of cases of RHT have Primary Aldosteronism Suppression Higher In of Renin Activity, Low K+ and Mg++, Met Alkalosis 24 hour urinary aldosterone excretion the background of higher dietary sodium intake General AT increase in R-A-S activity due to obesity II independent Aldosterone excess Stimulated by adipocyte derived secretagogues PRIMARY ALDOSTERONISM AND RHT
70% to 80% of patients with Cushing's have RHT Excessive stimulation of nonselective mineralocorticoid R IRS, DM and OSAS which coexist may contribute TOD is more severe in Cushing's syndrome Routine MR antihypertensive drugs are not effective Antagonist - Eplerenone or Spironolactone are effective Surgical excision of ACTH or Cortisol producing tumour CUSHING’S SYNDROME AND RHT
Small but important cause of Secondary RHT Prevalence Increased Episodic is 0. 1% to 0. 6% of hypertensives BP variability – A CV risk factor by itself Hypertension, Palpitation, Headache and Sweating Dysglycemia Has a diagnostic Specificity of 90% Plasma Has and abnormal GTT are usually associated free metanephrine and normetanephrine 99% sensitivity and 89% specificity PHEOCHROMOCYTOMA AND RHT
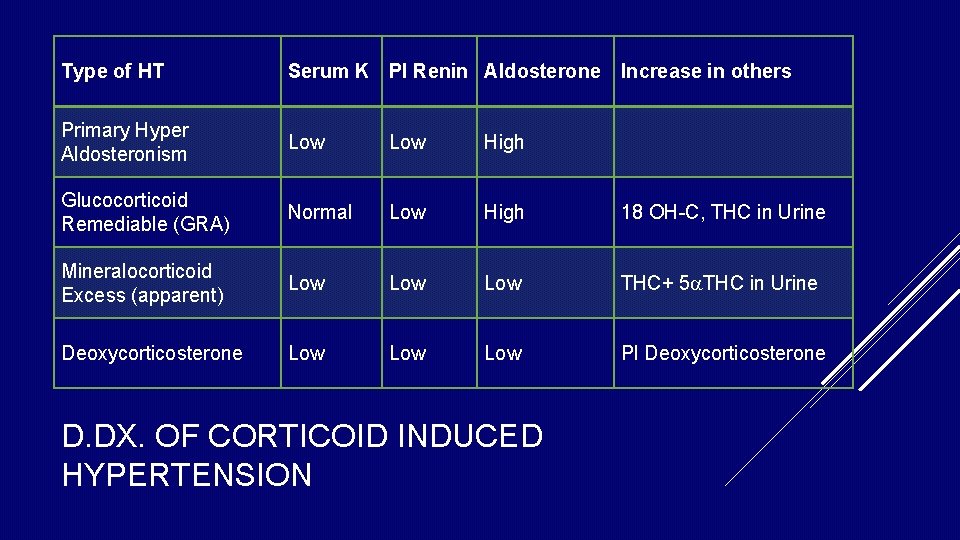
Type of HT Serum K Pl Renin Aldosterone Increase in others Primary Hyper Aldosteronism Low High Glucocorticoid Remediable (GRA) Normal Low High 18 OH-C, THC in Urine Mineralocorticoid Excess (apparent) Low Low THC+ 5 THC in Urine Deoxycorticosterone Low Low Pl Deoxycorticosterone D. DX. OF CORTICOID INDUCED HYPERTENSION
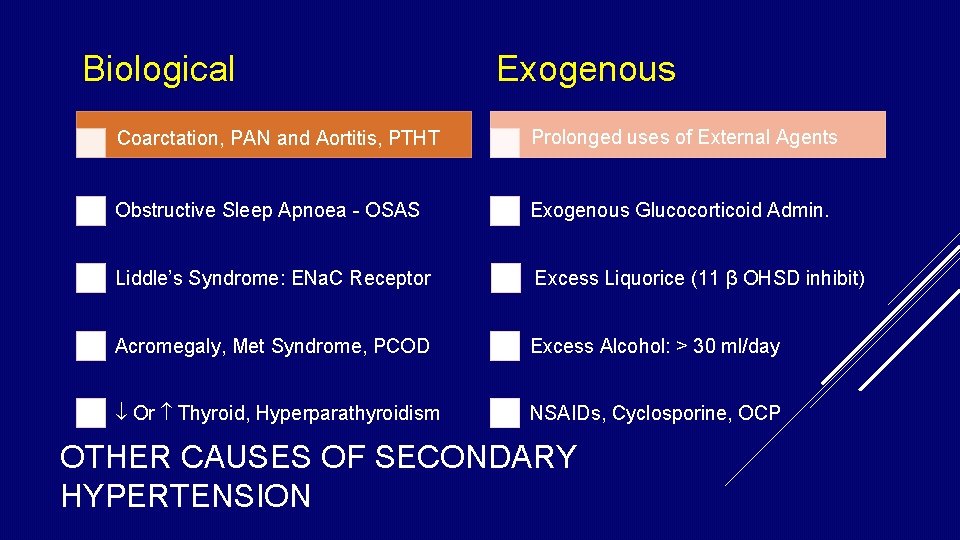
Biological Exogenous Coarctation, PAN and Aortitis, PTHT Prolonged uses of External Agents Obstructive Sleep Apnoea - OSAS Exogenous Glucocorticoid Admin. Liddle’s Syndrome: ENa. C Receptor Excess Liquorice (11 β OHSD inhibit) Acromegaly, Met Syndrome, PCOD Excess Alcohol: > 30 ml/day Or Thyroid, Hyperparathyroidism NSAIDs, Cyclosporine, OCP OTHER CAUSES OF SECONDARY HYPERTENSION
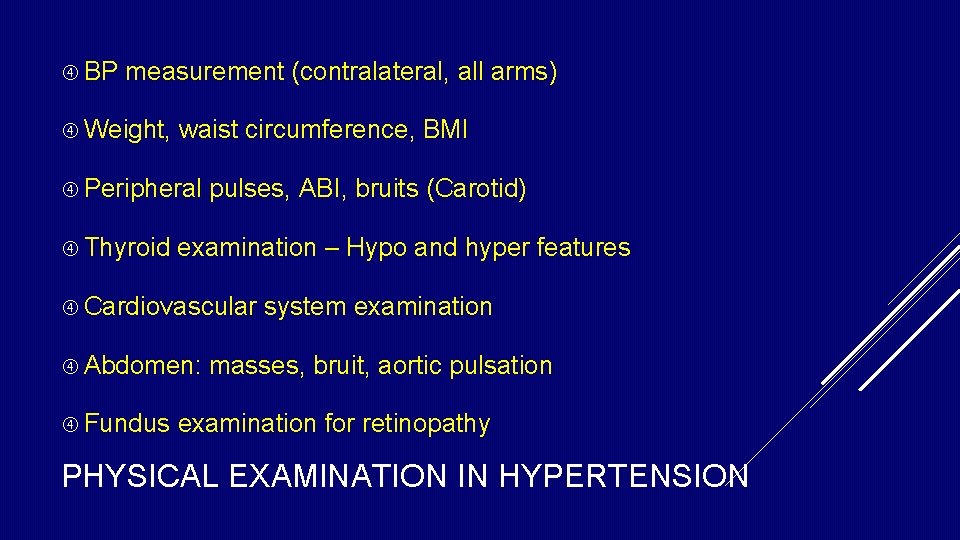
BP measurement (contralateral, all arms) Weight, waist circumference, BMI Peripheral Thyroid pulses, ABI, bruits (Carotid) examination – Hypo and hyper features Cardiovascular Abdomen: Fundus system examination masses, bruit, aortic pulsation examination for retinopathy PHYSICAL EXAMINATION IN HYPERTENSION
Good blood pressure recording technique – cuff size Strict compliance with treatment recommendations Evaluation for secondary causes of resistant hypertension Ambulatory BP monitoring (ABPM) – to exclude “White Coat” Assessment History Day for TOD – CKD, Retinopathy, LVH – is essential of drug intake that can cause resistant hypertension time sleepiness, loud snoring, apnoeic spells - OSAS EVALUATION OF RESISTANT HYPERTENSION
Angiography, DSA MRI, CT, USG, Colour D Nuclear Medicine SECONDARY HYPERTENSION: EVALUATIONS
Salt Restriction Weight Loss Physical Activity Smoking Cessation Alcohol Abstinence Glycaemia and Lipid Control LIFE STYLE PRINCIPLES FOR HYPERTENSION
If a correctable cause is found, treat that Aggressive Effective MRA drug therapy – Optimizing the current Rx. Diuresis – Furosemide BID/Torsemide OD antagonists, Spironolactone, Triamterene, Amiloride Hydralazine or Minoxidil + β-Blocker and a diuretic Transdermal Clonidine DRUG TREATMENT OF RESISTANT HYPERTENSION
Consider Plasma Renin Measurement Adding Doxazosin to regimen Spironolactone, Eplerenone SOME PRACTICAL POINTS OF RX. OF RHT
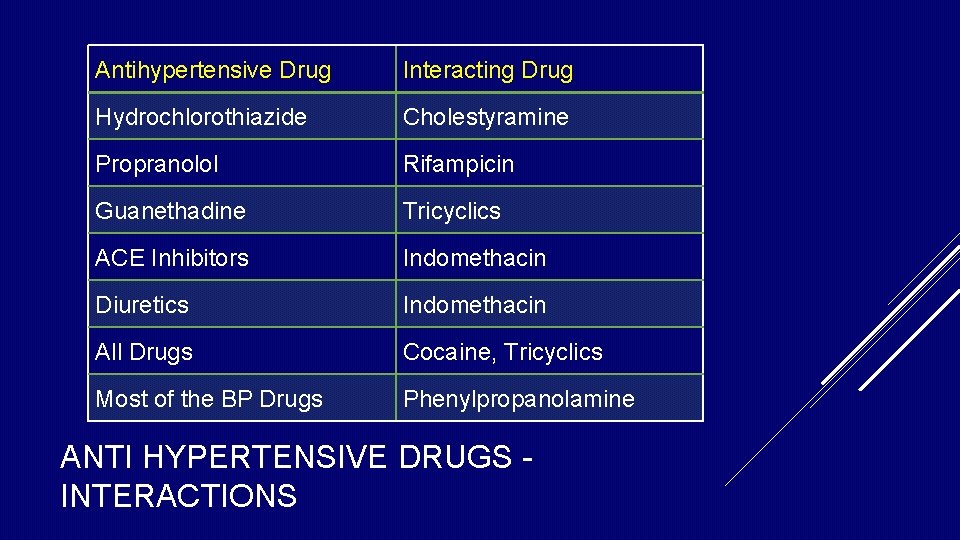
Antihypertensive Drug Interacting Drug Hydrochlorothiazide Cholestyramine Propranolol Rifampicin Guanethadine Tricyclics ACE Inhibitors Indomethacin Diuretics Indomethacin All Drugs Cocaine, Tricyclics Most of the BP Drugs Phenylpropanolamine ANTI HYPERTENSIVE DRUGS INTERACTIONS
Direct Renin Inhibitors (Aliskiren) Neutral New Endopeptidase (NEP) Inhibitors (Omapatrilat) Aldosterone Antagonists (Eplerenone) Aldosterone Clonidine Extended Release Endothelin Novel Synthase Inhibitors Antagonists (Darusentan) Combinations Algorithms FUTURE OPTIONS FOR RESISTANT HYPERTENSION
The following procedures are invasive and irreversible Implantable pulse generators – perivascular carotid sinus leads to be surgically implanted Renal Denervation – particularly in those with renal origin of the disease – Promising results Neurovascular decompensation – may be temporary NON PHARMACOLOGICAL APPROACHES
Thank you all www. drsarma. in