
Reference Intervals for New Methods Dr Graham Jones






















- Slides: 42
Reference Intervals for New Methods Dr Graham Jones Department of Chemical Pathology St Vincent’s Hospital, Sydney www. sydpath. stvincents. com. au
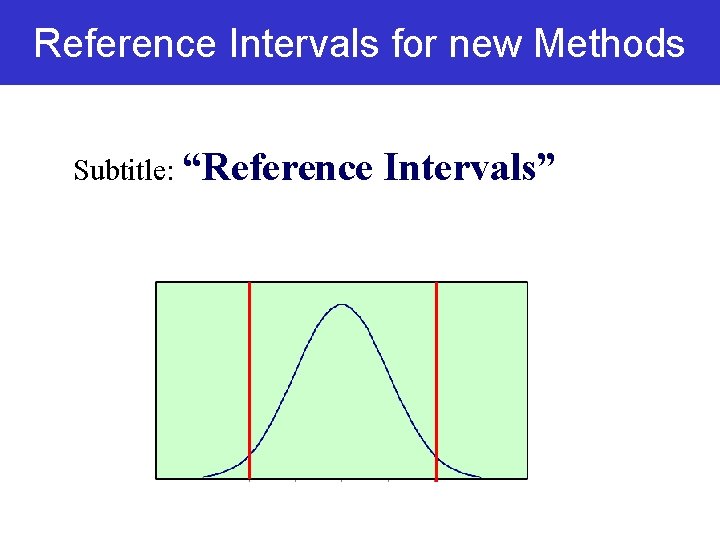
Reference Intervals for new Methods Subtitle: “Reference Intervals”
Contents • Introduction to reference intervals • Reference intervals for the new method – Derive de-novo – Transfer from old method – Literature – Other Laboratories • Conclusions
Defining Reference Intervals • Central 95% of results from a reference population – IFCC/NCCLS definition • Excludes 2. 5% above and below interval • For healthy population are “Health-associated Reference intervals” • Can be any population, but must be defined – eg, pregnant, premature, hospitalised, treated.
Other forms: • Other statistical cuttoffs – Troponin: 99 th centile of healthy population – Apo (a): 80 th centile of total population • Recommended interval (decision point) – Impaired fasting glucose (6. 1 - 6. 9 mmol/L) – Target LDL concentration (<2. 0 mmol/L) • Therapeutic Interval – Drugs, INR, APTT, TSH
Current Paradigm • Based on recommendations from the NCCLS and the IFCC • Repeated in Product Information from most reagent suppliers • Encoded in the NATA summary of ISO/IEC guide 17025. – laboratories may perform their own detailed reference interval studies or – may validate reference intervals published elsewhere for their own methods and populations
Generating a new reference interval • • • Define and select reference population* Define collection conditions and numbers Collect samples Analyse samples Perform statistical evaluation* Put into practice • Tietz Textbook covers standard approach very well (HE Solberg)
Define Reference Population • Source – eg blood bank, lab volunteers, students • Numbers • Exclusions • Likely Partitioning – Age – Sex – Other • Difficult to get extremes of age and high numbers
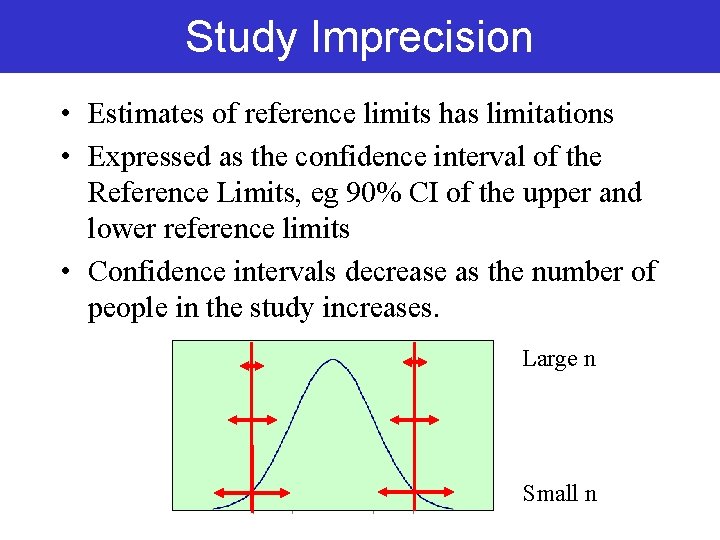
Study Imprecision • Estimates of reference limits has limitations • Expressed as the confidence interval of the Reference Limits, eg 90% CI of the upper and lower reference limits • Confidence intervals decrease as the number of people in the study increases. Large n Small n
Non-parametric statistics • Lowest number where error envelope can be calculated is 120 • For n=120 – 2. 5 th centile is 4 th lowest result – 90% confidence limit for LRL is lowest sample and 7 th lowest sample • These values often very scattered giving wide intervals
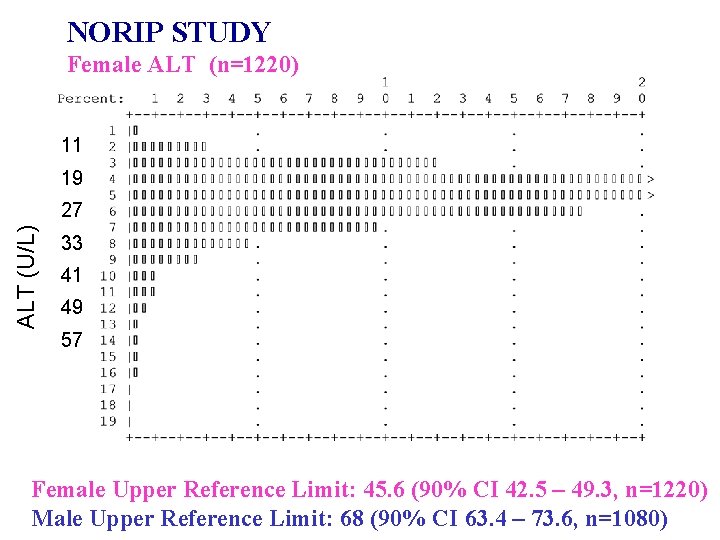
NORIP STUDY Female ALT (n=1220) 11 19 ALT (U/L) 27 33 41 49 57 Female Upper Reference Limit: 45. 6 (90% CI 42. 5 – 49. 3, n=1220) Male Upper Reference Limit: 68 (90% CI 63. 4 – 73. 6, n=1080)
Generating Intervals • Is hard to do well • Requires time and effort and money • But any local data may be very useful for validation of other intervals
“Impossible” Intervals • Some reference intervals are essentially impossible to produce from local studies: – Paediatric intervals – Stages of pregnancy (eg h. CG in 5 th week) – Stages of menstrual cycle – Nutritional parameters • Reflects local diet • May normalise deficiency state
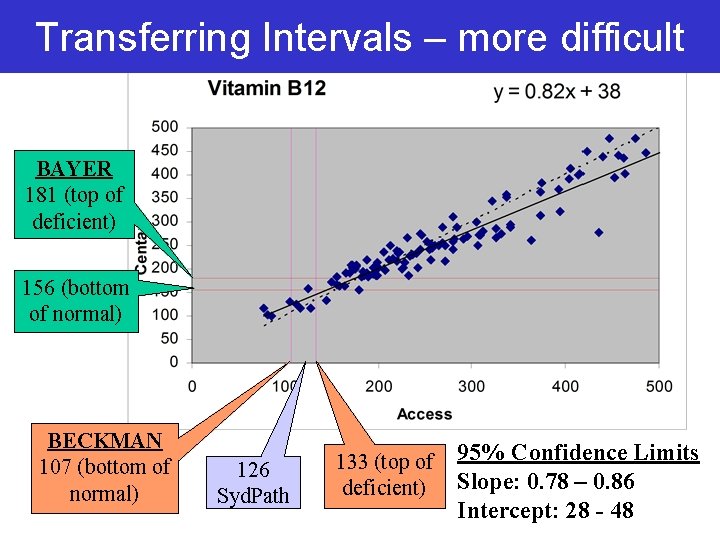
Transfer Intervals from previous method • Implies previous intervals are good – Check source and validity • Transfer requires good correlation • Advantage is clinical acceptance – Note: much the following data related to introduction of a Bayer Centaur for Vitamin B 12.
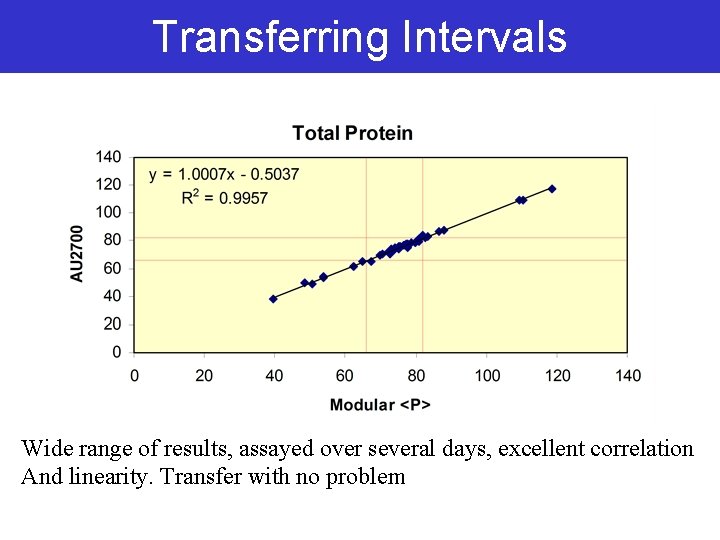
Transferring Intervals Wide range of results, assayed over several days, excellent correlation And linearity. Transfer with no problem
Transferring Intervals – more difficult BAYER 181 (top of deficient) 156 (bottom of normal) BECKMAN 107 (bottom of normal) 126 Syd. Path 133 (top of deficient) 95% Confidence Limits Slope: 0. 78 – 0. 86 Intercept: 28 - 48
Correlation Data • Patient samples • Focus on results near limits • Beware effect of extreme values on statistics – Passing and Bablock preferred to linear regression • Use correlation data from several days and calibrations • Review source of previous Intervals
Validation of reference intervals • NCCLS protocol • Measure 20 samples appropriate for reference interval on new method • Exclude outliers • If 2 or fewer are outside proposed inetrvals – Accept intervals • If >2 are outside proposed intervals – Measure another 20 – If 2 or fewer are outside – accept intervals • Cannot detect overly wide intervals
Review Previous Method • Previous method may have significant amounts of data (information) • For many assays many of the results will be on “normal” patients • For all assays will allow assessment of previous reference intervals • Methods: – Inspection – Frequency histograms (all data, some data) – Formal methods (Bhattacharya)
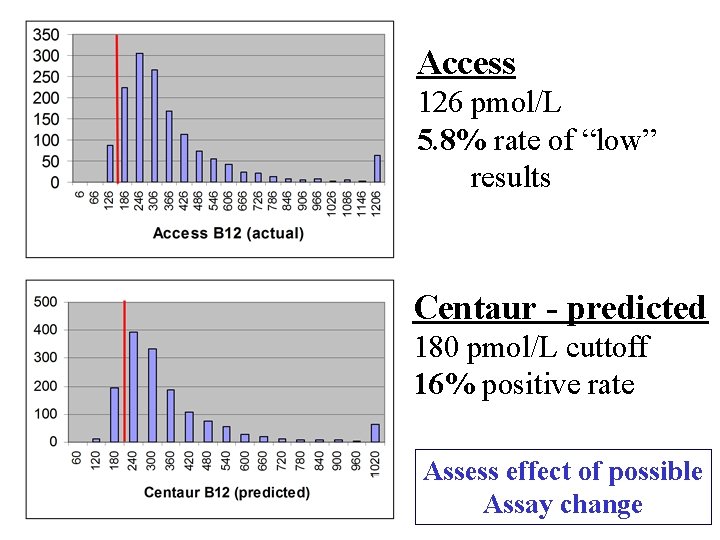
Access 126 pmol/L 5. 8% rate of “low” results Centaur - predicted 180 pmol/L cuttoff 16% positive rate Assess effect of possible Assay change
Data Mining old results • Bhattacharya, LG. Journal of the Biometric Society. 1967; 23: 115 -135. • Example data: Frequency Distribution of the forkal length of the Porgy caught by pair-trawl fishery in the East China Sea.
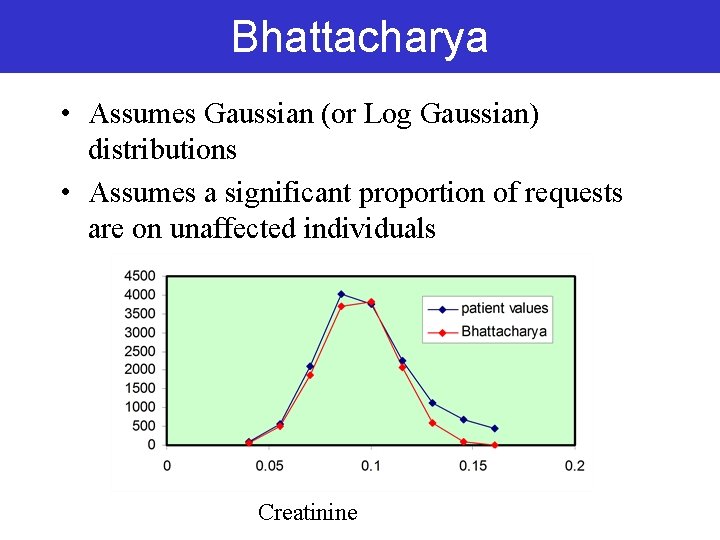
Bhattacharya • Assumes Gaussian (or Log Gaussian) distributions • Assumes a significant proportion of requests are on unaffected individuals Creatinine
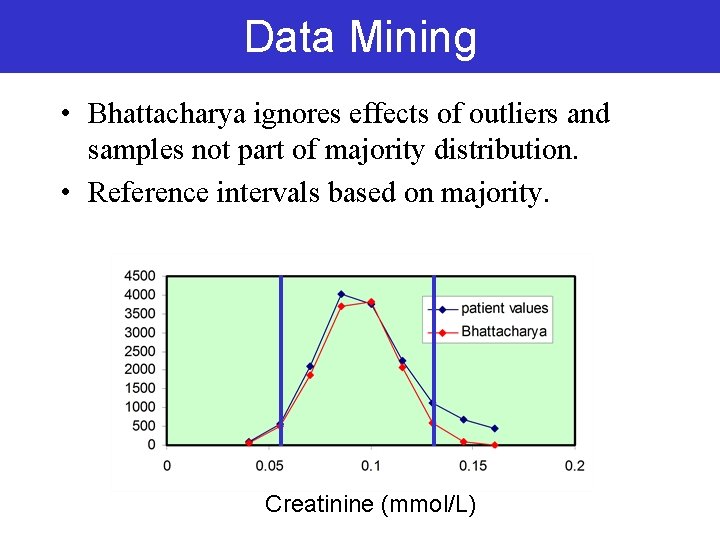
Data Mining • Bhattacharya ignores effects of outliers and samples not part of majority distribution. • Reference intervals based on majority. Creatinine (mmol/L)
Literature • Look for same method • Equivalent population • Sources – Peer-reviewed publications – Gray Literature • Abstracts (eg AACB, AACC, ACB) – Company literature • Product information (PI) • Other
Literature sources • Vital where population reference intervals may be of limited use • Dietary factors • Special groups – Eg paediatrics • Numbers are prohibitive – eg 99 th centile for troponins • Following examples taken from Syd. Path data for creatinine (Roche) and Vitamin B 12 (Centaur)
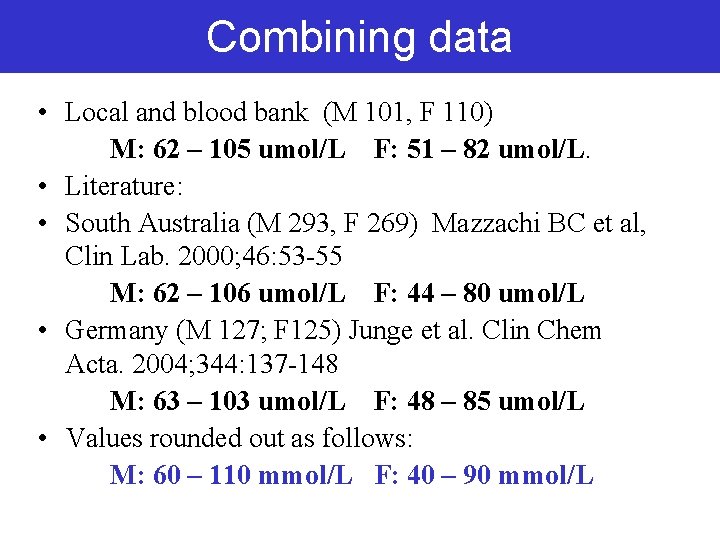
Combining data • Local and blood bank (M 101, F 110) M: 62 – 105 umol/L F: 51 – 82 umol/L. • Literature: • South Australia (M 293, F 269) Mazzachi BC et al, Clin Lab. 2000; 46: 53 -55 M: 62 – 106 umol/L F: 44 – 80 umol/L • Germany (M 127; F 125) Junge et al. Clin Chem Acta. 2004; 344: 137 -148 M: 63 – 103 umol/L F: 48 – 85 umol/L • Values rounded out as follows: M: 60 – 110 mmol/L F: 40 – 90 mmol/L
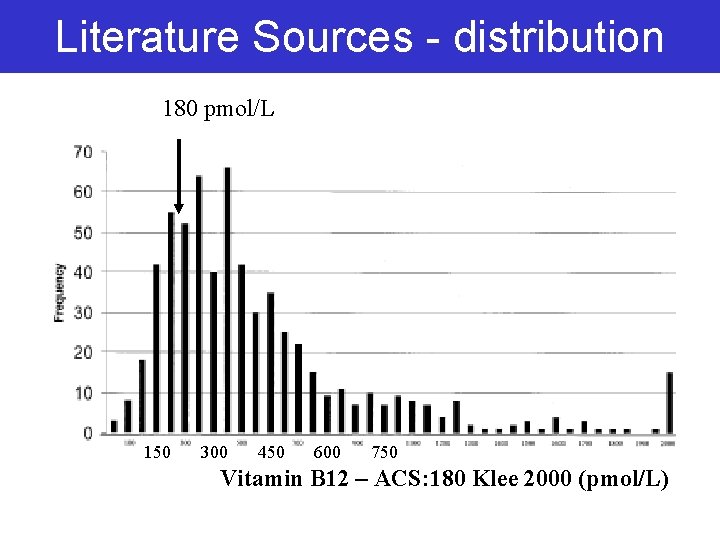
Literature Sources - distribution 180 pmol/L 150 300 450 600 750 Vitamin B 12 – ACS: 180 Klee 2000 (pmol/L)
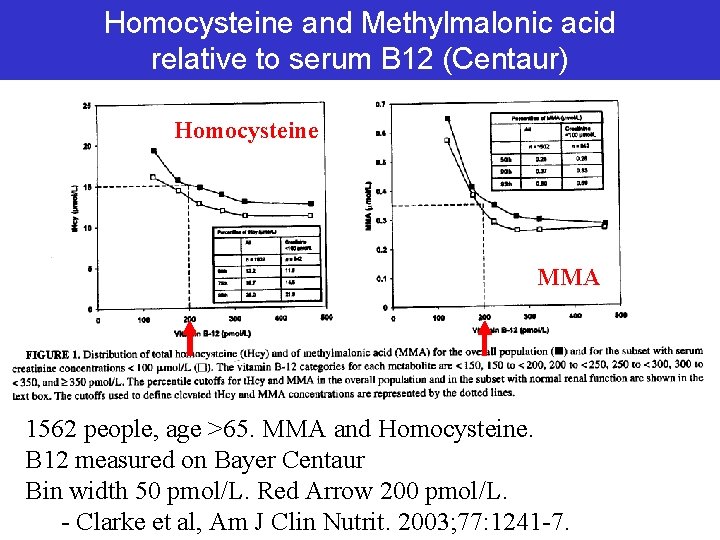
Homocysteine and Methylmalonic acid relative to serum B 12 (Centaur) Homocysteine MMA 1562 people, age >65. MMA and Homocysteine. B 12 measured on Bayer Centaur Bin width 50 pmol/L. Red Arrow 200 pmol/L. - Clarke et al, Am J Clin Nutrit. 2003; 77: 1241 -7.
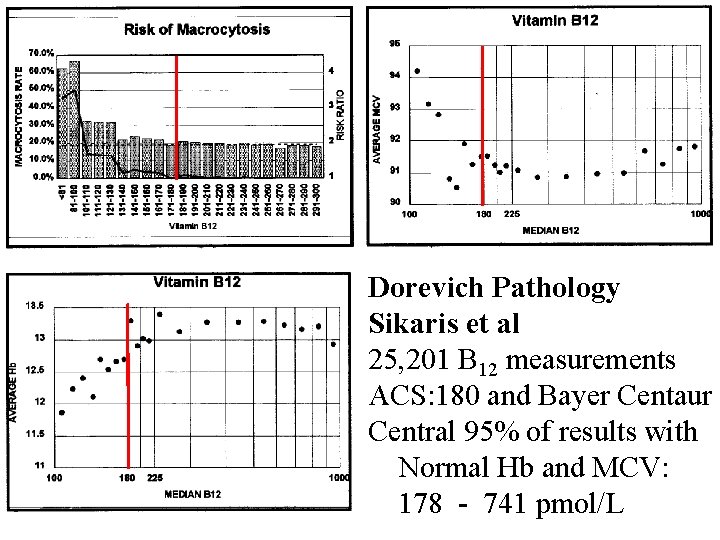
Dorevich Pathology Sikaris et al 25, 201 B 12 measurements ACS: 180 and Bayer Centaur Central 95% of results with Normal Hb and MCV: 178 - 741 pmol/L
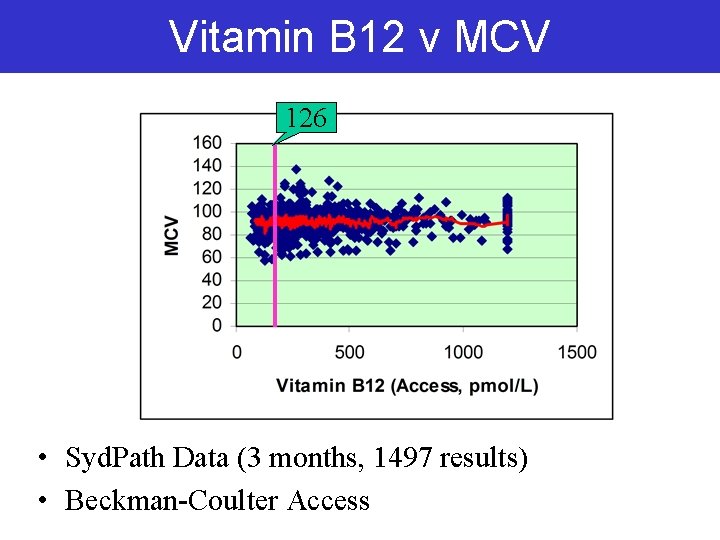
Vitamin B 12 v MCV 126 • Syd. Path Data (3 months, 1497 results) • Beckman-Coulter Access
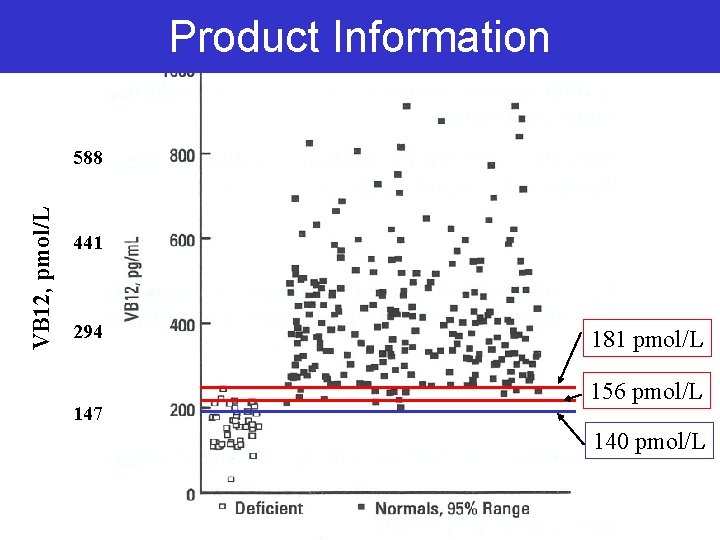
Product Information VB 12, pmol/L 588 441 294 147 181 pmol/L 156 pmol/L 140 pmol/L
Centaur Vitamin B 12 • 6 studies using Centaur or ACS: 180 • • Product information 3 x refereed publications 1 x AACB abstract 1 x local study (NZ) • Data combined to make reference interval – Deficient <120 pmol/L – Indeterminate 120 – 180 pmol/L – Replete >180 pmol/L
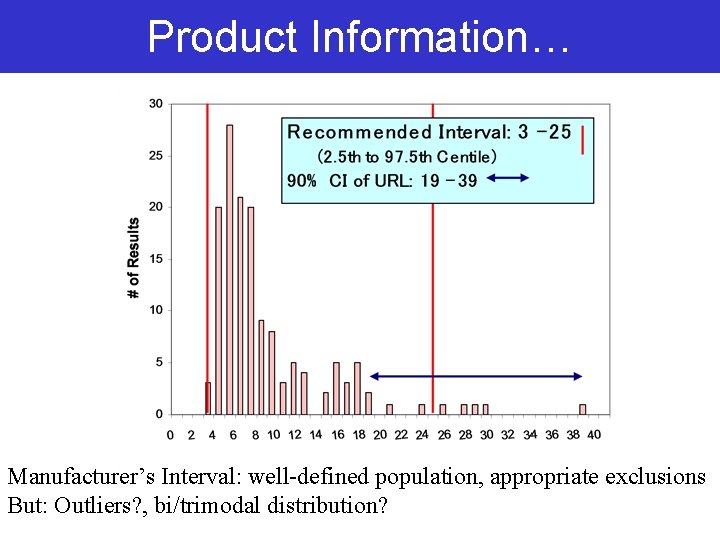
Product Information… Manufacturer’s Interval: well-defined population, appropriate exclusions But: Outliers? , bi/trimodal distribution?
Other laboratories • If someone has done the work, and uses the same method, review their work and apply the intervals. • Need to verify assay bias. • Collaborative effort between several labs with the same method may be a powerful method of setting reference intervals – Spanish Group – NORIP: http: //wip. furst. no/norip/
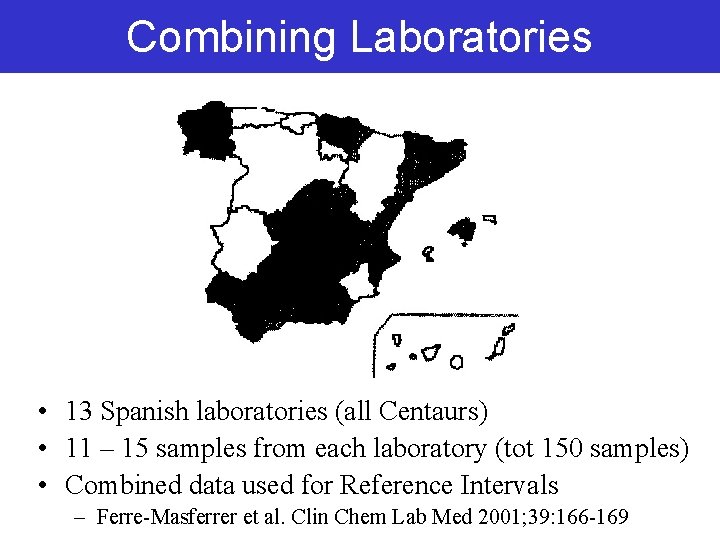
Combining Laboratories • 13 Spanish laboratories (all Centaurs) • 11 – 15 samples from each laboratory (tot 150 samples) • Combined data used for Reference Intervals – Ferre-Masferrer et al. Clin Chem Lab Med 2001; 39: 166 -169
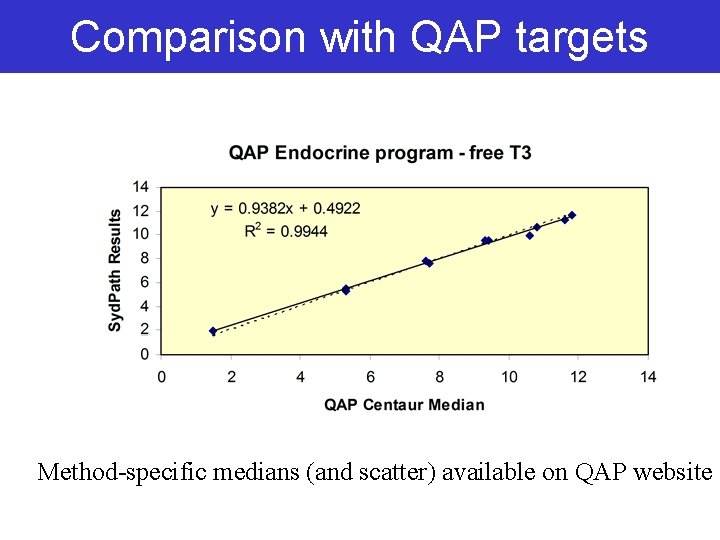
Other Sources: accuracy base • In order to share method-specific literature need to ensure assay accuracy. • “Is my Bloggs method for X working the same as everyone else’s Blogg’s method? ” • QAP results – measure QAP samples – look up results for method group • QC material target values • Shared samples
Comparison with QAP targets Method-specific medians (and scatter) available on QAP website
Plea to manufacturers. . . • Searching refereed literature by trade names can be difficult – ie Abbott, Elecsys, Immulite, Vitros are terms that are not often searchable in Medline, pubmed etc • If companies keep a resource library of information it would be very useful. • Note “google Scholar” can be useful – http: //scholar. google. com
Clinical Input • Previous slides about Vitamin B 12 are taken from a presentation to haematologists at St Vincent’s Hospital • Actively seeking their input on decision points • Allows inclusiveness and practical input
Putting it all together • Different sources will give (slightly) different values. • Judgement is required to combine data • Other factors include: – Precision of intervals – Long term precision of assay(s) – Biological variation – Rounding for ease of memory – Partitioning
Implementing • Recommend temporary footnote • eg change in method and change intervals, see lab for further details • Make further details available if needed – source document (NATA) – Handout – Website
Conclusions • A new method is a good time to review reference intervals • Uncritical transfer of old intervals is bad practice • Many sources of information can be used • Judgement is required for final decision • Working with other labs may be of great benefit