
RECURRENCE OF RENOSPLENIC ENTRAPMENT FOLLOWING RENOSPLENIC SPACE ABLATION

RECURRENCE OF RENOSPLENIC ENTRAPMENT FOLLOWING RENOSPLENIC SPACE ABLATION IN A STALLION Emily A. Barrell, MS Mentors: Dean A. Hendrickson, DVM, DACVS; J. Lacy Kamm, DVM Colorado State University Veterinary Teaching Hospital Fort Collins, Colorado

SIGNALMENT AND HISTORY • “Christian Geronimo” • Seven-year-old Appaloosa-Trakehner stallion • Previous history of renosplenic entrapment and laparoscopic renosplenic space ablation 7 years prior as a weanling • Referred in October 2009 for signs of colic: -Inappetance -Rolling -Decreased defecation • Non-responsive to analgesia as per r. DVM (xylazine, butorphanol, buscopan, ephedrine)
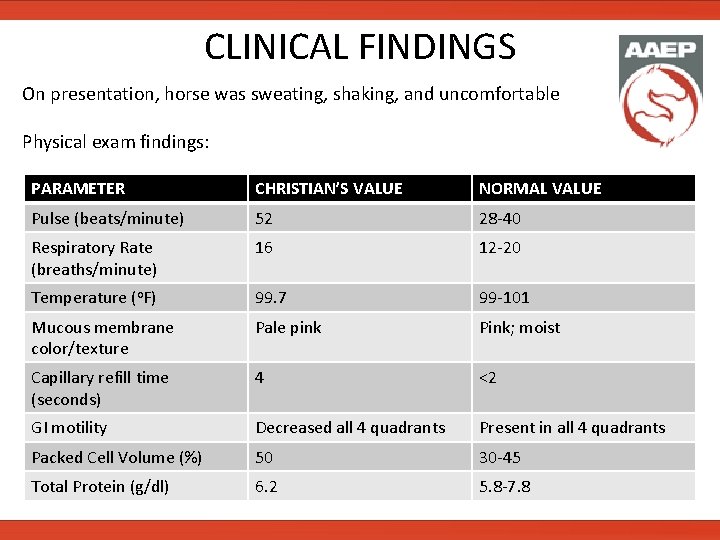
CLINICAL FINDINGS On presentation, horse was sweating, shaking, and uncomfortable Physical exam findings: PARAMETER CHRISTIAN’S VALUE NORMAL VALUE Pulse (beats/minute) 52 28 -40 Respiratory Rate (breaths/minute) 16 12 -20 Temperature (o. F) 99. 7 99 -101 Mucous membrane color/texture Pale pink Pink; moist Capillary refill time (seconds) 4 <2 GI motility Decreased all 4 quadrants Present in all 4 quadrants Packed Cell Volume (%) 50 30 -45 Total Protein (g/dl) 6. 2 5. 8 -7. 8
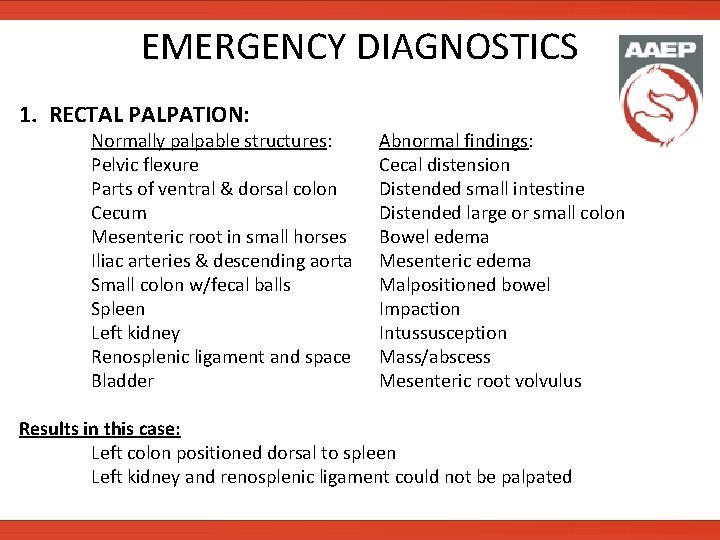
EMERGENCY DIAGNOSTICS 1. RECTAL PALPATION: Normally palpable structures: Pelvic flexure Parts of ventral & dorsal colon Cecum Mesenteric root in small horses Iliac arteries & descending aorta Small colon w/fecal balls Spleen Left kidney Renosplenic ligament and space Bladder Abnormal findings: Cecal distension Distended small intestine Distended large or small colon Bowel edema Mesenteric edema Malpositioned bowel Impaction Intussusception Mass/abscess Mesenteric root volvulus Results in this case: Left colon positioned dorsal to spleen Left kidney and renosplenic ligament could not be palpated
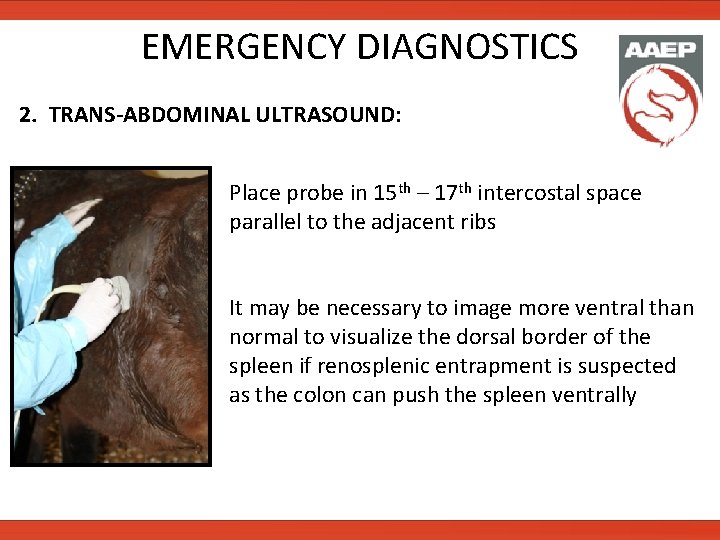
EMERGENCY DIAGNOSTICS 2. TRANS-ABDOMINAL ULTRASOUND: Place probe in 15 th – 17 th intercostal space parallel to the adjacent ribs It may be necessary to image more ventral than normal to visualize the dorsal border of the spleen if renosplenic entrapment is suspected as the colon can push the spleen ventrally
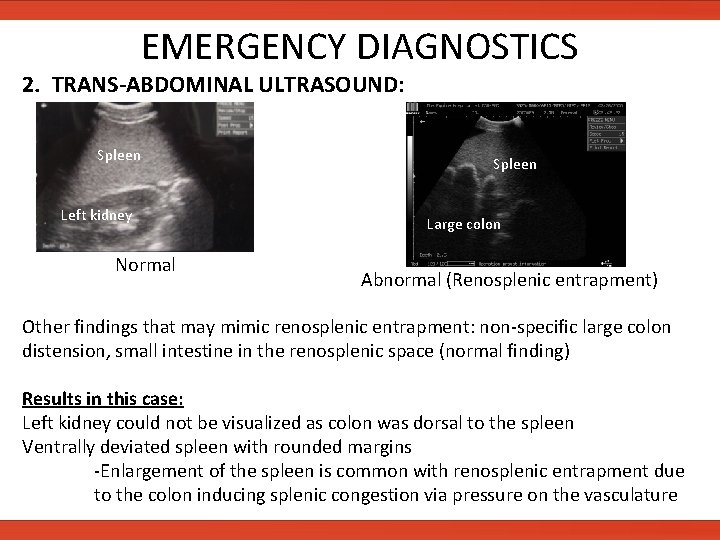
EMERGENCY DIAGNOSTICS 2. TRANS-ABDOMINAL ULTRASOUND: Spleen Left kidney Normal Spleen Large colon Abnormal (Renosplenic entrapment) Other findings that may mimic renosplenic entrapment: non-specific large colon distension, small intestine in the renosplenic space (normal finding) Results in this case: Left kidney could not be visualized as colon was dorsal to the spleen Ventrally deviated spleen with rounded margins -Enlargement of the spleen is common with renosplenic entrapment due to the colon inducing splenic congestion via pressure on the vasculature
EMERGENCY DIAGNOSTICS 3. ABDOMINOCENTESIS: Normal values: TP < 2. 0 g/dl; WBC < 5000 cells/µl; Clear, straw-yellow color Common abnormalities: Large intestinal obstruction: TP > 2. 0; WBC variable Strangulating small intestinal lesion: TP > 4. 0; WBC variable; serosanguinous color Renosplenic entrapment: TP and WBC often normal →Increased TP or WBCs can indicate longer duration of entrapment and may make surgical correction more likely Results in this case: Abdominal fluid slightly serosanguinous TP = 1. 3 g/dl
PROBLEM LIST • Pale mucus membranes • Delayed CRT Hypovolemia • ↑ PCV • Tachycardia • Ventrally deviated spleen* • ↓ Gut sounds* • Colic/Abdominal pain* • Displaced left colon* • Non-visible left kidney on ultrasound* * Denote most significant problems
DIFFERENTIAL DIAGNOSES Moderate Abdominal Pain - Non-strangulating obstruction - Colitis - Displaced colon Displaced left colon -Renosplenic entrapment -Gas colic -Large colon torsion Ventrally deviated spleen - Renosplenic entrapment Non-visible left kidney on u/s - Renosplenic entrapment - Fluid- or gas-distended large colon - Small intestine or small colon in the renosplenic space ↓Gut sounds - Reduced feed intake - Ileus - Obstruction
DIAGNOSIS Based on: Rectal exam findings Ultrasound imaging Abdominocentesis Clinical presentation Top differential is RENOSPLENIC ENTRAPMENT, despite a previous renosplenic space ablation procedure Prior to this case, recurrence of renosplenic entrapment following a renosplenic space ablation has NOT been reported

POSSIBLE CAUSES OF FAILURE Possible causes of failure of the initial renosplenic space ablation: • Young age of colt at time of first procedure -Shape or size of renosplenic space may change with age, causing the ablation to fail • Inadequate suture bite size and spacing through the visceral peritoneum and splenic capsule -Too much tension along suture line may cause the ablation to fail
MEDICAL TREATMENT OPTIONS Phenylephrine - Alpha adrenergic agonist - Causes splenic contraction - Up to 90% success rate in stable patients - Dose: 8 -16 mg/450 kg in 1 L saline given over 15 minutes - Heart rate and rhythm should be monitored during administration - Can be repeated several times CAUTION: Do not administer to hypovolemic patients as reflex bradycardia may ensue and result in hypoperfusion
MEDICAL TREATMENT OPTIONS Exercise Rolling - Jogging for 15 -30 minutes to shake the colon loose from the renosplenic space -Repeat rectal exam after exercise to evaluate position of the colon -General anesthesia is used to place horse in dorsal recumbency while abdomen is vigorously balloted -Horse can then be placed into left lateral, balloted again, and rolled to right lateral recumbency for recovery ROLLING VIDEO COMPLICATIONS: Cecal or colonic volvulus (iatrogenic) Cecal or colonic rupture Persistence or worsening of left displacement

SURGICAL TREATMENT OPTIONS 1. Ventral midline celiotomy Advantages: Access to majority of anatomy Correction of unexpected/undiagnosed findings Disadvantages: Requires general anesthesia Longer convalescent period Increased cost to owner When to use: Evidence of intestinal compromise Evidence of other intestinal lesions Inability to perform a rectal exam pre-operatively Inability to adequately control pain without general anesthesia

SURGICAL TREATMENT OPTIONS 2. Standing flank laparotomy Advantages: Avoidance of general anesthesia Direct access to affected anatomy Option for simultaneous closure of renosplenic space Reduced convalescent period Reduced cost to owner Disadvantages: Limited access to other anatomy in the case of incorrect diagnosis or multiple lesions
METHODS FOR PERMANENT CORRECTION • Colopexy • Large colon resection • Surgical closure of the renosplenic space →Open vs. laparoscopic →Suture closure vs. mesh placement

THERAPEUTIC PLAN 1. Phenylephrine + exercise →Horse was administered phenylephrine and jogged, but rectal exam showed no resolution of entrapment 2. Rolling and abdominal ballottement under general anesthesia →Horse was anesthetized and placed in dorsal recumbency with hindlimbs hoisted. Abdomen was balloted and horse was placed in left lateral recumbency for recovery. Rectal palpation following recovery confirmed resolution of the entrapment 3. Surgical correction if necessary →Unnecessary in this case 4. Repeat renosplenic space ablation →Scheduled approximately 2 weeks after discharge
THERAPEUTIC PLAN Repeat laparoscopic renosplenic space ablation Laparoscopy sites – left flank: Instrument portal Laparoscope portal 17 th Intercostal space, level with dorsal tuber coxae Paralumbar fossa midway between 18 th rib and tuber coxae Large-bore cannula portal 5 cm ventral to instrument portal Cranial Caudal
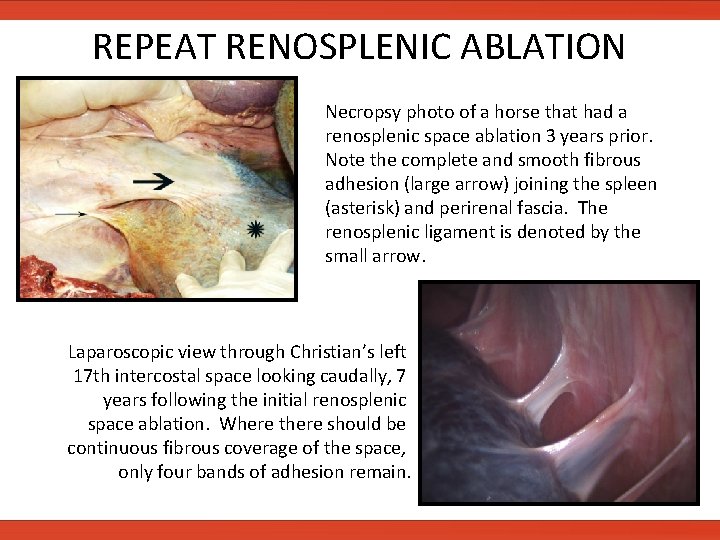
REPEAT RENOSPLENIC ABLATION Necropsy photo of a horse that had a renosplenic space ablation 3 years prior. Note the complete and smooth fibrous adhesion (large arrow) joining the spleen (asterisk) and perirenal fascia. The renosplenic ligament is denoted by the small arrow. Laparoscopic view through Christian’s left 17 th intercostal space looking caudally, 7 years following the initial renosplenic space ablation. Where there should be continuous fibrous coverage of the space, only four bands of adhesion remain.
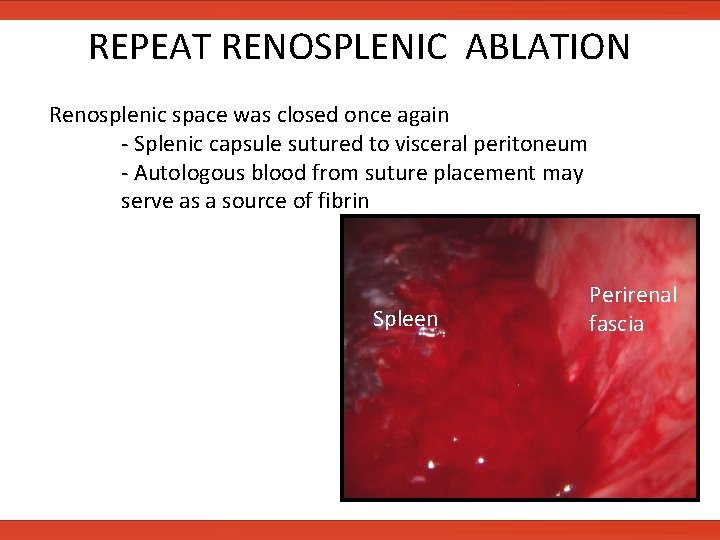
REPEAT RENOSPLENIC ABLATION Renosplenic space was closed once again - Splenic capsule sutured to visceral peritoneum - Autologous blood from suture placement may serve as a source of fibrin Spleen Perirenal fascia

OUTCOME “Christian” discharged from the hospital and recovered well at home Five months following the procedure owner reports no recurrences or complications

FURTHER READING/REFERENCES 1. Epstein KL, Parente EJ. Laparoscopic obliteration of the nephrosplenic space using propylene mesh in five horses. Vet Surg. 2006; 35: 431 -437. 2. Farstvedt E, Hendrickson DA. Laparoscopic closure of the nephrosplenic space for prevention of recurrent nephrosplenic entrapment of the ascending colon. Vet Surg. 2005; 34: 642 -645. 3. Mariën T. Laparoscopic closure of the nephrosplenic space in the standing horse. In: Equine diagnostic and surgical laparoscopy. Ed: Fischer AT; W. B. Saunders Company, Philadelphia. 2002. Pp. 265 -271. 4. Mueller POE, Moore JN. Gastrointestinal emergencies and other causes of colic. In: Equine emergencies: treatment and procedures, 3 rd ed. Ed: Orsini JA, Divers TJ; Saunders Elsevier, Saint Louis. 2008. 5. Rakestraw PC, Hardy J. Large intestine. In: Equine surgery, 3 rd ed. Ed: Auer JA, Stick JA ; Saunders Elsevier, Saint Louis. 2006. Pp. 453 -456.

ACKNOWLEDGEMENTS Photographs courtesy of Dr. Dean Hendrickson, Dr. Diana Hassel, Ms. Alisa Blake, and Mr. Ron Wahl. Thanks to Dr. Hendrickson, Dr. Lacy Kamm, and Dr. Hassel for all their time and assistance
- Slides: 23