
REABILITAO CARDIOPULMONAR E METABLICA Tales de Carvalho Doutor

REABILITAÇÃO CARDIOPULMONAR E METABÓLICA Tales de Carvalho Doutor pela Faculdade de Medicina da USP (Área de Patologia); Professor do Centro de Ciências da Saúde e do Esporte (Univ. do Estado de Santa Catarina); Diretor da Clínica de Prevenção e Reabilitação CARDIOSPORT; Membro da diretoria do DERC-SBC; Ex-presidente da Sociedade Brasileira de Medicina do Esporte.

Arquivos Brasileiros de Cardiologia. 2006; 83 (5): 448 -52

Arquivos Brasileiros de Cardiologia. 2006; 83 (5): 448 -52

Hambrecht R et al. Percutaneous coronary angioplasty compared with exercise training in patients with stable coronary artery disease: a randomized trial. Circulation. 2004 23; 109(11): 1371 -8. üTreinamento físico vs Angioplastia com stent; üDesfechos: sintomatologia, ausência de angina ao esforço, perfusão miocárdica, custo-efetividade e aspectos clínicos combinados (morte de causa cardíaca, AVC, CRM, ATC, IAM, piora objetiva da angina com hospitalização); ü 101 homens, após cinecoronariografia de rotina, aleatoriamente designados para 12 meses de EXERCÍCIO ou ATC.
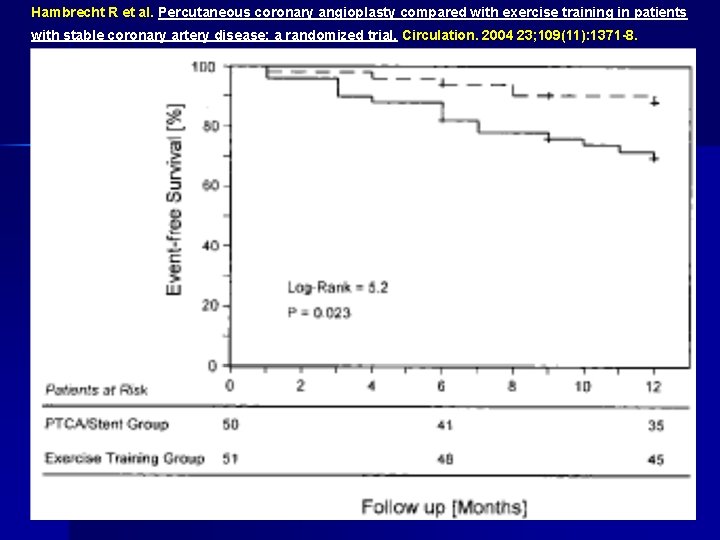
Hambrecht R et al. Percutaneous coronary angioplasty compared with exercise training in patients with stable coronary artery disease: a randomized trial. Circulation. 2004 23; 109(11): 1371 -8.

Hambrecht R et al. Percutaneous coronary angioplasty compared with exercise training in patients with stable coronary artery disease: a randomized trial. Circulation. 2004 23; 109(11): 1371 -8. RESULTADOS üLivre de eventos exercício 88% versus ATC 70% (P=0, 023) üIncremento de VO 2 mx exercício (+16%) vs ATC (P<0, 001) üGasto ATC $US 6. 956 vs exercício $US 3. 429 (P<0, 001)

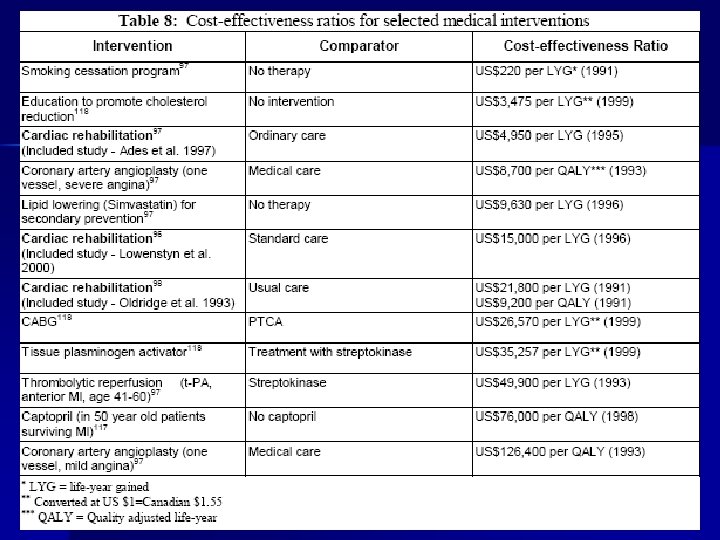
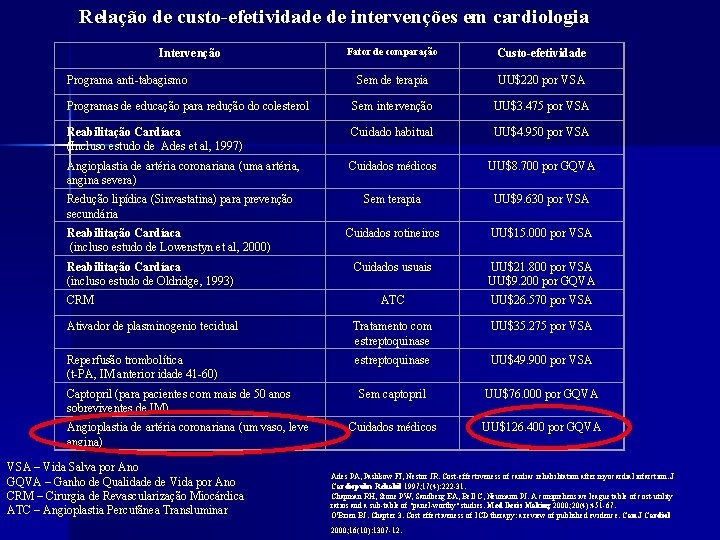
Relação de custo-efetividade de intervenções em cardiologia Fator de comparação Custo-efetividade Sem de terapia UU$220 por VSA Programas de educação para redução do colesterol Sem intervenção UU$3. 475 por VSA Reabilitação Cardíaca (Incluso estudo de Ades et al, 1997) Cuidado habitual UU$4. 950 por VSA Angioplastia de artéria coronariana (uma artéria, angina severa) Cuidados médicos UU$8. 700 por GQVA Redução lipídica (Sinvastatina) para prevenção secundária Sem terapia UU$9. 630 por VSA Cuidados rotineiros UU$15. 000 por VSA Cuidados usuais UU$21. 800 por VSA UU$9. 200 por GQVA ATC UU$26. 570 por VSA Ativador de plasminogenio tecidual Tratamento com estreptoquinase UU$35. 275 por VSA Reperfusão trombolítica (t-PA, IM anterior idade 41 -60) estreptoquinase UU$49. 900 por VSA Sem captopril UU$76. 000 por GQVA Cuidados médicos UU$126. 400 por GQVA Intervenção Programa anti-tabagismo Reabilitação Cardíaca (incluso estudo de Lowenstyn et al, 2000) Reabilitação Cardíaca (incluso estudo de Oldridge, 1993) CRM Captopril (para pacientes com mais de 50 anos sobreviventes de IM) Angioplastia de artéria coronariana (um vaso, leve angina) VSA – Vida Salva por Ano GQVA – Ganho de Qualidade de Vida por Ano CRM – Cirurgia de Revascularização Miocárdica ATC – Angioplastia Percutãnea Transluminar Ades PA, Pashkow FJ, Nestor JR. Cost-effectiveness of cardiac rehabilitation after myocardial infarction. J Cardiopulm Rehabil 1997; 17(4): 222 -31. Chapman RH, Stone PW, Sandberg EA, Bell C, Neumann PJ. A comprehensive league table of cost-utility ratios and a sub-table of "panel-worthy" studies. Med Decis Making 2000; 20(4): 451 -67. O'Brien BJ. Chapter 3. Cost effectiveness of ICD therapy: a review of published evidence. Can J Cardiol 2000; 16(10): 1307 -12.
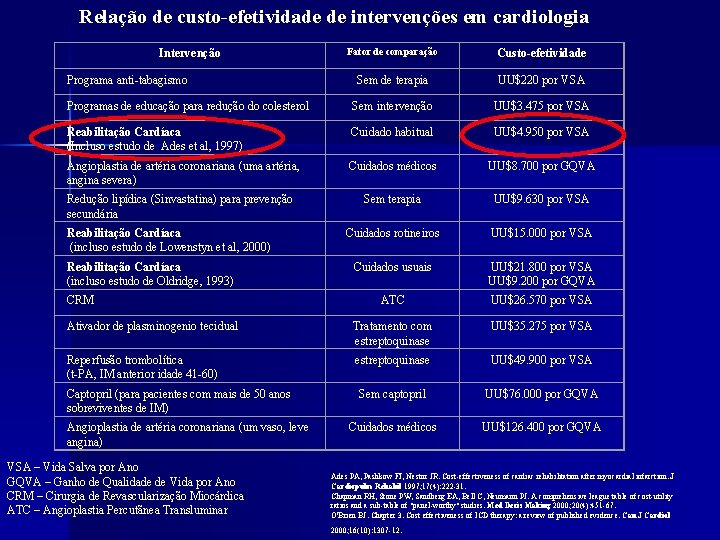
Relação de custo-efetividade de intervenções em cardiologia Fator de comparação Custo-efetividade Sem de terapia UU$220 por VSA Programas de educação para redução do colesterol Sem intervenção UU$3. 475 por VSA Reabilitação Cardíaca (Incluso estudo de Ades et al, 1997) Cuidado habitual UU$4. 950 por VSA Angioplastia de artéria coronariana (uma artéria, angina severa) Cuidados médicos UU$8. 700 por GQVA Redução lipídica (Sinvastatina) para prevenção secundária Sem terapia UU$9. 630 por VSA Cuidados rotineiros UU$15. 000 por VSA Cuidados usuais UU$21. 800 por VSA UU$9. 200 por GQVA ATC UU$26. 570 por VSA Ativador de plasminogenio tecidual Tratamento com estreptoquinase UU$35. 275 por VSA Reperfusão trombolítica (t-PA, IM anterior idade 41 -60) estreptoquinase UU$49. 900 por VSA Sem captopril UU$76. 000 por GQVA Cuidados médicos UU$126. 400 por GQVA Intervenção Programa anti-tabagismo Reabilitação Cardíaca (incluso estudo de Lowenstyn et al, 2000) Reabilitação Cardíaca (incluso estudo de Oldridge, 1993) CRM Captopril (para pacientes com mais de 50 anos sobreviventes de IM) Angioplastia de artéria coronariana (um vaso, leve angina) VSA – Vida Salva por Ano GQVA – Ganho de Qualidade de Vida por Ano CRM – Cirurgia de Revascularização Miocárdica ATC – Angioplastia Percutãnea Transluminar Ades PA, Pashkow FJ, Nestor JR. Cost-effectiveness of cardiac rehabilitation after myocardial infarction. J Cardiopulm Rehabil 1997; 17(4): 222 -31. Chapman RH, Stone PW, Sandberg EA, Bell C, Neumann PJ. A comprehensive league table of cost-utility ratios and a sub-table of "panel-worthy" studies. Med Decis Making 2000; 20(4): 451 -67. O'Brien BJ. Chapter 3. Cost effectiveness of ICD therapy: a review of published evidence. Can J Cardiol 2000; 16(10): 1307 -12.

Georgiou D. Cost-effectiveness analysis of long-term moderate exercise training in chronic heart failure. Am J Cardiol 2001 Apr 15; 87(8): 984 -8 O treinamento físico na ICC prolonga a vida pelo custo de $ US 1. 773 / ano por vida salva

Number Needed to Treat
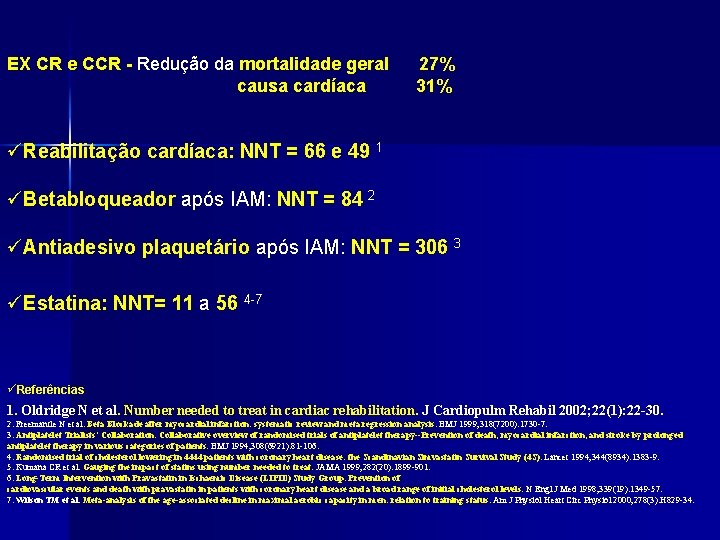
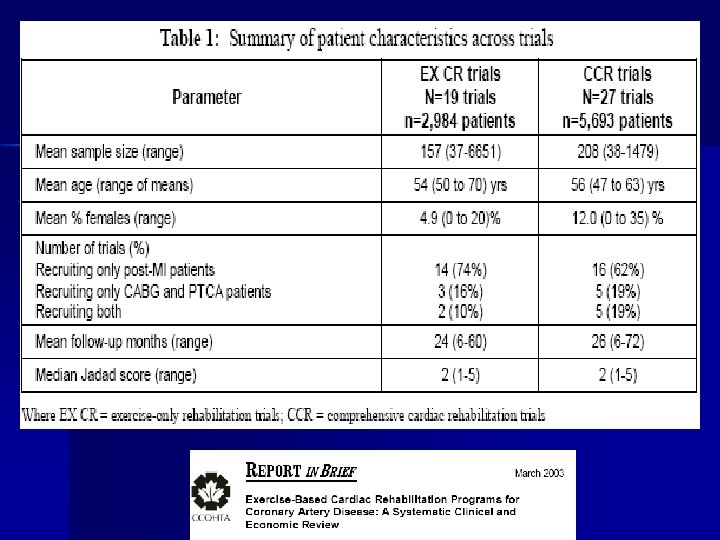
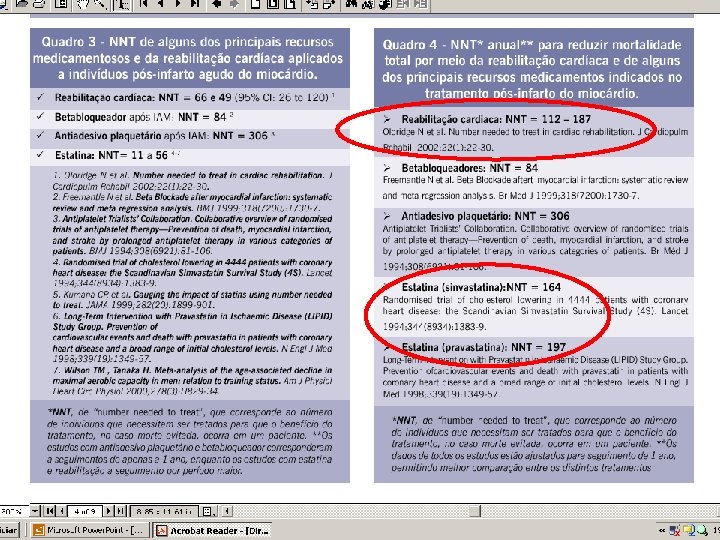
EX CR e CCR - Redução da mortalidade geral causa cardíaca 27% 31% üReabilitação cardíaca: NNT = 66 e 49 1 üBetabloqueador após IAM: NNT = 84 2 üAntiadesivo plaquetário após IAM: NNT = 306 3 üEstatina: NNT= 11 a 56 4 -7 üReferências 1. Oldridge N et al. Number needed to treat in cardiac rehabilitation. J Cardiopulm Rehabil 2002; 22(1): 22 -30. 2. Freemantle N et al. Beta Blockade after myocardial infarction: systematic review and meta regression analysis. BMJ 1999; 318(7200): 1730 -7. 3. Antiplatelet Trialists' Collaboration. Collaborative overview of randomised trials of antiplatelet therapy--Prevention of death, myocardial infarction, and stroke by prolonged antiplatelet therapy in various categories of patients. BMJ 1994; 308(6921): 81 -106. 4. Randomised trial of cholesterol lowering in 4444 patients with coronary heart disease: the Scandinavian Simvastatin Survival Study (4 S). Lancet 1994; 344(8934): 1383 -9. 5. Kumana CR et al. Gauging the impact of statins using number needed to treat. JAMA 1999; 282(20): 1899 -901. 6. Long-Term Intervention with Pravastatin in Ischaemic Disease (LIPID) Study Group. Prevention of cardiovascular events and death with pravastatin in patients with coronary heart disease and a broad range of initial cholesterol levels. N Engl J Med 1998; 339(19): 1349 -57. 7. Wilson TM et al. Meta-analysis of the age-associated decline in maximal aerobic capacity in men: relation to training status. Am J Physiol Heart Circ Physiol 2000; 278(3): H 829 -34.

EX CR e CCR - Redução da mortalidade geral causa cardíaca 27% 31% üReabilitação cardíaca: NNT = 66 e 49 1 üBetabloqueador após IAM: NNT = 84 2 üAntiadesivo plaquetário após IAM: NNT = 306 3 üEstatina: NNT= 11 a 56 4 -7 üReferências 1. Oldridge N et al. Number needed to treat in cardiac rehabilitation. J Cardiopulm Rehabil 2002; 22(1): 22 -30. 2. Freemantle N et al. Beta Blockade after myocardial infarction: systematic review and meta regression analysis. BMJ 1999; 318(7200): 1730 -7. 3. Antiplatelet Trialists' Collaboration. Collaborative overview of randomised trials of antiplatelet therapy--Prevention of death, myocardial infarction, and stroke by prolonged antiplatelet therapy in various categories of patients. BMJ 1994; 308(6921): 81 -106. 4. Randomised trial of cholesterol lowering in 4444 patients with coronary heart disease: the Scandinavian Simvastatin Survival Study (4 S). Lancet 1994; 344(8934): 1383 -9. 5. Kumana CR et al. Gauging the impact of statins using number needed to treat. JAMA 1999; 282(20): 1899 -901. 6. Long-Term Intervention with Pravastatin in Ischaemic Disease (LIPID) Study Group. Prevention of cardiovascular events and death with pravastatin in patients with coronary heart disease and a broad range of initial cholesterol levels. N Engl J Med 1998; 339(19): 1349 -57. 7. Wilson TM et al. Meta-analysis of the age-associated decline in maximal aerobic capacity in men: relation to training status. Am J Physiol Heart Circ Physiol 2000; 278(3): H 829 -34.

FILOSOFIA Reabilitação CV Carlson JJ et al. Program participation, exercise adherence, cardiovascular outocomes, and program cost of traditional versus modified cardiac rehabilitation. Am J Cardiol 2000 Jul 1; 86(1): 17 -23 Protocolo Modificado vs Protocolo Tradicional } Ø Maior aderência Ø Estrutura simplificada Ø Menores custos Ø (US$ 738 a menos / paciente)

Resultado Clínico e Econômico de um Programa de Prevenção e Reabilitação Cardiovascular Dissertação de mestrado Autora: Fabiana Pereira Vecchio Rebelo Orientador: Prof. Dr. Tales de Carvalho Arquivos Brasileiros de Cardiologia. Março/2007

n n n CT : alto ótimo LDL-C : alto desejável HDL-C : baixo alto TG limítrofe : ótimo CT/HDL alto risco : baixo risco Rebelo FPV, Carvalho T et al. Resultado Clínico e Econômico de um Programa de Prevenção e Reabilitação Cardiovascular Arquivos Brasileiros de Cardiologia. Cardiovascular Março, 2007.
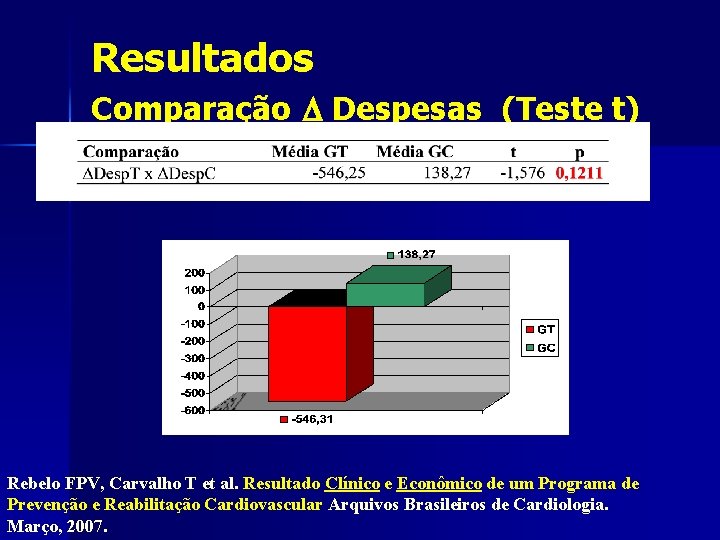
Resultados Comparação Despesas (Teste t) Rebelo FPV, Carvalho T et al. Resultado Clínico e Econômico de um Programa de Prevenção e Reabilitação Cardiovascular Arquivos Brasileiros de Cardiologia. Cardiovascular Março, 2007.

PROJETO RCPM

CPMR SYSTEM COMPONENTES DA AVALIAÇÃO Ø Consulta médica - ênfase para aspectos que possibilitem o encaminhamento com a prescrição de exercício e programa de metas a ser atingido. Ø Exames Laboratoriais: hemograma, colesterol total e frações, triglicerídeos, ácido úrico, glicemia, creatinina, sódio, potássio e parcial de urina. Para os diabéticos serão solicitadas, também, hemoglobina glicosilada e glicemia pós-prandial. Ø Questionários de qualidade de vida: genérico e específicos. Ø Teste Ergométrico: para detecção de eventuais alterações, determinação da aptidão física e verificação da FCmx. Ø Teste da Milha: a ser aplicado nos pacientes sem grande limitação física. Ø Teste de 6 minutos: a ser aplicado nos pacientes com grande limitação física. Ø Teste de Claudicação: a ser aplicado nos pacientes com DAOP. Ø Avaliação Cineantropométrica: determinação do IMC, circunferência do abdome e do quadril. Ø Avaliação da Postura e flexibilidade: para determinar eventuais problemas que possam interferir na prática de exercícios.

CURSOS REGULARES CPMR SYSTEM

SEMINÁRIOS ANUAIS CPMR SYSTEM

ESTÁGIO ATUAL DO PROJETO CPMR SYSTEM

Prevenção e tratamento da cardiopatia isquêmica De Lorgeril M et al. Effect of a mediterranean type of diet on the rate of cardiovascular complications in patients with coronary artery disease. Insights into the cardioprotective effect of certain nutriments. J Am Coll Cardiol 1996 Nov 1; 28(5): 1103 -8. GC 303 e GE 302 indivíduos DIETA DO MEDITERR NEO Follow-up - 27 meses Desfechos principais - morte de causa cardiovascular e IAM secundários - AI, AVC, ICC e tromboembolia

Prevenção e tratamento da cardiopatia isquêmica De Lorgeril M et al. Effect of a mediterranean type of diet on the rate of cardiovascular complications in patients with coronary artery disease. Insights into the cardioprotective effect of certain nutriments. J Am Coll Cardiol 1996 Nov 1; 28(5): 1103 -8. Desfechos principais e secundários GE = RR 0, 24, p < 0. 0001

Prevenção e tratamento da cardiopatia isquêmica De Lorgeril M et al. Effect of a mediterranean type of diet on the rate of cardiovascular complications in patients with coronary artery disease. Insights into the cardioprotective effect of certain nutriments. J Am Coll Cardiol 1996 Nov 1; 28(5): 1103 -8. Desfechos principais e secundários GE = RR 0, 24, p < 0. 0001 REDUZIU A INCIDÊNCIA DE EVENTOS EM 76%

Social support, depression, and mortality during the first year after myocardial infarction Frasure-Smith N et al. Circulation 2000

CONTROLE DO ESTRESSE

Obrigado pela atenção! Tales de Carvalho tales@cardiol. br
- Slides: 31