
PULMONARY FUNCTION TESTS Dr D Rispa Assistant Professor























- Slides: 28
PULMONARY FUNCTION TESTS Dr. D. Rispa Assistant Professor Pharmacy Practice Department
Definition Pulmonary function tests(PFTs) provide objective and quantifiable measures of lung function and are useful in the diagnosis, evaluation and monitoring of respiratory disease. PFTs can assess effectiveness of therapy and detect pulmonary side effects of medication.
Uses of PFT’s v Diagnosis • • Signs and symptoms of respiratory disease Follow up of historical or laboratory findings Disease effects on pulmonary function Drug effects on pulmonary function v. Evaluation • Medical-legal issues • Rehabilitation v. Monitoring • • • Respiratory disease progression Prognosis Occupational or environmental exposure to toxins Therapeutic drug effectiveness Drug effects on pulmonary function
List of PFT’s 1. 2. 3. 4. 5. 6. 7. Spirometry Peak expiratory flow rate Body Plethysmography Carbon monoxide diffusion capacity Airway reactivity tests Six-minute walk test Specialized tests • Infant pulmonary function testing • Carbon monoxide breath test • Sputum inflammatory markers
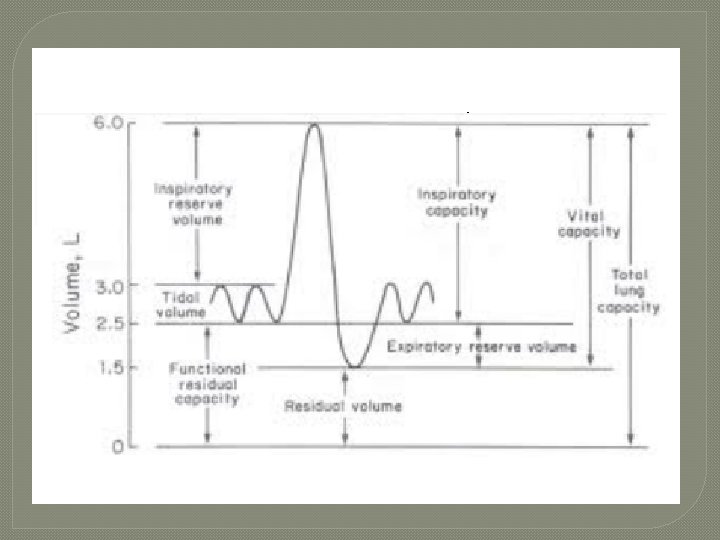
o Tidal Volume(TV): It is the amount of air inhaled and exhaled at rest. It is usually a very small proportion of the lung volume and is infrequently used as a measure of respiratory disease. o Inspiratory Reserve Volume(IRV): the volume measured from the top of the TV(initial point of normal exhalation) to maximal inspiration. o Expiratory Reserve Volume(ERV): During expiration, the volume from the bottom of TV(initial point of normal inhalation) to maximal expiration. o Residual Volume(RV): It is the volume of air left in the lungs at the end of forced expiration to the bottom of ERV.
o Inspiratory Capacity(IC): It is the volume measured from the point of the TV where inhalation normally begins to maximal inspiration. IC = TV + IRV o Functional Residual Capacity(FRC): It is the volume of gas remaining in the lungs at the end of the TV FRV = ERV + RV o Vital Capacity(VC): It is the volume of air that is exhaled as much as possible after inhaling as much as possible. VC = IRV+TV+ERV o Total Lung Capacity(TLC): It is the summation of all the lung volumes. TLC = IRV+TV+ERV+RV
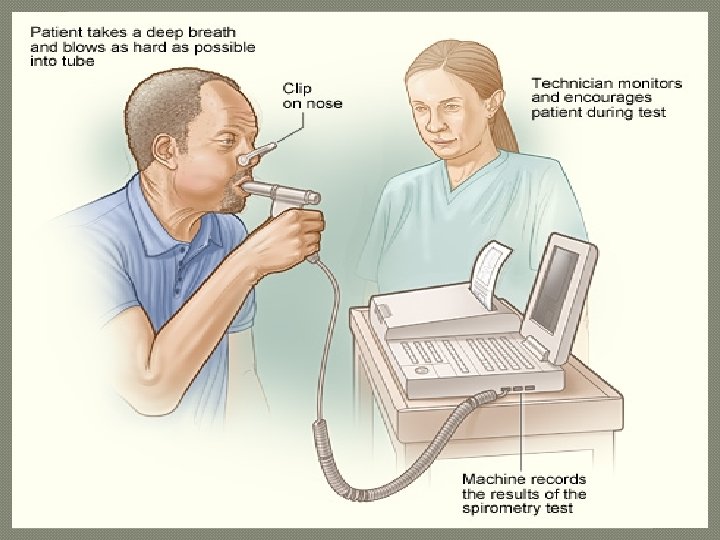
Spirometry Ø Spirometry is a test that measures various aspects of breathing and lung function. Ø It measures how much and how quickly a person can move air in and out of lungs. Ø It is performed by having a person breath into a tube connected to a machine, that measures the amount and flow of inhaled and/or exhaled air. The physical forces of the airflow and the total amount air inhaled and/or exhaled are converted by transducers to electrical signals and displayed on the computer screen.
Ø The instrument used in spirometry is called spirometer Ø Spirometer are of 2 types • Open circuit system – Patient is asked to inhale before inserting the mouthpiece and forcefully exhales. • Closed circuit system – mouthpiece is inserted and several normal breaths be taken before the airflow is measured. Ø A spirometry can be static or dynamic. The term static spirometry identifies a test that is volume based and slow. The term dynamic spirometry identifies a test that is based on time and more dependent on flow and forced.
The parameters measured by spirometry: • Forced vital capacity (FVC). This measures the amount of air you can exhale with force after you inhale as deeply as possible. • Forced expiratory volume (FEV). This measures the amount of air you can exhale with force in one breath. The amount of air you exhale may be measured at 1 second (FEV 1), 2 seconds (FEV 2), or 3 seconds (FEV 3). FEV 1 divided by FVC can also be determined. • Forced expiratory flow 25% to 75%. This measures the air flow halfway through an exhale. • Maximum voluntary ventilation (MVV). This measures the greatest amount of air you can breathe in and out during one minute.
• Slow vital capacity (SVC). This measures the amount of air you can slowly exhale after you inhale as deeply as possible. • Total lung capacity (TLC). This measures the amount of air in your lungs after you inhale as deeply as possible. • Functional residual capacity (FRC). This measures the amount of air in your lungs at the end of a normal exhaled breath. • Residual volume (RV). This measures the amount of air in your lungs after you have exhaled completely. It can be done by breathing in helium or nitrogen gas and seeing how much is exhaled. • Expiratory reserve volume (ERV). This measures the difference between the amount of air in your lungs after a normal exhale (FRC) and the amount after you exhale with force (RV).
Peak Expiratory Flow Rate • The peak expiratory flow rate(PEFR) occurs within the first milliseconds of expiratory flow and is the measure of the maximum airflow rate. This measures how quickly a person can exhale. • PEFR is used during an acute exacerbation of asthma in the emergency room over the use of spirometry, since most patients are unable to perform spirometry during an exacerbation. • Peak flow monitoring is useful to assess asthma medication changes and to identify worsening asthma control. • The PEFR has a wide normal range and is based on the patient’s height, age and gender.
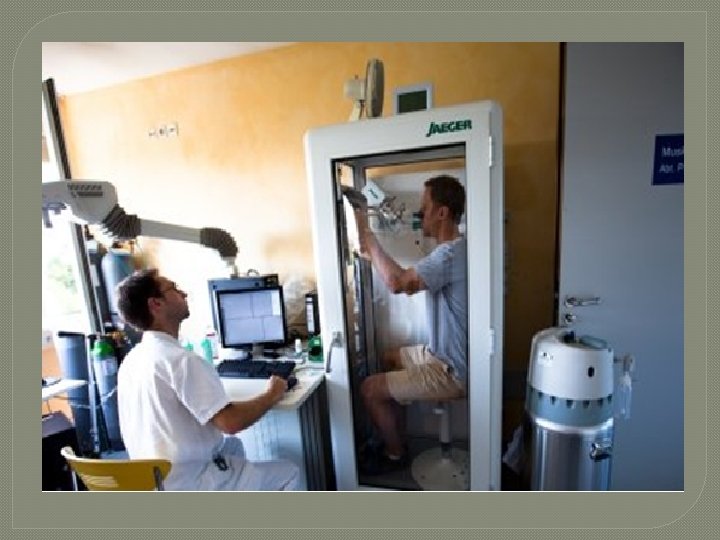
Body Plethysmography • Body plethysmography is a method used to obtain lung volume measures. Lung volume tests indicate the amount of gas contained in the lungs at the various stages of inflation. • The lung volumes and capacities can be determined by body plethysmography, gas dilution and imaging techniques. • Gas dilution – measures ventilated areas Body Plethysmography – measures both ventilated and non ventilated areas. • In body plethysmograhy, a patient sits in an airtight box and is told to inhale and exhale against a closed shutter. Inside, a mouthpiece contains a pressure transducer. This is done to measure the change in pressure within the box during respiration. It senses the intrathoracic pressure generated, when patient rapidly and forcefully puffs against the closed mouthpiece.
By using Boyle’s Law, the functional residual capacity is calculated P x 1 V = P x V 1 2 2 where P = pressure inside box, where patient is seated 1 V = Volume of the box 1 P = Intrathoracic pressure generated by the patient 2 V = Calculated volume of the patient’s thoracic cavity 2 From FRC, the lung volumes and capacities can be calculated.
Body Plethysmography measures • • Tidal volume Inspiratory reserve volume(IRV) Expiratory reserve volume(ERV) Residual Volume(RV) These 4 lung volumes in various combination s make up lung capacities • • Inspiratory capacity(IC) Vital capacity Functional residual capacity(FRC) Total lung capacity(TLC)
Airway Reactivity Tests v Bronchodilator (Reversibility) Test • The diagnostic work-up used in asthma is spirometry with reversibility. • The patient is asked to perform spirometry immediately before and 15 -30 min after the administration of an inhaled short acting beta 2 adrenergic agonist. • The result is an improvement of FEV 1 and/or FVC by atleast 12% and/or 200 ml respectively. • This test is used to diagnose and determine the severity of asthma in patients 5 yrs old or older. • Post bronchodilator FEV 1 is a useful measurement in children to monitor lung growth, since children with asthma may have decreased lung growth. Reversibility studies are particularly useful to help differentiate an asthma patient from the patient with COPD.
v. Bronchoprovocation Challenge Testing(BPT) • BPT measures the reactivity of the airways to known concentrations of agents that induce airway narrowing. • These tests are often referred as challenges as the airways are challenged with increasing doses of a provoking agent until a desired drop in lung function occurs. • Agents used to provoke the lungs include inhaled methacholine, histamine, adenosine and specific allergants. • BPT’s are used to aid in the diagnosis of asthma, when the more common tests(symptom history, spirometry with reversibility) cannot confirm or reject the diagnosis, to evaluate the effects of drug therapy on airway hyper reactivity and for research.
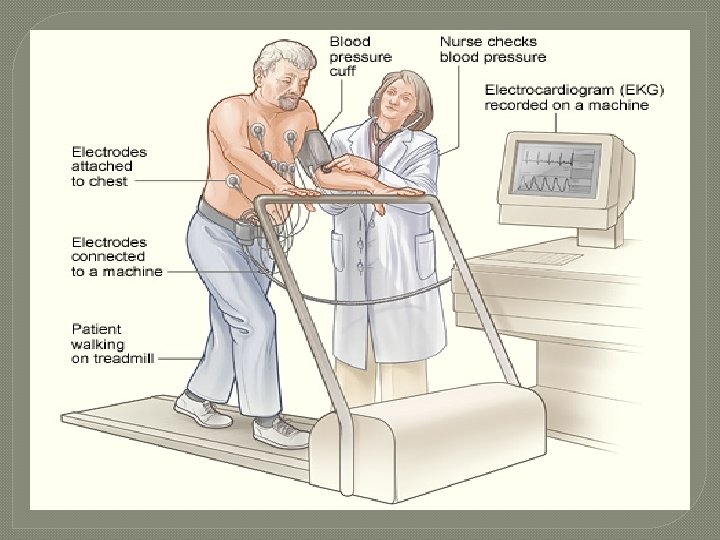
Exercise Challenge Testing Ø Exercise or exertion induced bronchospasm (EIB) occurs in the majority of patients with asthma. The etiology of EIB is thought to be related to the cooling and drying of the airways caused by the rapid breathing during exercise. Exercise challenge testing is used to confirm or rule out EIB and to evaluate the effectiveness of medications used to treat or prevent EIB. Ø Exercise tests are usually done with a motor driven treadmill (with adjustable speed and grade) or the electromagnetically braked cycle ergometer. Heart rate should be monitored throughout the test. Nose clips should be worn and the room air should be dry and cool, to promote water loss from the airway during the exercise test. Ø After the exercise is completed, the patient does serial spirometry at 5 min intervals for 20 -30 minutes. FEV 1 is the primary outcome variable. A 10% or more decrease in FEV 1 from baseline is generally accepted as an abnormal response, in the diagnosis of EIB.
Six-Minute Walk Test(6 MWT) Ø It is a test used to measure the distance a patient can walk on a flat, hard surface in 6 minutes. Ø The results of the test have been correlated to the patient’s quality of life and abilities to complete daily activities. Ø The results of the 6 MWT also helps to predict morbidity and mortality for patients with congestive heart failure, COPD and primary pulmonary hypertension. Ø In case of pulmonary hypertension studies, this test is used to monitor the efficacy of interventions with medications. Ø It is also used to assess the amount of oxygen needed with exertion. Patients with mild – moderate pulmonary disease may have normal oxygen saturation at rest but poor oxygen saturation with exertion. An oxygen saturation of 88% or lower indicates the need for supplemental oxygen.
Diffusion Capacity Tests v These tests measure the ability of gases to cross the alveolarcapillary membrane and are useful in assessing interstitial lung disease. v They measure the per minute transfer of gas from the alveoli to the blood. v Usually carbon monoxide is used because it is normally absent in the lungs and has high affinity to the hemoglobin in RBC. v Abnormal results of this test indicates poor diffusion due to lose of surface area of alveoli or thickening of the alveolar-capillary membrane (due to infiltration of inflammatory/fibrotic cells.
v Diffusion capacity of lungs to carbon monoxide is measured by two methods • Single Breath test • Steady-state test • Single Breath Test Patient inhales a mixture of 0. 3% carbon monoxide, 10%helium and air to vital capacity. After holding breath for 10 sec, the patient exhales fully. The concentration of CO and helium in exhaled air. These concentrations are compared to inhaled concentrations. Mean value for CO is 25 -30 ml/min/mm. Hg. • Steady-State Test Patient breaths a 0. 1%-0. 2% concentration of CO for 5 -6 min. In the final 2 min, the expired gases are collected an arterial blood gas(ABG) is obtained. The concentration of CO, CO 2 and O 2 are measured. By this, the amount of gas transferred across the alveolar membrane per unit time. v These tests are useful for assessing gas exchange.
v Decreased diffusion capacity is seen in diseases that causes alveolar fibrotic changes, which may be idiopathic, drug induced, etc. v DLCO also indicates decreased Hb levels in RBC and pulmonary capillary blood volume. Specialized Tests i. Infant Pulmonary Function testing • This test helps in investigating the development of the lungs, the progression of lung disease and the response to pulmonary treatment. • The equipment used is expensive and requires specialized training and the results are standardized and helps in diagnosing, monitoring and treating lung diseases in infants.
ii. Carbon monoxide breath test • This test is used to identify the smokers. • This is a simple breath test using CO meter, after inhalation the amount of CO in the blood (%COHgb) and body (in ppm). • 10 ppm or less is considered as non-smokers. Clinically 1 -2 ppm is nonsmoker level. iii. Inflammatory Markers Airway inflammation is seen in many airway diseases. Measuring the inflammatory mediators helps in understanding airway disease and its treatment. v Bronchial Alveolar Lavage(BAL) • By bronchoscopy technique, a small amount of buffered, warmed and sterile normal saline is flushed into the airways and then drawn back and analysed for cell components(WBC’s) and proteins(histamine).
v Induced Sputum • Normally it is not possible to produce enough sputum for analysis. Hence sputum is induced. • Patient inhales nebulized hypertonic saline and sputum is collected. Patients are pretreated with short-acting beta 2 adrenergic agonist to prevent airway bronchospasm from hypertonic saline. • So obtained sputum is analyzed for inflammatory markers. v Fractional exhaled nitric oxide (FENO) • Measurement of exhaled concentrations of nitric oxide (NO) is being evaluated as a possible noninvasive test of airway inflammation both in diagnosing and monitoring asthma.