
Proven Health Navigator A Patient Centered Primary Care














- Slides: 17
Proven. Health Navigator: A Patient Centered Primary Care Model Duane Davis, MD, VP, Chief Medical Officer Janet Tomcavage, RN, MSN, VP, Health Services Geisinger Health Plan 1
Geisinger Health System: Danville, Pa Geisinger Clinic: 700 Physicians 41 Community Practice Sites Geisinger Medical Centers - 3 Acute Care Hospitals Geisinger Health Plan: 80 Hospitals 16, 000 Providers 215, 000 Members 2
Better Value for health care spend is the goal 1. Someone needs to be charged with delivering value 2. Medical Home/Chronic care models will cost more 3. Any delivery system changes must deliver savings today 4. Proven Health Navigator is GHS value agent 3
Proven Health Navigator Strategy • Deliver optimal health status for individuals and population based value outcomes via a partnership between PCP’s and GHP that provides 360 degree, 24/7 care and guidance to the practice population. 4
Value is defined as hitting target metrics in the domains of: • Patient experience • Quality outcomes • Efficiency outcomes 5
Proven. Health Navigator Pilot Goals • Improve patient experience and health status • Improve quality and efficiency across the entire spectrum of care • Transform primary care from transaction to value focus • Provide meaningful coordination across all of Health Care 6
The System has five functional components 1. 2. 3. 4. 5. Patient Centered Primary Care Integrated Population Management Care Systems Quality Outcomes Program Value Reimbursement Program 7
1. Patient Centered Primary Care: expanding primary care capabilities • • • Acute and chronic illness care Expanded scope of services Team based care Patient and family engagement & education Rx management program Chronic disease and preventive care optimization via EMR embedded triggers 8
2. Population Management: giving PCP’s ability to see and impact a population • • Predictive Modeling Population profiling and segmentation Health promotion Case Management on site Disease Management education Patient specific intervention plans Remote monitoring Pharmaceutical management 9
3. Value Care Systems: keeping patients in line of sight across the care continuum • Micro-delivery referral systems – High volume specialties – Ancillary services – Radiology, Lab • 360 degree care systems – – Hospital care Home Health SNF’s ER coverage 10
4. Quality Outcomes Program: tracking outcomes and continually improving • Patient Satisfaction Metrics • Chronic Disease Metrics – Diabetes, CHF, Coronary Disease, Hypertension • Preventive Services Metrics – HEDIS Influenza, Pneumoccal 11
5. Value Reimbursement Program: Aligning payment with value outcomes • Fee For Service • Practice transformation stipends - Physician - Infrastructure • Value Based incentive payments – Opportunity based on efficiency results – Payments based on quality metrics 12
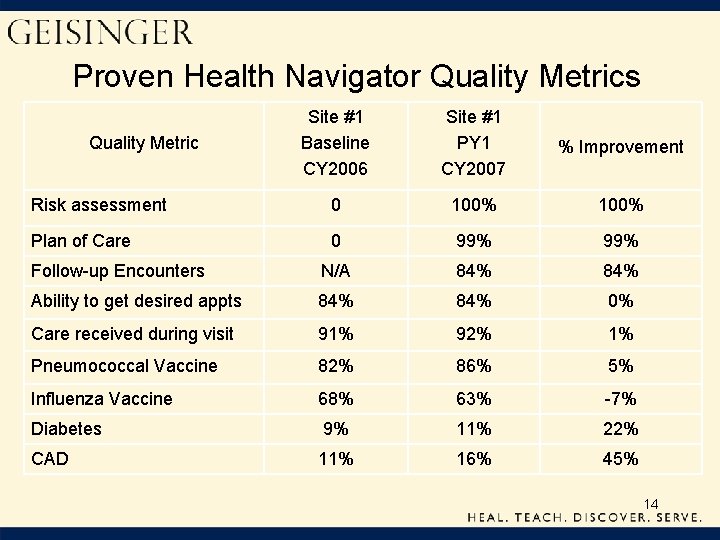
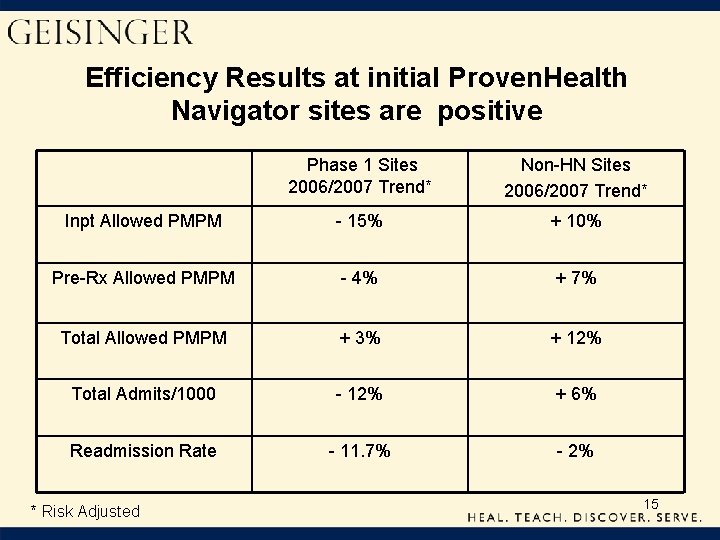
Initial Results are promising • Quality – improved outcomes • Efficiency – improved medical trend 13
Proven Health Navigator Quality Metrics Site #1 Baseline CY 2006 Site #1 PY 1 CY 2007 % Improvement Risk assessment 0 100% Plan of Care 0 99% Follow-up Encounters N/A 84% Ability to get desired appts 84% 0% Care received during visit 91% 92% 1% Pneumococcal Vaccine 82% 86% 5% Influenza Vaccine 68% 63% -7% Diabetes 9% 11% 22% CAD 11% 16% 45% Quality Metric 14
Efficiency Results at initial Proven. Health Navigator sites are positive Phase 1 Sites 2006/2007 Trend* Non-HN Sites 2006/2007 Trend* Inpt Allowed PMPM - 15% + 10% Pre-Rx Allowed PMPM - 4% + 7% Total Allowed PMPM + 3% + 12% Total Admits/1000 - 12% + 6% Readmission Rate - 11. 7% - 2% * Risk Adjusted 15
Experience to date has led to 5 implementation priorities • • • Predictive Modeling to stratify Population Make Case Manager key member of care team Manage transitions of care – post acute hospital Manage SNF admissions Use EPIC reporting and decision support to drive QI 16
Q&A Discussion 17