
Procration mdicalement assiste et surveillance biologique Dr Ellen

Procréation médicalement assistée et surveillance biologique Dr. Ellen Anckaert Laboratorium klinische Chemie en Radioimmunologie Sector Hormonologie en tumormarkers Ellen. anckaert@uzbrussel. be

PMA et surveillance biologique l But des analyses hormonales g Avant la PMA g Suivi de la PMA l Aspects analytiques des immunoessais g Hormones stéroïdales g Prolactine g Gonadotrophines l 2 AMH titel 3/6/2021

Classification d’ anovulation Traitement spécifique pour induction d’ ovulation Hypogonadisme Hypogonadotrope (OMS I, 5 -10%) Pompe à Gn. RH si origine hypothalamique LH, FSH ; E 2 Anovulation normogonadotrope (OMS II, surtout OMPK: 70 -85%) LH > FSH; SHBG Citrate de clomifène androgènes Régime/Metformine (obésité, résistance à l’ insuline) Hypogonadisme Hypergonadotrope (OMS III, 10 -30%) Gonadotrophines E 2 LH, FSH Hyperprolactinémie (5 -10%) Agonists de la dopamine 3 titel Prolactine 3/6/2021
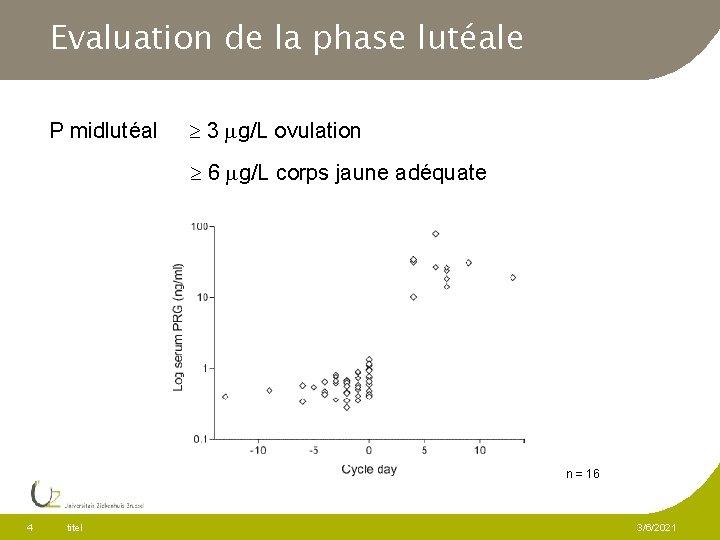
Evaluation de la phase lutéale P midlutéal 3 g/L ovulation 6 g/L corps jaune adéquate n = 16 4 titel 3/6/2021
Classification des patients avant stimulation pour PMA choix de la dose d’FSH • ‘Normo répondeuses’ • • • 5 200 IU/J d’ FSH ‘Mauvaises répondeuses’ • FSH J 3 > 10 -15 IU/L 300 IU/J d’ FSH ‘Hyper répondeuses’ (OMPK) titel FSH J 3 < 10 -15 IU/L FSH N, LH/FSH • 100 IU/J d’ FSH Androgènes • Eviter le Risque de SHO! SHBG 3/6/2021

PMA et surveillance biologique l But des analyses hormonales g Avant la PMA g Suivi de la PMA l Aspects analytiques des immunoessais g Hormones stéroïdales g Prolactine g Gonadotrophines l 6 AMH titel 3/6/2021

Suivi biologique de la superovulation Jour 1(règles) PROTOCOLE LONG AGONISTE Agoniste Gn. RH jour 21 h. MG / FSH h. CG PROTOCOLE ANTAGONISTE h. MG / FSH Antagoniste Gn. RH jour 7 INITIER 7 titel h. CG CROISSANCE FOLLICULAIRE h. CG 3/6/2021

Superovulation pour IVF/ICSI DEMARRER STIMULATION PAR h. MG / FSH UNIQUEMENT SI: 1. LH < 2 IU/L 2. E 2 < 50 ng/L 3. P 4 < 1, 5 µg/L 4. Absence de cystes > 20 mm de diamètre SI NON : augmenter dose et durée de Gn. RHa & attendre de démarrer 8 titel 3/6/2021

Superovulation pour IVF/ICSI ADAPTATION DES DOSES DE GONADOTROPHINES: après 4 jours: E 2 doit être > 100 ng/L E 2 40 -50 % augmentation journalière L’ augmentation journalière d’E 2 de 40 -50 % doit durer de 6 à 8 jours P 4 doit rester < 1. 5 µg/L 9 titel 3/6/2021

Superovulation pour IVF/ICSI DECISION HCG ECHOGRAPHIE: DIAMETRE FOLLICULE 17 mm = OVOCYTE apte d’ atteindre le stade M II après HCG E 2 / follicule large ( 15 mm) : 200 -300 ng/L = follicule mature Busereline/h. MG: Taux normal de maturation 36 h après h. CG (10. 000 U) = 85 % des ovocytes sont métaphase II 10 titel 3/6/2021
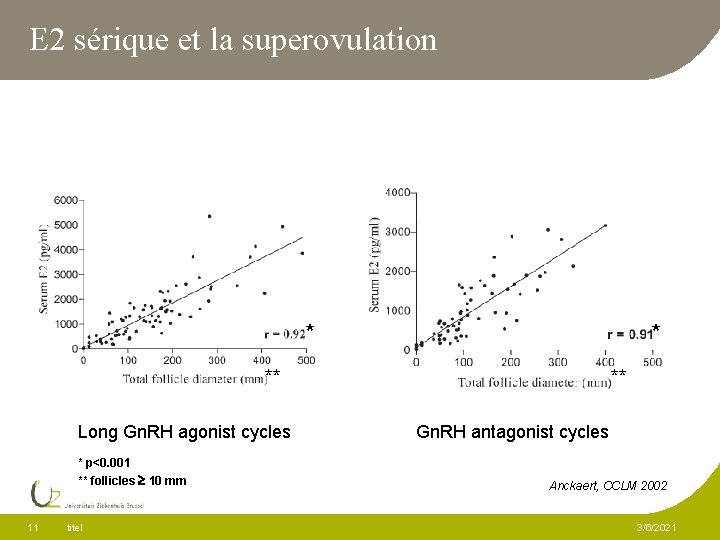
E 2 sérique et la superovulation Serum E 2 (ng/L) 8000 6000 * 4000 * ** ** 2000 Long Gn. RH agonist cycles * p<0. 0010 ** follicles 10 mm 11 titel Gn. RH antagonist cycles 400 Anckaert, CCLM 2002 3/6/2021
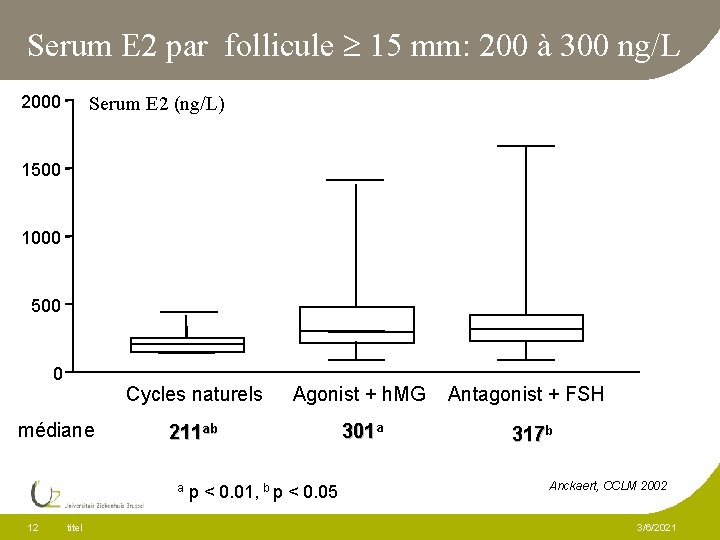
Serum E 2 par follicule 15 mm: 200 à 300 ng/L 2000 Serum E 2 (ng/L) 1500 1000 500 0 Cycles naturels médiane 211 ab a 12 titel Agonist + h. MG Antagonist + FSH 301 a 317 b * p < 0. 01, b p < 0. 05 Anckaert, CCLM 2002 3/6/2021
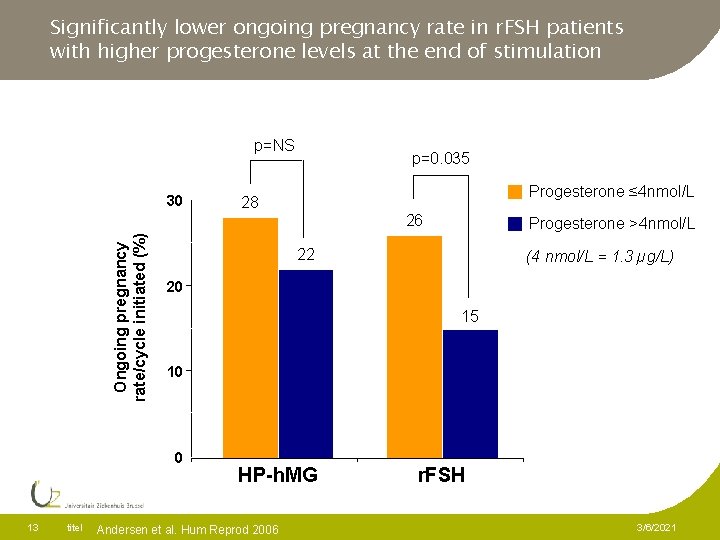
Significantly lower ongoing pregnancy rate in r. FSH patients with higher progesterone levels at the end of stimulation p=NS Ongoing pregnancy rate/cycle initiated (%) 30 p=0. 035 Progesterone ≤ 4 nmol/L 28 25 26 Progesterone >4 nmol/L 22 (4 nmol/L = 1. 3 µg/L) 20 15 15 10 5 0 13 titel HP-h. MG Andersen et al. Hum Reprod 2006 r. FSH 3/6/2021
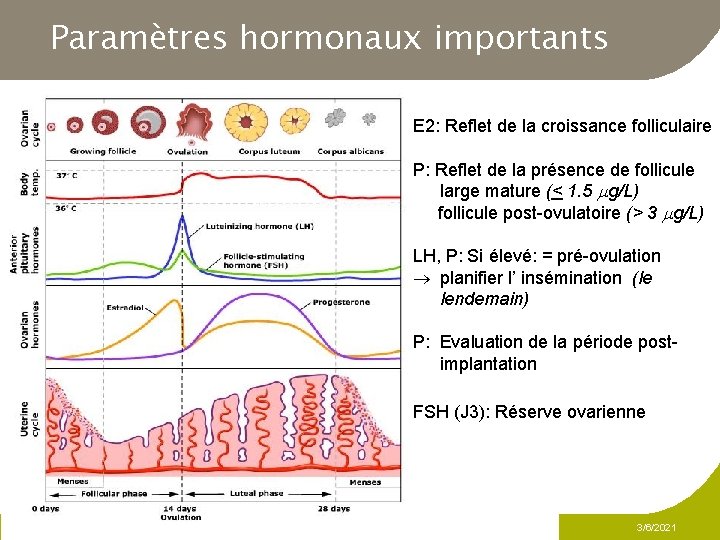
Paramètres hormonaux importants Menstrual cycle © 2007 Up. To. Date® • www. uptodate. com Licensed to Vrije Universiteit Brussel E 2: Reflet de la croissance folliculaire Support. Tag: [WEB 005 -144. 248. 16. 30 -391 C 1 F 9 DA 1 -1540] 14 titel P: Reflet de la présence de follicule large mature (< 1. 5 g/L) follicule post-ovulatoire (> 3 g/L) LH, P: Si élevé: = pré-ovulation planifier l’ insémination (le lendemain) P: Evaluation de la période postimplantation FSH (J 3): Réserve ovarienne 3/6/2021

PMA et surveillance biologique l But des analyses hormonales g Avant la PMA g Suivi de la PMA l Aspects analytiques des immunoessais g Hormones stéroïdales g Prolactine g Gonadotrophines l 15 AMH titel 3/6/2021
Evolution steroid hormone assays Extraction/chromatography RIA specificity, precision Direct RIA • Monoclonal Abs with high specificity • Blocking binding proteins Non-isotopic automated immunoassay precision , high troughput, speed BUT between-method CV 16 titel 3/6/2021
Indications E 2 in ART l Monitoring follicular growth g Ovulation induction g COH for IVF/ICSI Optimalisation assays for: speed, high troughput, good precision at high concentration level l l Cycle irregularity / Anovulation Monitoring down-regulatie Gn. RH analogues Demand high sensitivity assays 17 titel 3/6/2021
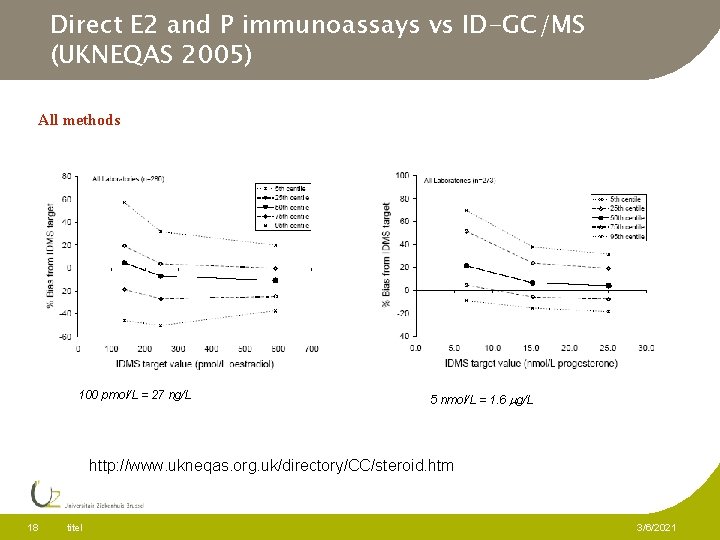
Direct E 2 and P immunoassays vs ID-GC/MS (UKNEQAS 2005) All methods 100 pmol/L = 27 ng/L 5 nmol/L = 1. 6 g/L http: //www. ukneqas. org. uk/directory/CC/steroid. htm 18 titel 3/6/2021
Accuracy and precision of automated E 2 and P assays using native serum samples l l Belgian External Quality Assessment (Institut scientifique de Santé publique) Fresh frozen serum samples g without additives and preservatives no matrix effects g from single donors g pooled serum from pregnant women g target value determined with reference method (IDGCMS) l 6 most frequently used automated methods Coucke W, Hum Reprod, in press 19 titel 3/6/2021
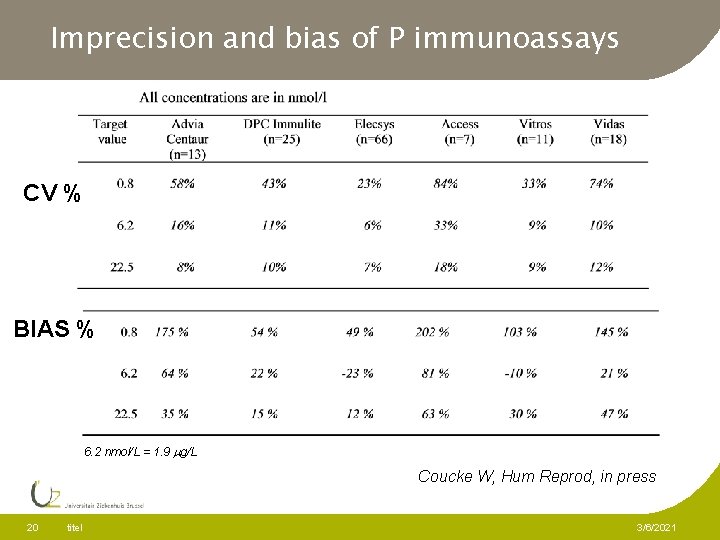
Imprecision and bias of P immunoassays CV % BIAS % 6. 2 nmol/L = 1. 9 g/L Coucke W, Hum Reprod, in press 20 titel 3/6/2021
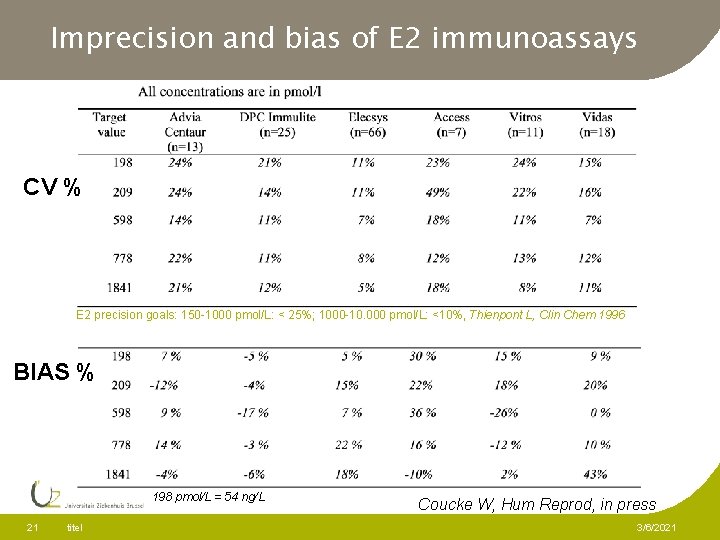
Imprecision and bias of E 2 immunoassays CV % E 2 precision goals: 150 -1000 pmol/L: < 25%; 1000 -10. 000 pmol/L: <10%, Thienpont L, Clin Chem 1996 BIAS % 198 pmol/L = 54 ng/L 21 titel Coucke W, Hum Reprod, in press 3/6/2021
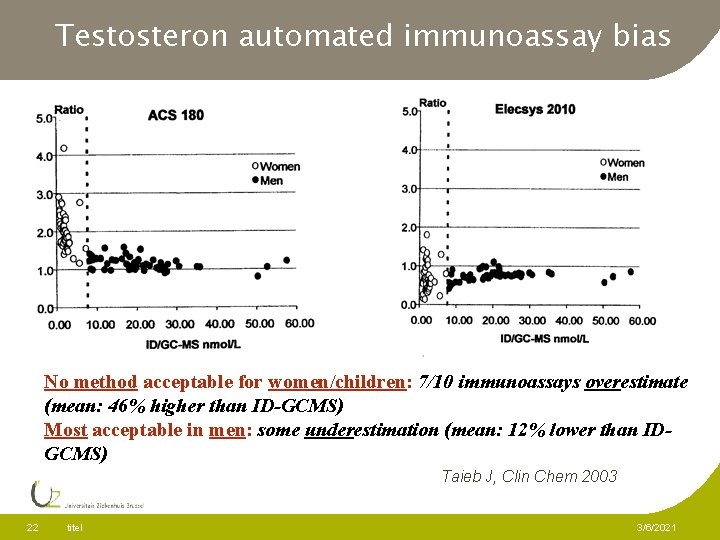
Testosteron automated immunoassay bias No method acceptable for women/children: 7/10 immunoassays overestimate (mean: 46% higher than ID-GCMS) Most acceptable in men: some underestimation (mean: 12% lower than IDGCMS) Taieb J, Clin Chem 2003 22 titel 3/6/2021
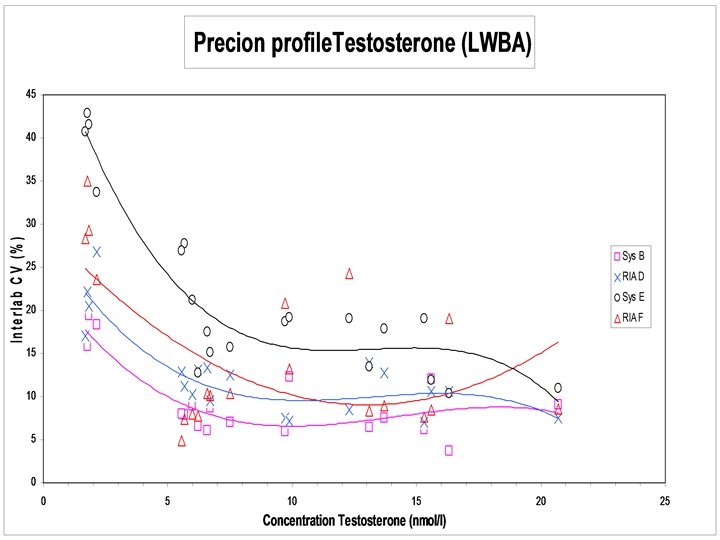
Testosteron assays: precisie 23 titel 3/6/2021
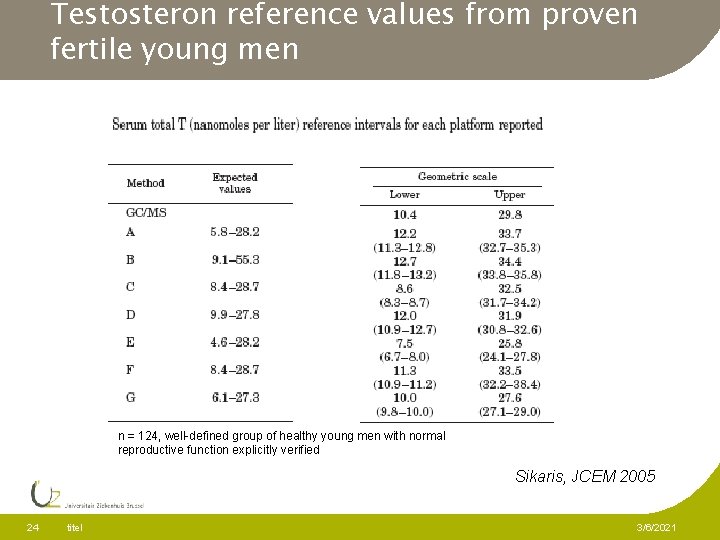
Testosteron reference values from proven fertile young men n = 124, well-defined group of healthy young men with normal reproductive function explicitly verified Sikaris, JCEM 2005 24 titel 3/6/2021
Conclusion direct steroid immunoassays l l 25 titel Large inter-method CV caused by g ¹ calibration g ¹ antibody specificity g ¹ effect binding proteins g optimalisation assays for ¹ concentration range Insufficient sensitivity (not appropriate for low values) for some systems for E 2 and P and for all systems for testosterone l Poor method robustness for some methods l Some systems are superior to others! between-user within-method variation) (high 3/6/2021
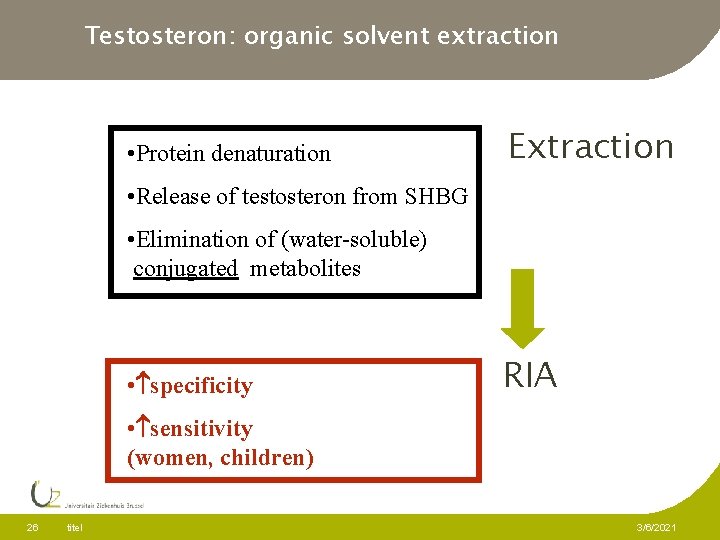
Testosteron: organic solvent extraction • Protein denaturation Extraction • Release of testosteron from SHBG • Elimination of (water-soluble) conjugated metabolites • specificity RIA • sensitivity (women, children) 26 titel 3/6/2021
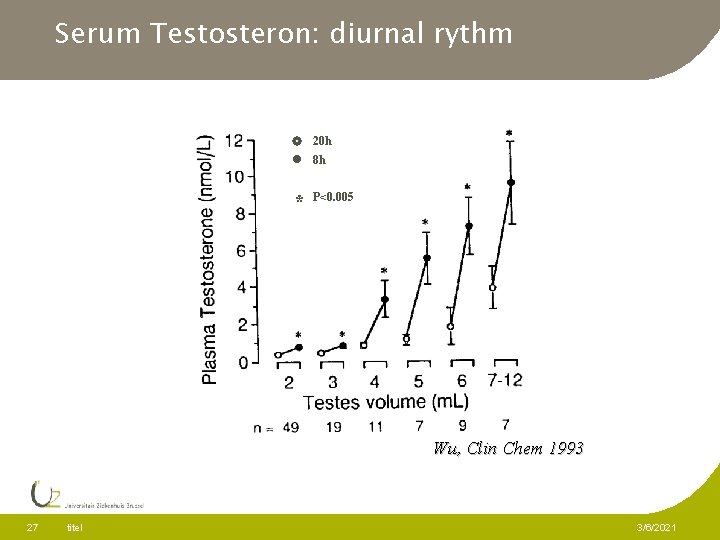
Serum Testosteron: diurnal rythm 20 h 8 h * P<0. 005 Wu, Clin Chem 1993 27 titel 3/6/2021
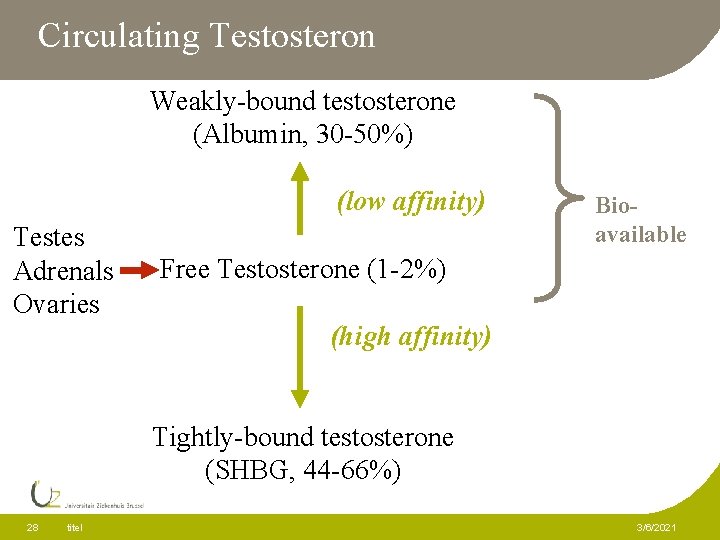
Circulating Testosteron Weakly-bound testosterone (Albumin, 30 -50%) (low affinity) Testes Adrenals Ovaries Bioavailable Free Testosterone (1 -2%) (high affinity) Tightly-bound testosterone (SHBG, 44 -66%) 28 titel 3/6/2021
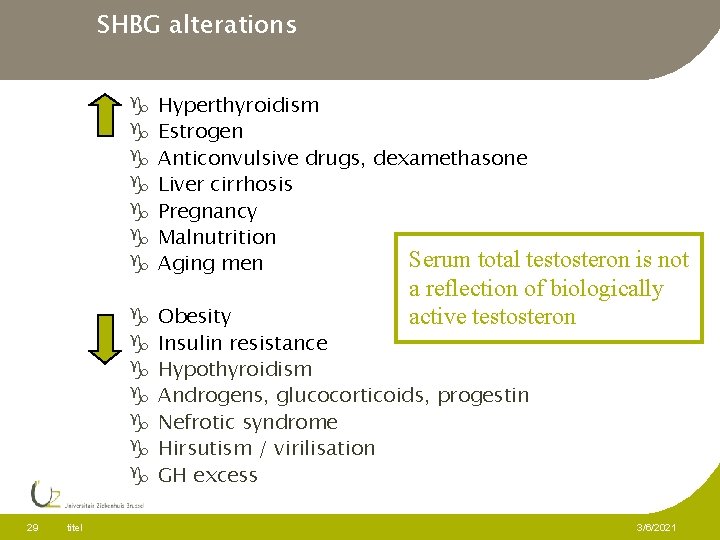
SHBG alterations 29 titel g g g g Hyperthyroidism Estrogen Anticonvulsive drugs, dexamethasone Liver cirrhosis Pregnancy Malnutrition Serum total testosteron Aging men g g g g Obesity Insulin resistance Hypothyroidism Androgens, glucocorticoids, progestin Nefrotic syndrome Hirsutism / virilisation GH excess is not a reflection of biologically active testosteron 3/6/2021
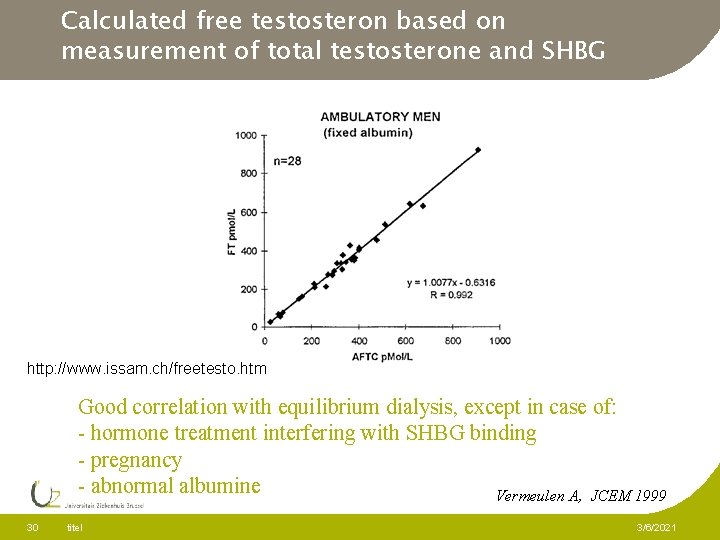
Calculated free testosteron based on measurement of total testosterone and SHBG Op basis van testo RIA en SHBG IRMA http: //www. issam. ch/freetesto. htm Good correlation with equilibrium dialysis, except in case of: - hormone treatment interfering with SHBG binding - pregnancy - abnormal albumine Vermeulen A, JCEM 1999 30 titel 3/6/2021
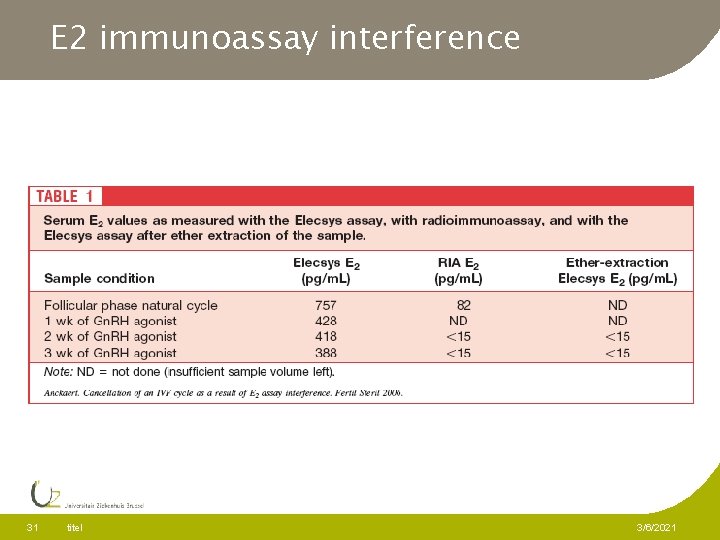
E 2 immunoassay interference 31 titel 3/6/2021

PMA et surveillance biologique l But des analyses hormonales g Avant la PMA g Suivi de la PMA l Aspects analytiques des immunoessais g Hormones stéroïdales g Prolactine g Gonadotrophines l 32 AMH titel 3/6/2021
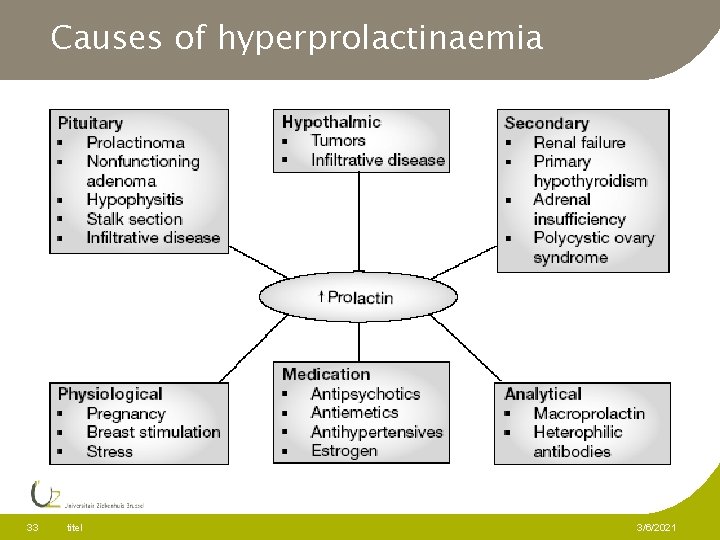
Causes of hyperprolactinaemia 33 titel 3/6/2021
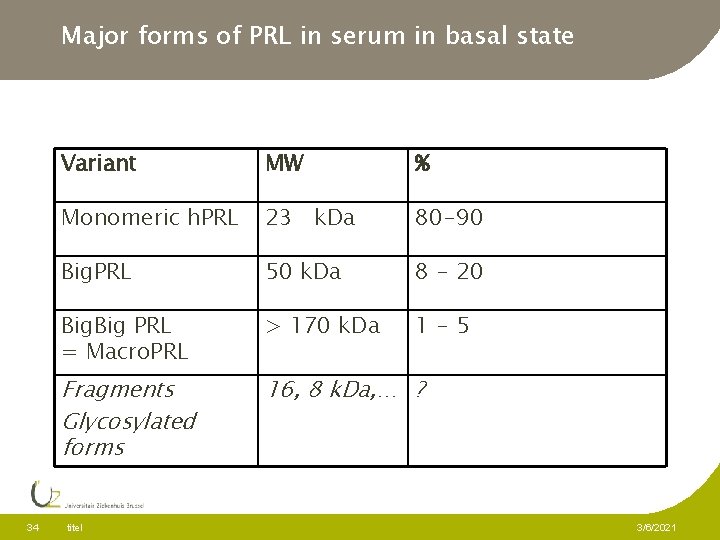
Major forms of PRL in serum in basal state 34 Variant MW % Monomeric h. PRL 23 k. Da 80 -90 Big. PRL 50 k. Da 8 - 20 Big PRL = Macro. PRL > 170 k. Da 1 -5 Fragments Glycosylated forms 16, 8 k. Da, … ? titel 3/6/2021
Macroprolactinaemia l Definition: Hyperprolactinemia where g an important fraction of circulating PRL consists of (in-vivo) biologically inactive macroprolactin g and monomeric PRL is within the reference values l Gel Filtration Chromatography: > 30 -60% macro. PRL l > 90% of cases: macro. PRL = PRL-Ig. G complex l l 35 Accounts for up to 26% of cases of hyper. PRL Can cause unnecessary work-up and treatment titel 3/6/2021
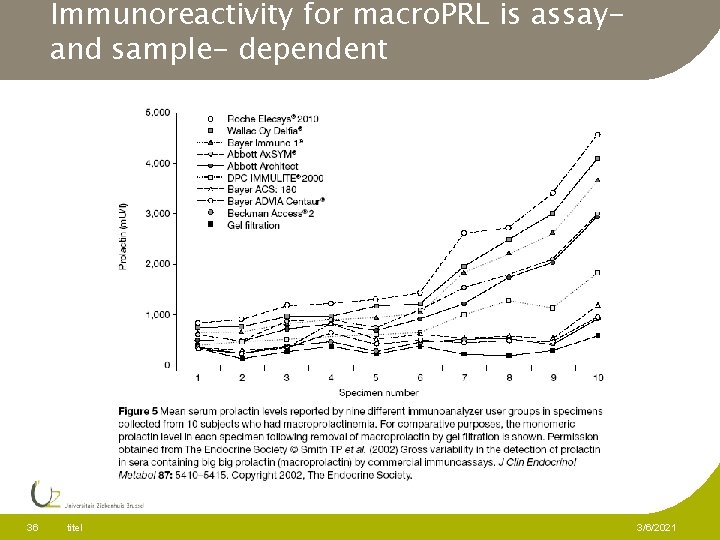
Immunoreactivity for macro. PRL is assayand sample- dependent 36 titel 3/6/2021
PEG precipitation l l First choice method for detection of macro. PRL if no interference in immunoassay If serum PRL > 1000 m. IU/l g 200 µL serum + 200 µL PEG 6000 25% (g/v) in PBS buffer in conical tube (room temperature), vortex 1 min g 30 min centrifugation at 3000 RPM g measurement of PRL in serum and in supernatant after PEG treatment with the Elecsys PRL II assay l Calculation % Recovery = (PRL supernatant * 2)/PRL serum *100 Interpretation: 60%: no macro. PRL < 60%: macro. PRL 37 titel 3/6/2021
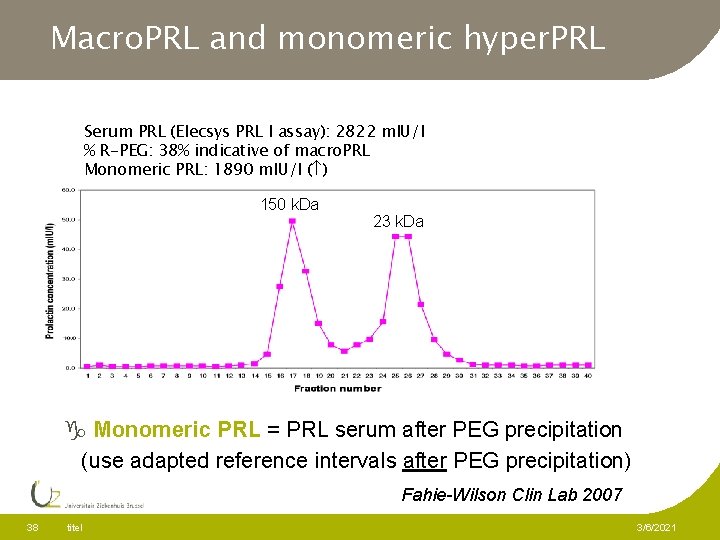
Macro. PRL and monomeric hyper. PRL Serum PRL (Elecsys PRL I assay): 2822 m. IU/l % R-PEG: 38% indicative of macro. PRL Monomeric PRL: 1890 m. IU/l ( ) 150 k. Da 23 k. Da g Monomeric PRL = PRL serum after PEG precipitation (use adapted reference intervals after PEG precipitation) Fahie-Wilson Clin Lab 2007 38 titel 3/6/2021

PMA et surveillance biologique l But des analyses hormonales g Avant la PMA g Suivi de la PMA l Aspects analytiques des immunoessais g Hormones stéroïdales g Prolactine g Gonadotrophines l 39 AMH titel 3/6/2021
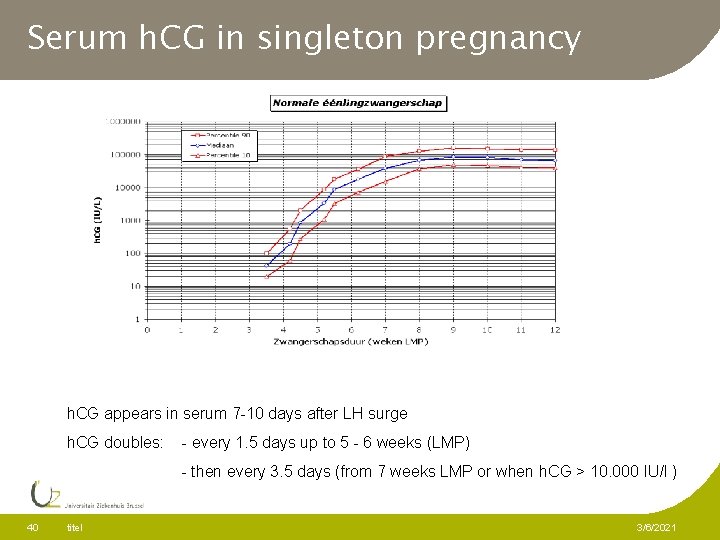
Serum h. CG in singleton pregnancy h. CG appears in serum 7 -10 days after LH surge h. CG doubles: - every 1. 5 days up to 5 - 6 weeks (LMP) - then every 3. 5 days (from 7 weeks LMP or when h. CG > 10. 000 IU/l ) 40 titel 3/6/2021

Serum h. CG in ectopic pregnancy l l l h. CG discriminatory zone: ectopic pregnancy to be excluded if (D&C) g transvaginal US: absence of demonstrable intra-uterine pregnancy g and h. CG > 1000 à 2000 IU/L h. CG increase rate is often abnormal, but it is normal in 1/3 ectopic pregnancies Serum progesterone: good discriminative capacity between viable and non-viable, but NOT for discrimination between ectopic and non-ectopic. g > 20 -25 ng/m. L: viable pregnancy g 5 -20 ng/m. L: grey zone g < 5 ng/m. L: non-viable (0. 3% viable pregnancy) 41 titel 3/6/2021
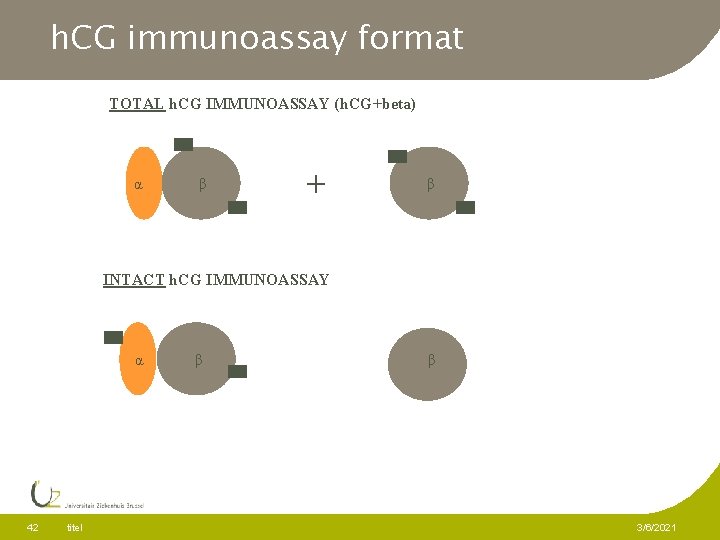
h. CG immunoassay format TOTAL h. CG IMMUNOASSAY (h. CG+beta) α β + β INTACT h. CG IMMUNOASSAY α 42 titel β β 3/6/2021
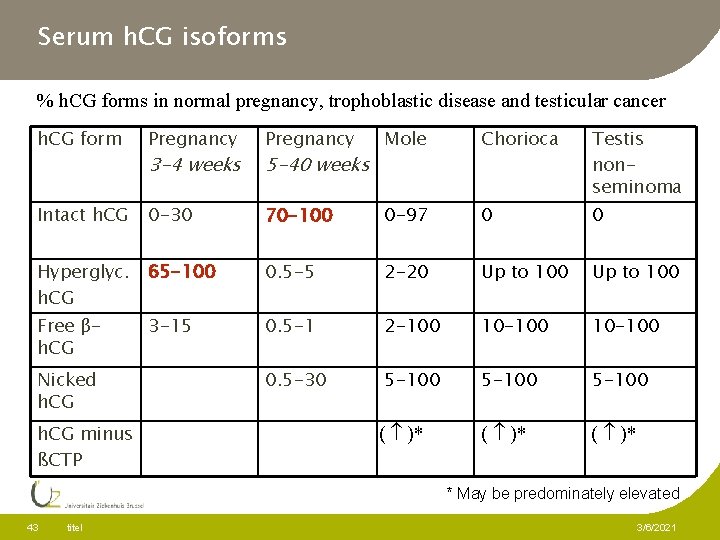
Serum h. CG isoforms % h. CG forms in normal pregnancy, trophoblastic disease and testicular cancer h. CG form Pregnancy Mole Chorioca Testis nonseminoma Intact h. CG 0 -30 70 -100 0 -97 0 0 Hyperglyc. h. CG 65 -100 0. 5 -5 2 -20 Up to 100 Free βh. CG 3 -15 0. 5 -1 2 -100 10 -100 0. 5 -30 5 -100 ( )* Nicked h. CG minus ßCTP 3 -4 weeks 5 -40 weeks ( )* * May be predominately elevated 43 titel 3/6/2021
Variability automated gonadotrophin assays l Different specificity of monoclonal antibodies for circulating isoforms g Glycosylation g Micro-heterogeneity in polypeptide chain (LH, FSH) g Fragments, nicked forms, aggregates l Calibration differences l l l 44 titel Primary international standards - LH 80/552 = gepurified pituitary extract - FSH 78/549 = pituitary extract - FSH 92/510 = recombinant human FSH Secundary kit standards Matrix effects 3/6/2021
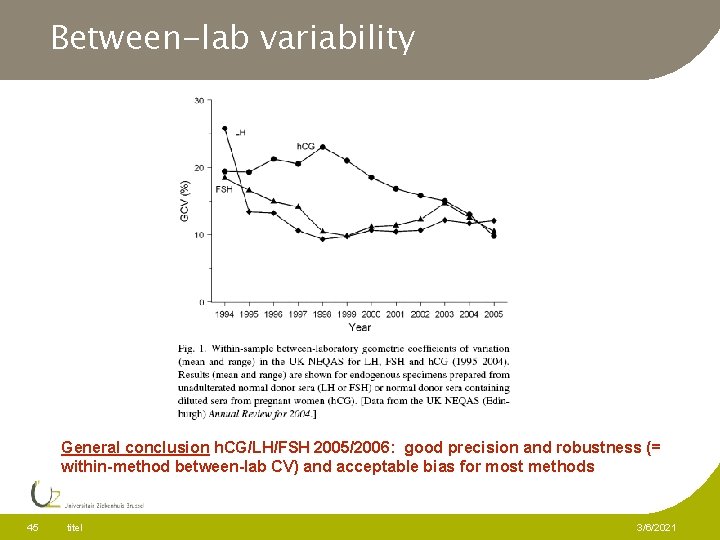
Between-lab variability General conclusion h. CG/LH/FSH 2005/2006: good precision and robustness (= within-method between-lab CV) and acceptable bias for most methods 45 titel 3/6/2021
Luteinising Hormone (LH) Follicle Stimulating Hormone (FSH) l l l Secretion by adenohypophyse Glycoprotein hormones (MW 28 – 33 k. Da) Heterodimers g -chain = identical LH, FSH, TSH, h. CG g β-chain biological and immunological specificity LH and h. CG: 80% homology Specific monoclonal Abs to avoid crossreactivity 46 titel 3/6/2021
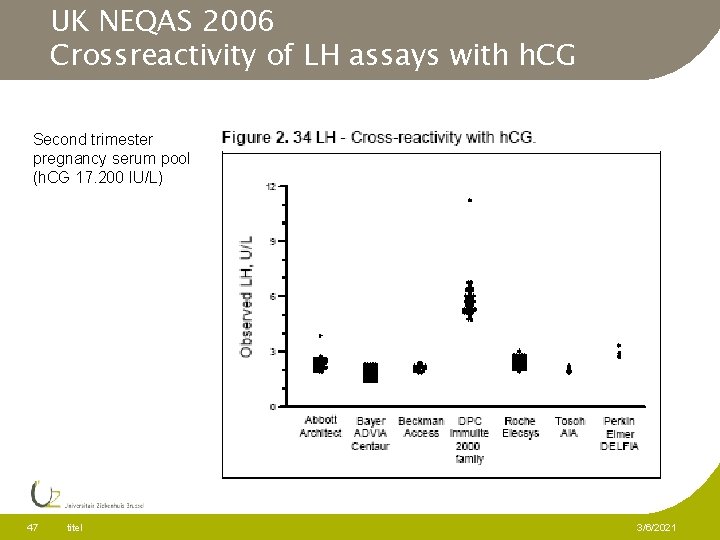
UK NEQAS 2006 Crossreactivity of LH assays with h. CG Second trimester pregnancy serum pool (h. CG 17. 200 IU/L) 47 titel 3/6/2021
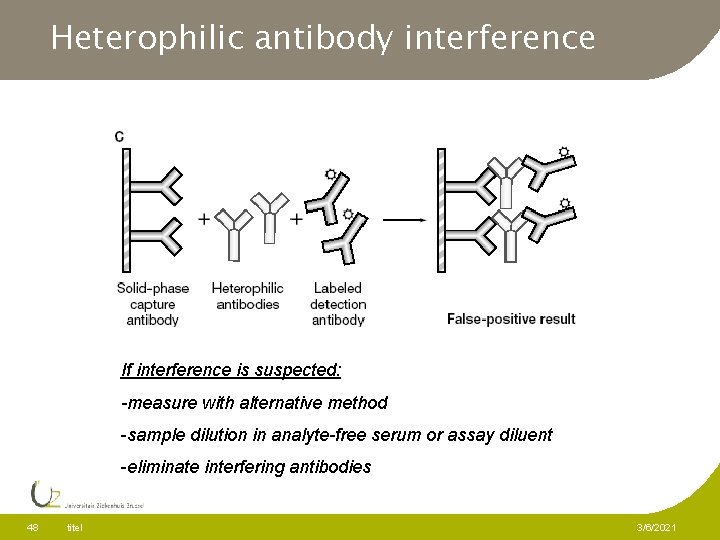
Heterophilic antibody interference If interference is suspected: -measure with alternative method -sample dilution in analyte-free serum or assay diluent -eliminate interfering antibodies 48 titel 3/6/2021
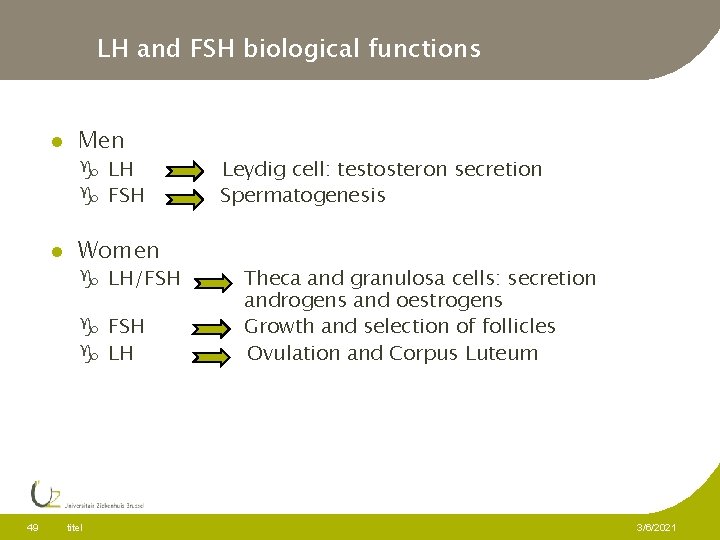
LH and FSH biological functions l Men g LH g FSH l Women g LH/FSH g LH 49 titel Leydig cell: testosteron secretion Spermatogenesis Theca and granulosa cells: secretion androgens and oestrogens Growth and selection of follicles Ovulation and Corpus Luteum 3/6/2021
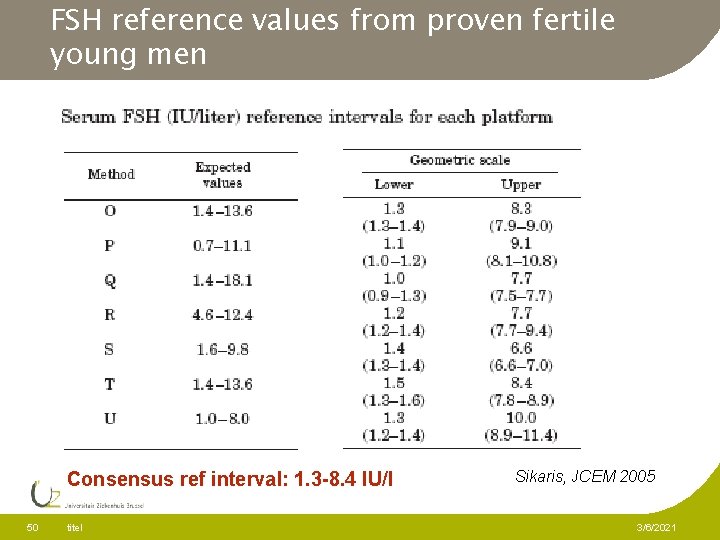
FSH reference values from proven fertile young men Consensus ref interval: 1. 3 -8. 4 IU/l 50 titel Sikaris, JCEM 2005 3/6/2021

PMA et surveillance biologique l But des analyses hormonales g Avant la PMA g Suivi de la PMA l Aspects analytiques des immunoessais g Hormones stéroïdales g Prolactine g Gonadotrophines l 51 AMH titel 3/6/2021
AMH l l Glycoprotein, 140 k. Da homodimer TGFβ family of growth and differentiation factors (inhibins, activins, … Anti-Mullerian Hormone: causes regression of Mullerian duct in male foetus Secretion: g Men: g Women: 52 titel Immature Sertoli cells Fetal and postnatal Granulosa cells ovaria Adult 3/6/2021
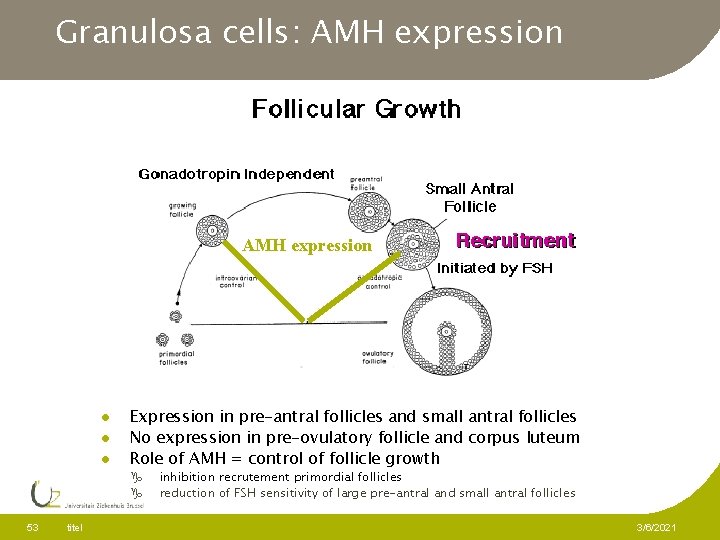
Granulosa cells: AMH expression l l l Expression in pre-antral follicles and small antral follicles No expression in pre-ovulatory follicle and corpus luteum Role of AMH = control of follicle growth g g 53 titel inhibition recrutement primordial follicles reduction of FSH sensitivity of large pre-antral and small antral follicles 3/6/2021
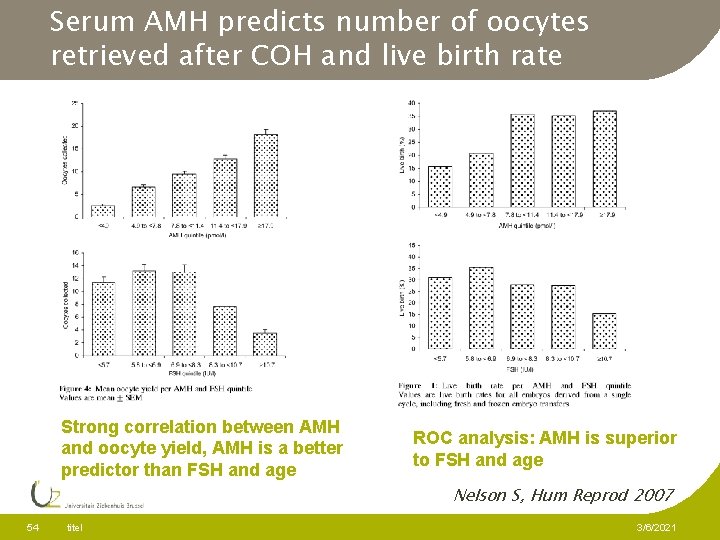
Serum AMH predicts number of oocytes retrieved after COH and live birth rate Strong correlation between AMH and oocyte yield, AMH is a better predictor than FSH and age ROC analysis: AMH is superior to FSH and age Nelson S, Hum Reprod 2007 54 titel 3/6/2021
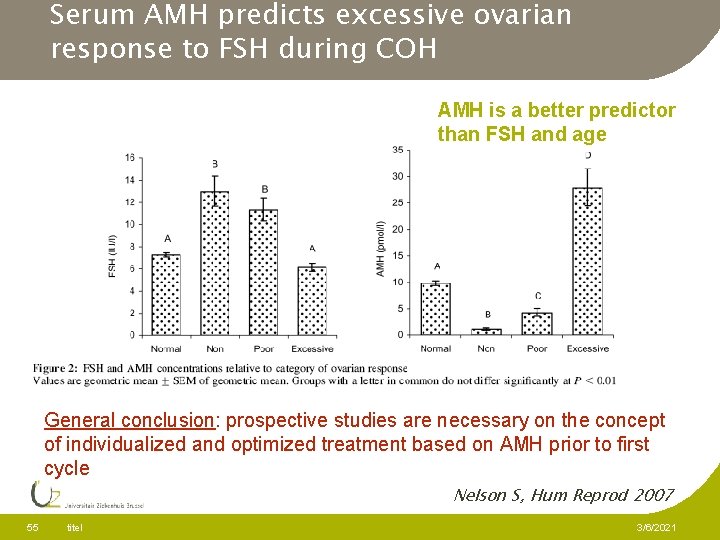
Serum AMH predicts excessive ovarian response to FSH during COH AMH is a better predictor than FSH and age General conclusion: prospective studies are necessary on the concept of individualized and optimized treatment based on AMH prior to first cycle Nelson S, Hum Reprod 2007 55 titel 3/6/2021
Serum AMH is increased in PCOS l PCOS: two- to threefold increase in serum AMH g Defective selection mechanism of dominant follicle results in anovulation and accumulation of small antral follicles (mainly 2 -5 mm), which contribute to AMH secretion g Increased AMH production per follicle occurs and the increased granulosa cell AMH production may contribute to anovulation (AMH lowers the sensitivity of follicles to FSH) l Serum AMH cut-off 8. 4 ng/ml for diagnosis of PCOS offers g high specificity (92%) g and sensitivity (67%) (Pigny, JCEM 2006) 56 titel 3/6/2021
Advantages of serum AMH measurement l l Ovarian aging: serum AMH decreases before the increase of FSH and the decrease of inhibin B On cycle day 3: Intercycle reproducibility for AMH is higher than for inhibin B, E 2, FSH and antral follicle count one single AMH measurement is sufficient Fanchin R, Hum Reprod 2005 l 57 titel AMH levels remain relatively constant during the menstrual cycle AMH measurement can be done during the entire menstrual cycle 3/6/2021
- Slides: 57