
Practical Cardiology Case Studies Wendy Blount DVM Nacogdoches
Practical Cardiology Case Studies Wendy Blount, DVM Nacogdoches TX

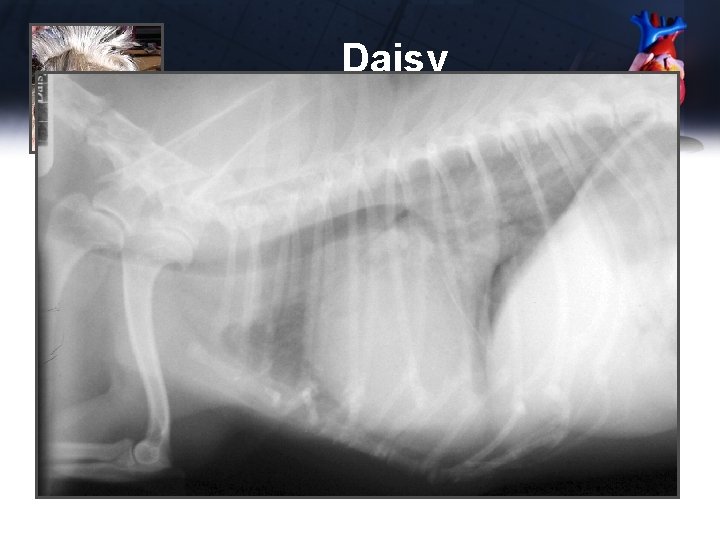
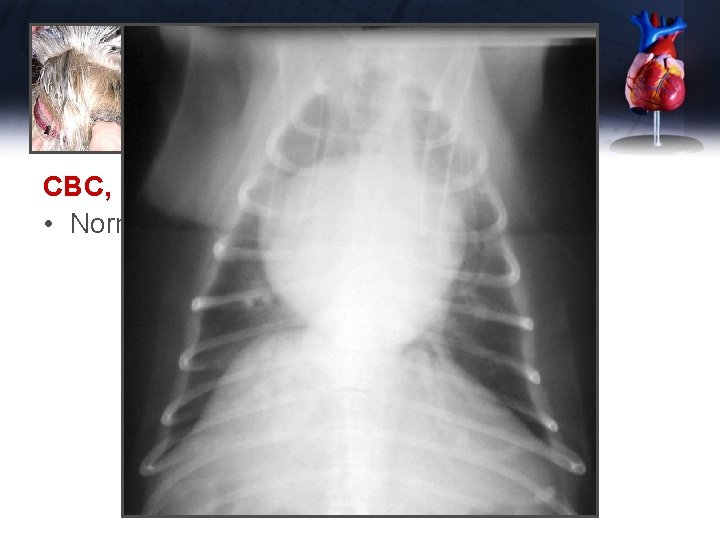
Daisy Signalment • 15 year old spayed female mixed terrier • 11 pounds Chief Complaint • Became dyspneic while on vacation, as they drove over a mountain pass • Come to think of it, she has been breathing hard at night for some time

Daisy Exam • T 100. 2, P 185, R – 66, BP – 145, BCS – 3. 5 • Increased respiratory effort (heart sounds) • 3/6 pansystolic murmur loudest at left apex • Mucous membranes pale pink • Crackles in the small airways • Pulses weak, somewhat irregular, no pulse deficits • CRT 3. 5 -4 seconds
Daisy CBC, mini-panel, electrolytes • Normal
Daisy CBC, mini-panel, electrolytes • Normal
Daisy ECG

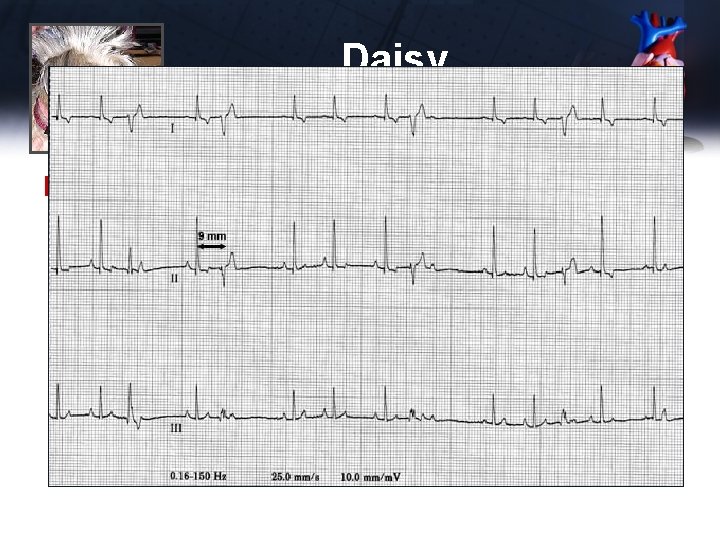
Daisy Calculating Instantaneous Heart Rate (i. HR) • Measure R wave to R wave (9 mm) • • Divide by paper speed (25 mm/sec) for time per beat 9 mm x _sec_ = 0. 36 sec per heart beat 25 mm • • Calculate beats per minute _heart beat_ x _60 sec = 166 beats/minute 0. 36 sec minute

Daisy ECG • • Rate – 110 bpm Rhythm – sinus arrhythmia with VPCs MEA – normal (lead II has tallest R waves) P, QRS and T waves – normal – No evidence of enlarged LA and LV on the ECG • VPC – abnormal QRS – – – Comes too early (i. HR 166 bpm) Wide and bizarre shape Not preceded by a P wave T wave opposite in polarity than normal QRS Compensatory pause after the VPC

Daisy Initial Therapeutic Plan • Lasix 25 mg IM, then 12. 5 mg PO BID • Enalapril 2. 5 mg PO BID • Pimobendan 1. 25 mg PO BID • Owner is a med tech, and set up oxygen mask to use PRN at home

Daisy When to treat VPCs • VPCs unusual for MR • Did not treat in this case, because: – MR dogs not predisposed to sudden death • PS, SAS and DCM are more associated with sudden death due to arrhythmia – Ectopic focus not firing at a fast rate (166 bpm) • <200 bpm i. HR is well away from the T wave – No pulse deficits – did not affect hemodynamics – Primary treatments for VPC are Sotalol or B blocker • Negative inotropes not ideal for myocardial failure

Daisy Recheck – 4 days • Daisy’s breathing is much improved (30 -40 at rest) • Lateral chest x-ray • Electrolytes normal • BUN 52
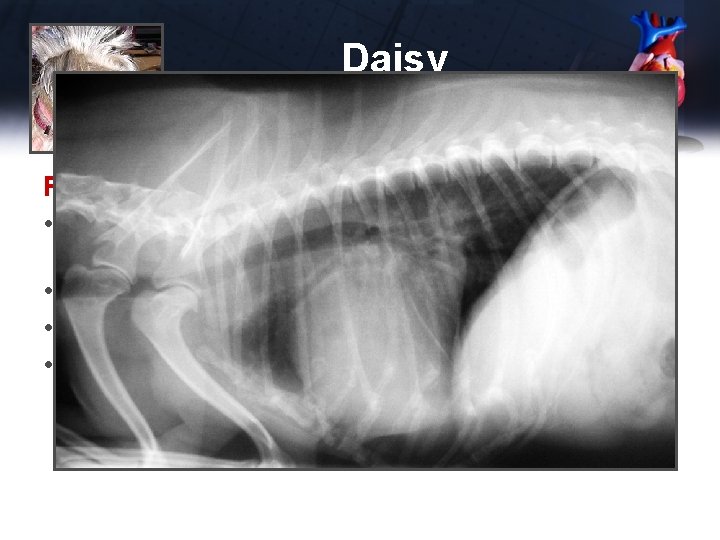
Daisy Recheck – 4 days • Daisy’s breathing is much improved (30 -40 at rest) • Lateral chest x-ray • Electrolytes normal • BUN 52

Daisy Diagnostic Plan - updated • Decrease enalapril to SID • Recheck BUN 1 week • Recheck chest rads 1 week Recheck – 1 week • BUN – 37 • Thoracic rads no change • Request recheck in 3 months, or sooner if respiratory rate at rest is above 35 per minute
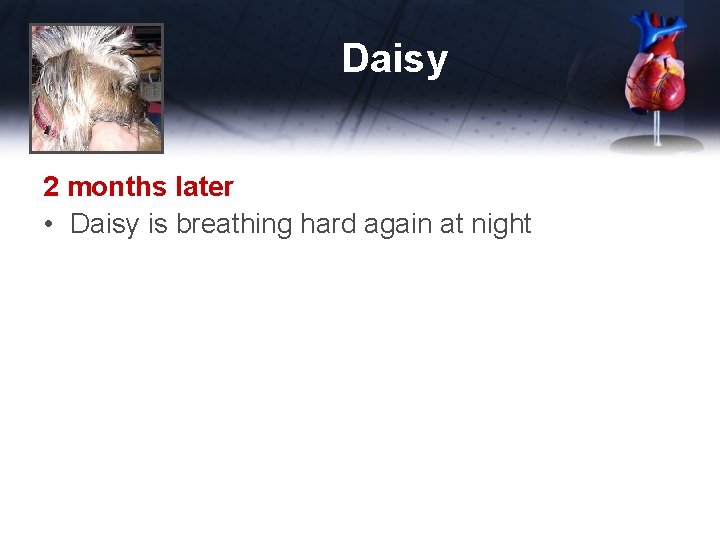
Daisy 2 months later • Daisy is breathing hard again at night
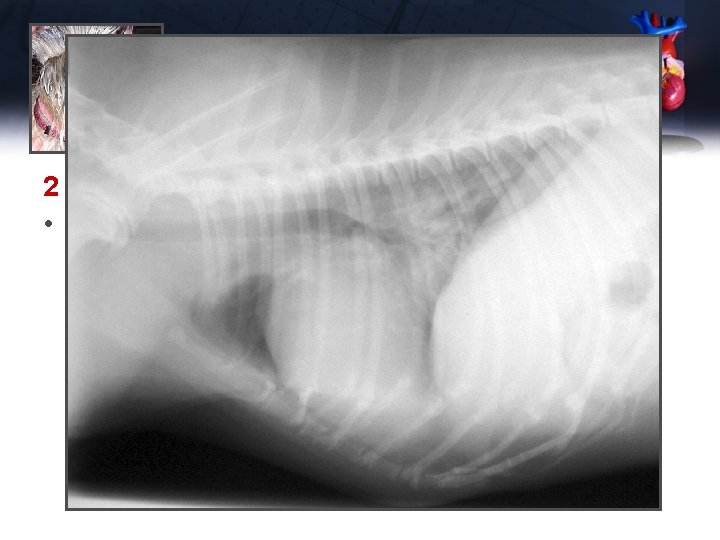
Daisy 2 months later • Daisy is breathing hard again at night
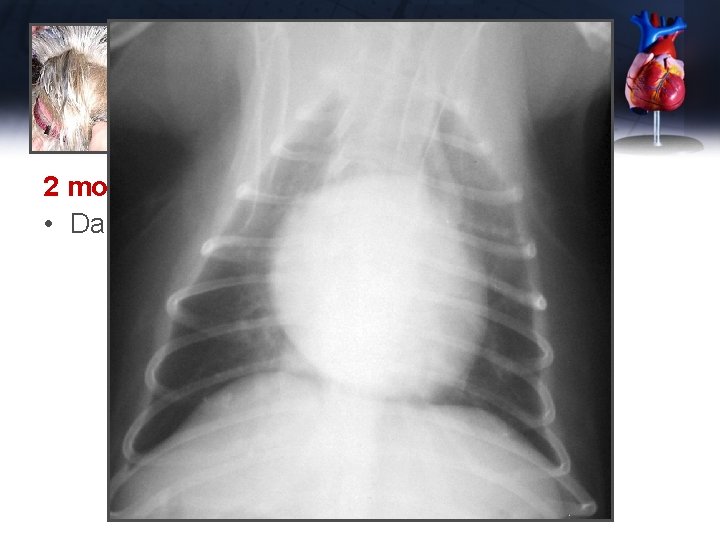
Daisy 2 months later • Daisy is breathing hard again at night

Daisy Bloodwork • CBC, electrolytes normal • BUN 88 Therapeutic Plan • Increase furosemide to 18. 75 mg PO BID • Add hydralazine 2. 5 mg PO BID • Recheck chest rads, BUN, electrolytes, blood pressure 1 week

Daisy Recheck – 1 week • Clinically much improved – respiratory rate 3040 per minute at rest • electrolytes normal • BUN 58 • Blood pressure 135
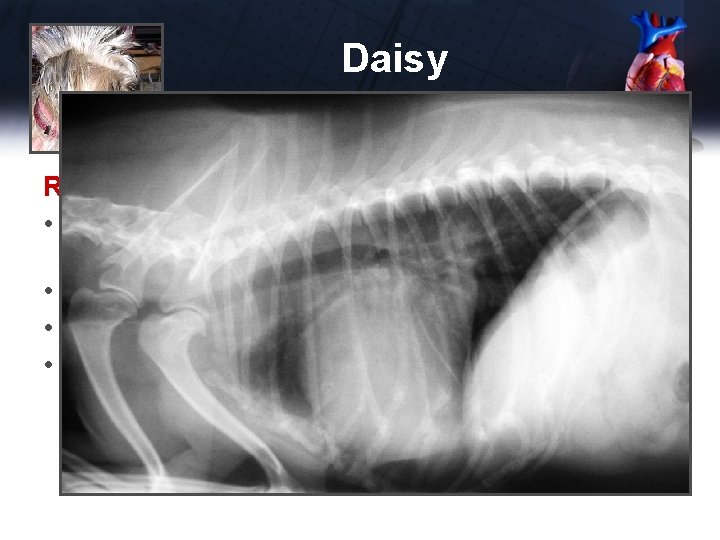
Daisy Recheck – 1 week • Clinically much improved – respiratory rate 3040 per minute at rest • electrolytes normal • BUN 58 • Blood pressure 135
Daisy Recheck – 6 months • Daisy dyspneic again Exam • Similar to last crisis – BP 90

Daisy Bloodwork • CBC, electrolytes normal • BUN 105, creat 2. 1
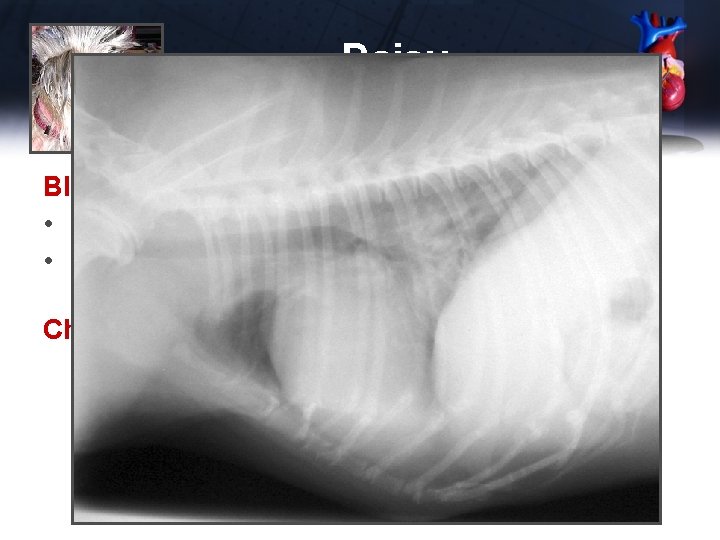
Daisy Bloodwork • CBC, electrolytes normal • BUN 105, creat 2. 1 Chest x-rays

Daisy Bloodwork • CBC, electrolytes normal • BUN 105, creat 2. 1 Chest x-rays • Similar to last crisis ECG • Sinus tachycardia, wide P wave
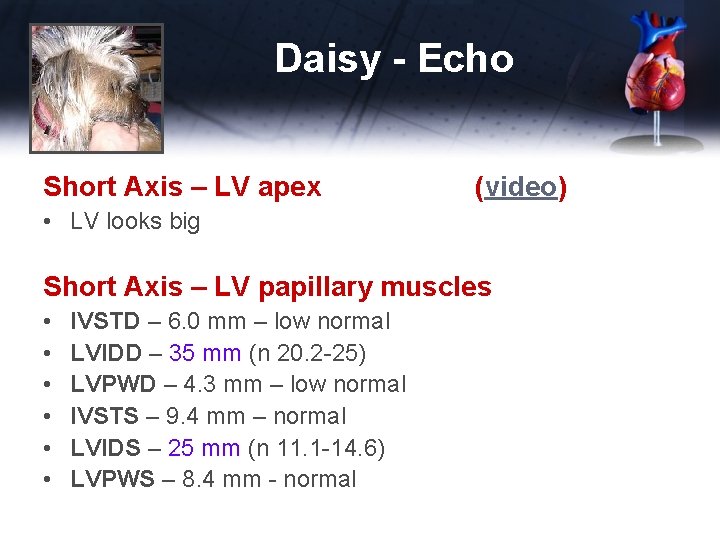
Daisy - Echo Short Axis – LV apex (video) • LV looks big Short Axis – LV papillary muscles • • • IVSTD – 6. 0 mm – low normal LVIDD – 35 mm (n 20. 2 -25) LVPWD – 4. 3 mm – low normal IVSTS – 9. 4 mm – normal LVIDS – 25 mm (n 11. 1 -14. 6) LVPWS – 8. 4 mm - normal
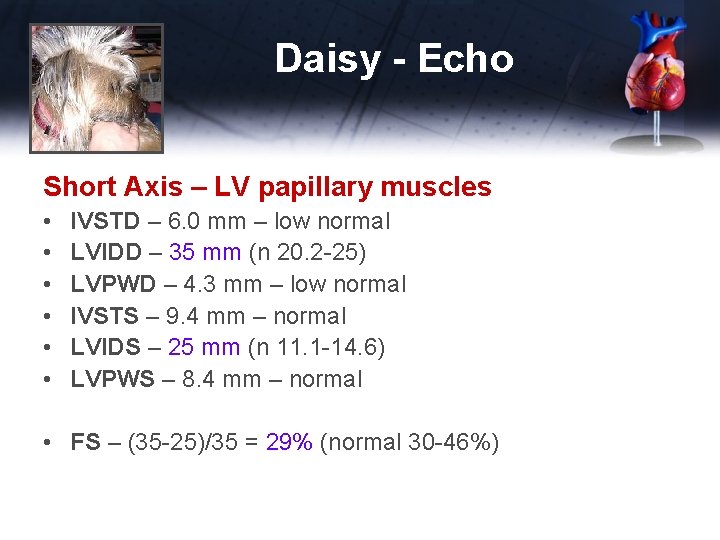
Daisy - Echo Short Axis – LV papillary muscles • • • IVSTD – 6. 0 mm – low normal LVIDD – 35 mm (n 20. 2 -25) LVPWD – 4. 3 mm – low normal IVSTS – 9. 4 mm – normal LVIDS – 25 mm (n 11. 1 -14. 6) LVPWS – 8. 4 mm – normal • FS – (35 -25)/35 = 29% (normal 30 -46%)
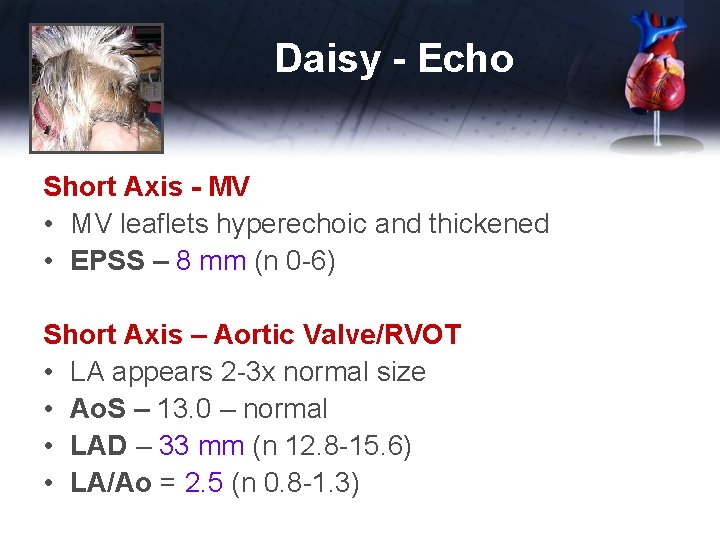
Daisy - Echo Short Axis - MV • MV leaflets hyperechoic and thickened • EPSS – 8 mm (n 0 -6) Short Axis – Aortic Valve/RVOT • LA appears 2 -3 x normal size • Ao. S – 13. 0 – normal • LAD – 33 mm (n 12. 8 -15. 6) • LA/Ao = 2. 5 (n 0. 8 -1. 3)

Daisy - Echo Long View – 4 Chamber • LV and LA both appear large • MV is very thick and knobby, with some prolapse into the LA

Daisy - Echo Long View – 4 Chamber • LV and LA both appear large • MV is very thick and knobby, with some prolapse into the LA

Daisy - Echo Long View – 4 Chamber • LV and LA both appear large • MV is very thick and knobby, with some prolapse into the LA • Pulmonary vein markedly enlarged Long View – LVOT • Large LA, Large LV

Daisy Therapeutic Plan • Increase hydralazine to 5 mg PO BID • Add spironolactone 12. 5 mg PO BID • Increase furosemide to 18. 75 mg PO TID x 2 days, then decrease to BID if respiratory rate decreases to less than 40 per minute at rest. • Recheck 1 week – BUN, creat, phos, electrolytes, chest rads, BP

Daisy Recheck – 1 week • Clinically improved again • BP - 125 • BUN 132, creat 2. 6, phos 6. 6 • Electrolytes normal • chest rads improved pulmonary edema Therapeutic Plan – Update • Add aluminum hydroxide gel 2 cc PO BID

Daisy 5 Months later • Coughing getting worse • Chest rad show no pulmonary edema • LA getting larger Therapeutic Plan – Update • Add torbutrol 2. 5 mg PO PRN to control cough

Daisy 18 Months after initial presentation • Owner discontinue pimobendan due to GI upset 28 months after initial presentation • Daisy finally took her final breath • BUN >100 for 22 months

Chronic MV Disease • • May be accompanied by similar TV disease (80%) TV disease without MV disease possible but rare LHF and/or RHF can result Right heart enlargement can develop due to pulmonary hypertension, in turn due to LHF

Chronic MV Disease Echo abnormalities: (doppler echo) • • • LA and/or RA dilation, LV and/or RV dilation Exaggerated IVS motion (toward RV in diastole) Increased FS first, then later decreased FS Thickened valve leaflets (video) (video 2) If TV only affected, left heart can appear compressed, small and perhaps artifactually thick • Ruptured CT – – MV flips around in diastole – MV flies up into LA during systole – “MV flail” (video) – May see trailing CT, or CT floating in the LV

Chronic MV Disease Right Heart Failure • Medications similar to LHF • Medications not as effective at eliminating fluid congestion – More effective at preventing fluid accumulation, once controlled • Periodic abdominocentesis and/or pleurocentesis required • Prognosis for RHF and LHF is extremely variable
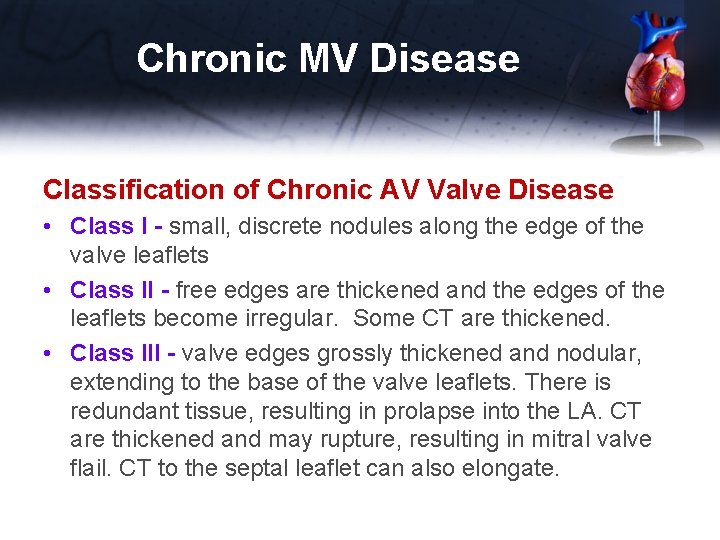
Chronic MV Disease Classification of Chronic AV Valve Disease • Class I - small, discrete nodules along the edge of the valve leaflets • Class II - free edges are thickened and the edges of the leaflets become irregular. Some CT are thickened. • Class III - valve edges grossly thickened and nodular, extending to the base of the valve leaflets. There is redundant tissue, resulting in prolapse into the LA. CT are thickened and may rupture, resulting in mitral valve flail. CT to the septal leaflet can also elongate.

Chronic MV Disease LA Jet Lesions • fibrous plaques in the endocardium in a region subjected to the impact of the high velocity MR jet. • Endomyocardial splits or tears may also be identified. • On occasion, a full thickness left atrial tear occurs resulting in hemopericardium, pericardial tamponade, and usually death. • Rarely, a full thickness endomyocardial tear will involve the interatrial septum, causing an acquired atrial septal defect. (MR Client Handout) (ACVIM MVD Guidelines)

MVD in Cavaliers • Leading cause of death in Cavaliers • CHF can develop as young as 1 -3 years old • First sign of disease is mitral murmur – Careful annual auscultation • Radiographs should be done as soon as murmur is detected – q 6 months when progressing – annually for stable disease – Sooner when respiratory rate exceeds 35 -40 per minute • Doppler Echo when abnormalities are present on rads

MVD in Cavaliers • The median survival period from grade III CHF due to MVD is approximately seven months, with 75% of the dogs dead by one year • Current recommendation is that no Cavalier be bred until after 5 years of age, with no murmur • At this time, a majority of Cavaliers are affected (Client Handout)

Trip Signalment • 2 year old castrated male border collie Chief Complaint/History • Productive Cough, weight loss for 2 months • Breathing hard for a 2 days • Energy good; did well in agility 4 days ago • Owner thinks had lifelong PU-PD • Has wanted to be in AC this summer – unlike last summer when he enjoyed being outside
Trip Exam • T 102. 2, P 168, R 42, CRT 3 sec • BCS 2. 5 • BP 100 • Bounding pulses, notable in dorsal pedal artery • Precordial – exaggerated left apical heave • Lung sounds clear
Trip Exam • 3 murmurs: 1. PMI left base (audio) – To-and-fro murmur 3/6 – aortic stenosis in systole, regurg in diastole 2. PMI left apex, but heard all over chest (link) – Holosystolic murmur 3/6 – Mitral regurgitation due to LHF 3. PMI Carotid artery (audio) – 2/6 ejection murmur – aortic stenosis

Trip Differential Diagnoses • Aortic endocarditis • SAS with aortic regurgitation • Mitral regurgitation (endocarditis? ) Diagnostic Plan • Thoracic radiographs • EKG • Echocardiography
Trip EKG • Normal sinus rhythm for 10 minutes
Trip EKG • Normal sinus rhythm for 10 minutes

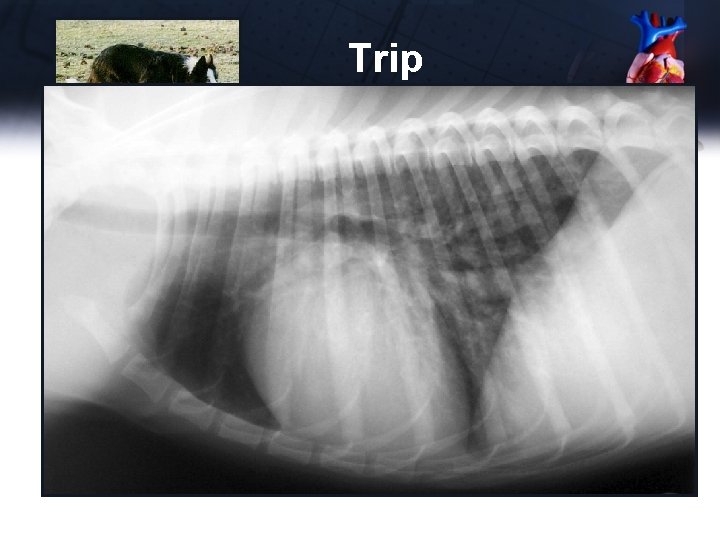
Trip EKG • Normal sinus rhythm for 10 minutes Thoracic Radiographs • Interstitial pattern caudal lung fields • Vertebral heart score 10. 5 • Enlarged cranial pulmonary lobar vein • Mildly enlarged left atrium • Early left congestive heart failure

Trip - Echo Short Axis – LV Apex • No abnormalities noted Short Axis – LV PM
Trip - Echo Short Axis – LV Apex • No abnormalities noted Short Axis – LV PM

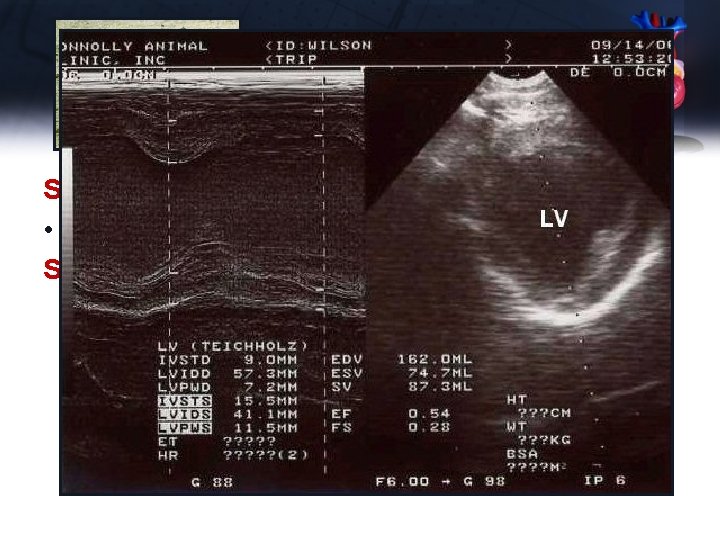
Trip - Echo Short Axis – LV Apex • No abnormalities noted Short Axis – LV PM • LVIDD – 57. 3 (n 31. 3 -34) • IVSTS – 15. 5 mm (n 12. 6 -13. 7) • LVIDS – 41. 1 mm (18. 8 -20. 7) • FS = (57. 3 -41. 1)/57. 3 = 28% (n 30 -46%) • EF = 54% (n >70%)

Trip - Echo Short Axis – MV • EPSS – 8 mm (n 0 -6) Short Axis – Ao/RVOT • Ao. S – 20. 2 (normal) • LAD – 27. 8 (n 19. 0 -20. 5) • LA/Ao – 27. 8/20. 2 = 1. 38 (n 0. 8 -1. 3) • Aortic valve leaflets are hyperechoic
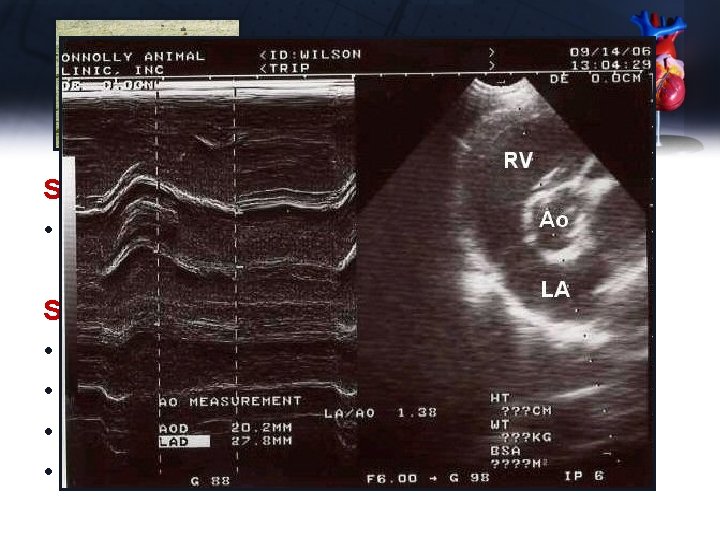
Trip - Echo Short Axis – MV • EPSS – 8 mm (n 0 -6) Short Axis – Ao/RVOT • Ao. S – 20. 2 (normal) • LAD – 27. 8 (n 19. 0 -20. 5) • LA/Ao – 27. 8/20. 2 = 1. 38 (n 0. 8 -1. 3) • Aortic valve leaflets are hyperechoic
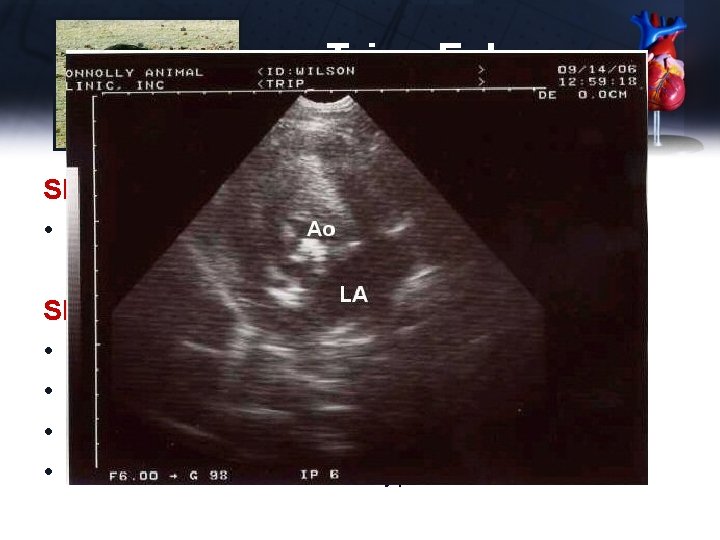
Trip - Echo Short Axis – MV • EPSS – 8 mm (n 0 -6) Short Axis – Ao/RVOT • Ao. S – 20. 2 (normal) • LAD – 27. 8 (n 19. 0 -20. 5) • LA/Ao – 27. 8/20. 2 = 1. 38 (n 0. 8 -1. 3) • Aortic valve leaflets are hyperechoic

Trip - Echo Short Axis – PA • No abnormalities noted Long Axis – 4 Chamber
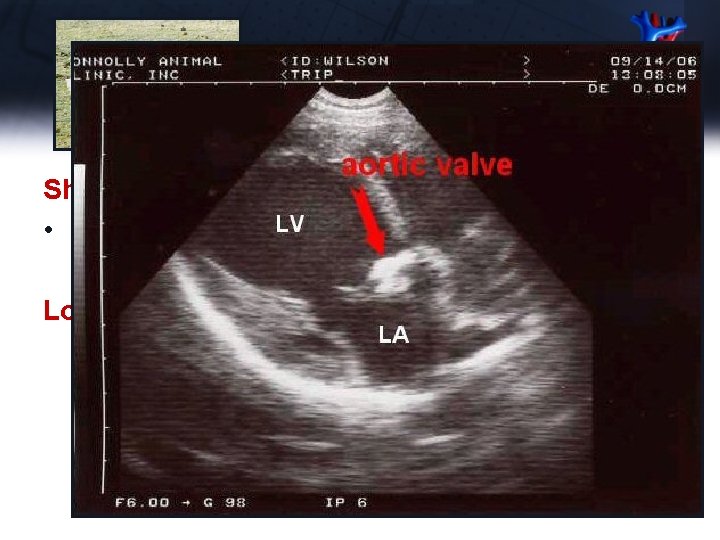
Trip - Echo Short Axis – PA • No abnormalities noted Long Axis – 4 Chamber

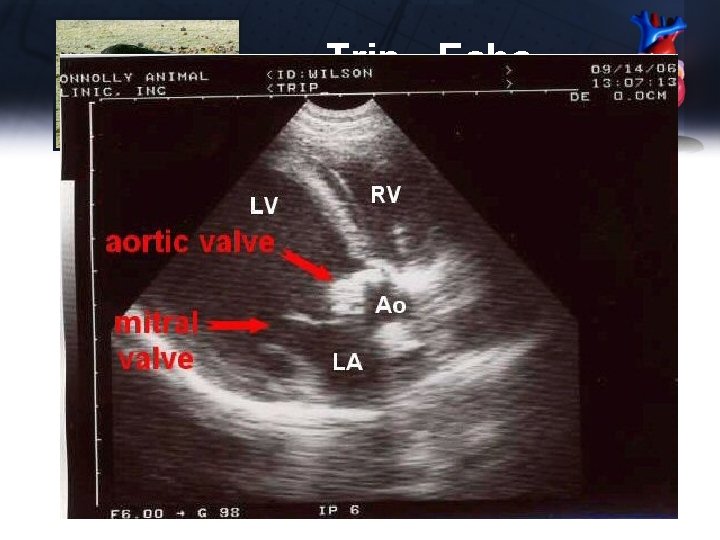
Trip - Echo Short Axis – PA • No abnormalities noted Long Axis – 4 Chamber • LA appeared mildly enlarged • IVS bowed anteriorly toward RV • No evidence of mitral encodarditis or endocardiosis • Vegetation on aortic valve
Trip - Echo

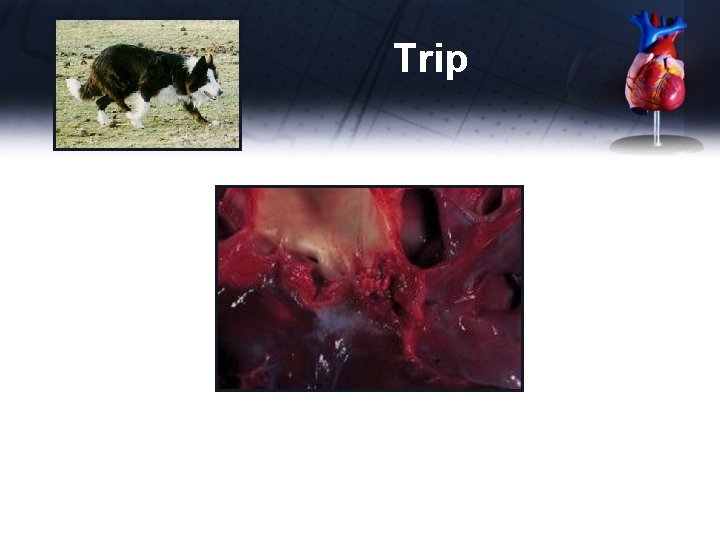
Trip - Echo Long Axis – LVOT (video) • Hyperechoic thickened aortic valve leaflets Diagnosis • Aortic endocarditis Therapeutic Plan • Elected euthanasia due to poor prognosis
Trip

Valvular Endocarditis Clinical Features • Present for FUO, weight loss or heart failure • Aortic much more common than mitral • Dogs much more common than cats • Many bacteria including Bartonella • Breed predisposition – Rottweiler, Boxer, Golden retriever – Newfoundland, German shepard

Valvular Endocarditis Clinical Features • Abnormal valve + bacteremia = endocarditis • Bacteremia caused routinely by: – – – Dental cleaning Brushing your teeth (chewing) Constipation, any GI illness defecation Urinary catheterization infection
Valvular Endocarditis ECG abnormalities • Tall, wide P wave (LA enlargement) • Tall R wave (LV enlargement) • Ventricular arrhythmias common – Treat if multiform of >30 per minute – Class I or III antiarrhythmic – Sotalol 2 -3 mg/kg PO BID Thoracic radiographs • Left heart failure
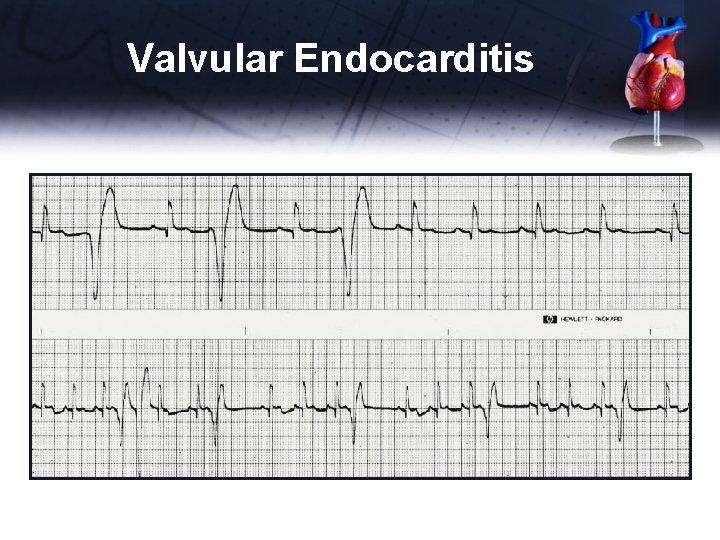
Valvular Endocarditis ECG abnormalities • Tall, wide P wave (LA enlargement) • Tall R wave (LV enlargement) • Ventricular arrhythmias common – Treat if multiform of >30 per minute – Class I or III antiarrhythmic – Sotalol 2 -3 mg/kg PO BID Thoracic radiographs • Left heart failure
Valvular Endocarditis Echocardiographic abnormalities • Thickened, hyperechoic valves • Vegetation may flop around – MV in diastole, AV in systole • Variable LV dilation (more with time) • FS normal to low normal until myocardial failure • MV endocarditis can be difficult to distinguish from MV endocardiosis – Endocarditis dogs are systemically ill

Valvular Endocarditis Treatment • Based on urine and blood culture and sensitivity, Bartonella PCR • Antibiotics – IV 3 -5 days – broad spectrum until culture results – SC/IM 3 -5 days – Then PO long term – often for life • Treat Heart failure (severe) • Treat ventricular arrhythmia if present • Watch for and treat bacterial embolization of abdominal organs, skin, IVDiscs, CNS, joints, etc. • Watch for and treat immune complex disease

Valvular Endocarditis Prognosis • <20% survival • Antibiotic therapy often required for life • Median survival is 6 days from diagnosis for aortic endocarditis • Survival is longer for mitral endocarditis – LHF due to MR not as severe as Ao. R (Client Handout)

Maximus 18 month old male Boxer Chief Complaint • Drastic and rapid weight loss • Not eating well • Coughing up blood tinged fluid since yesterday Exam, Chest rads, ECG • Similar to Trip, except temp 103. 8 • And BCS 2

Maximus Diagnostics • Blood culture – negative (2 samples 2 hours apart) • Urine culture – Enterobacter susceptible to all • CBC – neutrophilia 23, 100/ul – Mild anemia – PCV 35. 5%

Maximus Diagnostics • General Health Profile, electrolytes – BUN – 55 (n 10 -29) – ALT – 225 (n 10 -120) – Albumin – 2. 2 (n 2. 3 -3. 7) • Urinalysis – USG – 1. 045 – WBC 7 -10/hpf, rare bacteria seen

Maximus Treatment (58 lbs, BCS 2, RR 66) • Antibiotics – IV - ampicillin 750 mg TID, Baytril 150 mg BID x 3 days – IM – ampicillin 750 mg BID, Baytril 150 mg x 3 days – PO – ampicillin 750 mg BID, Baytril 136 mg PO for life • Furosemide – 100 mg IV TID the first day - RR down to 28 – Then 75 mg PO BID • Enalapril – 15 mg PO BID • Pimobendan – 5 mg PO BID

Maximus Treatment – Day 3 – RR 30, eating well • Chest x-rays – Pulmonary edema much improved, but mild amount still present • Continue Furosemide, Enalapril, Pimobandan • Added Spironolactone – 25 mg PO BID

Maximus Diagnostics – Day 5 – RR 36, BP 150 • Chest x-rays - No change • BUN – 43 • Electrolytes - normal Treatment – Day 5 • Continue Furosemide, Enalapril, Pimobendan • Spironolactone – increased to 50 mg PO BID • Added Hydralazine – 12. 5 mg PO BID

Maximus Diagnostics – Day 10 RR 30, BP 135, Wt 61. 8, Temp 103 • Chest x-rays – perihilar edema resolved • BUN – 11, albumin 2. 3 • Electrolytes – normal • CBC – neutrophilia 23, 000/ul Continued this treatment for the rest of Max’s life – 3 months

Summary • • • Power. Point – Cases – Valvular Disease. pdf of Power. Point – Valvular Disease All Audio and Video Files ACVIM Position Statement on CHF Client Handouts – – Endocarditis Valvular Dysplasia Congestive Heart Failure MVD in Cavaliers
- Slides: 74