
Pharmacy Speaks Automation does the evidence back up

#Pharmacy. Speaks Automation – does the evidence back up Hub and Spoke? Gareth Jones

Context • Limited capacity (space and staff) • Growing workload • Innovative technology • Lack of funding • Quality improvement (safety) • Policy-drive to adopt hub and spoke
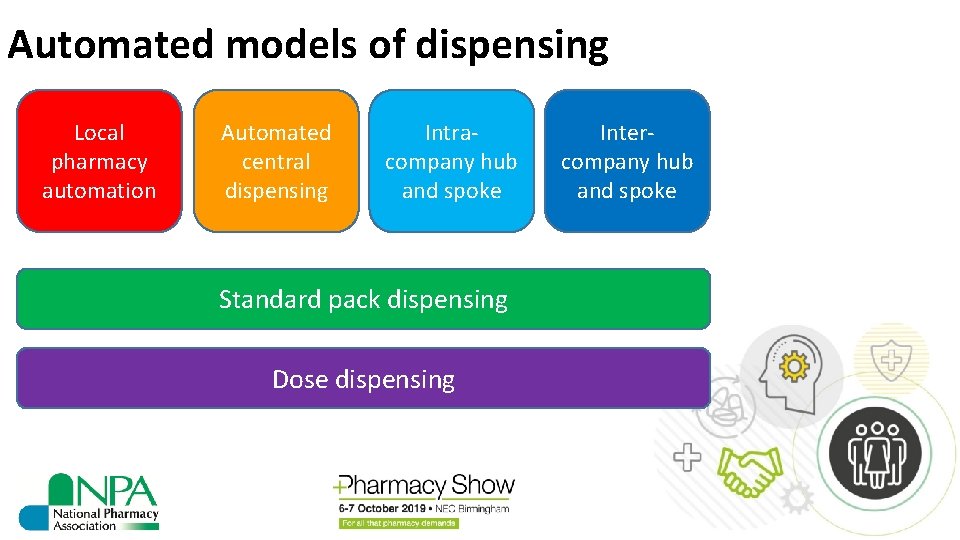
Automated models of dispensing Local pharmacy automation Automated central dispensing Intracompany hub and spoke Standard pack dispensing Dose dispensing Intercompany hub and spoke

Local pharmacy automation

Automated central dispensing

Intra-company hub and spoke

Inter-company hub and spoke • Contract • Competition • Funding • Local co-ops • Regional wholesalers • Verticallyintegrated (VIs) • Buying groups
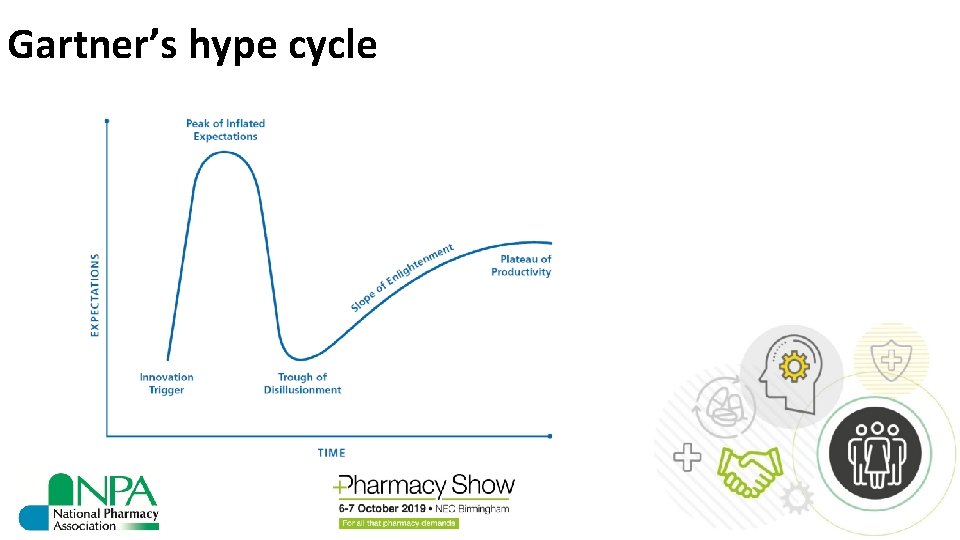
Gartner’s hype cycle

NPA Hub and Spoke T&F Group • Manchester University literature review • Over 400 members responded to survey • Visit to an automated hub • Interviewed 20 experts • Legal opinion from a QC
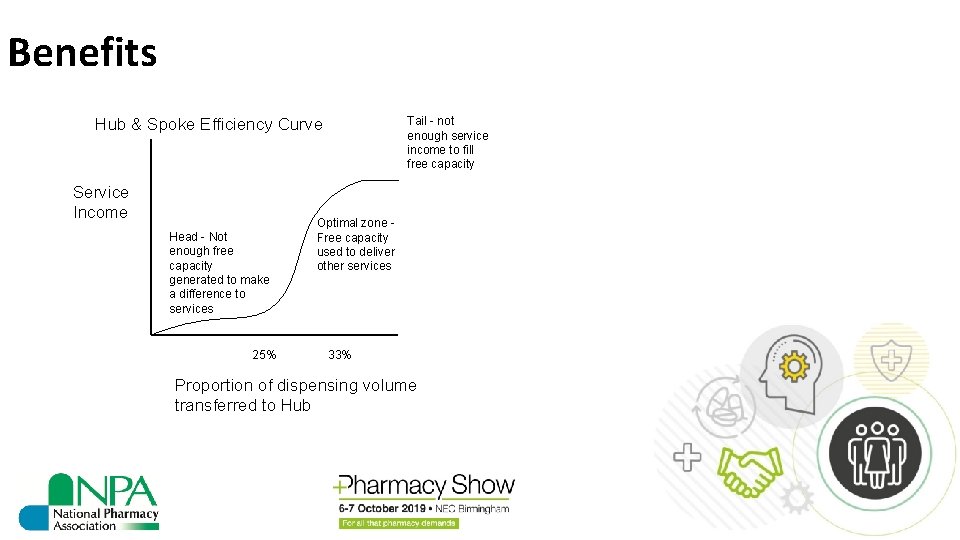
Benefits Tail - not enough service income to fill free capacity Hub & Spoke Efficiency Curve Service Income Head - Not enough free capacity generated to make a difference to services 25% Optimal zone Free capacity used to deliver other services 33% Proportion of dispensing volume transferred to Hub

Centralising the preparation of MDS has enabled us to find a way to still provide this costly service to our patients. However there are costs which increase through hub and spoke. For labour intense services like MDS it works, but it would struggle to work in my opinion for general repeats as these can be completed as efficiently in a branch. In addition sadly most repeat business is less structured in ordering/need.

I run a hub & spoke operation for my own pharmacies. It works well. It has reduced my overall stock holding significantly but not my profitability. However, it hasn't delivered the time savings I was expecting because there is still a lot of work to do in the branch. . .

. . . . we still need to accept the order from the patient for 100% of Rxs, collect 100% of Rxs, reconcile the Rxs with the orders, clinically check them, send them to the hub, receive them from the hub, sort into collection and deliveries, etc. The only thing we save is time in creating the label, sticking the label on the box, and accuracy checking. Everything else is the same. But if I had to outsource to a 3 rd party I wouldn't be able to pay them

Hub and spoke operations will not be able to cope with 'brand intolerances', offer on-the-day advice about stock availability, run back to the surgery to ask why an item hasn't been included or if a dose can be changed, or any of the hundreds of routine interventions that community pharmacies make every day. All of these will throw workload back to GPs where at the moment we are preventing this by liberal applications of common sense and goodwill!

NPA Hub and Spoke T&F Group • Enablers • Electronic repeat dispensing • Original pack dispensing • Contract that protects independents • Professional standards • Expansion in NHS services • Barriers • Supply restrictions (such as DTP and limited wholesaler) • Increases the power of the seller (wholesaler) • EU FMD • New direct and indirect costs to pharmacies and the NHS

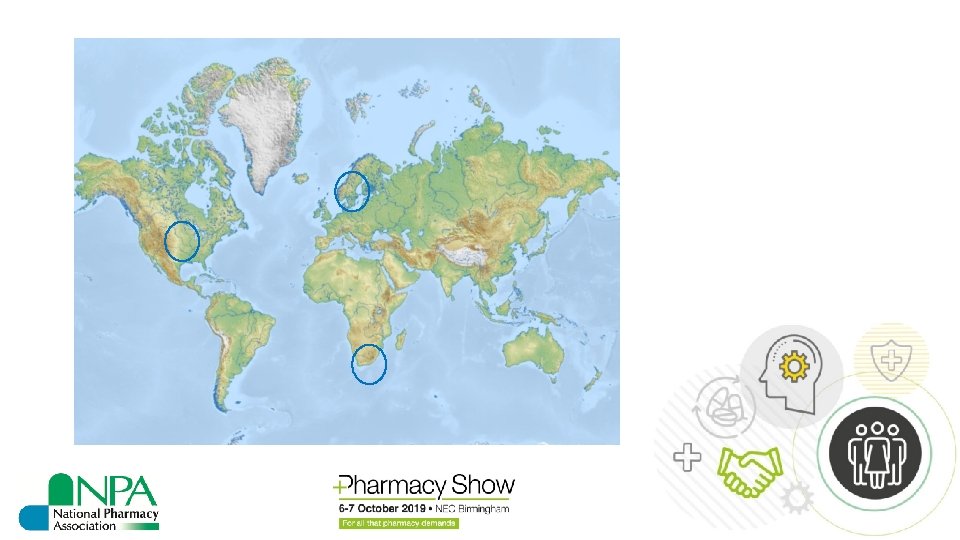

Netherlands • Standard dispensing via hubs is established in the Netherlands – used by most multiples and about one-third of independents • 360, 000 patients received ADD from a hub – pharmacy supported by premium payment

Sweden • ADD is well established in Sweden • Thought to have, per capita, largest number of MDS patients worldwide

Denmark • ADD has been widespread in Denmark since 2003 • Research notes: – The literature is inconclusive as to whether ADD is a safer way of dispensing medicines

USA • “Central fill” permitted since 2003 - 34% of US prescriptions dispensed this way • US dispensing practices are very labour intensive

South Africa • Chronic Dispensing Unit in Cape Town • Serves 350, 000 patients – partially automated
Impact on operations Quality ? Flexibility ? ? Speed ? Dependability ? Cost ?

Is hub and spoke a strategy that independents should pursue? • Strategic objectives • Release capacity to deliver additional services • Improve the efficiency of the service • Improve the quality of the service (patient safety)

Is hub and spoke a strategy that independents should pursue? q. Will it deliver strategic objectives of capacityrelease, efficiency and safety? q. Does it align with the existing capabilities of the pharmacy q. How will internal processes respond? q. Can it be resourced? q. Will the required level of operational performance be delivered? q. Will stakeholder relationships be adversely affected? q. How will it affect financial performance? q. How will it affect the way we compete?

How should we respond to hub and spoke at the current time? 1. Individual decision based on numerous factors (inter or intracompany model, existing capacity, level of efficiency, opportunities for new services, dose dispensing, standard dispensing) 2. Not make assumptions in relation to cost, ability to release capacity or safety

How should we respond to hub and spoke at the current time? 3. NPA continues to research this field, and will offer guidance and seek opportunities to support to members whatever happens
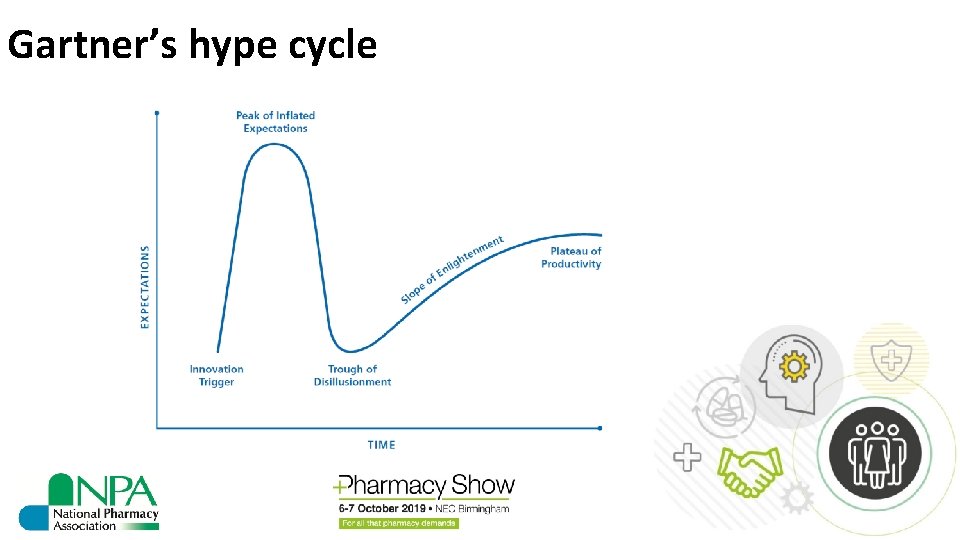
Gartner’s hype cycle

Automation – does the evidence back up Hub and Spoke? g. jones@npa. co. uk @Gareth. NPA
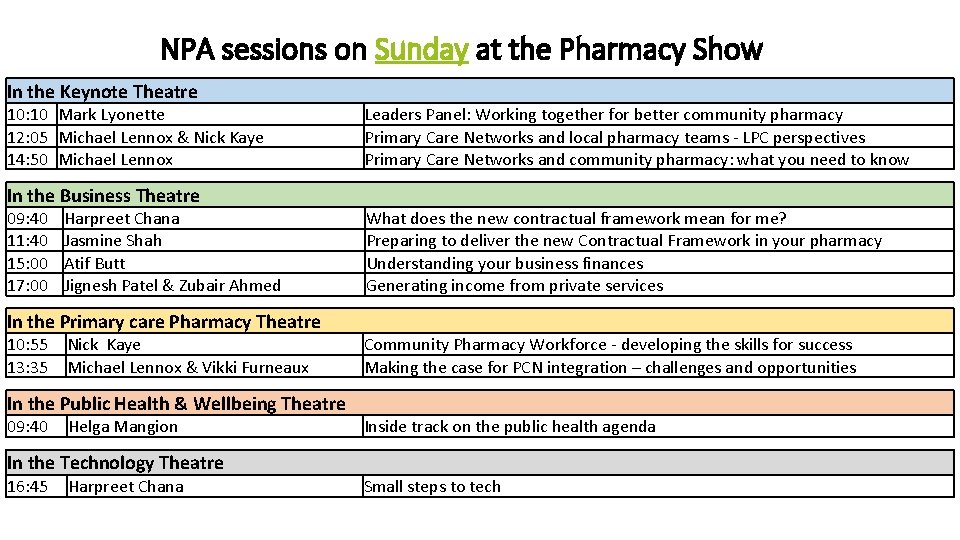
NPA sessions on Sunday at the Pharmacy Show In the Keynote Theatre 10: 10 Mark Lyonette 12: 05 Michael Lennox & Nick Kaye 14: 50 Michael Lennox Leaders Panel: Working together for better community pharmacy Primary Care Networks and local pharmacy teams - LPC perspectives Primary Care Networks and community pharmacy: what you need to know In the Business Theatre 09: 40 11: 40 15: 00 17: 00 Harpreet Chana Jasmine Shah Atif Butt Jignesh Patel & Zubair Ahmed What does the new contractual framework mean for me? Preparing to deliver the new Contractual Framework in your pharmacy Understanding your business finances Generating income from private services In the Primary care Pharmacy Theatre 10: 55 13: 35 Nick Kaye Michael Lennox & Vikki Furneaux Community Pharmacy Workforce - developing the skills for success Making the case for PCN integration – challenges and opportunities In the Public Health & Wellbeing Theatre 09: 40 Helga Mangion Inside track on the public health agenda In the Technology Theatre 16: 45 Harpreet Chana Small steps to tech
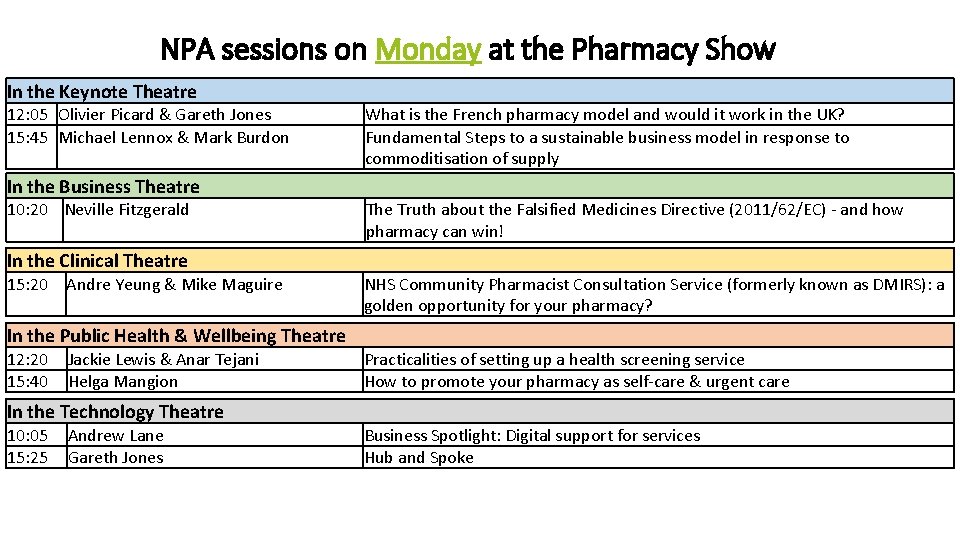
NPA sessions on Monday at the Pharmacy Show In the Keynote Theatre 12: 05 Olivier Picard & Gareth Jones 15: 45 Michael Lennox & Mark Burdon What is the French pharmacy model and would it work in the UK? Fundamental Steps to a sustainable business model in response to commoditisation of supply In the Business Theatre 10: 20 Neville Fitzgerald The Truth about the Falsified Medicines Directive (2011/62/EC) - and how pharmacy can win! In the Clinical Theatre 15: 20 Andre Yeung & Mike Maguire NHS Community Pharmacist Consultation Service (formerly known as DMIRS): a golden opportunity for your pharmacy? In the Public Health & Wellbeing Theatre 12: 20 15: 40 Jackie Lewis & Anar Tejani Helga Mangion Practicalities of setting up a health screening service How to promote your pharmacy as self-care & urgent care In the Technology Theatre 10: 05 15: 25 Andrew Lane Gareth Jones Business Spotlight: Digital support for services Hub and Spoke
- Slides: 32