
Pediatric Board Review Course Pediatric HematologyOncology Kusum Viswanathan

Pediatric Board Review Course Pediatric Hematology/Oncology Kusum Viswanathan, MD Chair, Department of Pediatrics Director, Division of Pediatric Hematology/Oncology Brookdale University Hospital and Medical Center

A newborn baby has a hemoglobin of 14 gm/d. L and the MCV is 82. True statements regarding a newborn baby include all of the following except: 1. This is a normal Hb and MCV for a newborn 2. Feto-maternal hemorrhage can be a cause of anemia 3. A low MCV is suggestive of chronic feto-maternal hemorrhage or Alpha Thalassemia trait. 4. Kleihauer-Betke test looks for the presence of fetal hemoglobin in the mother’s blood 5. The Apt test looks for the presence of adult hemoglobin in the baby’s gastric aspirate

6 week old term infant referred for anemia. Hb 7. 5, Retic 2 %. Mother O+, Baby A -, Direct Coombs + Cord blood Hb 14. 2 g/d. L. Jaundice of 15 mg/d. L at 48 hours of life, recd photo Rx and discharged at 5 days. No complaints, pale, Bili 3. 5, Direct 0. 5. Blood smear shows spherocytes

Most likely explanation for the anemia 1. G 6 PD deficiency 2. Hereditary spherocytosis 3. Physiologic anemia 4. ABO incompatibilty 5. Rh hemolytic disease
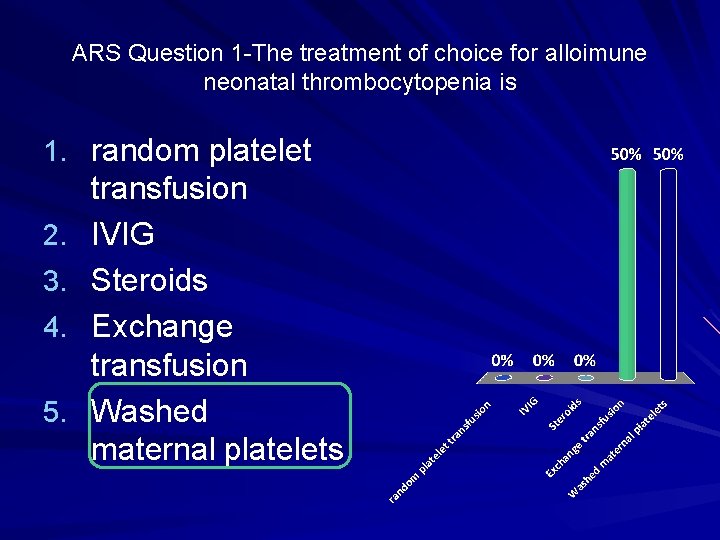
ARS Question 1 -The treatment of choice for alloimune neonatal thrombocytopenia is 1. random platelet 2. 3. 4. 5. transfusion IVIG Steroids Exchange transfusion Washed maternal platelets

Auto-immune Thrombocytopenia True statements regarding Newborn Autoimmune Thrombocytopenia include all except: 1. Occurs in babies born to mothers with ITP/Hx of ITP 2. It is because of passive transfer of antibodies (Ig. M) from 3. 4. 5. mother. The mother can have a normal or low platelet count The nadir occurs a few days after birth Platelets < 50, 00 have a 1% risk of ICH Treatment: IVIG to mother, Fetal platelet counts, C sec, US, IVGG to baby

Allo-Immune Thrombocytopenia Allo or Iso-Immune: Normal platelet count in mother Similar to Rh disease; PL A 1 antigen/ Zw-a negative mother. 97% of population is PL A 1 positive Sensitization early in pregnancy Plt function defect because Anti-PL-A 1 interferes w/aggregation. Severe bleeding more likely; first born affected Recovery in 2 -3 weeks Mother’s washed (PLA 1 neg) platelets; IVIG; Ultrasound; Steroids
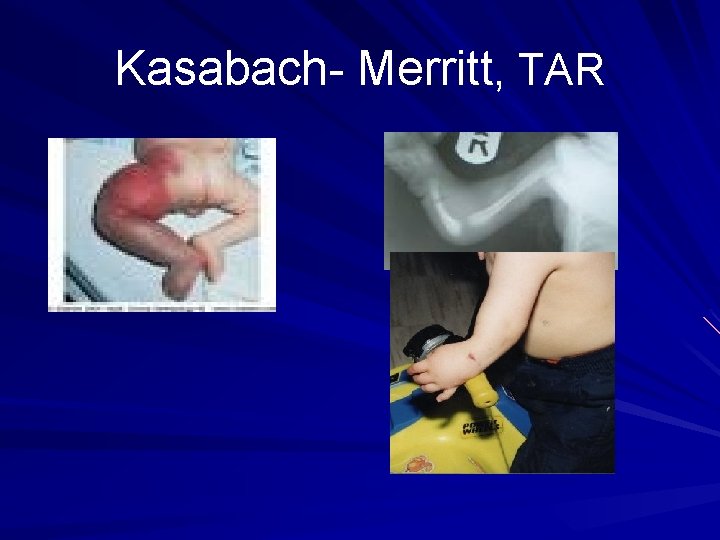
Kasabach- Merritt, TAR

15 month old female presented to the ER with h/o URI, and scattered petechiae and ecchymoses over the body and lower extremities. Physical exam normal, no hepatosplenomegaly. WBC-7, 000, Hb 12. 8 gm/dl, Plts-5, 000, Normal differential- Next step 1. 2. 3. 4. perform a bone marrow aspirate to confirm the diagnosis Non-accidental injury; skeletal survey to rule out bony fractures treatment with either IVIG or anti-D Administer platelet transfusion
Acute ITP Usually acute onset; immune mediated; post viral Peak 2 -5 years of age, PE –no lymphadenopathy (LN), hepatosplenomegaly. CBC- other cell lines normal, large plts on smear Treat if plt< 10, 000 or wet ITP, Treat- IVIG best response, 48 -72 hours; blocks Fc receptors, SE – Anti-D (WIn. Rho)- Rh+ , hemolysis, quick response – Steroids good response, block phagocytosis, reduces antibodies, SE, inexpensive, need BM BM- Increased megakaryocytes, otherwise normal Chronic- If >6 months, F>M, older, unpredictable prognosis
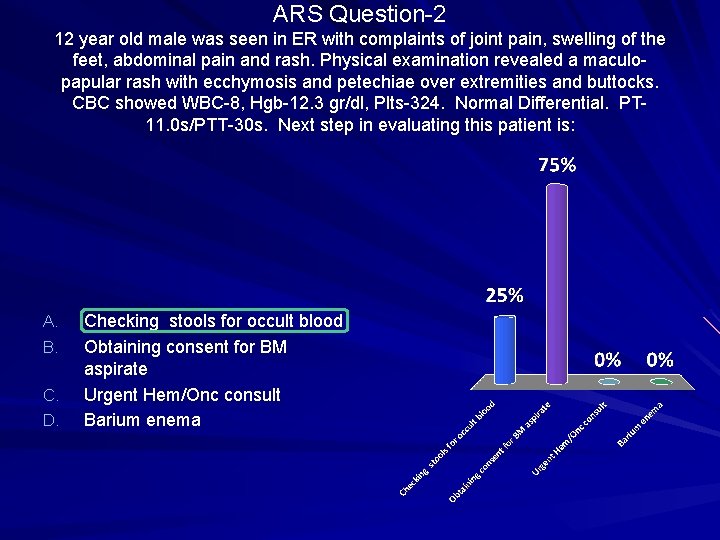
ARS Question-2 12 year old male was seen in ER with complaints of joint pain, swelling of the feet, abdominal pain and rash. Physical examination revealed a maculo- papular rash with ecchymosis and petechiae over extremities and buttocks. CBC showed WBC-8, Hgb-12. 3 gr/dl, Plts-324. Normal Differential. PT 11. 0 s/PTT-30 s. Next step in evaluating this patient is: A. B. C. D. Checking stools for occult blood Obtaining consent for BM aspirate Urgent Hem/Onc consult Barium enema
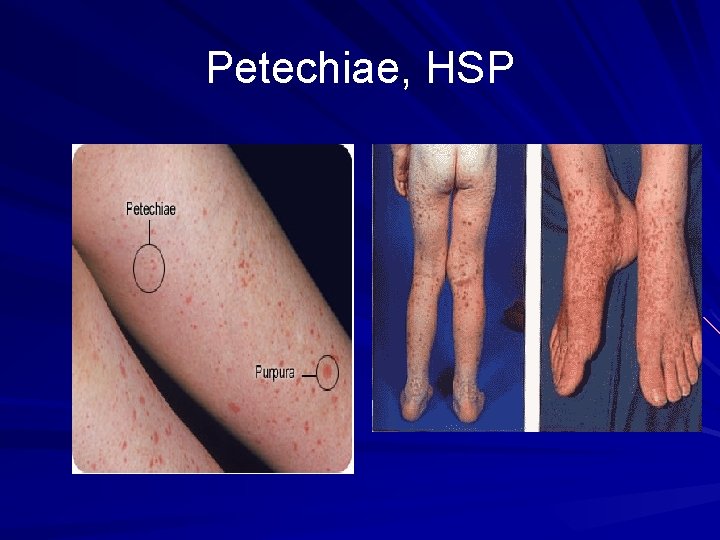
Petechiae, HSP

A 2 year old boy presents for evaluation of a chronic pruritic eruption. H/o recurrent epistaxis, otitis media, and pneumonia P/E reveals erythematous, slightly scaling patches on the trunk and in the antecubital and popliteal fossae. Petechiae too- most suggestive of 1. 2. 3. 4. 5. Acrodermatitis enteropathica Ataxia telangiectasia Atopic dermatitis Langerhans cell histiocytosis Wiskott-Aldrich syndrome
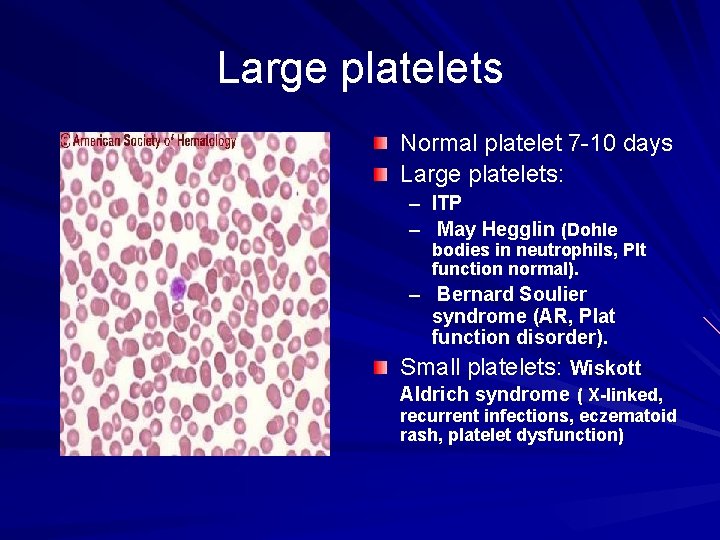
Large platelets Normal platelet 7 -10 days Large platelets: – ITP – May Hegglin (Dohle bodies in neutrophils, Plt function normal). – Bernard Soulier syndrome (AR, Plat function disorder). Small platelets: Wiskott Aldrich syndrome ( X-linked, recurrent infections, eczematoid rash, platelet dysfunction)

ARS-3 --An 18 month old girl brought in for pallor. Normal diet and PMH. She is alert, interactive, only pallor, normal vital signs, No hepatosplenomegaly, lymph nodes or bruises. CBC- Normal WBC, Plt, Hb 4. 5 g/dl, MCV 76, Reticulocyte count 0. 3%. You are considering TEC-Transient Erythroblastopenia of childhood. All are true except: A. B. C. D. E. Patients are often over a year of age 60 % recover MCV and Hb F are high during recovery Treat with red cell transfusions The rbc ADA is normal
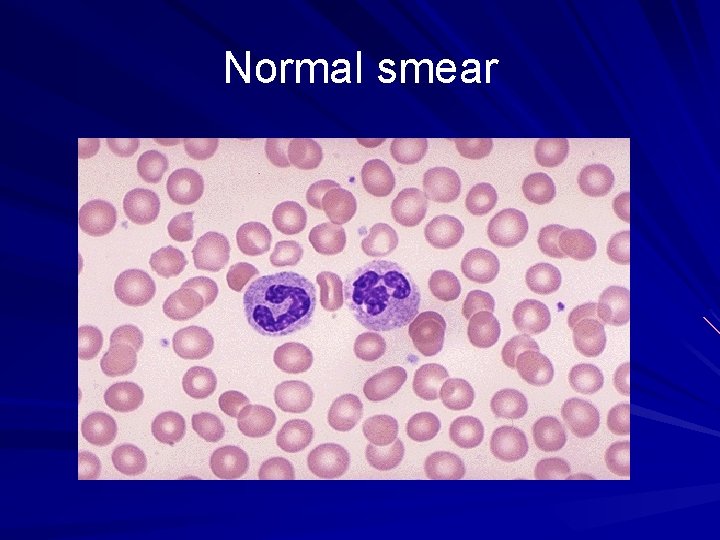
Normal smear

An 8 month old girl with a history of ventricular septal defect and horseshoe kidney presents for a health maintenance visit. Her parents are concerned that she is not feeding well, appearing to become “tired” soon after beginning to breastfeed. She is tachycardic and appears pale. Her hemoglobin level is 3. 8 g/d. L. Peripheral smear reveals macrocytic red blood cells. The bone marrow aspirate shows normal cellularity of the marrow with markedly decreased erythroid precursors. Which of the following findings is most likely to be identified during additional physical examination of this patient? 1. Multiple superficial hemangiomas 2. Cutis aplasia 3. Bifid thumbs 4. Speckled white rings in the periphery of the iris 5. Posterior parietal hair whorl

Microcytic anemia is a characteristic laboratory abnormality of all listed diseases except 1. 2. 3. 4. Iron deficiency Lead poisoning Sickle cell disease Thalassemia trait
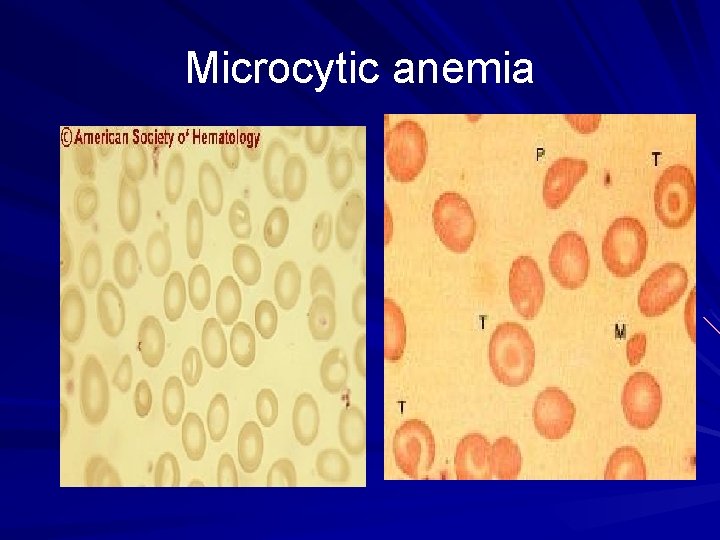
Microcytic anemia

Anemia A blood smear taken from a toddler shows microcytic hypochromic anemia. Iron supplementation therapy is started. When will the reticulocyte response be at maximum? 1. 1 -2 days 2. 5 -7 days 3. 14 -21 days 4. 3 -4 weeks 5. about 6 weeks

Iron deficiency questions Low MCV, low MCHC, low retic, RDW can be normal, Low Iron, Incr TIBC, Transferrin low, Ferritin low Causes: Inadequate dietary intake – Toddlers, too much milk, less solids, Breast fed need iron supplements – Blood loss: Menstrual, GI tract, Meckels, Epistaxis D/D: Thalassemia trait- MCV much lower in prop to anemia Anemia of chronic disease- low Fe, low TIBC, normal /high Ferritin.

ARS Question-4 - 3 year old comes for a routine check and found to be anemic. P/E Normal. CBC Hb 8. 9, MCV 58, Iron levels are normal. Hemoglobin electrophoresis is done and shows Beta Thalassemia trait. All are true except: A. B. C. D. E. The MCV is always low Fetal hemoglobin is often > 2% Hemoglobin A 2 is often > 3. 5% May respond to Iron RDW is usually normal
Beta Thalassemia Minor Quantitative defect in globin chains – Reduced production of Beta chains Hb electrophoresis – Hb A- 2 Alpha, 2 Beta – Hb F- 2 Alpha, 2 Gamma – Hb A 2 - 2 Alpha, 2 Delta Excess Alpha combines with Gamma or Delta- Increased Hb F and A 2. Smear abnormalities significant even with MILD anemia. Anemia Low MCV, normal RDW, normal retic Smear shows aniso and poikulocytosis, target cells, microcytes, misshapen cells, basophilic stippling Hb Electrophoresis: Increased Hb A 2 and/or F. Normal iron studies, no response to iron

Beta Thalassemia Major No production of Beta chains- Chromosome 11 Autosomal recessive 25 % chance with each pregnancy Pre-natal testing for carriers Chorionic villous sampling for diagnosis Transfusion dependent-allows for normal development Pen Prophylaxis, Anti oxidants Splenectomy after age 5 Iron overload- inherent and transfusion Need chelators BMT is a cure
ARS- Q- 5 -4 year old male with no complaints. Routine CBC showed a Hb 10 gm/d. L, MCV 62, RDW 12. 5 , Retic 0. 2%, Normal Iron studies, Hemoglobin electrophoresis was normal with normal Hb A 2 and Hb F. What is the most likely diagnosis? A. B. C. D. E. Hookworm infestation Thallassemia Hereditary spherocytosis GI bleeding

Regarding Alpha Thalassemia All of the statements are true except: 1. It is carried on 4 alleles 2. The severe form is Hydrops fetalis 3. Hemoglobin H disease occurs when 3 alleles are affected 4. Diagnosed by newborn screening when a “fast moving” hemoglobin is noted. 5. Fast moving hemoglobin on newborn screening is made up of a hemoglobin with 4 beta chains

Thalassemia- Alpha Reduced Alpha chains 4 types- carried on 4 allelles. (xx/xx) One absent- Silent carrier (x-/xx) 2 absent- Alpha Thal trait (xx/- - or x-/x-) 3 absent- Hb H disease (x-/- -) Has 4 excess Beta chains) 4 absent- Hydrops fetalis (- -/- -) NB period: Excess Gamma chains form Hb Barts - FAST moving Hb on Newborn screening
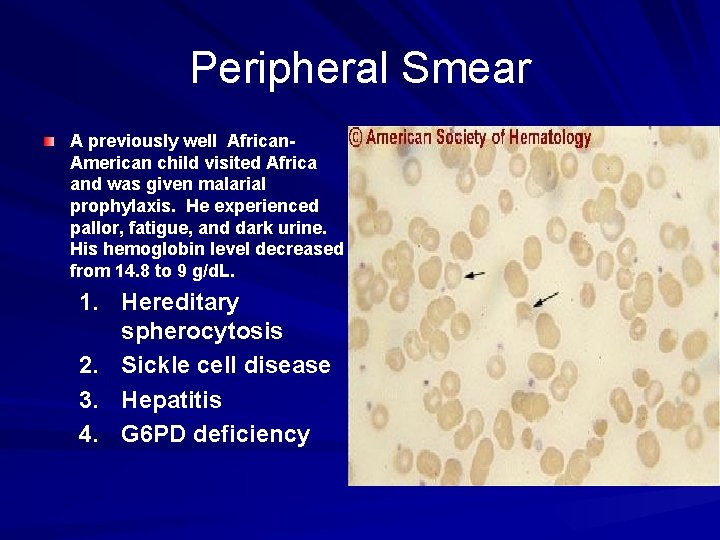
Peripheral Smear A previously well African. American child visited Africa and was given malarial prophylaxis. He experienced pallor, fatigue, and dark urine. His hemoglobin level decreased from 14. 8 to 9 g/d. L. 1. Hereditary spherocytosis 2. Sickle cell disease 3. Hepatitis 4. G 6 PD deficiency

Children with hereditary spherocytosis have all of the listed conditions except 1. positive Direct Coombs 2. splenomegaly, gallbladder stones 3. abnormalities in spectrin and /or ankyrin 4. increased MCHC 5. abnormal osmotic fragility test.

A 6 year old girl who has hereditary spherocytosis presents with a 1 week history of fever. Physical exam reveals abdominal pain, vomiting, fatigue and pallor. Her hemoglobin is typically about 10 g/d. L with a retic count of 9%, but now, her hb is 4 g/d. L and the retic count is 1%. The bilirubin is 1 mg/d. L. Of the following, the MOST likely cause for this girl’s present illness is infection with – – – Coxsackie virus Parvovirus B 19 Epstein-Barr virus Hepatitis A virus Influenza A virus
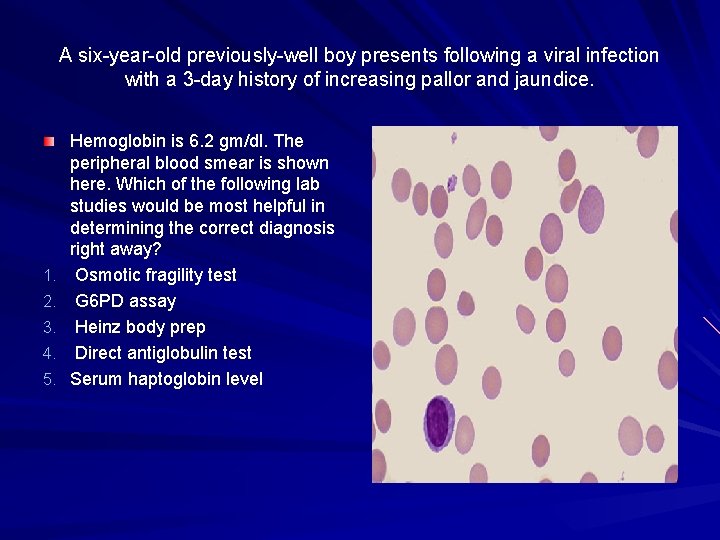
A six-year-old previously-well boy presents following a viral infection with a 3 -day history of increasing pallor and jaundice. 1. 2. 3. 4. 5. Hemoglobin is 6. 2 gm/dl. The peripheral blood smear is shown here. Which of the following lab studies would be most helpful in determining the correct diagnosis right away? Osmotic fragility test G 6 PD assay Heinz body prep Direct antiglobulin test Serum haptoglobin level

A six year-old previously-well girl presents with a three day history of diarrhea and increasing pallor 1. 2. 3. 4. 5. Hb is 6. 2 gm/dl, Plt 40, 000. The peripheral blood smear is shown here. Which of the following tests would be most helpful in determining the correct diagnosis? Serum LDH Bone Marrow aspirate Direct antiglobulin test G 6 PD screening test Serum creatinine

ARS- Question 6 Newborn screening of one of your new clinic patient is reported as follows; Hb A- present, Hb F-present, Sickle hemoglobin- present. Repeat confirmed this. You will explain to the mother that her child has: A. Sickle cell B. C. D. disease Normal pattern for Afro-Americans Thalassemia trait Sickle cell trait.

Question Your state neonatal screening program reports that an infant in your practice has a pattern of hemoglobin F and S on newborn screening. The underlying disorder that would most likely present with this pattern is: 1. Congenital hemolytic anemia. 2. Sickle cell anemia and sickle beta+ thalassemia. 3. Sickle cell anemia and sickle beta 0 thalassemia. 4. Sickle cell anemia (hemoglobin S-C disease). 5. Sickle cell trait.

Newborn Screening Questions You get a call from a frantic parent because she received a letter from the State regarding her baby’s test results on NBS. FS- SS disease, S-B 0 Thal, Sickle cell w/ HPFH. FSA- Sickle B+ thal, Sickle cell trait FSC- SC disease FAS- Sickle cell trait FAC- Hb C trait FAE- Hb E trait FE - Hb EE disease, E-Thal
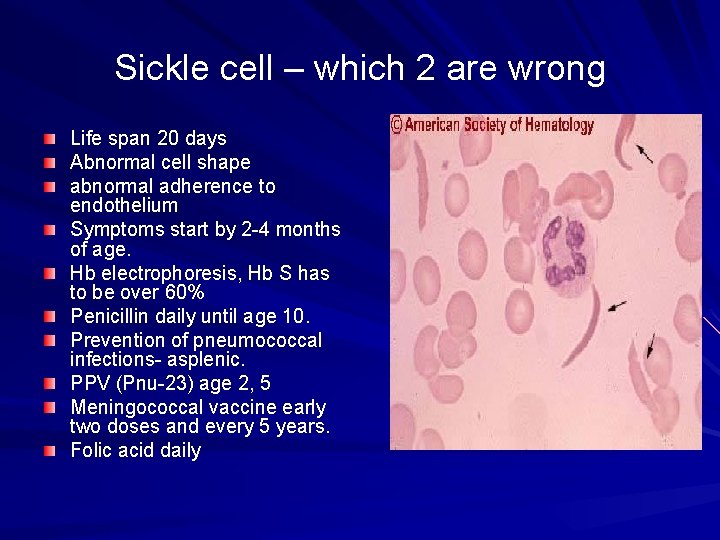
Sickle cell – which 2 are wrong Life span 20 days Abnormal cell shape abnormal adherence to endothelium Symptoms start by 2 -4 months of age. Hb electrophoresis, Hb S has to be over 60% Penicillin daily until age 10. Prevention of pneumococcal infections- asplenic. PPV (Pnu-23) age 2, 5 Meningococcal vaccine early two doses and every 5 years. Folic acid daily

Sickle cell questions Vaso-occlusive crisis New infant born in another country presenting with swollen hands---Dactylitis Aplastic crisis: – low Hb, low retic, Secondary to Parvovirus B 19 infection. Splenic sequestration crisis: – Sudden enlargement of the spleen in SS or older SC patient – – – Rx- Transfuse Teach spleen palpation Splenectomy

Transfusions in Sickle cell All of these have been indications for transfusion in Sickle cell disease except: 1. Acute drop of hemoglobin 2. Aplastic crises 3. Acute Chest Syndrome 4. Leg ulcers 5. Stroke

ARS- Question 7 - The mother of a 10 month old baby with SS disease asks you about prognostic indicators. All of the following indicate likelihood of more severe disease except: 1. High WBC 2. Associated alpha thalassemia trait 3. Low hemoglobin 4. Repeated episodes of dactylitis

True statements regarding Acute Chest Syndrome include all except 1. Presents with a new infiltrate on X-ray 2. Due to infarction, infection, BM fat embolism 3. Treat with antibiotics to cover pneumococcus, Mycoplasma, Chlamydia 4. Treat with bronchodilator, Incentive spirometry, transfusion 5. Intensive hydration is important

TCD- Transcranial Doppler A routine TCD on a 4 year old patient with SS disease shows a Cerebral blood flow (CBF) of 210 cm/second. What is the next step? STOP studies- STOP I and II

ARS-Question 8 -According to the STOP protocol all children with abnormal TCD require enrollment in hypertransfusion protocol till (choose one) 1. Repeat TCD is 2. 3. 4. normal Continue indefinitely the child reaches 18 years MRA/MRI are reported normal

True statements about Sickle cell and Hydroxyurea are all except 1. 2. 3. 4. 5. FDA approved for children Increases hemoglobin F level Increases hemoglobin Decreases WBC – ancillary effect Reduces number of ACS, VOC

A healthy 5 year old boy- 2 day hx of fever, P/E normal No hepatosplenomegaly, LN, no focus of infection. CBC WBC 3, Neutrophils 25 %, Hb 12, Platelet 200 X 109/L, ANC 750. Most appropriate step is 1. Amoxicillin for 10 days 2. G- CSF for 10 days. 3. BM aspirate 4. Refer to a hematologist 5. Repeat CBC in 1 -2 weeks

Neutropenia A 2 -year-old boy has had several 10 -day-long episodes of fever, mouth ulcerations, stomatitis, and pharyngitis. These episodes have occurred at about monthly intervals. Absolute neutrophil counts (ANC) have been 50/mm³on day 1 of each illness, 500/mm³ on day 10, and 1, 500/mm³ on day 14. 1. 2. 3. 4. 5. Among the following, the MOST likely cause for the findings in this patient is chronic benign neutropenia cyclic neutropenia Schwachman-Diamond syndrome severe congenital neutropenia transient viral bone marrow suppression

PT, PTT If the PTT is prolonged, you can do a mixing study. Mix patient plasma with equal amount of normal plasma and repeat the test. All of the following are true except If the PTT corrects after a mixing study, indicates that it is because of a deficiency in factor. 2. If the PTT does not correct after a mixing study, indicates that it is because of a circulating anti-coagulant 3. If the PTT corrects, then do a Factor VII assay 4. If the PTT corrects, do a Factor VIII, IX, XI assay 1.

A healthy 2 -day-old boy born at term undergoes circumcision. Bleeding noted at the site 10 hours after the procedure and increased steadily over the past 4 hours. Findings on exam are unremarkable except for bleeding along 2 to 3 mm of the surgical site; no petechiae or purpura. 1. Disseminated intravascular coagulation 2. Factor VIII deficiency hemophilia 3. Immune thrombocytopenic purpura 4. Neonatal alloimmune thrombocytopenia 5. Von Willebrand disease

Hemophilia All are true for Hemophilia except 1. One unit/kg of Factor VIII increases the level to 2%. 2. The half life of Factor VIII is 12 hours 3. Inheritance is X-linked recessive 4. Severe Hemophiliacs have a Factor level of 10 % 5. 30% develop inhibitors

Hemophilia Questions Factor VIII deficiency (Hemophilia A)-85% – X-linked recessive, Carriers asymptomatic – Severe<1%, Moderate 1 -5, Mild 6 -30 % – Treat Recombinant Factor VIII 1 unit/kg raises factor level by 2 %. Half life 12 hrs. Joint bleeds need 100%, muscle bleeds 50 %. – DDAVP for mild cases. – 30 % develop inhibitors after infusions with concentrate (Approx 50 infusions) Factor IX deficiency (Hemophilia B) – X-linked recessive, less common

A patient with Hemophilia A has asked you about the possibility of his children being affected with the disease. His partner is normal 1. 2. 3. 4. There is a 50 % chance that his sons will have the disease. There is a 50 % chance that his daughters will be carriers There is a 100 % chance that his sons will have the disease There is a 100 % chance that his daughters will be carriers

Case 13 year old girl just started her periods and has been bleeding for the past 16 days. She has used 14 pads a day and is tired. Her vital signs are stable, Hb 9. 5, PTT normal. The mother had heavy periods and her 6 year old brother has nose bleeds for the past 2 years.
ARS- Question 9 She was diagnosed with Type 1 Von Willebrand’s disease. The preferred treatment for VWD Type 1 is: A. Factor VIII B. C. D. E. replacement FFP Cryoprecipitate DDAVP Plasma exchange

The most common cause of familial predisposition to thrombosis is 1. 2. 3. 4. 5. Hemophilia antibodies Protein C deficiency Protein S deficiency Factor V Leiden mutation Antithrombin III deficiency

Tests performed on donated units of blood 1. 2. 3. 4. 5. All units are tested only for hepatitis B and C All units are tested only for human immunodeficiency virus (HIV) All units are tested for HIV, hepatitis B &hepatitis C all units are tested for HIV, hepatitis B, hepatitis C, sickle cell trait, cytomegalovirus, & EBV Only units obtained from donors who have one or more risk factors are screened for HIV, all units are tested only for hepatitis B and C
Transfusion IRRADIATED BLOOD products are required for each of these patients except: 1. Children with leukemia on chemotherapy 2. Sickle cell patients with Acute Chest Syndrome in PICU 3. Bone marrow transplanted patients 4. Preterm baby with RDS
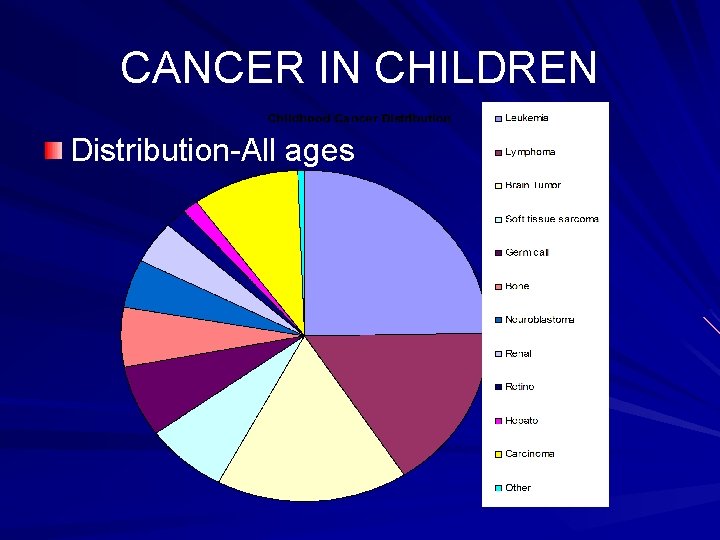
CANCER IN CHILDREN Distribution-All ages

A 6 -year-old girl has aching in her arms, legs, and back for > 2 weeks. She has a low grade fever. P/E shows the tip of a spleen. Results of laboratory tests include hemoglobin, 9. 4 g/d. L; WBC, 5, 600/mm³ with no abnormal cells noted on smear; and platelet count, 106, 000/mm³. You suspect leukemia. True statements about Leukemia include all of the following except: 1. 2. 3. 4. 5. Normal to see up to 5% blasts in the peripheral smear Diagnosis is made if there are >25 % blasts in the Bone marrow Single most common childhood cancer Peak age 2 -5 years More likely in patients with. Trisomy 21, Ataxia-Telangiectasia, Bloom syndrome, Kostmann’s, Monosomy 7, DBA, Fanconi anemia
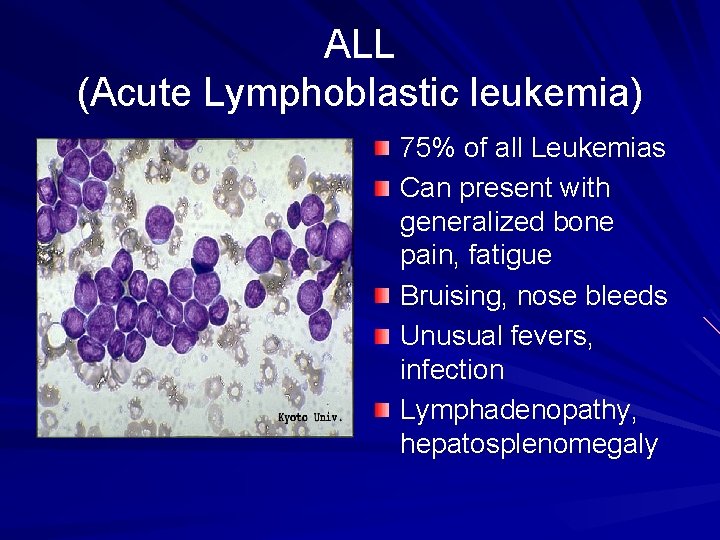
ALL (Acute Lymphoblastic leukemia) 75% of all Leukemias Can present with generalized bone pain, fatigue Bruising, nose bleeds Unusual fevers, infection Lymphadenopathy, hepatosplenomegaly

ALL Treatment Induction: 4 -6 weeks, Consolidation /delayed Intensification: 6 -12 months; rotating drugs. Maintenance : Daily oral 6 -MP, weekly MTX, Monthly pulses of Vincristine and Steroid. Imatinib mesylate-Tyrosine Kinase Inhibitor- Ph Chromosome positive patients CNS prophylaxis: Intrathecal chemo CNS Therapy: RT + Intensive systemic chemo Testicular disease: RT SANCTUARY- CNS, Testis

ARS- Question 10 Acute Lymphoblastic Leukemia. L A good prognostic feature of ALL is: A. High WBC B. Hyperdiploidy (>50 C. D. E. Chromosomes) Children < 1 year of age Remission by 6 weeks T cell origin

ALL- Fever A 5 year old boy who is receiving maintenance chemotherapy for acute lymphoblastic leukemia presents with a fever of 102. 2 F and chills of 1 day’s duration. He denies having a headache, URIsymptoms, vomiting, diarrhea, or abdominal pain. Physical examination reveals an ill-appearing child who has tachycardia but no obvious focus of infection. His skin is flushed, and he has delayed capillary refill. Results of laboratory evaluation include: WBC 1 x 10³/ mcl, Hb 8. 5 g/d. L, plt count 90 x 103/ mcl, and absolute neutrophil count, 200/ mm 3. Of the following, the MOST likely cause of his fever is a. Cytomegalovirus infection b. Disseminated Aspergillus infection c. Gram-negative bacteremia d. Haemophilus influenzae meningitis e. Parvovirus B 19 infection

Gleevec (Imatinib) is a revolutionary novel medication for treatment of Ph + CML. Pharmacologically it belongs to this group of medications : 1. Methylxanthines 2. HDAC inhibitors 3. Anthracyclines 4. Tyrosine kinase inhibitors.

Hodgkin’s Lymphoma 1. 2. 3. 4. 5. 16 year old male presents with a painless swelling in the supraclavicular region. Biopsy shows Hodgkin’s disease Stage 2. All are true except: Presence of “B” symptoms is worse for prognosis ” B” symptoms are fever, increasing size of mass Staging depends on whether it is on one or both sides of the diaphragm Sperm banking should be recommended Second malignancy can occur in patients who receive combination chemo and RT

Brain Tumors- Important to know 20% of all malignancies in children Age 3 -7 years Most often infratentorial Sx: Persistent vomiting, headache, gait imbalance, diplopia, ataxia, vision loss, school deterioration, growth deceleration Associations with Inherited Genetic disorders: – Neurofibromatosis, Tuberous sclerosis, Von. Hippel-Lindau disease, Li-Fraumeni (glioma), Turcot syndrome
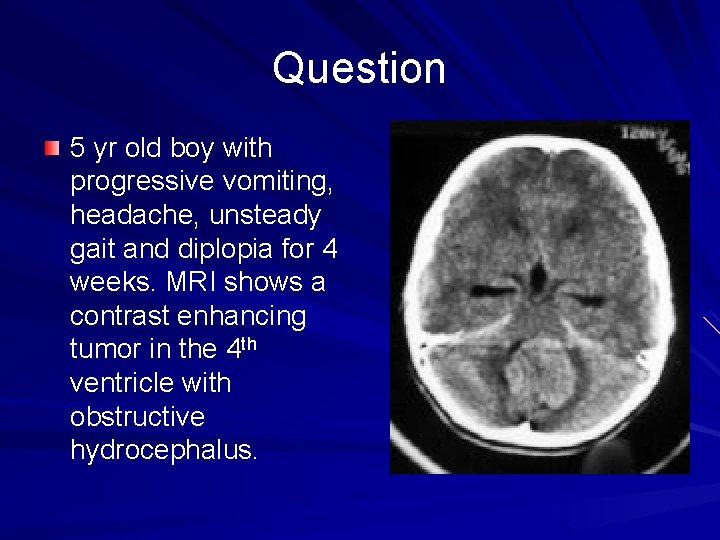
Question 5 yr old boy with progressive vomiting, headache, unsteady gait and diplopia for 4 weeks. MRI shows a contrast enhancing tumor in the 4 th ventricle with obstructive hydrocephalus.

Question Which of the following statements regarding Medulloblastoma is not true? 1. Most common malignant brain tumor in childhood 2. Often presents with increased intracranial pressure 3. Radiation therapy is not recommended since the tumor is not radio-sensitive 4. Exclusively located in the cerebellum 5. Can spread to the spine
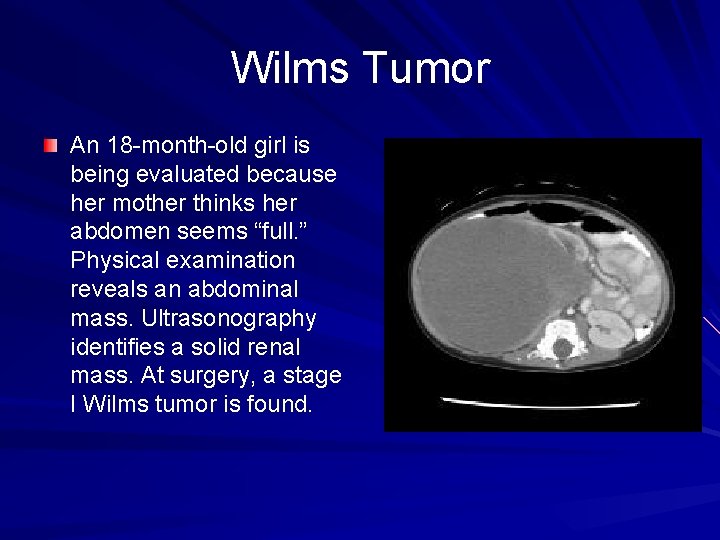
Wilms Tumor An 18 -month-old girl is being evaluated because her mother thinks her abdomen seems “full. ” Physical examination reveals an abdominal mass. Ultrasonography identifies a solid renal mass. At surgery, a stage I Wilms tumor is found.

Stage I Wilms Chance of 4 -year survival is CLOSEST to 1. 2. 3. 4. 5. 30% 45% 60% 75% 95%

ARS- Question 11 Congenital anomalies associated with Wilms tumor include all of the following except 1. Polydactyly 2. Aniridia 3. Hemihypertrophy 4. Cryptorchidism 5. Denys-Drash syndrome

Scrotal mass A 9 year old previously healthy male presents with an increasing mass in the scrotum. It can be any of the following except: 1. Para-testicular Rhabdomyosarcoma 2. Testicular Teratoma 3. Torsion of testis 4. Varicocoele

Rhabdomyosarcoma Painless non tender mass 60% under age 6 Sites: head & neck, GU, Extremities, mets lungs. Majority sporadic, associations: B-W, Li Fraumeni, NF 1 Types: – Embryonal 70%, better prognosis – Alveolar 30 %, trunk, worse prognosis Treatment: Surgery, Chemo, local control RT
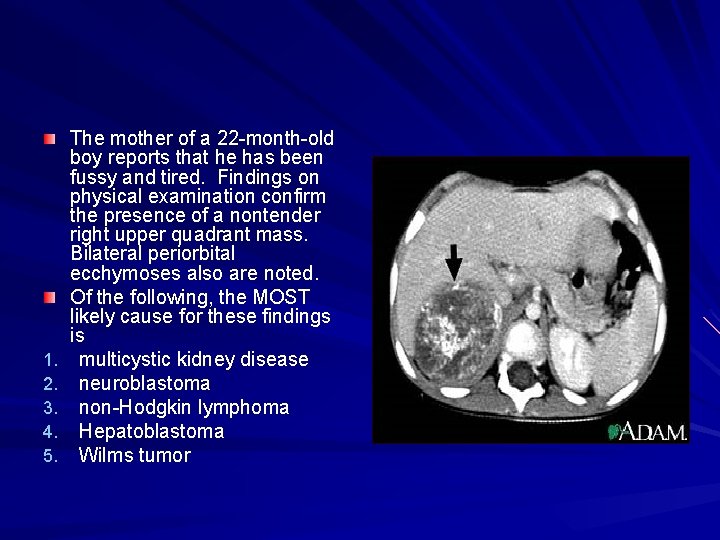
1. 2. 3. 4. 5. The mother of a 22 -month-old boy reports that he has been fussy and tired. Findings on physical examination confirm the presence of a nontender right upper quadrant mass. Bilateral periorbital ecchymoses also are noted. Of the following, the MOST likely cause for these findings is multicystic kidney disease neuroblastoma non-Hodgkin lymphoma Hepatoblastoma Wilms tumor

All statements are true about Neuroblastoma except: 1. 2. 3. 4. 5. Most common extra-cranial solid tumor Prognosis worse with N-myc oncogene amplification and tumor diploidy Most common cancer in the first year of life Frequent in <4 years, 97 % cases by 10 years Infants with localized primary tumor with dissemination limited to skin, liver and/or bone marrow known as Stage IVS require intensive chemotherapy.

Case A 16 year old male comes in because he fell in the supermarket. P/E shows a small painless mass on the medial aspect of the knee. • X ray shows a fracture and a lytic sunburst pattern. (periosteal elevation)-OS • Xray shows an onion peel appearance- ES • Xray- radioluscent, sharp, rounded lesion < 2 cm with reactive sclerosis- Osteoid Osteoma
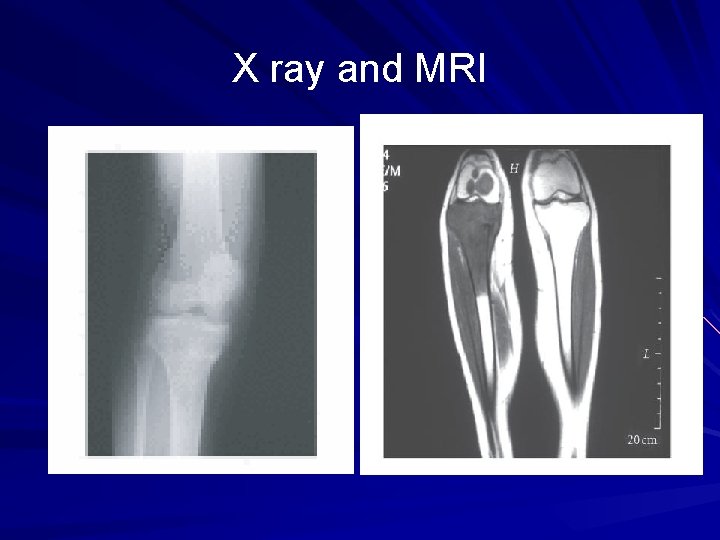
X ray and MRI
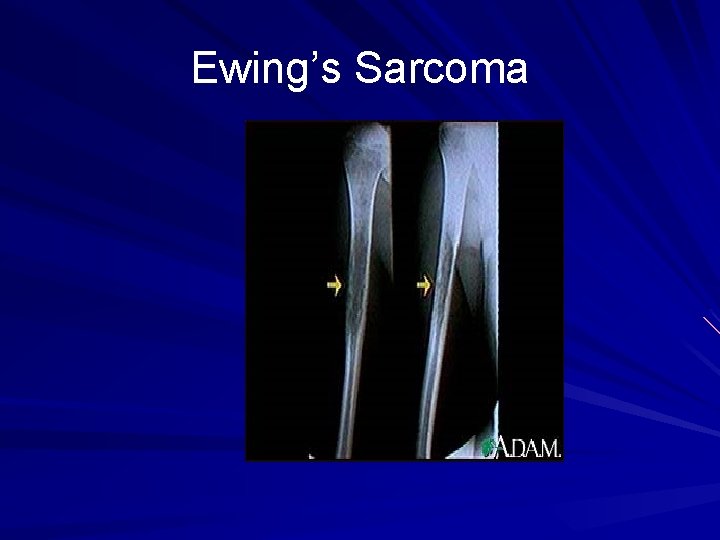
Ewing’s Sarcoma
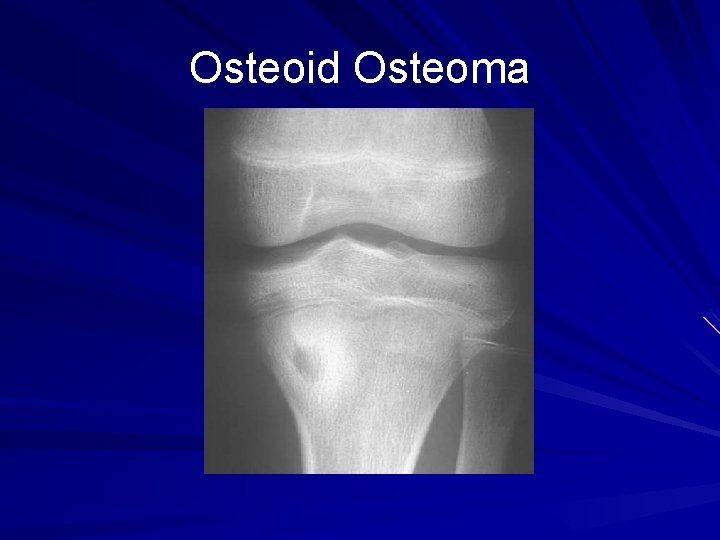
Osteoid Osteoma

Question During your evaluation of an infant in the nursery, you note that the red reflex in one eye seems paler than in the other. Of the following, the MOST appropriate next step is to a. Apply a cycloplegic to the infant’s eyes for examination before discharge b. Perform the corneal light reflex test c. Perform the cover-uncover test d. Re-evaluate the red reflex in 1 to 2 weeks e. Refer the infant to a pediatric ophthalmologist
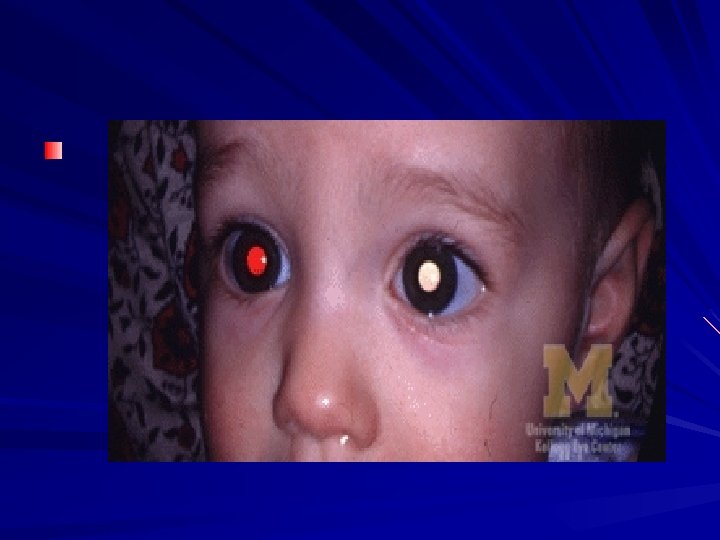

Retinoblastoma- need to know Presentation: Leukocoria (cats eye reflex), dilated pupil, esotropia, strabismus Unilateral 75 % (could be hereditary/non) – 60 % unilateral and non hereditary – 15 % unilateral and hereditary (RB 1 mutation) Bilateral 25 % – 25 % are bilateral and hereditary, have RB 1 mutation – Earlier age, 11 mos, Can develop in each eye separately – Higher incidence of sarcoma, melanoma, brain tumors.

A child with ALL was started on chemo. She had a WBC 82, 000, Hb 9 gm, plt ct 45, 000. She develops tumor lysis syndrome. Which depicts Tumor lysis 1. K high, P high, LDH normal, Na high 2. K high, P normal, LDH high, Na normal 3. K normal, P high, LDH high, Na high 4. K normal, P normal, LDH high, Na normal 5. K high, P high, LDH high, Na normal.

Chemotherapy-Side effects that you need to know Anthracyclines: Cardiac toxicity Vincristine: foot drop, peripheral neuropathy Cisplatinum: kidney, deafness Methotrexate, 6 MP: Liver toxicity Bleomycin: Pulmonary fibrosis Asparaginase: Pancreatitis, Coagulopathy Etoposide (VP-16): Secondary AML Cyclophosphamaide: Hemorrhagic cystitis (MESNA as Uroprotector) and Infertility

16 -year-old girl, completed therapy at age 8 for Hodgkins disease with Involved field RT and chemo. She now develops petechiae, purpura, lymphadenopathy and hepatosplenomegaly. Lab include: plt 12, 000, Hb 8. 0 gm/d. L; and WBC 13, 000/mm³. She has…. AML as a second malignancy Disseminated varicella Drug-induced ITP Late-onset aplastic anemia due to chemotherapy 5. Viral-induced ITP 1. 2. 3. 4.

You are evaluating a 9 year old child for short stature. She was treated at 3 yrs of age for Acute lymphoblastic leukemia, received cranial RT. Her height is < 5 th percentile and she is Tanner stage I. Most likely to have an abnormal test of 1. Growth hormone 2. Estradiol 3. Follicle stimulating hormone 4. Gonadotropin releasing hormone 5. Thyroid stimulating hormone

ARS Question- A 16 year old boy is receiving chemo for Rhabdomyosarcoma. He received a year of cycles of Vincristine, Actinimycin-D and Cyclophosphamide. Most likely endocrinologic late effect of this therapy 1. Growth hormone deficiency 2. Hypothyroidism 3. Impotence 4. Infertility 5. Osteoporosis

GVHD ( Graft vs Host disease): All are true except 1. It is the reaction of the donor lymphocytes 2. 3. 4. 5. against the host. Acute GVHD starts within the first 100 days and chronic is after 100 days. Affects the skin, liver and GI tract Irradiation of blood products does not help Complete HLA matching prevents GVHD
- Slides: 86