
PAROTID TUMORS Dr Ashith Shetty ModeratorDr Anand I



















































- Slides: 61
PAROTID TUMORS Dr. Ashith Shetty Moderator-Dr. Anand I. P
History Thomas Wharton, a London physician, described the submandibular duct. n Neils Stensen discovered the parotid duct in 1660. n John Hunter resected a parotid tumor in 1785. n Thomas Cawardine, a member of the surgical staff of the Bristol Royal Infirmary first suggested the facial nerve be identified. n
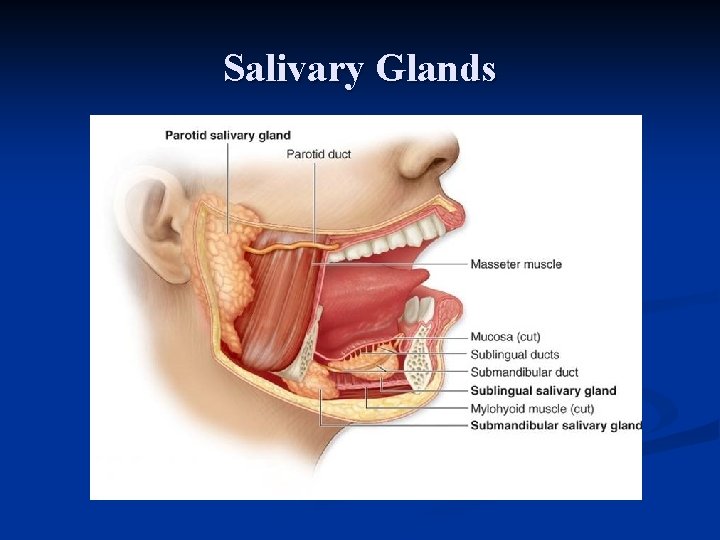
Anatomy Parotid gland is the largest serous salivary gland is also called the queen of the face n Parotid; para-around ; otic-ear n They produce saliva which keeps the oral cavity moist, helps in chewing and swallowing and also contain enzymes that aid digestion. n
Salivary Glands
n Largest of the three salivary glands, weighing from 14 -28 g. n Situated below the external acoustic meatus, between the ramus of mandible and mastoid process with the sternocleidomastoid muscle. n The investing layer of the deep cervical fascia splits to form a capsule; parotid capsule, and is attached above to the zygomatic arch.
n The gland is divided into 2 parts: Superficial part(80%)- overlies the masseter and mandible n Deep part(20%)-lies behind the mandible and medial pterygoid muscle n
n The parotid duct (Stensen’s duct), 5 cm in length, emerges from the middle of the anterior border of the gland, runs over masseter muscle, passes through buccinator muscle and opens into the oral mucosa opposite to the crown of upper 2 nd molar n An accessory part of the parotid gland if present is usually found adjacent to the parotid duct in the buccal space
n Structures within the parotid gland (from deep to superficial): External carotid artery, maxillary artery, superficial temporal artery, posterior auricular artery, transverse facial artery n Retromandibular vein formed by fusion of maxillary and superficial temporal veins n Facial nerve with its branches n
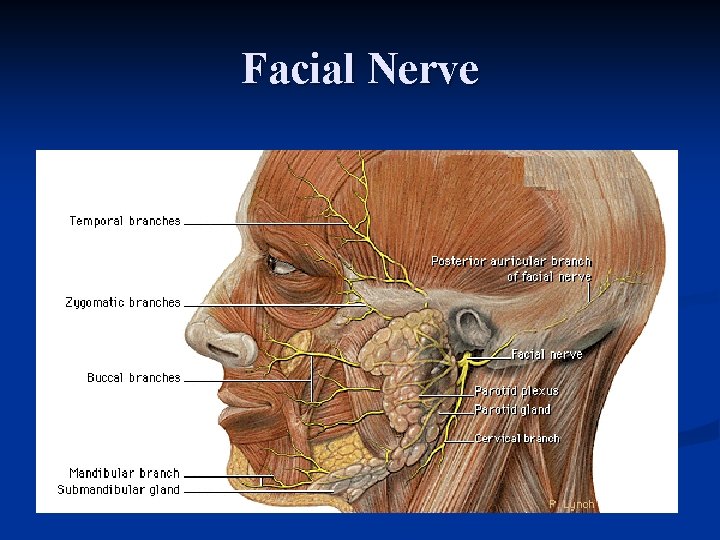
n Facial nerve: Emerges from stylomastoid foramen lying between external auditory meatus and mastoid process n Passes around the neck of the condyle of mandible and becomes superficial, later dividing into temporofacial and cervicofacial branches which in turn divides into many branches n Some of these may be interconnected as pes anserinus n Branches are- temporal, zygomatic, buccal, mandibular and cervical n
Facial Nerve
Facio-venous plane of Patey is of surgical importance. n The facial nerve along with the retromandibular vein is present in this plane. n
n Blood supply: Arterial- external carotid artery and its branches n Venous- external jugular vein n n Nerve supply: Parasympathetic nerves- is secretomotor from auriculotemporal n Sympathetic is vasomotor from plexus around the external carotid artery n Sensory nerve comes from the auriculotemporal nerve n n Lymphatic drainage: parotid nodes
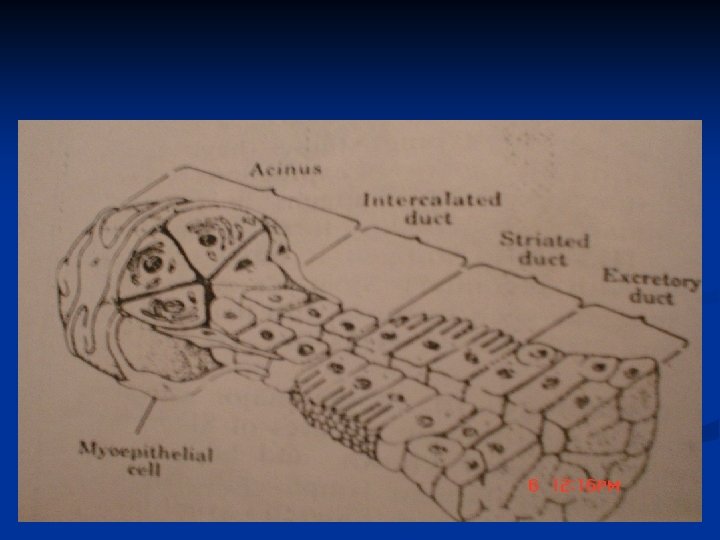
Histology n In major salivary glands, both serous and mucous cells are arranged into acini, which are drained by series of ducts- an intercalated duct that drains into a striated duct, which empties into an excretory duct n Contractile myoepithelial cells surround acini and intercalated ducts- help in draining saliva n Serous acini predominate in parotid gland n Mucinous acini abundant in sublingual and minor salivary glands n Serous and mucous acini in submandibular gland
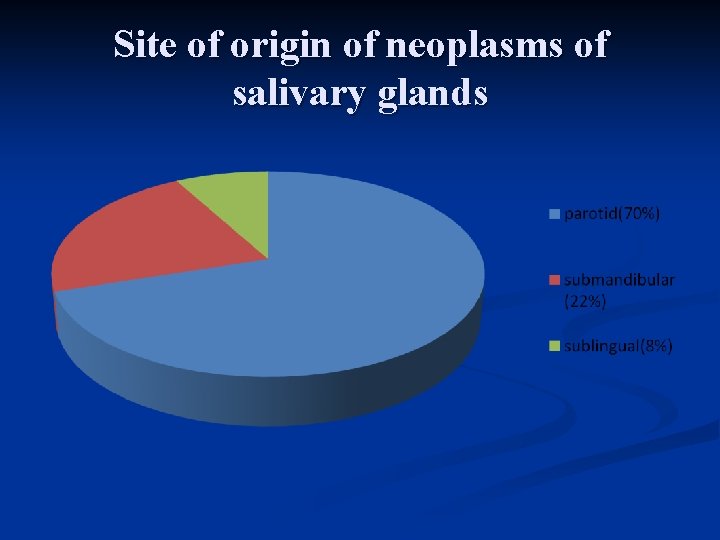
INCIDENCE Majority of the salivary gland tumors arise from the parotid gland n Highest incidence seen in the Eskimos of Greenland n
Site of origin of neoplasms of salivary glands
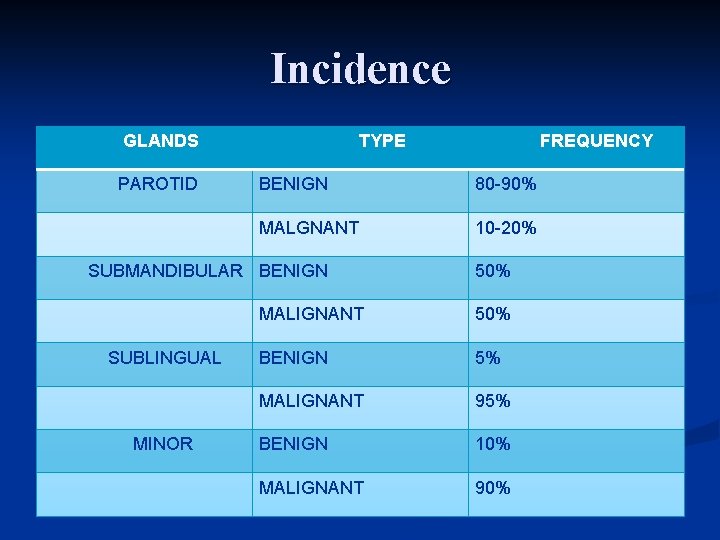
Incidence GLANDS PAROTID TYPE BENIGN 80 -90% MALGNANT 10 -20% SUBMANDIBULAR BENIGN SUBLINGUAL MINOR FREQUENCY 50% MALIGNANT 50% BENIGN 5% MALIGNANT 95% BENIGN 10% MALIGNANT 90%
Etiology 1. Radiation n 2. Viruses n 3. Ionizing radiation Ultraviolet radiation Age of onset- 12 - 16 years after exposure Role of Ebstein-Barr virus Genetic factors
4. Others n n n Occupational exposure- asbestos and rubber industries Hormonal effect- women with history of early menarche and nulliparity Warthin’s tumor strongly associated with cigarette smoking
Classification A. EPITHELIAL (90%) 1. n n n 2. n n n BENIGN PLEOMORPHIC ADENOMAS WARTHIN’S TUMOR OXYPHIL ADENOMA MALIGNANT MUCOEPIDERMOID CARCINOMA ADENOID CYSTIC CARCINOMA EPIDERMOID CARCINOMA UNDIFFERENTIATED CARCINOMA ARISING FROM PLEOMORPHIC ADENOMA
B. NON-EPITHELIAL TUMORS n n n HEMANGIOMA FIBROMA LIPOMA LYPHANGIOMA LYMPHOMA SARCOMA C. METASTATIC TUMORS
WHO CLASSIFICATION 1. ADENOMAS n n n 2. PLEOMORPHIC ADENOMA MYOEPITHELIOMA (MYOEPITHELIAL ADENOMA) BASAL CELL ADENOMA WARTHIN’S TUMOR ONCOCYTOMA (OXYPHIL ADENOMA) CARCINOMAS n n n ACINIC CELL CARCINOMA MUCOEPIDERMOID CARCINOMA ADENOID CYSTIC CARCINOMA
ADENOCARCINOMA n CARCINOMA IN PLEOMORPHIC ADENOMA n SQUAMOUS CELL CARCINOMA (EPIDERMOID CA) n UNDIFFERENTIATED CARCINOMA n 3. 4. 5. 6. 7. NONEPITHELIAL TUMORS MALIGNANT LYMPHOMAS SECONDARY TUMORS UNCLASSIFIED TUMORS TUMOR LIKE LESIONS
PRESENTATION Complex and diverse group of tumors n Diversity of histopathologic patterns n Different degree of aggressiveness and pattern of spread n
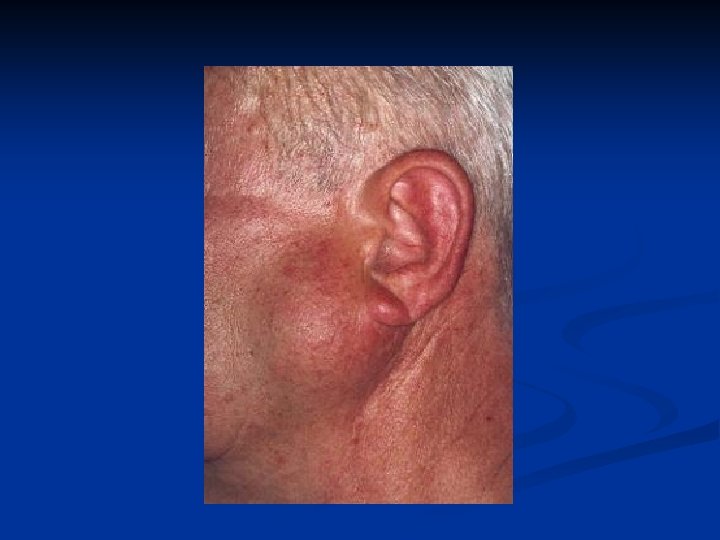
Presentation n n Both benign and malignant tumors of parotid gland usually present as a painless swelling Growth of these tumors is so slow that patients often wait many months or years before seeking attention Raised ear lobule Cannot be moved above the zygomatic arch- curtain sign Deviation of uvula and tonsil towards midline in case of deep lobe involvement
n Features indicative of malignancy facial nerve paresis or paralysis n Pain n Fixation of mass to overlying skin or underlying structures n Associated cervical adenopathy n
Pleomorphic adenoma The most common benign salivary gland tumor n Also known as mixed tumor n More common in females, 3 rd to 4 th decade n 80% are within the superficial lobe n
Pleomorphic Adenoma
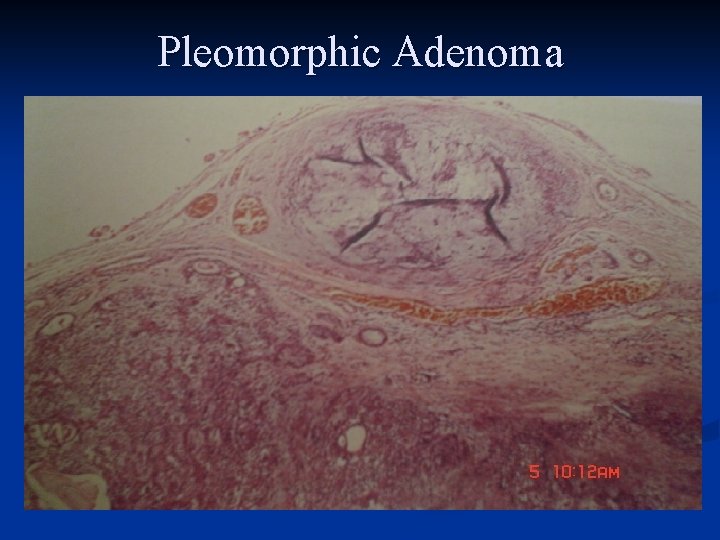
n n n Derived from mixture of epithelial and myoepithelial cells They reveal epithelial elements dispersed throughout a matrix along with a varying degree of myxoid, hyaline, cartilaginous and even osseous tissue They produce mucoid material Morphology- they are well demarcated masses. Although encapsulated, in some locations the capsule is not fully developed. The cut surface is grey white with myxoid and blue translucent areas of chondroid
Pleomorphic Adenoma
n Clinical features: Painless slow growing mass n Usually unilateral n Smooth, firm, lobulated, mobile swelling n Present as a swelling in front, below and behind ear n Raises the ear lobule n Curtain sign +ve n Obliteration of the retromandibular groove n
• • • Sometimes when deep lobe is involved, presents as a swelling in lateral wall of pharynx, soft palate and posterior pillar of the fauces. There may not be any visible swelling in the preauricular region, called as dumb bell tumor. Long standing pleomorphic adenoma may turn into carcinoma (ca. in ex. Pleomorphic adenoma) Recurrent pleomorphic adenoma- seen following incomplete tumor removal or spillage of the tumor during surgery.
Pleomorphic Adenoma
n Investigations: FNAC n CT scan n MRI n Technetium scan- cold spot (incision biopsy of parotid tumor is contraindicated as chances of seedling, injury to facial nerve and recurrence are high) n
n Treatment: Surgery- if only superficial lobe involved; superficial parotidectomy n If both lobes involved- total conservative parotidectomy preserving facial nerve n n Treatment of malignant pleomorphic adenoma: Radical parotidectomy, if facial nerve involved n Advanced tumors with fixed nodes may require post op radiotherapy n
Warthin’s tumor Also known as adenolymphoma or papillary cystadenoma lymphomatosum n Most common monomorphic adenoma n 2 nd most common tumor-10% of parotid tumors n Develops only in the parotid gland n Peak incidence- 60 -70 years n Predominantly in men n
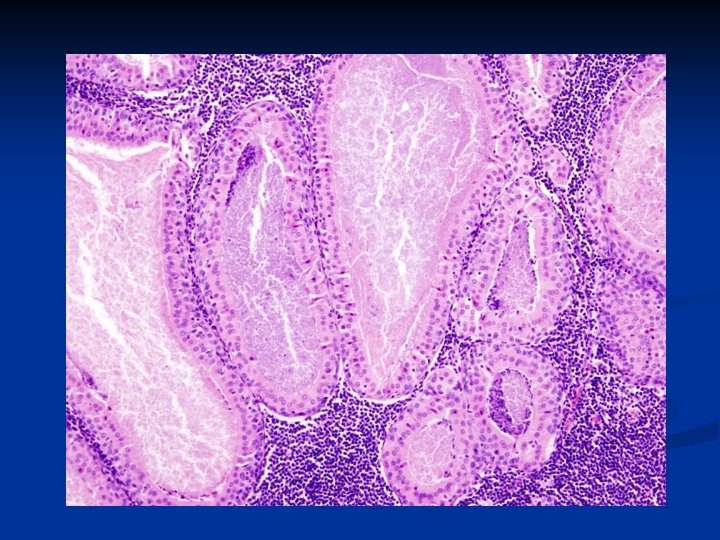
n Histology: n n Consists of a characteristic eosinophilic, glandular epithelial component and a stroma of lymphocytes which may form follicles or cysts Morphology: n n Most are round to oval, encapsulated masses, mostly arising in the superficial parotid gland Transection reveals a pale grey surface punctated by narrow cystic or cleft like spaces filled with a mucinous or serous secretion these spaces are lined by double layer of neoplastic epithelial cells resting on dense lymphoid stroma Double layer of lining cells is distinctive having an abundant, finely granular, eosinophilic cytoplasm, imparting an oncocytic appearance
n Clinical features: Slow growing, smooth, round border with soft, cystic consistency situated in the lower pole n Multifocal and bilateral n Smokers have higher risk n n Investigations: FNAC n Technetium scan-hot spot n n Treatment: n Enucleation to be done, since it is got a well defined capsule
Oncocytoma n n n Rare tumors , also known as Oxyphilic adenoma Predominantly in women in the 7 th or 8 th decade Parotid gland- most frequent site Benign tumor containing oncocytes (eosinophilic cells) with granular cytoplasm 6 Slow growing, smooth rubbery mass and rarely bilateral Treatment- excision is curative
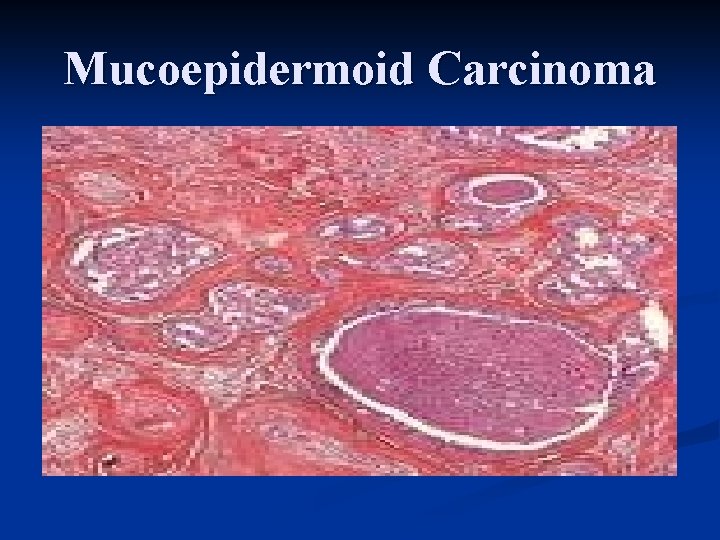
Mucoepidermoid carcinoma Commonest malignant salivary gland tumor n Contains two major elements-mucin producing cells and epithelial cells of epidermoid variety n MEC consists approximately 35% salivary gland malignancy n
Mucoepidermoid Carcinoma
Mucoepidermoid Carcinoma LOW GRADE / HIGH GRADE
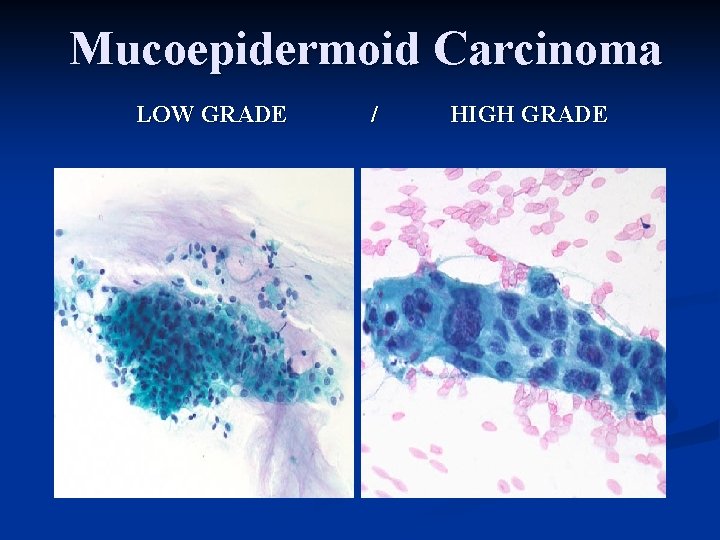
n Types: n n n Low grade- well differentiated, predominance of mucus secreting cells and well differentiated epidermoid cells Intermediate grade- moderately differentiated High grade- poorly differentiated, shows few or no mucus producing cells and poorly differentiated epidermoid cells The grading system of MEC also correlates with the prognosis Patients with high grade tend to present with more advanced stage disease and high incidence of nodal involvement, recurrence, metastasis and worse survival rate
n Morphology: Apparently circumscribed, lack well defined capsules and often infiltrative at margins n Pale and grey white on transection reveal small mucin containing cysts n Histologic pattern is that of cords, sheets or cystic configuration of squamous, mucus or intermediate cells n
n Clinical features n Swelling in parotid or submandibular region n Slowly progressive, eventually attaining a large size n Hard, nodular often with involvement of skin and lymph nodes n Facial nerve involvement is late n Treatment: Low grade- complete excision of tumor n High grade-needs post op radiation n In neck metastasis- neck dissection n
Adenoidcystic carcinoma Most common malignant tumor in submandibular gland n Peak incidence in 5 th and 6 th decade of life n Slightly more common among females n Very aggressive tumor n Described in 3 histological sub types: n Cribriform n Tubular n Solid (worst prognosis) n
Peculiar tendency to spread along nerves n Perineural infiltrates for a long distance in the perineural tissue of adjacent nerves and may invade medullary bone inducing significant bone resorption n Morphology: n Grossly- small, poorly encapsulated, infiltrative grey pink lesions n Histologically composed of small cells having dark compact nuclei and scant cytoplasm n
n Clinical features: Very hard and fixed mass n Pain, anesthesia and paralysis of the muscle due to involvement of corresponding nerves n Mandibular and maxillary branches of trigeminal nerve commonly involved n n Treatment: Radical parotidectomy n Radical radiotherapy n
Acinic cell carcinoma It’s a low grade malignancy n Peak incidence- 5 th decade n More in women n Rare, slow growing tumor n 4 histological sub typesn Solid n Microcystic n Papillarycystic n follicular n
TNM Classification n Primary tumor (T) TX: tumor cannot be assessed n T 0: no evidence of primary tumor n T 1: tumor 2 cm or less in greatest dimension without extraparenchymal extension n T 2: tumor 2 -4 cm in greatest dimension without extraparenchymal extension n T 3: tumor >4 cm with extraparenchymal extension n T 4 a: tumor involves skin, mandible, ear canal and/or facial nerve n T 4 b: tumor invades skull base and/or pterygoid plates and/or encases carotid artery n
n Regional lymph nodes(N) NX: regional lymph nodes not assessed n N 0: no regional lymph node metastasis n N 1: metastasis in a single ipsilateral lymph node 3 cm or less in size n N 2 a: metastasis in a single ipsilateral lymph node of 3 -6 cm in size n N 2 b: metastasis in a multiple ipsilateral lymph nodes, none>6 cm in size n N 2 c: metastasis in contralateral lymph node, none>6 cm in size n N 3: metastasis in lymph node of >6 cm in size n
n Distant metastasis(M) MX: distant metastasis not assessed n M 0: no distant metastasis n M 1: distant metastasis n
Investigation FNAC n CT Scan n Orthopantomogram n FNAC of lymph node n Radionuclide scan n Chest X ray n MRI n USG n
Treatment 1. Surgery Superficial parotidectomy- removal of superficial lobe (superficial to facial nerve) done in case of benign diseases of superficial lobe n Total conservative parotidectomy- here both lobes are removed with preservation of facial nerve. Done in benign diseases of parotid involving either only deep lobe or both n Radical parotidectomy- both lobes of parotid removed along with facial nerve, fat, fascia, muscles (masseter, pterygoids and buccinator), lymph nodes n
If lymph nodes are involved, radical neck dissection is done n Complications of surgery: n Flap necrosis n Hemorrhage n Infection n Salivary fistula n Facial nerve palsy n Frey’s syndrome n
2. Radiotherapy: n 3. Post operatively used to reduce the chance of relapse Chemotherapy
THANK YOU