
OHCP Maturity Assessment July 2020 1 8 Our





- Slides: 16
OHCP Maturity Assessment July 2020 1
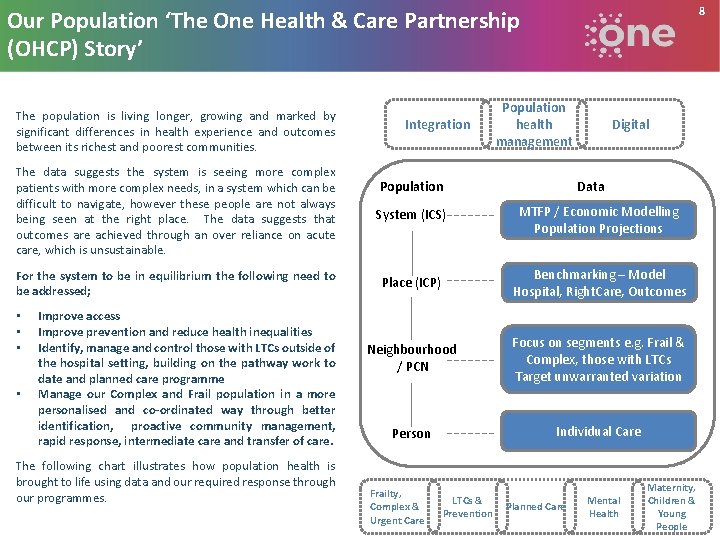
8 Our Population ‘The One Health & Care Partnership (OHCP) Story’ The population is living longer, growing and marked by significant differences in health experience and outcomes between its richest and poorest communities. Integration Population health management Digital The data suggests the system is seeing more complex patients with more complex needs, in a system which can be difficult to navigate, however these people are not always being seen at the right place. The data suggests that outcomes are achieved through an over reliance on acute care, which is unsustainable. System (ICS) MTFP / Economic Modelling Population Projections For the system to be in equilibrium the following need to be addressed; Place (ICP) Benchmarking – Model Hospital, Right. Care, Outcomes Neighbourhood / PCN Focus on segments e. g. Frail & Complex, those with LTCs Target unwarranted variation Person Individual Care • • Improve access Improve prevention and reduce health inequalities Identify, manage and control those with LTCs outside of the hospital setting, building on the pathway work to date and planned care programme Manage our Complex and Frail population in a more personalised and co-ordinated way through better identification, proactive community management, rapid response, intermediate care and transfer of care. The following chart illustrates how population health is brought to life using data and our required response through our programmes. Population Frailty, Complex & Urgent Care LTCs & Prevention Data Planned Care Mental Health Maternity, Children & Young People
West Essex Integrated Care Partnership Our Partnership The One Health and Care Partnership (our local ICP) will require considerable change in the way our organisations work, with calls for greater collaboration and new ways of doing things. The Core Partners (Tier 1 and Tier 2) within the One Health and Care Partnership are: § West Essex CCG § Princess Alexandra Hospital § Essex Partnership University Trust § Essex County Council. Working as the One Health and Care Partnership, we are combining expertise and resources to protect and improve services for our local population. The aim is to give people greater control over their own health and care, basing services on the health needs of the local population. There is a united objective to integrate services at the point of need ensuring that patients always receive high quality care in a location that best meets their needs and they see no distinction in the services they are offered. Wider engagement (Tier 3 and Tier 4) includes: § Primary Care Networks § GP Federations § Urgent Care Provider § 3 District Councils § Voluntary Sector 3
Overview q The development of the One Health and Care Partnership (OHCP) from April 2020 is a planned key transition point towards the development of an Integrated Care Trust for the West Essex Population. q Our ICP is built on the principles of the ICS through collaborative work carried out by system partners to further reshape the way we deliver care to our population via our PCN footprint. q The OHCP brings together NHS organisations, local hospitals, GPs, social care and the charity and voluntary sector in West Essex and we put local people, and the quality of health and care services, at the centre of all we do. The development of our partnership is our opportunity to stretch our ambition for real integration for our population. q This is part of a wider strategy being implemented by the Hertfordshire & West Essex Sustainability and Transformation Partnership (STP), of which many of the partners are members.
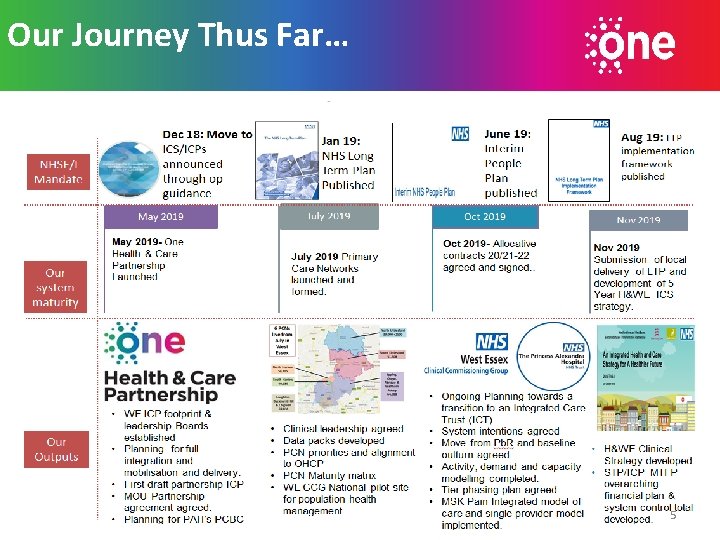
Our Journey Thus Far… 5
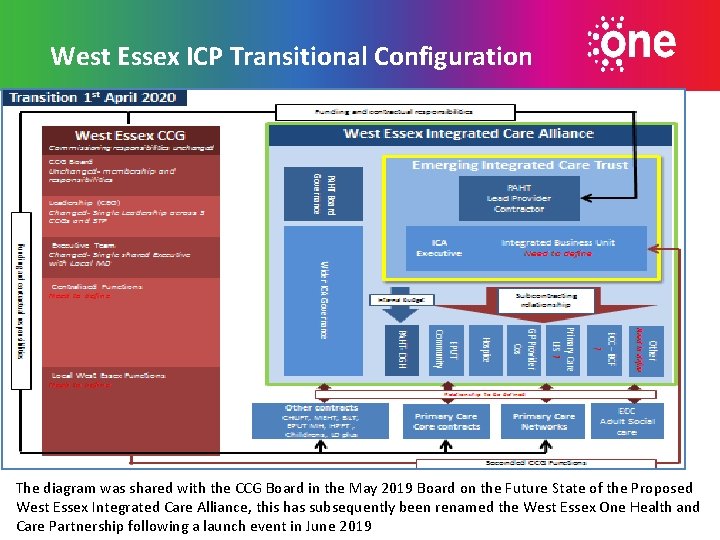
West Essex ICP Transitional Configuration The diagram was shared with the CCG Board in the May 2019 Board on the Future State of the Proposed West Essex Integrated Care Alliance, this has subsequently been renamed the West Essex One Health and Care Partnership following a launch event in June 2019
Maturity Matrix Assessment This matrix assessment has been adapted from the existing Integrated Care System (ICS) maturity matrix online tool published by NHS England/Improvement to enable systems undertake their local self-assessments. The assessment contains six domains. Four domains have been applied with exception to PCN development and Joint System Functions 7
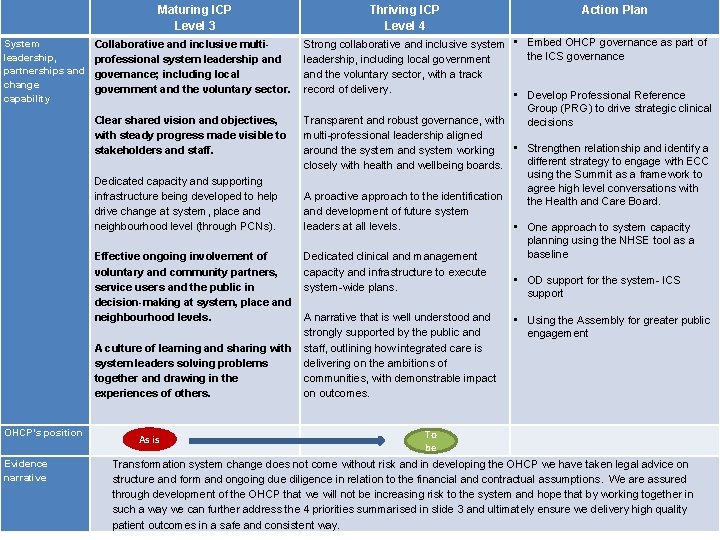
Maturing ICP Level 3 System leadership, partnerships and change capability OHCP’s position Evidence narrative Thriving ICP Level 4 Collaborative and inclusive multiprofessional system leadership and governance; including local government and the voluntary sector. Strong collaborative and inclusive system leadership, including local government and the voluntary sector, with a track record of delivery. Clear shared vision and objectives, Transparent and robust governance, with steady progress made visible to multi-professional leadership aligned stakeholders and staff. around the system and system working closely with health and wellbeing boards. Dedicated capacity and supporting infrastructure being developed to help A proactive approach to the identification drive change at system, place and development of future system neighbourhood level (through PCNs). leaders at all levels. Effective ongoing involvement of Dedicated clinical and management voluntary and community partners, capacity and infrastructure to execute service users and the public in system-wide plans. decision-making at system, place and neighbourhood levels. A narrative that is well understood and strongly supported by the public and A culture of learning and sharing with staff, outlining how integrated care is system leaders solving problems delivering on the ambitions of together and drawing in the communities, with demonstrable impact experiences of others. on outcomes. As is Action Plan • Embed OHCP governance as part of the ICS governance • Develop Professional Reference Group (PRG) to drive strategic clinical decisions • Strengthen relationship and identify a different strategy to engage with ECC using the Summit as a framework to agree high level conversations with the Health and Care Board. • One approach to system capacity planning using the NHSE tool as a baseline • OD support for the system- ICS support • Using the Assembly for greater public engagement To be Transformation system change does not come without risk and in developing the OHCP we have taken legal advice on structure and form and ongoing due diligence in relation to the financial and contractual assumptions. We are assured through development of the OHCP that we will not be increasing risk to the system and hope that by working together in such a way we can further address the 4 priorities summarised in slide 3 and ultimately ensure we delivery high quality 8 patient outcomes in a safe and consistent way.
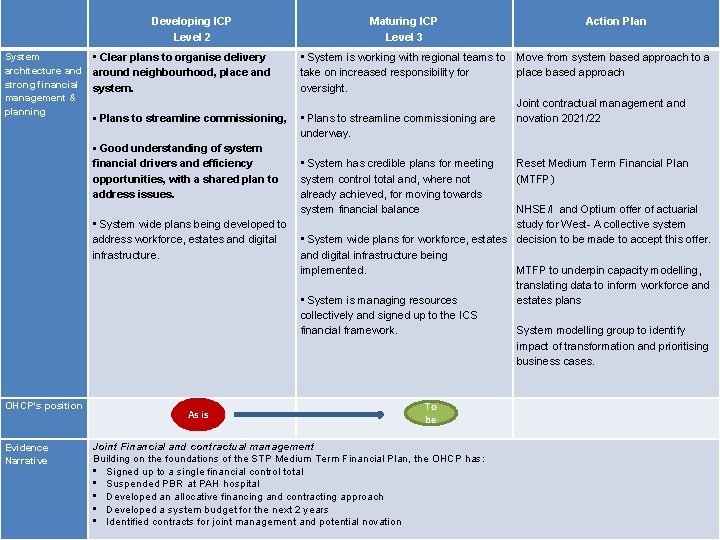
Developing ICP Level 2 System architecture and strong financial management & planning • Clear plans to organise delivery around neighbourhood, place and system. • Plans to streamline commissioning, • Good understanding of system financial drivers and efficiency opportunities, with a shared plan to address issues. • System wide plans being developed to address workforce, estates and digital infrastructure. OHCP’s position Evidence Narrative As is Maturing ICP Level 3 Action Plan • System is working with regional teams to Move from system based approach to a take on increased responsibility for place based approach oversight. Joint contractual management and • Plans to streamline commissioning are novation 2021/22 underway. • System has credible plans for meeting Reset Medium Term Financial Plan system control total and, where not (MTFP) already achieved, for moving towards system financial balance NHSE/I and Optium offer of actuarial study for West- A collective system • System wide plans for workforce, estates decision to be made to accept this offer. and digital infrastructure being implemented. MTFP to underpin capacity modelling, translating data to inform workforce and • System is managing resources estates plans collectively and signed up to the ICS financial framework. System modelling group to identify impact of transformation and prioritising business cases. To be Joint Financial and contractual management Building on the foundations of the STP Medium Term Financial Plan, the OHCP has: • Signed up to a single financial control total • Suspended PBR at PAH hospital • Developed an allocative financing and contracting approach • Developed a system budget for the next 2 years • Identified contracts for joint management and potential novation 9
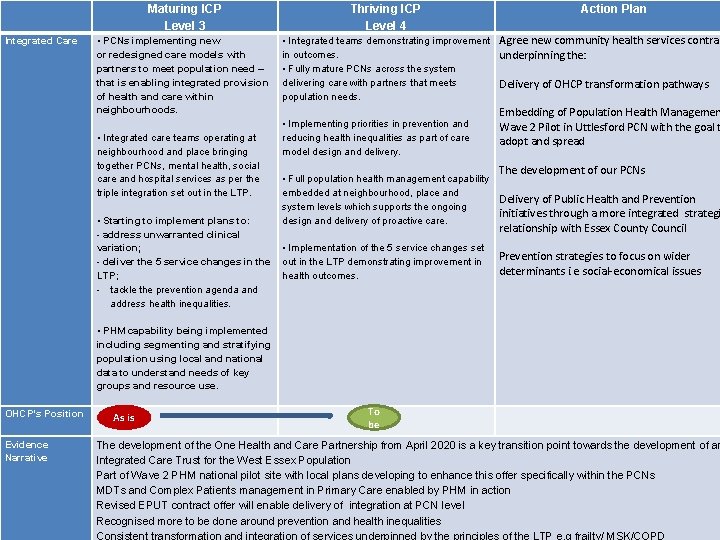
Integrated Care Maturing ICP Level 3 Thriving ICP Level 4 • PCNs implementing new or redesigned care models with partners to meet population need – that is enabling integrated provision of health and care within neighbourhoods. • Integrated care teams operating at neighbourhood and place bringing together PCNs, mental health, social care and hospital services as per the triple integration set out in the LTP. • Starting to implement plans to: - address unwarranted clinical variation; - deliver the 5 service changes in the LTP; - tackle the prevention agenda and address health inequalities. • Integrated teams demonstrating improvement in outcomes. • Fully mature PCNs across the system delivering care with partners that meets population needs. • Implementing priorities in prevention and reducing health inequalities as part of care model design and delivery. • Full population health management capability embedded at neighbourhood, place and system levels which supports the ongoing design and delivery of proactive care. • Implementation of the 5 service changes set out in the LTP demonstrating improvement in health outcomes. Action Plan Agree new community health services contrac underpinning the: Delivery of OHCP transformation pathways Embedding of Population Health Managemen Wave 2 Pilot in Uttlesford PCN with the goal t adopt and spread The development of our PCNs Delivery of Public Health and Prevention initiatives through a more integrated strategi relationship with Essex County Council Prevention strategies to focus on wider determinants i. e social-economical issues • PHM capability being implemented including segmenting and stratifying population using local and national data to understand needs of key groups and resource use. To be OHCP’s Position Evidence Narrative The development of the One Health and Care Partnership from April 2020 is a key transition point towards the development of an Integrated Care Trust for the West Essex Population Part of Wave 2 PHM national pilot site with local plans developing to enhance this offer specifically within the PCNs MDTs and Complex Patients management in Primary Care enabled by PHM in action Revised EPUT contract offer will enable delivery of integration at PCN level 10 Recognised more to be done around prevention and health inequalities Consistent transformation and integration of services underpinned by the principles of the LTP e. g frailty/ MSK/COPD As is
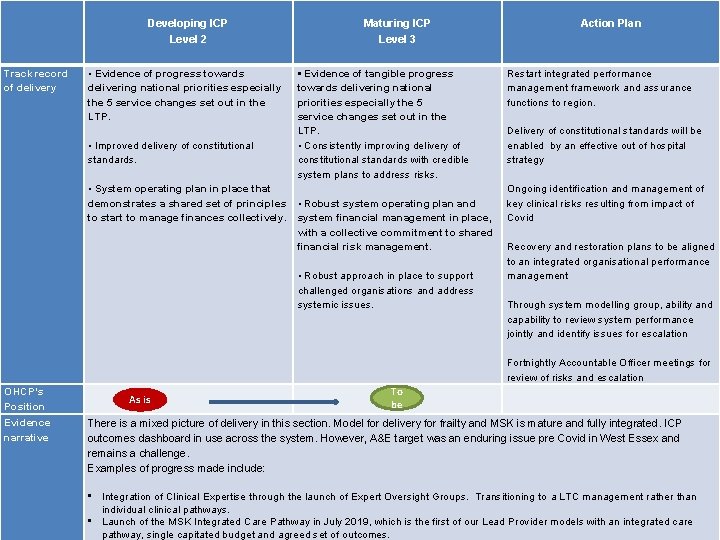
Developing ICP Level 2 Track record of delivery Maturing ICP Level 3 • Evidence of progress towards delivering national priorities especially the 5 service changes set out in the LTP. • Evidence of tangible progress towards delivering national priorities especially the 5 service changes set out in the LTP. • Improved delivery of constitutional • Consistently improving delivery of standards. constitutional standards with credible system plans to address risks. • System operating plan in place that demonstrates a shared set of principles • Robust system operating plan and to start to manage finances collectively. system financial management in place, with a collective commitment to shared financial risk management. • Robust approach in place to support challenged organisations and address systemic issues. OHCP’s Position Evidence narrative As is To be Action Plan Restart integrated performance management framework and assurance functions to region. Delivery of constitutional standards will be enabled by an effective out of hospital strategy Ongoing identification and management of key clinical risks resulting from impact of Covid Recovery and restoration plans to be aligned to an integrated organisational performance management Through system modelling group, ability and capability to review system performance jointly and identify issues for escalation Fortnightly Accountable Officer meetings for review of risks and escalation There is a mixed picture of delivery in this section. Model for delivery for frailty and MSK is mature and fully integrated. ICP outcomes dashboard in use across the system. However, A&E target was an enduring issue pre Covid in West Essex and remains a challenge. Examples of progress made include: • Integration of Clinical Expertise through the launch of Expert Oversight Groups. Transitioning to a LTC management rather than individual clinical pathways. 11 • Launch of the MSK Integrated Care Pathway in July 2019, which is the first of our Lead Provider models with an integrated care pathway, single capitated budget and agreed set of outcomes.
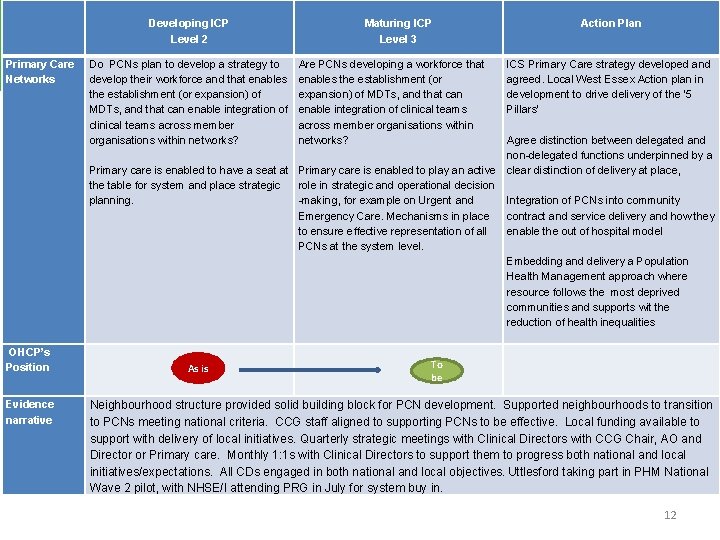
Developing ICP Level 2 Primary Care Networks Maturing ICP Level 3 Action Plan Do PCNs plan to develop a strategy to develop their workforce and that enables the establishment (or expansion) of MDTs, and that can enable integration of clinical teams across member organisations within networks? Are PCNs developing a workforce that enables the establishment (or expansion) of MDTs, and that can enable integration of clinical teams across member organisations within networks? ICS Primary Care strategy developed and agreed. Local West Essex Action plan in development to drive delivery of the ‘ 5 Pillars’ OHCP’s Position Evidence narrative Neighbourhood structure provided solid building block for PCN development. Supported neighbourhoods to transition to PCNs meeting national criteria. CCG staff aligned to supporting PCNs to be effective. Local funding available to support with delivery of local initiatives. Quarterly strategic meetings with Clinical Directors with CCG Chair, AO and Director or Primary care. Monthly 1: 1 s with Clinical Directors to support them to progress both national and local initiatives/expectations. All CDs engaged in both national and local objectives. Uttlesford taking part in PHM National Wave 2 pilot, with NHSE/I attending PRG in July for system buy in. Agree distinction between delegated and non-delegated functions underpinned by a Primary care is enabled to have a seat at Primary care is enabled to play an active clear distinction of delivery at place, the table for system and place strategic role in strategic and operational decision planning. -making, for example on Urgent and Integration of PCNs into community Emergency Care. Mechanisms in place contract and service delivery and how they to ensure effective representation of all enable the out of hospital model PCNs at the system level. Embedding and delivery a Population Health Management approach where resource follows the most deprived communities and supports wit the reduction of health inequalities As is To be 12
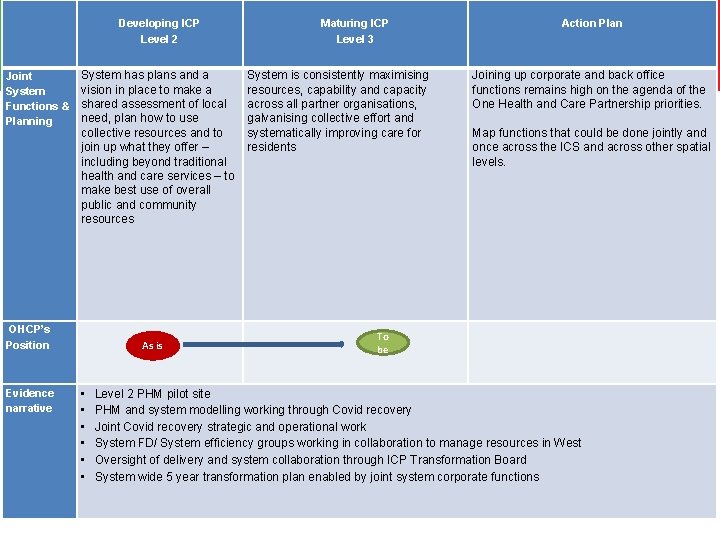
Developing ICP Level 2 Maturing ICP Level 3 Action Plan Joint System Functions & Planning System has plans and a vision in place to make a shared assessment of local need, plan how to use collective resources and to join up what they offer – including beyond traditional health and care services – to make best use of overall public and community resources System is consistently maximising resources, capability and capacity across all partner organisations, galvanising collective effort and systematically improving care for residents Joining up corporate and back office functions remains high on the agenda of the One Health and Care Partnership priorities. OHCP’s Position Evidence narrative • • • As is To be Map functions that could be done jointly and once across the ICS and across other spatial levels. Level 2 PHM pilot site PHM and system modelling working through Covid recovery Joint Covid recovery strategic and operational work System FD/ System efficiency groups working in collaboration to manage resources in West Oversight of delivery and system collaboration through ICP Transformation Board System wide 5 year transformation plan enabled by joint system corporate functions 13
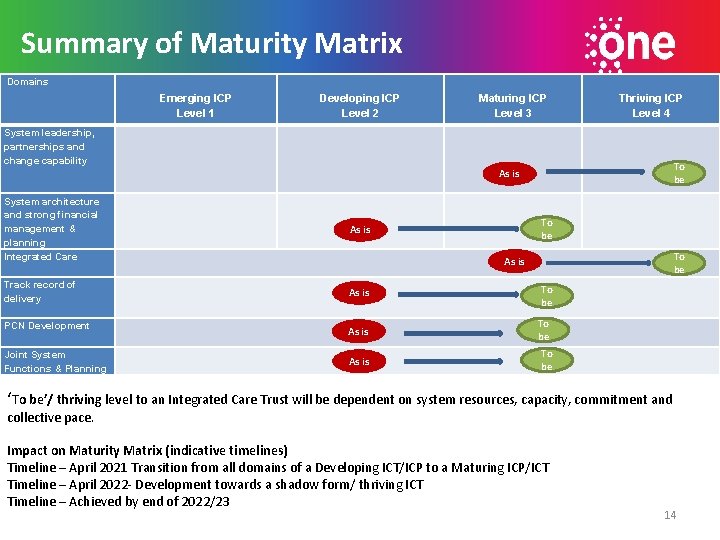
Summary of Maturity Matrix Domains Emerging ICP Level 1 Developing ICP Level 2 Maturing ICP Level 3 Thriving ICP Level 4 System leadership, partnerships and change capability To be As is System architecture and strong financial management & planning Integrated Care Track record of delivery PCN Development Joint System Functions & Planning To be As is As is To be ‘To be’/ thriving level to an Integrated Care Trust will be dependent on system resources, capacity, commitment and collective pace. Impact on Maturity Matrix (indicative timelines) Timeline – April 2021 Transition from all domains of a Developing ICT/ICP to a Maturing ICP/ICT Timeline – April 2022 - Development towards a shadow form/ thriving ICT Timeline – Achieved by end of 2022/23 14
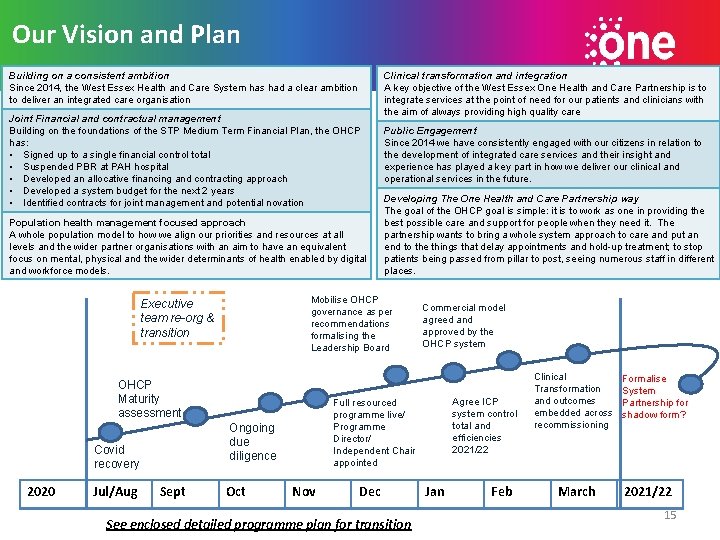
Our Vision and Plan Building on a consistent ambition Since 2014, the West Essex Health and Care System has had a clear ambition to deliver an integrated care organisation Joint Financial and contractual management Building on the foundations of the STP Medium Term Financial Plan, the OHCP has: • Signed up to a single financial control total • Suspended PBR at PAH hospital • Developed an allocative financing and contracting approach • Developed a system budget for the next 2 years • Identified contracts for joint management and potential novation Population health management focused approach A whole population model to how we align our priorities and resources at all levels and the wider partner organisations with an aim to have an equivalent focus on mental, physical and the wider determinants of health enabled by digital and workforce models. OHCP Maturity assessment 2020 Jul/Aug Developing The One Health and Care Partnership way The goal of the OHCP goal is simple: it is to work as one in providing the best possible care and support for people when they need it. The partnership wants to bring a whole system approach to care and put an end to the things that delay appointments and hold-up treatment; to stop patients being passed from pillar to post, seeing numerous staff in different places. Oct Commercial model agreed and approved by the OHCP system Agree ICP system control total and efficiencies 2021/22 Full resourced programme live/ Programme Director/ Independent Chair appointed Ongoing due diligence Sept Public Engagement Since 2014 we have consistently engaged with our citizens in relation to the development of integrated care services and their insight and experience has played a key part in how we deliver our clinical and operational services in the future. Mobilise OHCP governance as per recommendations formalising the Leadership Board Executive team re-org & transition Covid recovery Clinical transformation and integration A key objective of the West Essex One Health and Care Partnership is to integrate services at the point of need for our patients and clinicians with the aim of always providing high quality care Nov Dec See enclosed detailed programme plan for transition Jan Feb Clinical Transformation and outcomes embedded across recommissioning March Formalise System Partnership for shadow form? 2021/22 15
Areas identified for accelerated support Organisational and leadership development q PAH- with transition to an Integrated Care Trust, the organisation will require significant organisational development support and a consideration of future business models q PCNs- - A key element of this programme will be focused on working with the leadership and practices to enable them to develop their capability to work together as part of such an alliance. q Bring practices together in clusters and localities/ federations to develop a shared vision and common purpose, and in turn to enable localities to work with maturity as part of a provider alliance q Increased appetite for ambitious change and the risk appetite that comes with this. Defined models of care with integrated teams q OD support - Shifting the way EPUT work with PAH and the PCNs, changing behaviours, enabling commitment and capability to a holistic MDT approach that drives true integrated care or patients. Transition: Support for the system to define and publish framework for what functions might be undertaken at each system level: ICS, ICP, Borough and PCN level. Regional and National Support q NHS England support developing business models q Shift to a single system assurance process for the ICP q Support with new payment mechanisms, risk share agreements and a transition to Capitated Budgets Development of Population Health Management in Primary Care Networks q Embedding wave 2 principles into delivery/ starting in Uttlesford and rolling out Demonstrating Transformational Outcomes q Programmes are designed to focus on delivery built around patient defined outcomes and not process driven 16 measures.