
Obstetrisk anestesi ALNSF Fagkongress 2009 Guro Grindheim Lege

Obstetrisk anestesi ALNSF Fagkongress 2009 Guro Grindheim Lege Anestesi og Intensivklinikken OUS Rikshospitalet GG ALNSF Høstkonress 2009

Obstetrisk anestesi Gravid fysiologi Anestesi ved sectio Anestesi til gravide med kronisk sykdom eller svangerskapskomplikasjoner GG ALNSF Høstkonress 2009

Obstetrisk anestesi Fysiologiske endringer i graviditet Hensyn til den gravide og foster GG ALNSF Høstkonress 2009

Gravid fysiologi Lunge; MV , FRC Kardiovaskulært; CO (+50%), regionalraskere flow gjennom Et stort hjerte pumper et stort, tyntflytende blodvolum Motstand karseng en forstørret og utvidet Hemodynamikk/hematologi BV (Plasmavolum) koagulasjonsfaktorer GG ALNSF Høstkonress 2009
Gravid fysiologi GG ALNSF Høstkonress 2009

Anestesi ved sectio Valg av anestesiform – Regional anestesi Aktivert EDK (epidural kateter) Spinal – GA (generell anestesi) GG ALNSF Høstkonress 2009
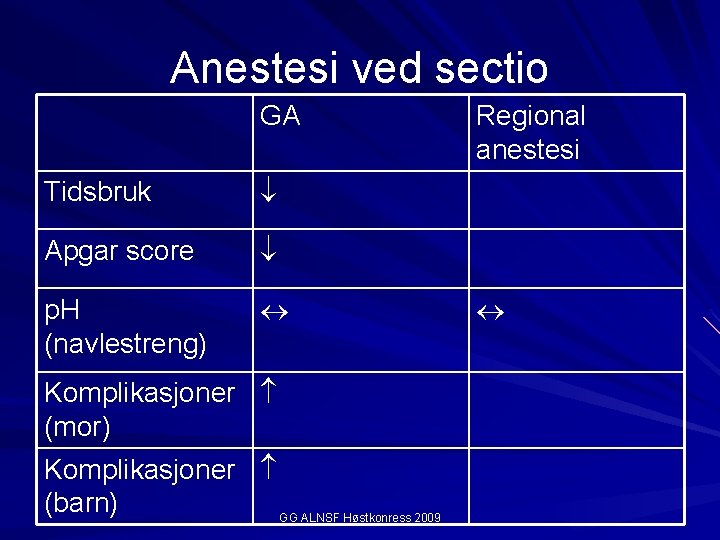
Anestesi ved sectio GA Tidsbruk Apgar score p. H (navlestreng) Komplikasjoner (mor) Komplikasjoner (barn) GG ALNSF Høstkonress 2009 Regional anestesi
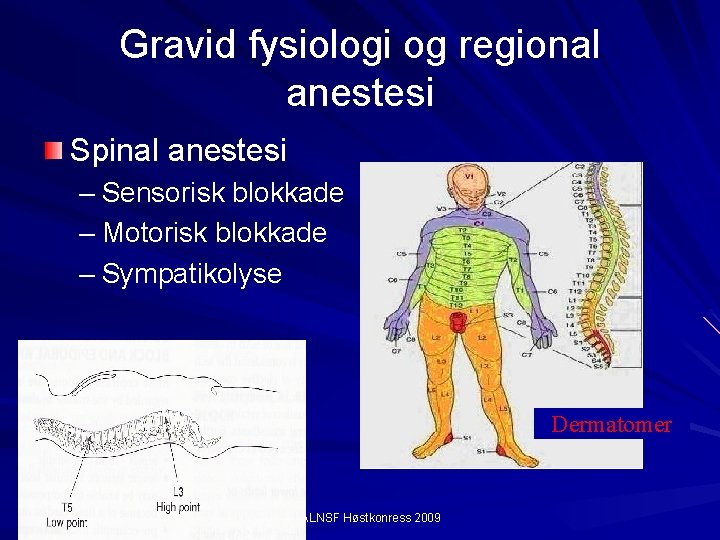
Gravid fysiologi og regional anestesi Spinal anestesi – Sensorisk blokkade – Motorisk blokkade – Sympatikolyse Dermatomer GG ALNSF Høstkonress 2009

Gravid fysiologi og regional anestesi Spinal anestesi – Sensorisk blokkade – Motorisk blokkade – Sympatikolyse 2 nivåer kranialt for øvre sensoriske nivå GG ALNSF Høstkonress 2009
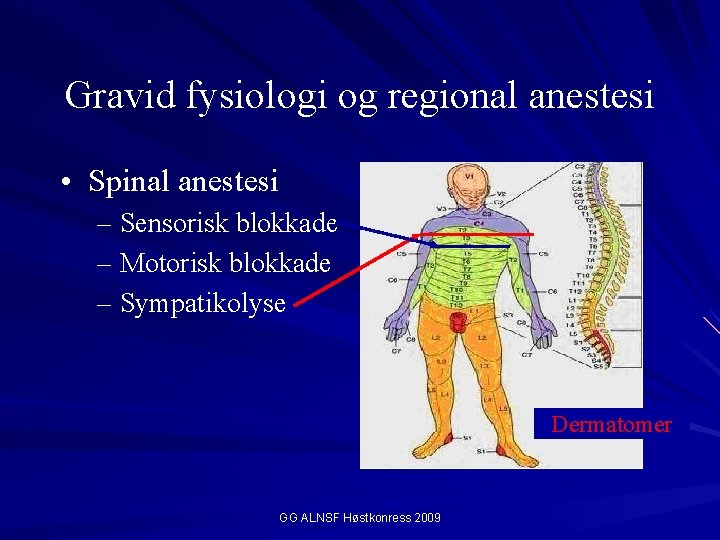
Gravid fysiologi og regional anestesi • Spinal anestesi – Sensorisk blokkade – Motorisk blokkade – Sympatikolyse Dermatomer GG ALNSF Høstkonress 2009
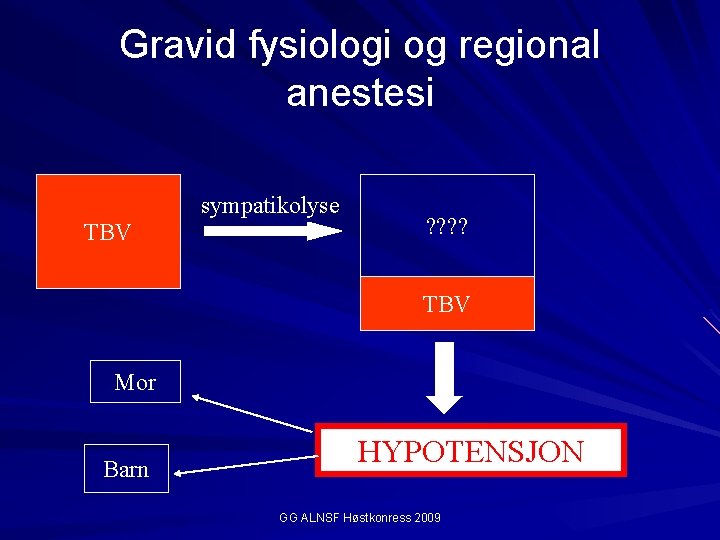
Gravid fysiologi og regional anestesi sympatikolyse TBV ? ? TBV Mor Barn HYPOTENSJON GG ALNSF Høstkonress 2009
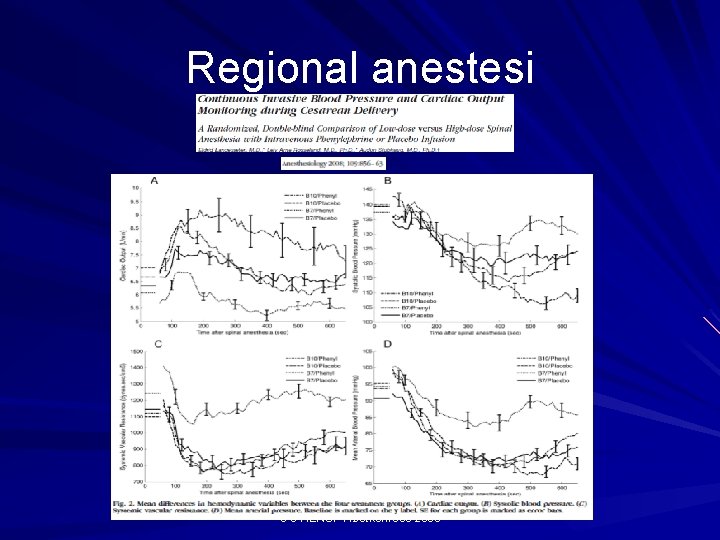
Regional anestesi GG ALNSF Høstkonress 2009
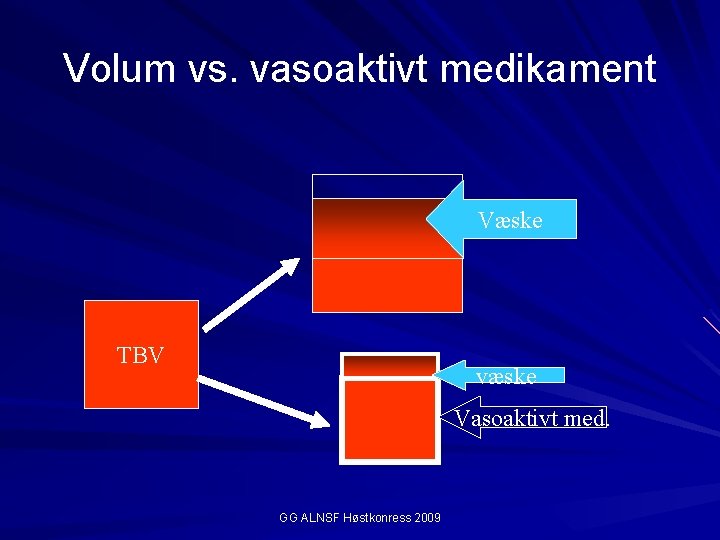
Volum vs. vasoaktivt medikament Væske TBV væske Vasoaktivt med. GG ALNSF Høstkonress 2009

Regional anestesi Hypotensjon forekommer hos 55 - 90% Ingen metoder er alene vist å eliminere hypotensjon Væskestøt; – – – Kolloider krystalloider ingenting Ingen forskjell mellom ulike administrasjonsrutiner Prehydrering vs cohydrering – Skille friske, elektive pasienter fra Ø-hjelp-pasienter Kompresjon av ben Fenylefrin vs efedrin – Efedrin krysser i større grad placenta enn hva tilfellet er for fenylefrin og gir bla økt føtalt laktat og katekolamin-nivå samt redusert p. H i navlestrengsblod. – Med mindre mor er bradycard anbefales fenylefrin-infusjon. GG ALNSF Høstkonress 2009

Væske – fenylefrin - efedrin Cochrane review juni 2006 ”Techniques for preventing hypotension during spinal anaesthesia for caesarian section” While interventions such as colloids, ephedrine, phenylephrine or lower leg compression can reduce the incidence of hypotension, none have been shown to eliminate the need to treat maternal hypotension during spinal anaesthesia for caesarian section…… No conclusion can be drawn with the optimum volume of intravenous fluid, route or timing of administration of ephedrine… GG ALNSF Høstkonress 2009

Volum vs. vasoaktivt medikament Væske Vasoaktivt medikament – Klarer ikke fullt ut kompensere – 2. - 3. Postop. døgn? ? – Kompenserer – Unngå væskeoverskudd – Styrbar • 1000 - 2000 ml krystalloid • Kolloid kun på indikasjon • Vasoaktivt medikament for å kompensere påført sympatikolyse GG ALNSF Høstkonress 2009

Fenylefrin vs. efedrin Fenylefrin 1 - reseptor agonist – Vasokonstriksjon – Bradycardi Infusjon (bolus) Efedrin 1, 1 og 2 agonist – – – HR Kontraktilitet CO Bolus GG ALNSF Høstkonress 2009

Regional anestesi -oppsummering Tilpasset dose spinalanestesi Coloading med krystalloider Fenylefrin-infusjon evt bolus GG ALNSF Høstkonress 2009

Generell anestesi GG ALNSF Høstkonress 2009

Sectio i generell anestesi Monitorering Na- citrat Preoxygenering Innledning; – RSI Thiopenthal Suxamethonium Cricoid trykk – Tube på plass…. . VÆR SÅ GOD! VEDLIKEHOLD ANESTESI? ? GG ALNSF Høstkonress 2009

Fysiologiske endringer under graviditet Redusert behov for anestesi GG ALNSF Høstkonress 2009

Anestesi gasser og uteruskontraksjon Sevoflurane, Isofluran og Desfluran Uteruskontraksjon + BLØDNING OG ATONI GG ALNSF Høstkonress 2009

Anestesi gasser og uteruskontraksjon Anestesigasser hemmer kontraktilitet i myometriet – Redusert frekvens og amplitude Økende MAC gir økende reduksjon Redusert effekt av administrert oxytocin GG ALNSF Høstkonress 2009

Anestesi gasser og uteruskontraksjon Teori og praksis Fordeler og ulemper Konklusjon: • Anestesigasser har negativ påvirkning på uteruskontraksjon • Vurder overgang til TIVA (Remifentanil/Propofol) ved vanskelig hemostase el atoni. GG ALNSF Høstkonress 2009

TIVA ved sectio Innledning – Tid – Liten klinisk erfaring/ annet enn case-reports hos syke gravide – Forskning Vedlikehold – Godt alternativ, kanskje bedre? GG ALNSF Høstkonress 2009

Remifentanil ved sectio Ønsker: – Unngå stress/BT- stigning hos mor knyttet til intubasjon/kirurgi – Unngå påvirkning av den nyfødte Ulike strategier; – Vente med remifentanil til barnet er forløst – Bolus 1 g/kg (lavere BT-stigning ved intubasjon sammenliknet med saltvannsinjeksjon) – Kontinuerlig infusjon 0, 1 g/kg/min (doser på 0, 2 kg/min ga behov for assistert ventilasjon/naloxon hos 50% av de nyfødte) Remifentanil brukt under fødsel, bolus 0, 2 g/kg (ex: 80 kg gis det 16 g) gir ikke redusert økt behov for neonatal resc. GG ALNSF Høstkonress 2009

Anestesi gasser og uteruskontraksjon Teori og praksis Fordeler og ulemper Konklusjon: • Anestesigasser har negativ påvirkning på uteruskontraksjon • Vurder overgang til TIVA (Remifentanil/Propofol) ved vanskelig hemostase el atoni. GG ALNSF Høstkonress 2009

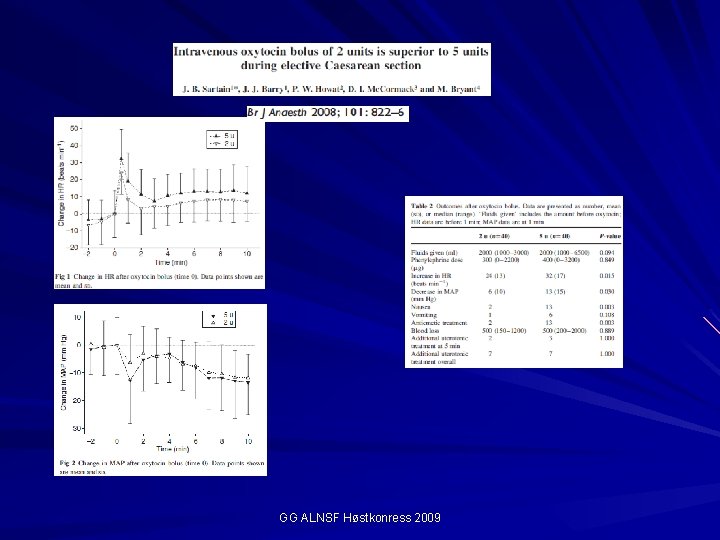
Oxytocin- bolus Hormon som produseres i hypofysens bakhorn Gir uteruskontraksjon og lukning av uterine kar Hvilken dose? – Virkning vs. Bivirkninger – Minste effektive dose GG ALNSF Høstkonress 2009
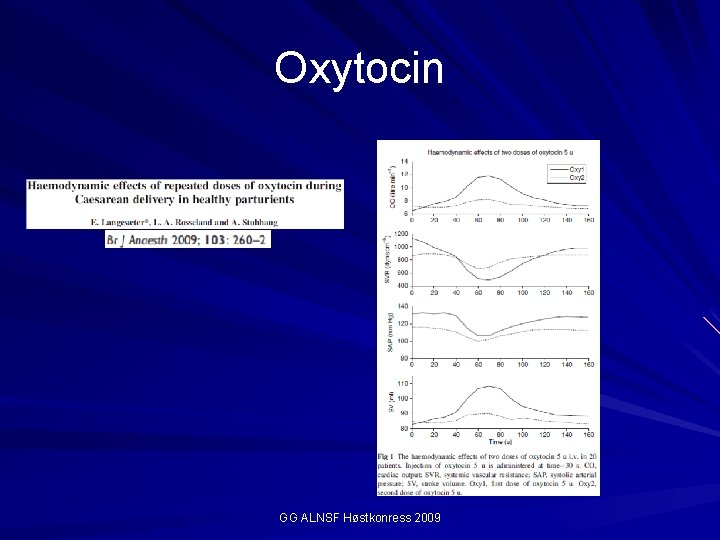
Oxytocin GG ALNSF Høstkonress 2009
GG ALNSF Høstkonress 2009

Preeklampsi Symptomer – Hypertensjon (BT > 140/90) – Proteinuri – Andre symptomer (cerebrale, +++) – HELLP (Hemolyse, Elevated Liver enzymes, Low Platelets) Rammer 6 - 8% av alle graviditeter. Betinget i samspillet mor placenta fetus GG ALNSF Høstkonress 2009

Preeklampsi Hva er farlig? ? ? – Mor Hypertensjon multiorgan affeksjon HELLP – Fetus Vekstretardasjon (IUGR) Død GG ALNSF Høstkonress 2009

Preeklampsi - sectio Monitorering Stabil hemodynamikk – Tåler regional anestesi godt Færre tilfeller av behandlingstrengende hypotensjon (syst BT<90 el reduksjon>30% av utgangsverdi) – Unngå stress (intubasjon/ extubasjon) Vurder opiat (remifentanil el alfentanil) ved GA. GG ALNSF Høstkonress 2009

Preeklampsi, -behandling Forløsning Blodtrykksreduksjon Mg. SO 4 ved alvorlig preeklampsi eller eklampsi – Magpie Trial 17, 5 mmol Mg. SO 4 over 10 min, deretter vedlikeholdsinfusjon over 24 t GG ALNSF Høstkonress 2009

Oppsummering Store hemodynamiske endringer hos gravide Regional anestesi Kohydrering Fenylefrin Dose oxytocin Overgang til TIVA ved sectio i generell anestesi? GG ALNSF Høstkonress 2009

Referanser anbefalt litteratur Techniques for preventing hypotension during spinal anaesthesia for caesarean section. Cochrane database Syst Rev 2006 Oct 18; (4) Dyer RA, Farina Z, Joubert IA et al: Crystalloid preload versus rapid crystalloid adminstration after induction of spinal anaesthesia (colaod) for elective caesarean section. Anaesth Intensive Care 2004; 32: 351 -7 Ngan Kee WD, Khaw KS, Tan PE, et al. Placental transfer and metabolic effects of phenylepinephrine and epinephrine during spinal anesthesia for cesarean delivery. Anesthesiology. 2009 Aug 10. Chan MT, Gin T. Postpartum changes in the minimum alveolar concentration of isoflurane. Anesthesiology 1995; 82: 1360– 3 Chan MT, Mainland P, Gin T. Minimum alveolar concentration of halothane and enflurane are decreased in early pregnancy. Anesthesiology 1996; 85: 782– 6 Gin T, Chan MT. Decreased minimum alveolar concentration of isoflurane in pregnant humans. Anesthesiology 1994; 81: 829– 32 Gin T, Mainland P, Chan MT, Short TG. Decreased thiopental requirements in early pregnancy. Anesthesiology 1997; 86: 73– 8 Zhou HH, Norman P, De. Lima LG, Mehta M, Bass D. The minimum alveolar concentration of isoflurane in patients undergoing bilateral tubal ligation in the postpartum period. Anesthesiology 1995; 82: 1364– 8 Yildiz K, Dogru K, Dalgic H et al. Inhibitory effects of desflurane and sevoflurane on oxytocin-induced contractions of isolated pregnant human myometrium. Acta Anaesthesiol Scand 2005; 49: 1355– 9. Yoo K Y, Lee J C, Yoon M H et al. The effects of volatile anesthetics on spontaneous contractility of isolated human pregnant uterine muscle: a comparison among sevoflurane, desflurane, isoflurane, and halothane. Anesth Analg 2006; 103: 443– 7. Gultekin et al. Comparing the relaxing effects of desflurane and sevoflurane on oxytocin- induced contractions of isolated myometrium in both pregnant and non- pregnant rats. Adv Ther 2006 Jan. Feb; 23(1): 39 -46 In vitro effects of propofol on gravid human myometrium. Thind AS, Turner RJ. Anaesth Intensive Care. 2008 Nov; 36(6): 802 -6. Van de Velde M, Teunkens A, Kuypers M, Dewinter T, Vandermeersch E. General anaesthesia with target controlled infusion of propofol for planned caesarean section: maternal and neonatal effects of a remifentanilbased technique. Int J Obstet Anesth 2004; 13: 153– 8. Mc. Guire W, Fowlie P W. Naloxone for narcotic-exposed newborn infants. Cochrane Database Syst Rev 2002: CD 003483 Ngan Kee. W D, Khaw K S, Ma K C, Wong A S, Lee B B, Ng F F. Maternal and neonatal effects of remifentanil at induction of general anesthesia for cesarean delivery: a randomized, GG ALNSF Høstkonress 2009 doubleblind, controlled trial. Anesthesiology 2006; 104: 14– 20

Anestesi under graviditet Relis. no: – Propofol Det finnes ikke data som tilsier at propofol har teratogene effekter, men muligheten kan heller ikke utelukkes da bruk av propofol i 1. og 2. trimester er dårlig dokumentert. GG ALNSF Høstkonress 2009
- Slides: 37