
Objectives By the end of this lecture the

Objectives • By the end of this lecture the student must be: A) Identify the Characters of Fungi B) describe the chemical tests for this genus • C) Differentiate between different sps. • D) List and match the symptoms, diagnosis and treatment for different sps.

Medical Mycology q. Myco = Fungi q. Ology = Science q. Mycology is the science deals with fungi q. Mycoses = Fungal infection q. Dermatophytosis - "ringworm" disease of the nails, hair, and/or stratum corneum of the skin caused by fungi called dermatophytes q. Dermatomycosis - more general name for any skin disease caused by a fungus 2

What is the FUNGUS? q. Eukaryotic → a true nucleus q. Do not contain chlorophyll q. Organoheterotrophic q. Cannot photosynthesize their own food q. Live either as saprophytes or parasites q. Have chitin cell walls q. Produce filamentous structures q. Reproduce by spores (sexual & asexual) q. Are aerobic life forms 3

What are Actinomyces? �True Bacteria (Prokaryotic) �Similar to fungi (fungi-like bacteria) WHY? 1. Clinical infection resembles mycoses 2. Grow on mycotic media 3. Grow slowly >48 h 4. Gross colonies resemble fungi § (rough, heaped, short aerial filaments) 5. Resemble mycelia microscopically, branched mycelia in tissue and smears with 4
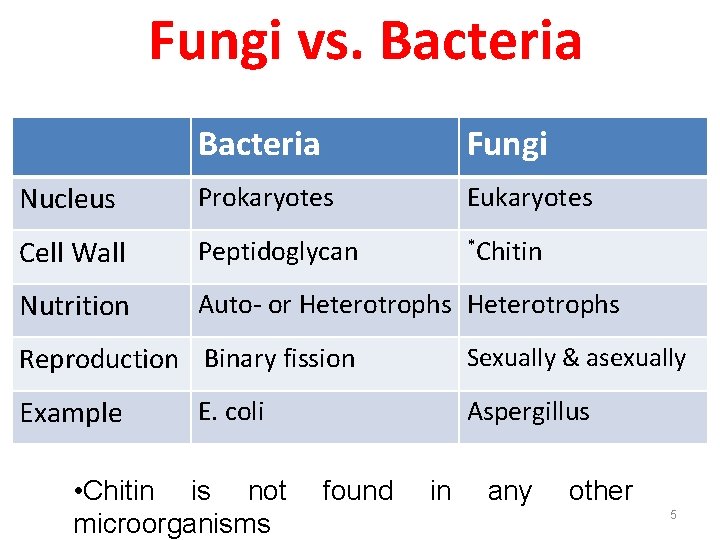
Fungi vs. Bacteria Fungi Nucleus Prokaryotes Eukaryotes Cell Wall Peptidoglycan *Chitin Nutrition Auto- or Heterotrophs Reproduction Binary fission Sexually & asexually Example Aspergillus E. coli • Chitin is not microorganisms found in any other 5

Types of fungi 1. Multicellular: Molds- filamentous �Penicillium, Aspergillus 2. Unicellular: Yeasts � Candida, Cryptococcus 3. Dimorphic Fungi � Dermatophytes, Histoplasma 6

YEAST �Facultative Anaerobes �Fermentation=ethanol and CO 2 �Non-filamentous unicellular fungi �Spherical or oval �Reproduction by �Fission or budding 7

DIMORPHIC FUNGI § Growth as a mold or as a yeast § Most pathogenic fungi are dimorphic fungi § At 37 o C yeast-like § At 25 o C mold-like § Can also occur with changes in CO 2 § Fungi grow differently in tissue vs nature/culture; often dictated by temp 8
Basic structure of fungi 1. Hyphae �Main body of most fungi is made up of fine, Cylindrical, branching threads called hyphae �Tubular cell wall filled with cytoplasm & organelles �Most hyphae are 2 -10 m diameter 2. Mycelia �When formed of many cells, cellular units connect together (intertwining) to form long filamentous A. Aerial mycelium �Part projects above the surface of medium B. Vegetative mycelium �Part penetrate into medium and absorb food 9
Basic structure of fungi • Septa—regular cross-walls formed in hyphae • Septate: Hyphae with septa - or • Aseptate or coenocytic: Lacking septa except to delimit reproductive structures & aging hyphae • Primary septa: Formed as a process of hyphal extension & generally have a septal pore, which allows for cytoplasmic & organelle movement • Secondary or adventitious septa are imperforate, formed to wall off ageing parts of the mycelium 10
Reproduction • Propagate via formation of spores • Sexual and asexual spores • The shape and type of spores are – Different from one type of fungi to another – Important in the classification & identification of different species of fungi 11
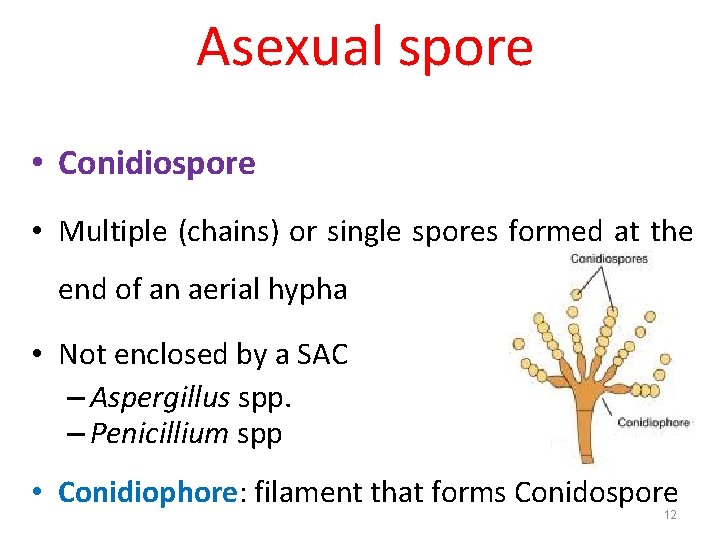
Asexual spore • Conidiospore • Multiple (chains) or single spores formed at the end of an aerial hypha • Not enclosed by a SAC – Aspergillus spp. – Penicillium spp • Conidiophore: filament that forms Conidospore 12
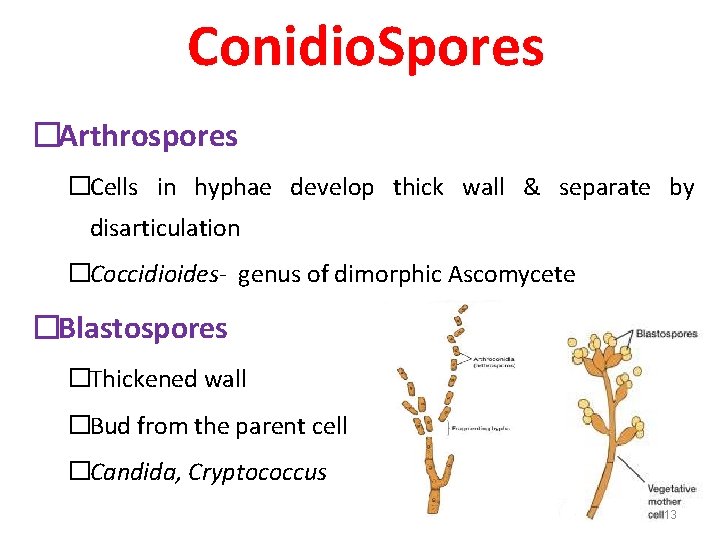
Conidio. Spores �Arthrospores �Cells in hyphae develop thick wall & separate by disarticulation �Coccidioides- genus of dimorphic Ascomycete �Blastospores �Thickened wall �Bud from the parent cell �Candida, Cryptococcus 13
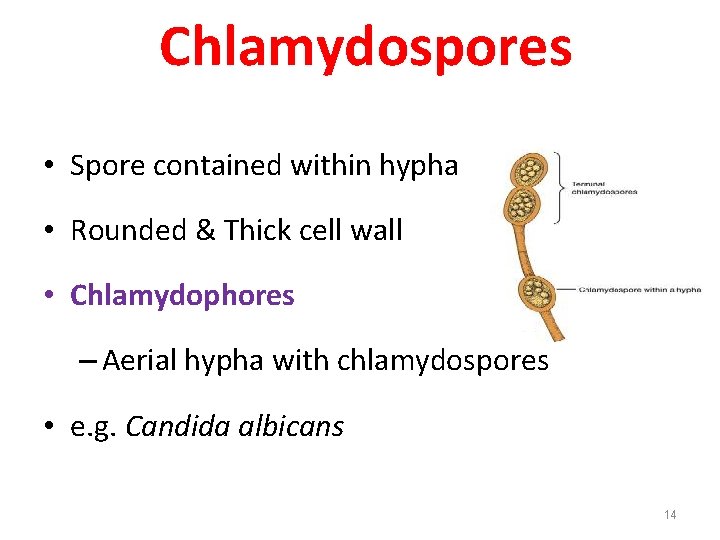
Chlamydospores • Spore contained within hypha • Rounded & Thick cell wall • Chlamydophores – Aerial hypha with chlamydospores • e. g. Candida albicans 14
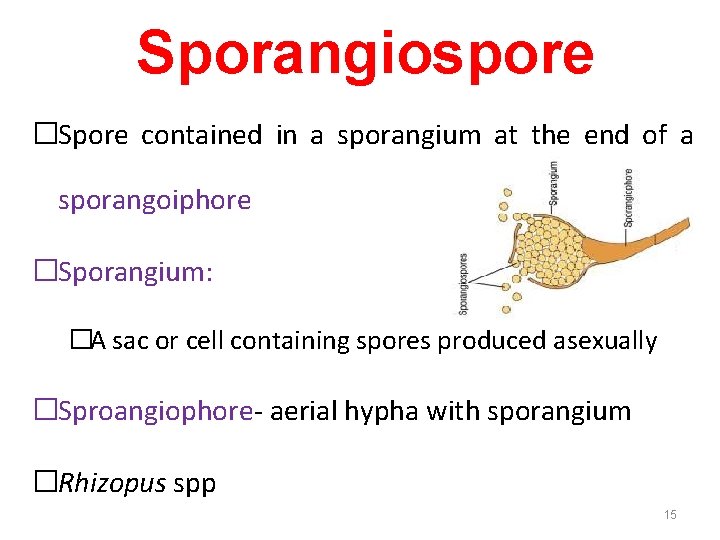
Sporangiospore �Spore contained in a sporangium at the end of a sporangoiphore �Sporangium: �A sac or cell containing spores produced asexually �Sproangiophore- aerial hypha with sporangium �Rhizopus spp 15

Sexual spores • Sexual spores - exhibit fusion of nuclei • Ascospore – Formed in sac-like cell (ascus) – Often 8 spores formed – Ascomycetes • Basidiospore – Produced on a specialized club-shaped structure (basidium) – Basidiomycetes • Zygospore – Thick-walled spore formed during sexual reproduction – Zygomycetes/ Mucor and Rhizopus 16
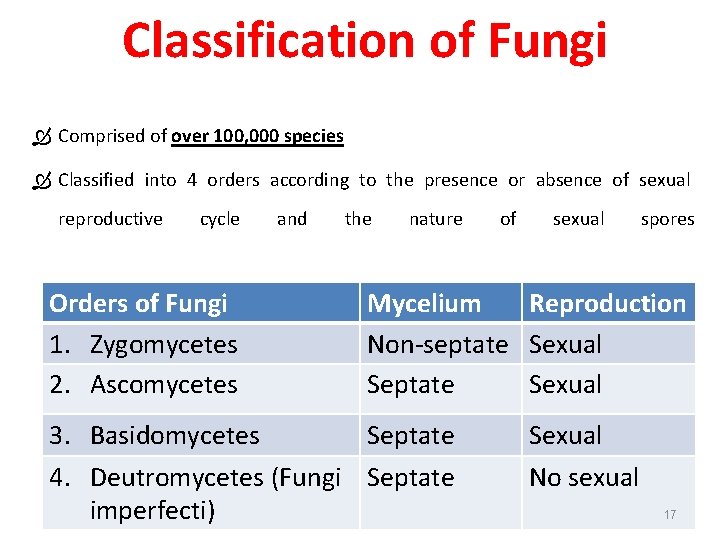
Classification of Fungi Comprised of over 100, 000 species Classified into 4 orders according to the presence or absence of sexual reproductive cycle Orders of Fungi 1. Zygomycetes 2. Ascomycetes and the nature of sexual spores Mycelium Reproduction Non-septate Sexual Septate Sexual 3. Basidomycetes Septate 4. Deutromycetes (Fungi Septate imperfecti) Sexual No sexual 17

ZYGOMYCETES • Phylum Zygomycota/Sexual/Non-septate • Lower fungi • < 1000 species • Produce zygospore, or sporangiospores • Include the common bread molds and other fungi that cause food spoilage • Mucor and Rhizopus are most familiar example 18

Ascomycetes • Phylum Ascomycota, Septate/Sexual/Higher fungi • Certain yeasts & some fungi that causes plant disease • Contains more than 30, 000 species of unicellular and multi-cellular fungi • Produce sexual spores (ascospores) • Produce asexual exospores (conidia) • Unicellular e. g. Saccharomyces, Candida • Multicellular e. g. Penicillum, Asperigullus, Claviceps, Dermatophytes, Sporothrix schenckii, Histoplasma 19

Basidomycetes • Phylum Basidiomycota/Septate/Sexual • Higher Fungi-Over 30, 000 different species • Sexual spores borne on clublike stalks (basidia) • Mushrooms (Agaricus bisporus, Agaricus campestris) are the most familiar members • Among Basidiomycota, only Malassezia & Cryptococcus are frequent human pathogens 20
Septate mycelium: Deutromycetes: • Fungi imperfecti • Sexual life cycle is either unknown or absent • Reproduce by various types of asexual spores including budding • Have an abundant mycelium at times while at other times they grow as yeast-like cells • Includes majority of pathogenic to man & animal • Resemble Ascomycetes in morphology • Examples: Trichophyton, Epidermophyton, Microsporon, Candida, Cryptococcus, Histoplasma 21
Fungal cell wall composition ØConsists of Ø 80% of polysaccharides ØPolysaccharide fibrils provide rigidity/integrity of wall Ø 20% of the wall consists of Proteins 1. Structural components (Fibrous) A. Chitin microfibrils �Polymers of ß (1 -4)-linked N-acetylglucosamine B. Chitosan (in Zygomycota only) �De-acetylated chitin C. ß-linked glucans �Polymers of β-1, 3 -linked glucose residues with short β -1, 6 -linked side chains 22
Fungal cell wall composition 2. Matrix components (Gel-like components) § Structural polymers are contained in gel-like matrix A. Mannoproteins § Glycoproteins (form matrix throughout wall) B. (1, 3) glucan 23
Structure of cell membrane �Semi-permeable �Phospholipid bilayer �Involved in uptake of nutrients �Anchorage for enzymes/proteins, e. g. , chitin synthase, glucan synthase, etc. �Signal transduction �Differs in that it contains ERGOSTEROL �Site of action for certain antifungal drugs n Human cell doesn't contain ergosterol n Human cell contains cholesterol 24
Medical Effect of Fungi • • I. Mycotoxicoses: Mould produces secondary metabolite (MYCOTOXINS) Highly toxic to humans Ingestion of toxic fungi or their metabolites Ergotism is caused by eating bread prepared from rye infected with Claviceps purpurea Historically, several large scale outbreaks of madness in populations have been attributed to ergotism Ergot are -adrenergic blockers inhibits response to adrenaline vasoconstriction necrosis gangaren Symptoms consisted of inflammation of infected tissue, followed by necrosis and gangrene 25

Medical Effect of Fungi �Natural occurrence: �Food products contaminated with AFLATOXINS include cereal (maize, rice & wheat), oilseeds (groundnut, soybean & cotton), spices (black pepper, coriander & zinger), tree nuts (almonds, and coconut) & milk �Physical and chemical properties: �Aflatoxins are potent toxic, carcinogenic, mutagenic, immunosuppressive agents, produced as secondary metabolites by Aspergillus flavus and A. parasiticus 26
Medical Effect of Fungi �II. Hypersensitivity Disease: �Fungal spores are inhalated �They can be an antigenic elicit immune response production of Ig or sensitized lymphocyte �Example is hypersensitivity pneumonitis 27
Medical Effect of Fungi �III. Colonization and resultant disease: �They may attack: 1. Outermost layers of Skin, hair and/or mucous membrane superficial mycoses 2. Epidermis as well as nail and hair cutaneous mycoses 3. Dermis, subcutaneous tissues, muscle and face Subcutaneous mycoses 4. The internal organs as the lungs, CNS, bones etc. systemic mycoses 5. Opportunistic - cause infection only in the immunocompromised 28

A. Superfacial mycosis 1. Tinea versicolor (Pityriasis versicolor) 2. Tinea nigra • They are extremely superficial mycoses • Primary Manifestation is pigment change of the skin • Both are named for their respective skin manifestation 29

Tinea versicolor (Pityriasis versicolor) • Causative agent: Malassezia globosa – Less common-Malassezia furfur • Lipophilic Yeasts belongs to Basidomycota • Normal flora of skin and scalp • Superficial opportunistic pathogens of the skin • Associated with seborrheic dermatitis, dandruff (Pityriasis capitis) and atopic dermatitis • Pityriasis versicolor is chronic superficial mycoses • Characterized by a blotchy discoloration of skin which may itch • With sunlight exposure the skin around patches will tan, but patches remains white 30

Pityriasis versicolor • Chronic superficial mycoses • Characterized by hyperpigmented lesions – Well-demarcated white, pink, or brownish lesions, often coalescing and covered with thin furfuraceous scales • The colour varies according to; – The normal pigmentation of the patient – exposure of the area to sunlight – the severity of the disease. • Lesions occur on the trunk, shoulders and arms, • Rarely on the neck and face • Fluoresce a pale greenish colour under Wood's ultraviolet light. 31

B. cutaneous Mycoses �Dermatophytes attack keratinous structure of skin, hair and nail and cause the group of disease known as Ringworms or Tinea �Candida can attack the skin, the mucous membranes and rarely the internal organs �Non-dermatophyte moulds e. g. Hendrsonula toruloidea, Scytalidium hyalium, Scopulariopsis brevicaulis 32

i. Dermatophytes • Confined to the outer layers of skin, hair & nails • Do not invade living tissues • Called dermatophytes (keratinophilic fungi) • Produce extracellular keratinas hydrolyze keratin • Utilize keratin for their nutrition • Keratin is the chief protein in skin, hair and nail • They caused dermatophycosis“Ringworm" or “Tinea" • Dermatophycosis refers to the characteristic central clearing that often occurs in dermatophyte infections 33

I. dermatophytes 1. Trichophyton (19 species) �Affect hair, skin & nails �Infect both children & adults 2. Epidermophyton �Infect skin, nails (rarely hair) �Infect adults, rarely in children (ringworm) �Epidermophyton floccosum 3. Microsporum (13 species) �Affect hair, skin (rarely nails) �Frequently in children, rarely in adults �M. canis is the most common infect man 34
Ecology and Mode of transmission • To determine the source of infection • Anthrophilic – Some Dermatophytes affect man only – Person -to-person transmission through contaminated objects (comb, hat, etc. ) – T. rubrum and T. mentagrophytes • Zoophilic – Other affect animal mainly – Direct transmission to humans by close contact with animals – M. canis and T. verrucosum 35
Ecology and Mode of transmission • Geophilic – Other live in soil and can affect man – Transmitted to humans by direct exposure – M. gypseum • Each geographic locality has its own dermatophyton – T. violacium is the prevalent causative organism of Tinea capitis in Egypt – M. audouini is prevalent cause in England 36

Tinea corporis �Small lesions occurring anywhere on the body �Causative agent: �Trichophyton rubrum, T. mentagrophytes, M. canis, and M. audouinii �Live on the skin surface (opportunistic) �Reservoir: Humans, soil & animals �Acquired by person-to-person transfer usually via direct skin contact with infected individual �Animal-to-human transmission is common 37

Tinea pedis "athlete's foot" �Infection of toe webs and soles of feet �Causative agent: �Trichophyton rubrum, T. mentagrophytes and Epidermophyton floccosum �Requires warmth and moisture to survive and grow �Causes scaling, flaking & itch of affected areas �Reservoirs: Humans �Athlete's foot is a communicable disease �Transmission: when people who regularly wear shoes go barefoot in a moist environment 38

Tinea capitis �Infection of the scalp �Causative agent: �Trichophyton and Microsporum invade the hair shaft �Trichophyton infection prevail in Central America to USA & in parts of Western Europe �Microsporum infection are in South America, Southern & Central Europe, Africa & Middle East �Reservoirs: Humans & animals (dogs, cats and cattle) �Transmitted by humans, animals or objects that harbor 39 the fungus
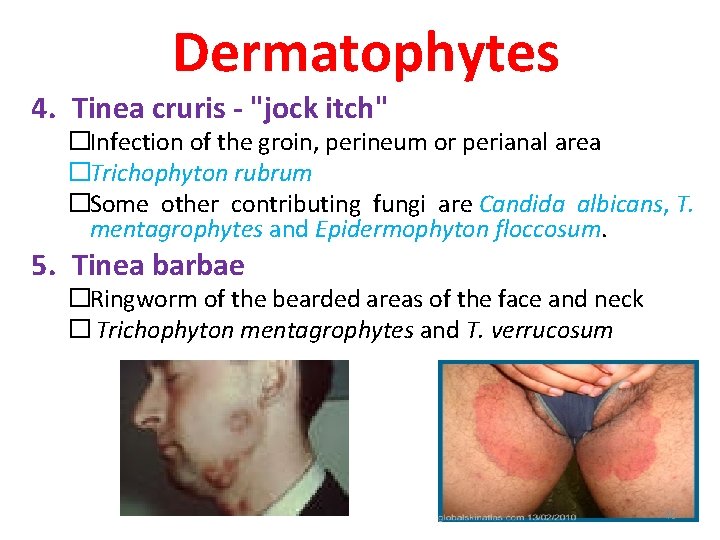
Dermatophytes 4. Tinea cruris - "jock itch" �Infection of the groin, perineum or perianal area �Trichophyton rubrum �Some other contributing fungi are Candida albicans, T. mentagrophytes and Epidermophyton floccosum. 5. Tinea barbae �Ringworm of the bearded areas of the face and neck � Trichophyton mentagrophytes and T. verrucosum 40

Dermatophytes 6. Tinea unguium (onychomycosis) – Infection of nails – Common - Trichophyton rubrum – Less common- T. interdigitale, Epidermophyton floccosum, T. violaceum, Microsporum gypseum, T. tonsurans, T. soudanense – Reservoirs: Humans and rarely animals or soil 41

Treatment of Dermatophytes �All are sensitive to grisofulvin �Tolfnatate available over the counter – Topical �Terbinifine (Lamisil) - oral, topical. �Ketoconazole seems to be most effective for tinea versicolor and other dermatophytes �Itraconazole - oral �Echinocandins (caspofungin) 42

Lab diagnosis of Dermatophytes • Specimen collection – Skin Scrapings, nail scrapings and epilated hairs • Direct Microscopy – Specimens should be examined using 10% KOH and Parker ink or calcofluor white mounts – Characteristic hyphae can be seen 43

Lab diagnosis of Dermatophytes • • Culture Specimens should be inoculated onto Sabouraud's dextrose agar (General purpose) Selective – Mycosel agar – Gentamicin: inhibits normal bacterial flora – Cycloheximide: inhibits saprophytic fungi – containing cycloheximide and incubated at 250 C for 4 weeks – The growth of any dermatophyte is significant 44
II. Candida • Yeast-like organism that lives as a commensal in oral mucosa, throat, skin, scalp, vagina, fingers, nails, bronchi, lungs, or intestine and vagina • Opportunistic organism • The causative agent of candidiasis – C. albicans, C. tropicalis & C. glabrata • Candidiasis encompasses infections that range from superficial such as thrush and vaginitis • Rarely become systemic in immunocompromised patients – Septicaemia, endocarditis and meningitis 45

Symptoms of Candida albicans • Thrush appears as creamy-white or bluish-white patches on the tongue - which is inflamed and sometimes-beefy red - and on the lining of the mouth, or in the throat. • Diaper rash caused by candida is an inflammation of the skin, usually red and sometimes scaly. • Vaginitis is characterized by a white or yellow discharge. – Inflammation of the walls of vagina and of the vulva (external genital area) causes burning and itching. • Infections of the fingernails and toenails appear as red, painful swelling around the nail. • Later, pus may develop. 46
Laboratory diagnosis of candida • Specimen: – A scraping or swab of the affected area or blood (candidemia) is placed on a microscope slide • Microscopic examination – A drop of 10% KOH solution is added to the specimen. – KOH dissolves the skin cells, but leaves Candida intact, permitting visualization of pseudohyphae and budding yeast cells typical of many Candida species. • Culture – Swab/blood is streaked on a culture SDA medium – The culture is incubated at 37°C for several days – The characteristics of colonies may allow initial diagnosis of organism causing disease symptom 47
Laboratory diagnosis of candida • A germ tube test is a diagnostic test in which a sample of fungal spores are suspended in serum and examined by microscopy for the detection of any germ tubes • It is particularly indicated for colonies of white or cream color on fungal culture, where a positive germ tube test is strongly indicative of Candida albicans 48

Treatment of candidacies – Oral drugs: Amphotericin B, fluconazole, and ketoconazole, are the drugs most commonly used to treat candidiasis – Topical administration of antifungal drugs such as clotrimazole, miconazole , tioconazole, and nystatin – The drug of choice is nystatin 49
c. Subcutaneous Mycoses �Rare �Confined to subcutaneous tissue & rarely spread systemically �Confined mainly to tropical regions �Include heterogeneous group of soil fungal infections �Introduced into the extremities by trauma/wound �Tend to be slow in onset and chronic in duration �The main subcutaneous fungal infections include �Sporotrichosis, chromoblastomycosis, MYCETOMA, lobomycosis, rhinosporidiosis, subcutaneous zygomycosis, & subcutaneous phaeohyphomycosis 50

C. Subcutaneous Mycoses 1. Sporotrichosis caused by Sporothrix schenckii �The fungus is saprophyte on dead plant material �Dimorphic fungi �Colonies of media at 250 C have delicate radiating forms that appear as white at first but turned black with prolonged incubation �Microscopic examination reveals branched hyphae with numerous conidia 51

Sporotrichosis • It was once common in Europe but cases are now rare • Most prevalent in Americas, South Africa & Australia • Infection usually follows and insect bite, thorn pricks or scratches from a fish spine. • Certain occupation groups appear to have increased risk from infection • These include florists, farm workers and others who handle hay and moss • The most common symptom is an ulcerative lesion that may develop into lymphangitis • Treated by saturated solution of KI and Amphotericin B 52

2. Chromoblastomycosis � Chronic, localized, slowly progressive infection of the subcutaneous tissue caused by several species of dematiaceous fungi � Tissue proliferation occurs around the area of inoculation producing crusted, verrucose, wartlike lesions � Causative agent �Most common: Cladophialophora carrionii & Fonsecaea pedrosoi �Less common: Fonsecaea compactum, Phialophora verrucosa 53
Chromoblastomycosis • Mode of Transmission • Traumatic implantation of fungal elements into skin • The infection occurs in tropical or subtropical climates, often in rural areas. • Traetment • Chromoblastomycosis treated by surgical removal and 5 -flurocytosine 54

Mycetoma �Also called Maduromycosis or Madura foot �Madura foot referring to first case seen in Madura region of India which was in the foot of patient �Syndrome involving cutaneous & subcutaneous tissues, fascia, and bone �Infection focused in one area of the body (Foot) �Distribution: World-wide but most common in barefooted populations in tropical sub- or regions �Characterized by draining sinuses, granules (vary in size, colour & degree of hardness) & tumefaction 55
Mycetoma • Mode of transmission – Traumatic implantation of causative agent • Causative agent (50% bacteria & 50% fungi) • Soil-inhabiting bacteria (actinomycotic mycetoma or actinomycosis) – Actinomadurae, Actinomyces israelii and Nocardia brasiliensis • Soil-inhabiting fungi (eumycetoma) Madurella mycetomatis & Madurella grisea 56

Treatment �Treatment for eumycetoma is less successful than for actinomycetoma �EUMYCETOMA �surgical treatment is still usually required �Ketoconazole 400 mg daily, itraconazole 300 mg daily & IV amphotericin B 50 mg daily �Therapy is suggested for 1 -2 years �Flucytosine, Topical nystatin & potassium iodide � ACTINOMYCOTIC MYCETOMA � Penicillin, gentamicin & co-trimoxazole for 5 weeks � Followed by maintenance therapy with amoxicillin & co-trimoxazole 57
Systemic Mycoses �Invasive infections of the internal organs with the organism gaining entry by; �Lungs, GIT or through intravenous lines �They may be caused by: 1. Primary (TRUE) pathogenic fungi 2. Opportunistic fungi that are of marginal pathogenicity but can infect the immunocompromised host 58
I. Primary Pathogenic Fungi • Histoplasma capsulatum (Histoplasmosis ) • Blastomyces dermatidis (Blastomycosis ) • Coccidioides immitis (Coccidiomycosis) • Paracoccidioides brasiliensis (paracoccidioidomycosis) • Dimorphic fungi normally found in soil • Infection occurs in previously healthy persons • Arises through the respiratory route (inhalation) 59

Histoplasmosis • Caused by dimorphic Histoplasma capsulatum • H. capsulatum is endemic in many parts of the world including North and South America • It is found in the soil and growth is enhanced by the presence of bird and bat excreta • Environments containing such material are often implicated as sources of human infection 60
Histoplasmosis • Lungs are the main site of infection but dissemination to liver, heart & CNS can occur. • Pulmonary infection can resemble symptoms seen in tuberculosis • Treatment: – Amphotericin B – Ketoconazole and other new azoles 61

II. Opportunistic Fungi • Patients usually have some serious immune or metabolic defect, or have undergone surgery • The diseases include aspergillosis, systemic Candidiasis, cryptococcosis, Zygomycosis, Pneumocystis carinii • Exceptionally, other fungi that are normally not pathogenic, such as Trichosporon, Fusarium or Penicillium, may cause systemic infections. 62

Cryptococcosis • Systemic infection caused by encapsulated yeast - Cryptococcus neoformans • Inhabits soil around pigeon roosts • Host defense is CMI • Affects both healthy & immunosuppressed individuals • Common infection of AIDS, cancer or diabetic • Primary infection in lungs via inhalation • Pulmonary infection leads to cough, fever & lung nodules • Polysaccharide capsule resists phagocytosis • Cryptococcal meningitis is most common disseminated manifestation • Can spread to skin, bone and prostate 63

Cryptococcosis �Lab. Diagnosis �Lumbar puncture and microscopic examination of cerebrospinal fluid is diagnostic �India Ink for CSF �Culture on SDA �White mucoid colonies within 48 hours �Cryptococcal antigen �Serum and CSF are 99% sensitive in AIDS �Serum is less sensitive in normal hosts �Treatment �Amphotericin B and fluconazole 64

Aspergillosis • Aspergillus is found in soil, on plants & in decaying organic matter. • 600 species, A. fumigatus is one of the most ubiquitous of the airborne saprophytic fungi • A. fumigatus is the main causative agent of Aspergillosis • Diseases of the soil fungus called Aspergillus • Major portal of entry is the respiratory tract – Via inhalation of conidia • Conidia are eliminated in immunocompetent host by innate immune mechanism • For people with weakened immune systems, breathing in conidia can lead to infection 65

Aspergillosis • Most commonly affects the sinuses or lungs • Symptoms of sinus infections include fever, headache, and sinus pain • Lung infections can cause fever and cough • In the immunosuppressed host, Aspergillus can disseminate throughout the body. • Treatment • Amphotericin B and nystatin • Voriconazole is currently the first-line treatment for invasive aspergillosis 66
Candidiasis • In severely immunocompromised patients, C. albicans can proliferate and disseminate throughout the body. • An infection in the bloodstream can affect the kidneys, heart, lungs, eyes, or other organs causing high fever, chills, anemia, and sometimes a rash or shock 67
Symptoms of Candida albicans • Candida can cause the following problems depending upon the organ infected: – in kidneys can cause blood in the urine – in heart can cause murmurs & valve damage – in the lungs can cause bloody sputum – in the eyes can cause pain and blurred vision – in the brain cause seizures and acute changes in mental function or behavior 68
- Slides: 68