
Nursing Assessment of the Cardiovascular System Keith Rischer









- Slides: 40
Nursing Assessment of the Cardiovascular System Keith Rischer RN, MA, CEN 1
Today’s Objectives… Ø Ø Ø Review the anatomy and physiology of the cardiovascular system. Describe cardiovascular changes associated with aging. Identify factors that place patients at risk for cardiovascular problems. Explain and describe pre- and post-care associated with diagnostic cardiovascular testing. Explain the purpose of hemodynamic monitoring. 2
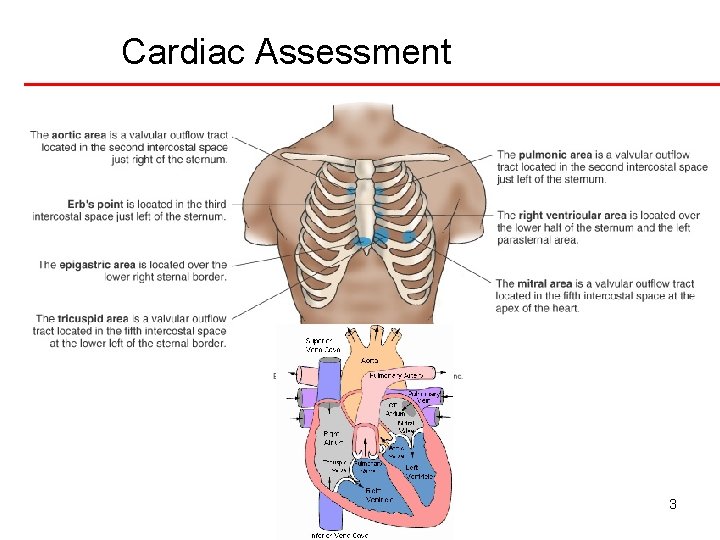
Cardiac Assessment 3
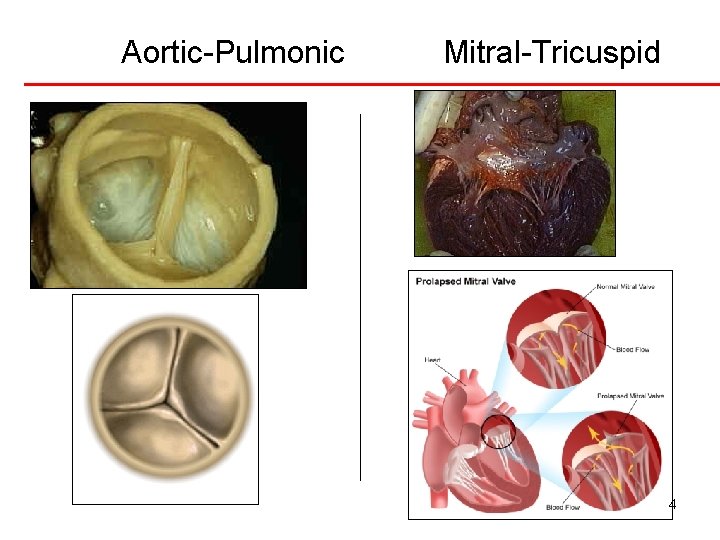
Aortic-Pulmonic Mitral-Tricuspid 4
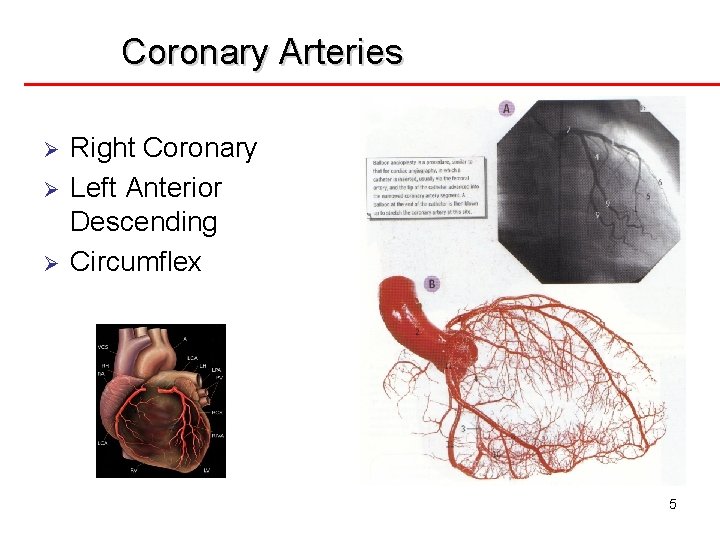
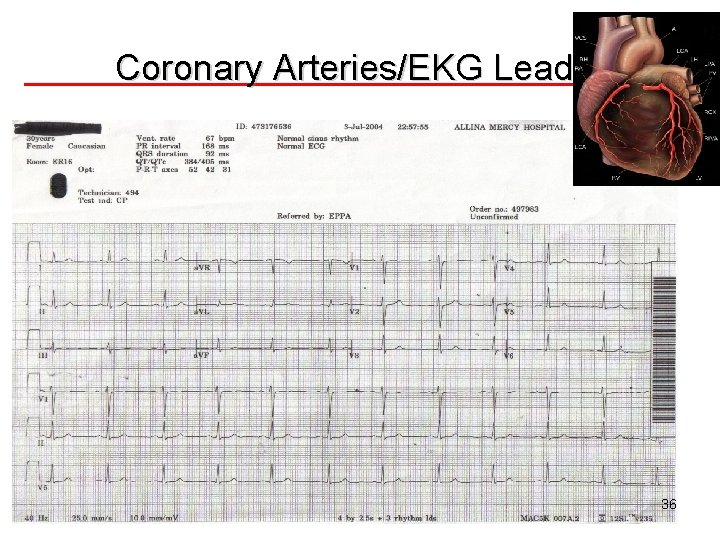
Coronary Arteries Ø Ø Ø Right Coronary Left Anterior Descending Circumflex 5
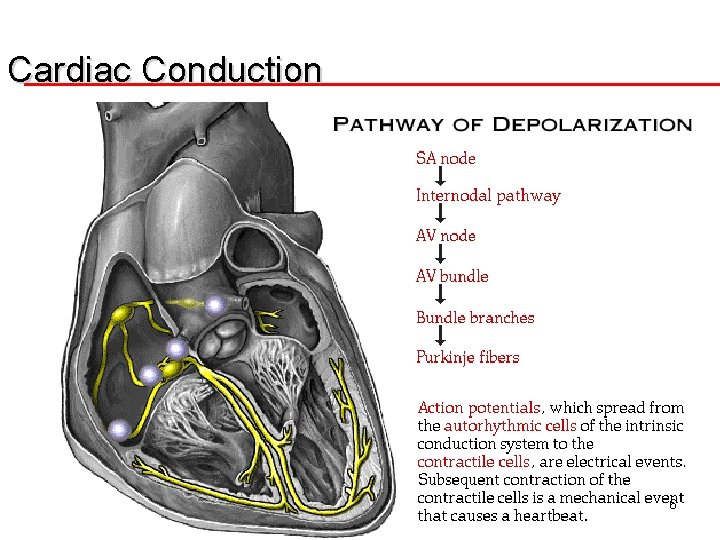
Cardiac Conduction SA node Both Atria AV Node Both Ventricles Bundle of His Bundle Branches - Perkinje Fibers 6
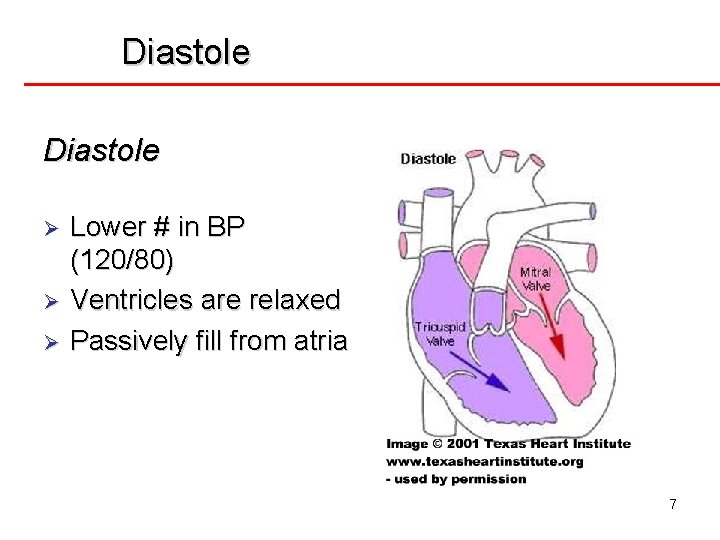
Diastole Ø Ø Ø Lower # in BP (120/80) Ventricles are relaxed Passively fill from atria 7
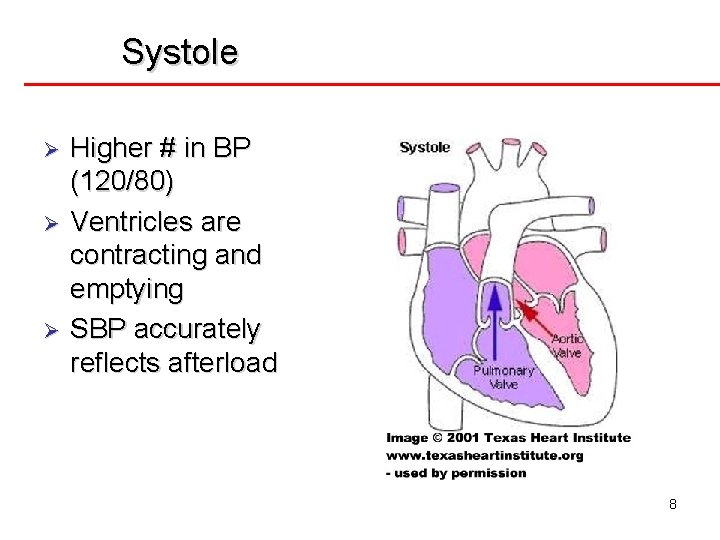
Systole Ø Ø Ø Higher # in BP (120/80) Ventricles are contracting and emptying SBP accurately reflects afterload 8
Cardiac Output v. CO = Stroke volume x heart rate v. SV (80 cc) x HR (80)= 6400 cc (6. 4 lpm) • Daily pumps 1800 gallons • 657, 000 gallons every year • Over 80 year lifetime: • 52, 560, 000 gallons 9
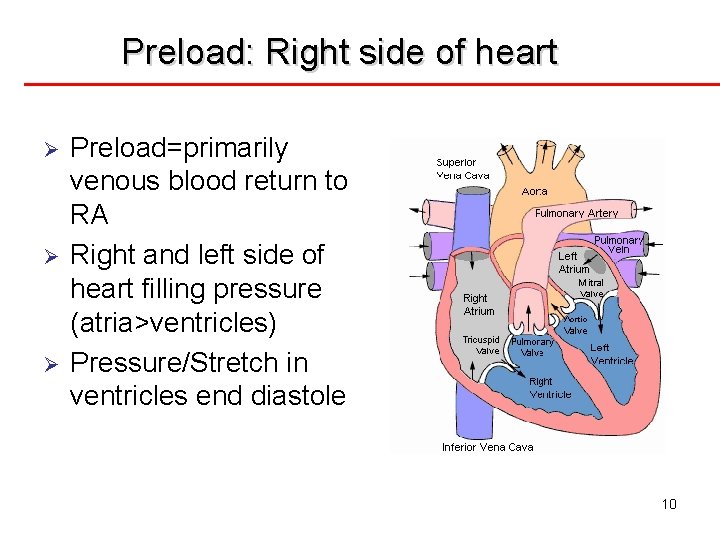
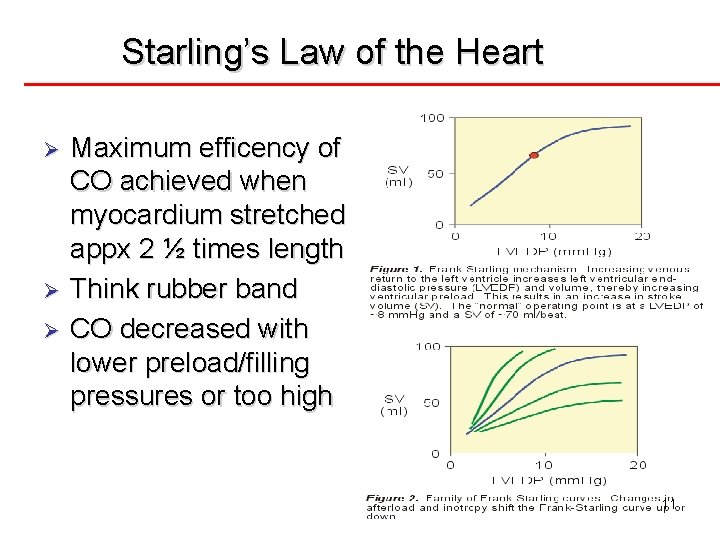
Preload: Right side of heart Ø Ø Ø Preload=primarily venous blood return to RA Right and left side of heart filling pressure (atria>ventricles) Pressure/Stretch in ventricles end diastole 10
Starling’s Law of the Heart Ø Ø Ø Maximum efficency of CO achieved when myocardium stretched appx 2 ½ times length Think rubber band CO decreased with lower preload/filling pressures or too high 11
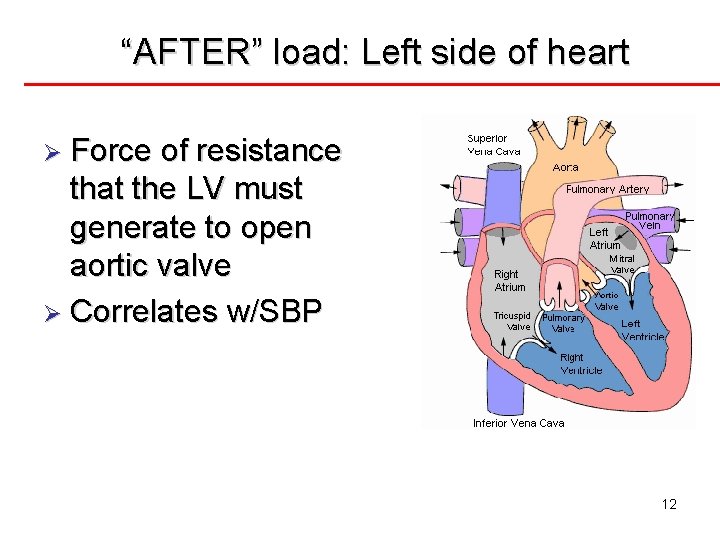
“AFTER” load: Left side of heart Ø Force of resistance that the LV must generate to open aortic valve Ø Correlates w/SBP 12
Contractility Ø Ability of heart to change force of contraction without changing resting length Ø Influenced by Ca++ Ø Inotropic-Influencing contractility independent of Starling mechanism q Positive inotropic q Negative inotropic 13
Assessment Techniques Ø History q Demographic data ü Age ü Gender ü Pre vs. post menopause q Family history and genetic risk q Personal medical history ü DM, HTN ü BCP use for women q Diet 14
Modifiable Risk Factors Cigarette smoking Ø Physical inactivity Ø Obesity Ø Psychological factors Ø Chronic disease Ø 15
Changes with Aging Ø Ø Ø Calcification in valves Pacemaker cells decrease in number Conduction time increases Left ventricle increases Aorta and large vessels thicken and become stiffer Baroreceptors less sensitive 16
Women & CAD Ø Ø Vague-atypical chief c/o q Only 53% have CP as chief c/o q Fatigue chief c/o Typically develop CAD 10+ years later then men Mortality twice as high q Less likely to have definitive 12 lead EKG q Smaller coronary arteries q Higher prevalence of silent ischemia q CABG higher mortality rate/complications q After first MI-more likely to suffer fatal event Women > 50 pay must address HTN, high cholesterol, family history, diabetes 17
Men Ø Ø Develop 10 -15 years earlier Initial event AMI Classic CP sx Develop greater collateral circulation compared to women Women Ø Ø Influence of menopause… 4 x risk Causes more deaths in women than men Initial event angina Atypical CP sx…fatigue 18
Elderly & CAD Ø More likely to have vague, atypical c/o Ø SOB, fatigue, syncope or falls Ø Any fall must be investigated for mitigating circumstances Ø Less likely to have radiation 19
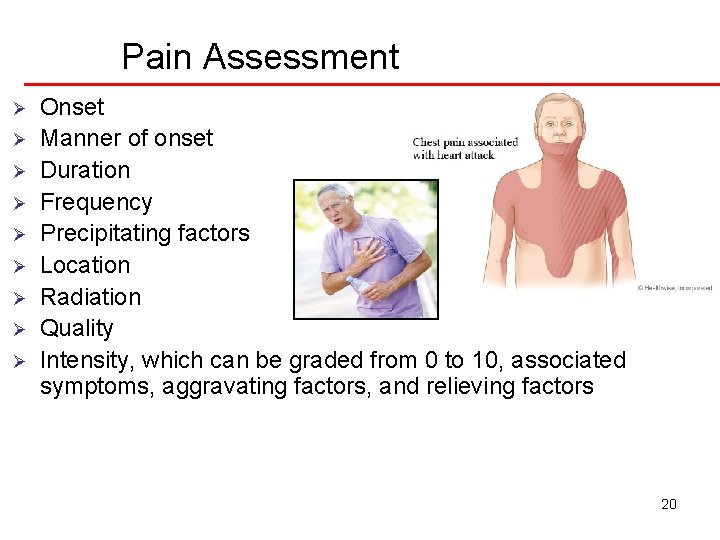
Pain Assessment Ø Ø Ø Ø Ø Onset Manner of onset Duration Frequency Precipitating factors Location Radiation Quality Intensity, which can be graded from 0 to 10, associated symptoms, aggravating factors, and relieving factors 20
ED Case Study Ø Ø Ø Ø D. K. is a 59 y. o. female who presents to ED for evaluation of chest pain/pressure. Patient was at the Chanhassen Dinner Theatre and reports her symptoms began around 1800 and felt nausea and lightheaded with a little chest pressure. Patient reports she started to feel clammy and waited a little while and started having sharp chest pain 10/10 around 2100 that radiated into her back and shoulder and her jaw went numb. Patient took Nitroglycerin SL and then another in 10 minutes Patient reports she her chest pain started to go away but her chest pressure has "never gone away". Patient's friend convinced her to call EMS around 2130. Patient was give IV Zofran and fluids en route. Patient currently denies jaw pain but reports her chest pressure is a 5/10. Patient has a history of 2 stents in 2006, Type 2 Diabetic. 1/2 PPD smoker. Patient currently has no nausea. Patient denies shortness of breath. Patient denies fever or chills. Patient denies numbness or tingling in extremities. Patient is a 21
ED Case Study: Nursing Assessment T-99 P-88 R-20 BP-162/88 sats 99% 2 l Ø Head to toe unremarkable Ø q breath sounds clear q pulses strong and equal, S 1 S 2 q Color pink warm/dry q NSR 80’s q Continues to c/o CP 5/10 q 12 lead EKG no acute changes-normal 22
Priorities… Medical Ø Nursing Ø 23
Rapid Response: Chest Pain Ø Situation: 6/12: 41 yr. male wakes up and complains of chest tightness and rates it at 9/10. q q q Ø Respirations are shallow Was given 3 doses of nitro with some relief, but it was also noted that chest pain is going on and off with nitro use. EKG shows no changes from 2007 results Left chest pain increases with movement, deep inspiration with radiation to left arm VS: T-99 P-88 (NSR) R-20 BP-162/90 sats 99% RA Background: q q Admitted 6/07 for chemotherapy due to dx Hodgkins Lymphoma PMH: HIV, CA of rectum, HTN, Anxiety 24
Clinical Manifestations: Dyspnea Ø Ø Ø Can occur as a result of both cardiac and pulmonary disease Difficult or labored breathing experienced as uncomfortable breathing or shortness of breath Dyspnea on exertion (DOE) Orthopnea q dyspnea when lying flat Paroxysmal nocturnal dyspnea (PND) q after lying down for several hours 25
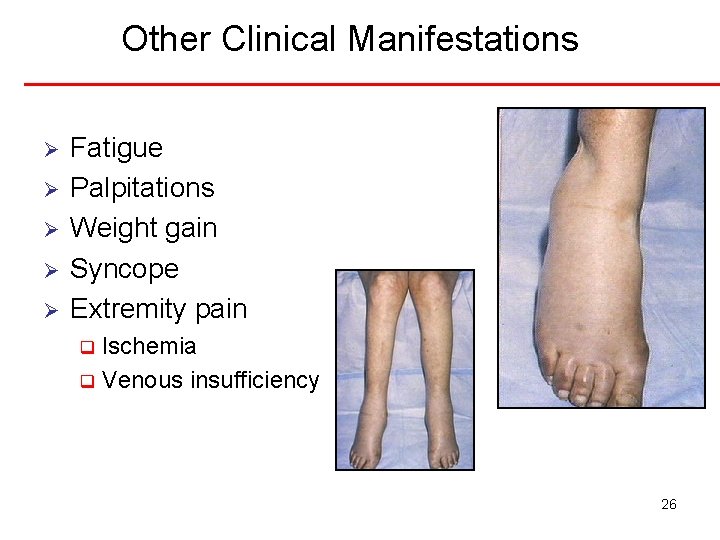
Other Clinical Manifestations Ø Ø Ø Fatigue Palpitations Weight gain Syncope Extremity pain Ischemia q Venous insufficiency q 26
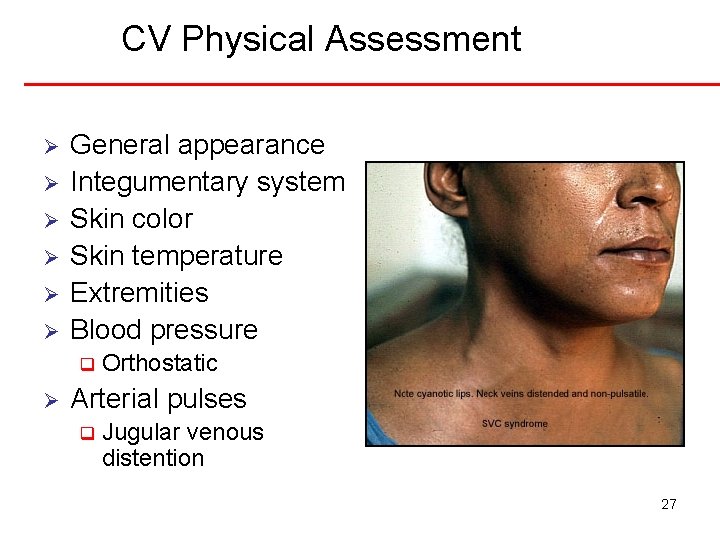
CV Physical Assessment Ø Ø Ø General appearance Integumentary system Skin color Skin temperature Extremities Blood pressure q Ø Orthostatic Arterial pulses q Jugular venous distention 27
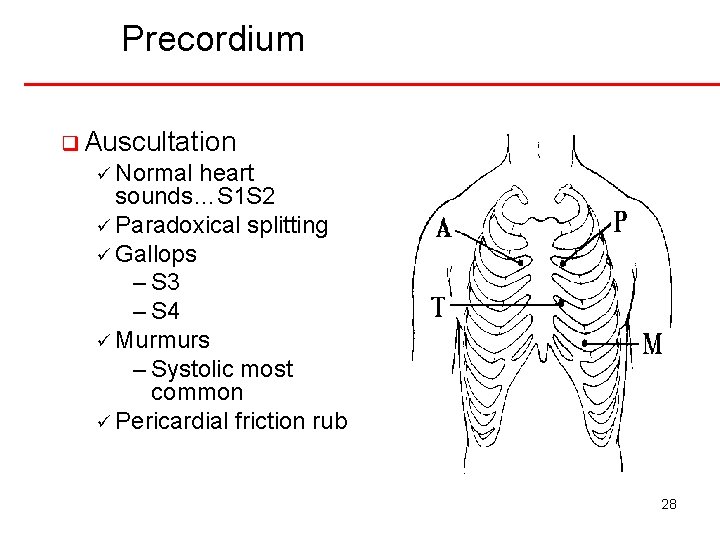
Precordium q Auscultation ü Normal heart sounds…S 1 S 2 ü Paradoxical splitting ü Gallops – S 3 – S 4 ü Murmurs – Systolic most common ü Pericardial friction rub 28
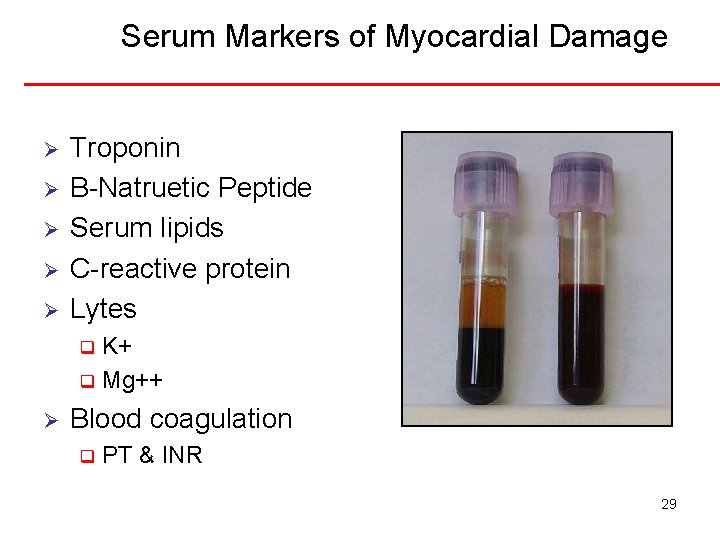
Serum Markers of Myocardial Damage Ø Ø Ø Troponin B-Natruetic Peptide Serum lipids C-reactive protein Lytes K+ q Mg++ q Ø Blood coagulation q PT & INR 29
Brain Natriuetic Peptide: BNP Ø Ø Ø 95 % of BNP resides in ventricles As pressure inc in ventricles in HF-BNP is released Bodies own ACE/B-blocker Only lab test that measures HF Normal is less than 100 q Elevated 100 -500 q + for CHF >500 Ø Uses: dx- assess response to tx 30
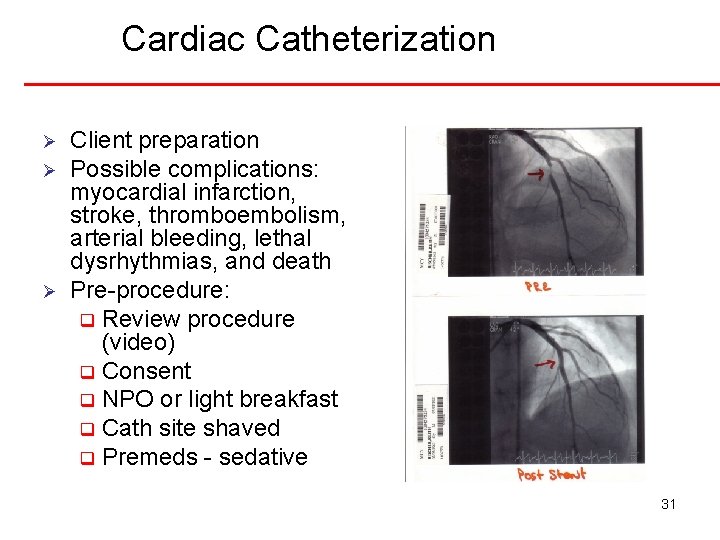
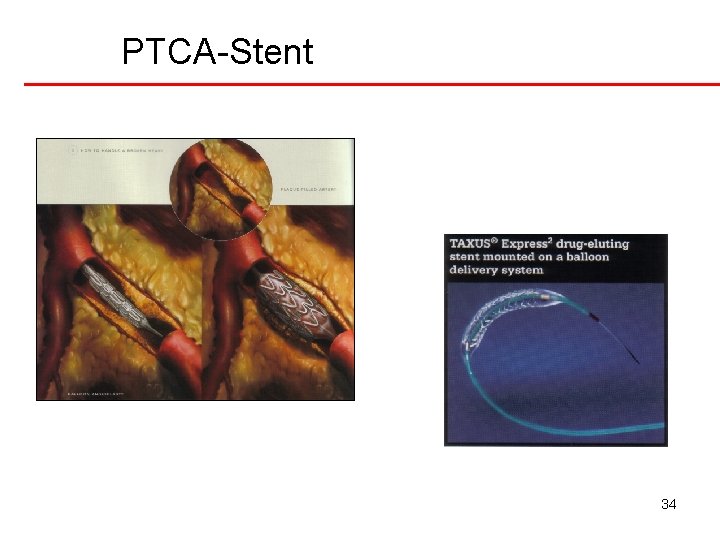
Cardiac Catheterization Ø Ø Ø Client preparation Possible complications: myocardial infarction, stroke, thromboembolism, arterial bleeding, lethal dysrhythmias, and death Pre-procedure: q Review procedure (video) q Consent q NPO or light breakfast q Cath site shaved q Premeds - sedative 31
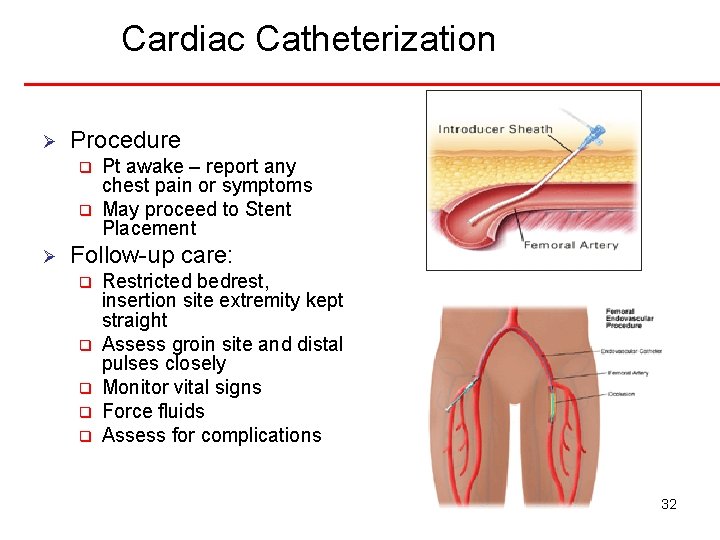
Cardiac Catheterization Ø Procedure q q Ø Pt awake – report any chest pain or symptoms May proceed to Stent Placement Follow-up care: q q q Restricted bedrest, insertion site extremity kept straight Assess groin site and distal pulses closely Monitor vital signs Force fluids Assess for complications 32
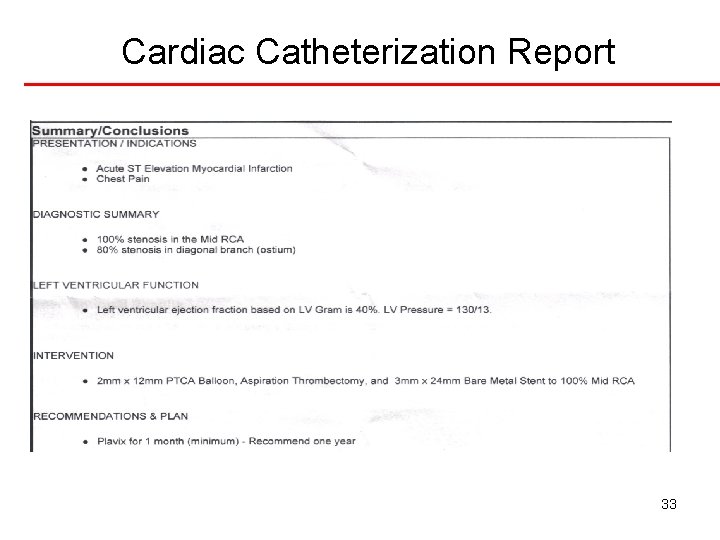
Cardiac Catheterization Report 33
PTCA-Stent 34
Other Diagnostic Tests 12 lead EKG Ø Holter monitor (ambulatory) Ø Electrophysiologic (EP) study Ø Exercise Stress test Ø Echocardiography Ø q Pharmacologic stress echocardiogram q Transesophageal echocardiogram Ø Thallium imaging 35
Coronary Arteries/EKG Leads 36
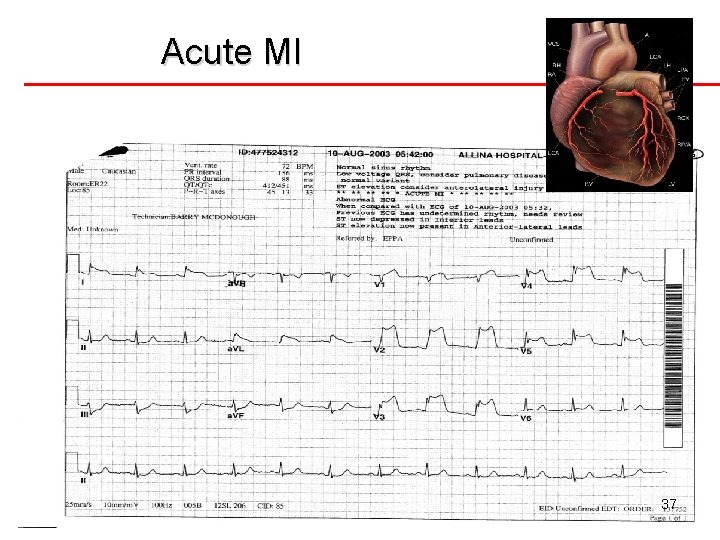
Acute MI 37
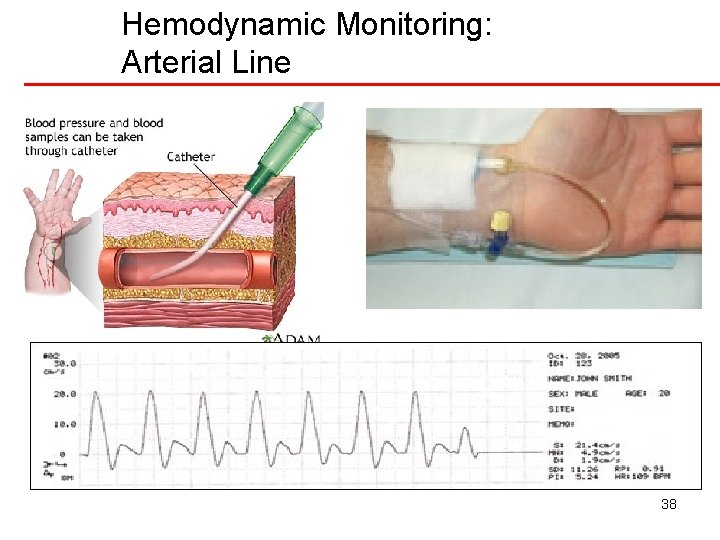
Hemodynamic Monitoring: Arterial Line 38
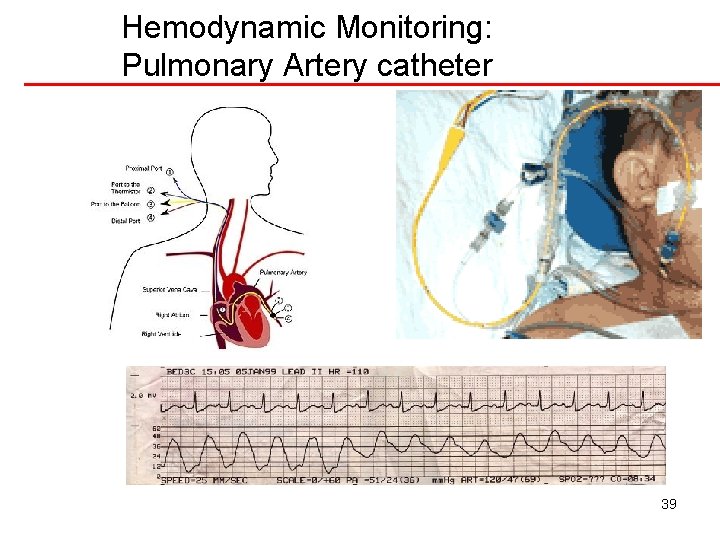
Hemodynamic Monitoring: Pulmonary Artery catheter 39
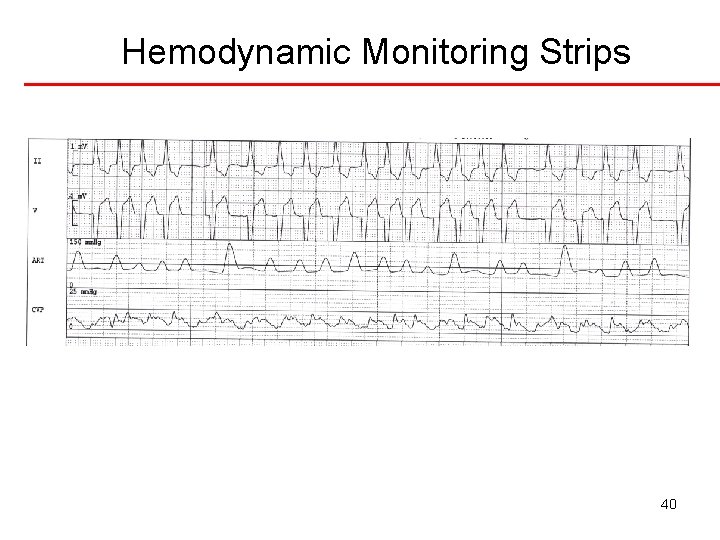
Hemodynamic Monitoring Strips 40