
North of England Falls Network Dr Fiona Shaw


















- Slides: 21
North of England Falls Network Dr Fiona Shaw Consultant Physician and Geriatrician, Newcastle upon Tyne Hospitals Trust Chair North East Regional Falls Task Group Chair North of England Falls Network Dr John Davison Consultant Geriatrician, Falls & Syncope Service Assistant Director of Medical Education, Newcastle upon Tyne Hospitals Trust Vice Chair North East Regional Falls Task Group
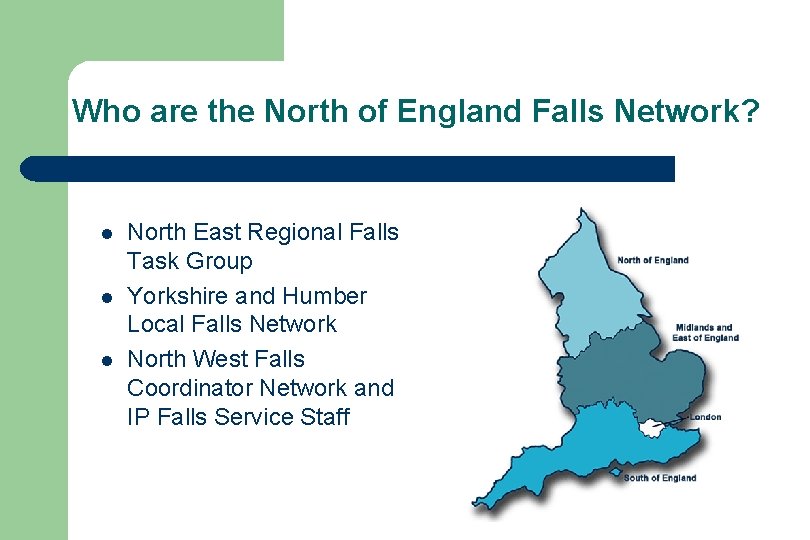
Who are the North of England Falls Network? l l l North East Regional Falls Task Group Yorkshire and Humber Local Falls Network North West Falls Coordinator Network and IP Falls Service Staff
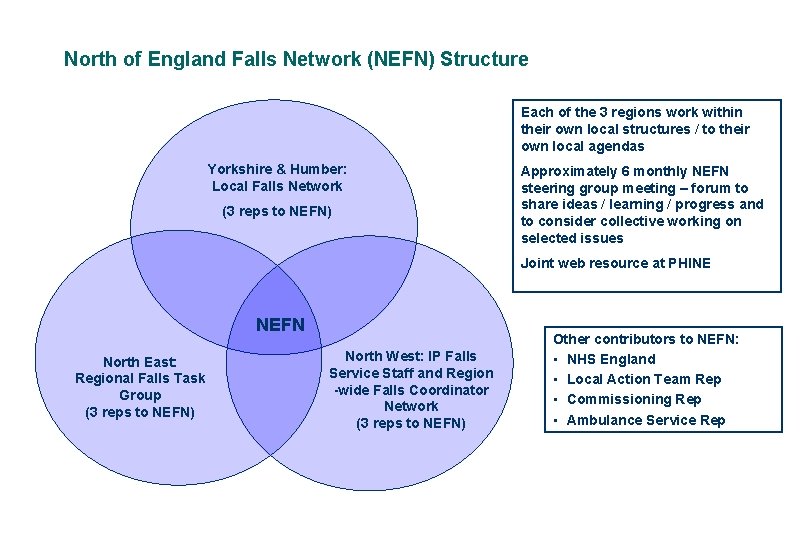
North of England Falls Network (NEFN) Structure Each of the 3 regions work within their own local structures / to their own local agendas Yorkshire & Humber: Local Falls Network (3 reps to NEFN) Approximately 6 monthly NEFN steering group meeting – forum to share ideas / learning / progress and to consider collective working on selected issues Joint web resource at PHINE NEFN North East: Regional Falls Task Group (3 reps to NEFN) North West: IP Falls Service Staff and Region -wide Falls Coordinator Network (3 reps to NEFN) Other contributors to NEFN: • NHS England • Local Action Team Rep • Commissioning Rep • Ambulance Service Rep
Who contributes? l l l l Community Falls Services Hospital Falls Services Specialist Syncope Services Fracture Liaison Teams Ambulance Services Social Services – community care teams Public Health General Practitioners Pharmacy Services Exercise providers via links with Falls Teams Third Sector Organisations Commissioners NHS North of England (Local Area Teams) / NHS England
How did we develop? l Safer Care NE supported by Northern Regional SHA: 2009 - 2011 l Sustained enthusiasm to maintain group after SHA disbanded. Realigned with NHS North of England l North East Regional Falls Task Group l 2012 explored potential to link with North West and Yorkshire and Humber l 2013 North of England Falls Network – existing structures and new individuals North West; entirely new structure in Yorkshire and Humber modeled on North East and with links to Improvement Academy (AHSN)
Evidence Base behind practice
Populations considered l Public Health Promotion – l Public Health Case ascertainment – – – l l N Tyneside Falls Prevention model Ambulance Services Community Care alarm referrals Primary Falls Prevention – Exercise Groups l l Secondary Falls Prevention – Emergency Department – Community Falls Services – Fracture Liaison falls assessment & referral – Care Homes Fracture Prevention Mental Health (inpatients)
Links North East Regional Falls and Fracture Prevention Strategy Safer Care North East: Falls Task Group and Regional Implementation Group 2012 – 2015
Benchmarking l Consensus agreement document: Recommendations for Good Practice: Organisational Issues, Services Delivered, Inpatient / Hospital Falls, Care Homes, Training, Information, Quality Metrics l Audit 2010 against this standard completed across all of North East (Hospital and Community) l Identified areas of good practice and gaps to focus improvements – potential for shared learning / expertise l Disseminated to all CEOs of contributing organisations
Outcomes of Benchmarking Exercise l Individual issues addressed – – l Funding for Osteoporosis Specialist Nurse Development of Falls Training Recurrent themes identified across region – – Lack of robust pathways of referral from emergency departments to falls services Assessment and treatment of osteoporosis
Standard Setting l Recommendations for Good Practice document – agreement to re-audit – l CQUIN development – – l Re-Audit 2014 – improvements in all domains / standards maintained Regionally Suggested 2011/2012 and 2012/2013 Implemented South of Tyne and Wear PCT with other areas working voluntarily towards standards Regional Falls Strategy 2012 - 2015
Regionally suggested Falls (and fractures) CQUIN 2011/2012 and 2012/2013 l Capture of falls information in the Emergency Department l Evidence of timely referral to falls service for patients who present to ED with: – – – l A fall A blackout A fracture relating to a fall Evidence of timely and appropriate assessment by falls service including: – – Initial falls assessment Screening for osteoporosis
North East Regional Falls and Fracture Prevention Strategy 2012 – 2015 Safer Care North East: Falls Task Group and Regional Implementation Group Set of prioritised falls and bone health objectives, mapped to Department of Health priorities l Regionally agreed plan for use in service development North East Regional Falls and Fracture Prevention discussions with commissioners and trusts Strategy 2012 – 2015 l Auditable performance targets l Local good practice examples l Circulated to CEO’s l Safer Care North East: Falls Task Group and Regional Implementation Group
Strengths of group l l l l l Patient centred Passion for patient care Passion for ageing population – equity and access Clinicians delivering services to patients Determination Communication and leadership Cohesiveness and co-operation Honesty – no politics Positive change attitudes Flexibility in adopting ideas – responsive to feedback
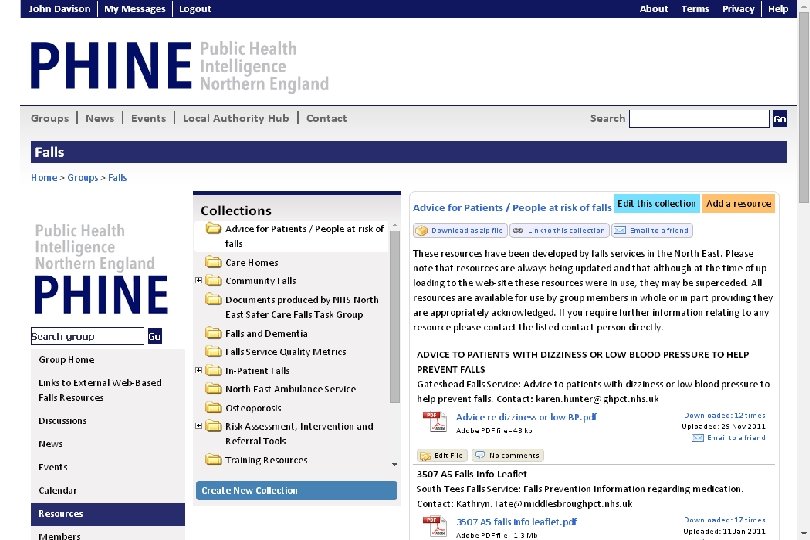
Resources l l l l Each other Regular meetings Best practice dissemination E-mail communication http: //www. phine. org. uk/safer-care-north-east/Falls NHS North of England / NHS England Emerging links with Patient Safety Collaboratives / AHSNs
Dissemination l #t 1 noefs – – Summation of evidence base Patient Safety priorities Current research Best practice examples l l – l Health care based Community based collaborative work – e. g. Arriva Inpatient falls initiatives and impact Sharing Best Practice – – Improvement Academy AHSN / Patient Safety Collaborative links Public Health NHS England
Challenges l l l l Fragmentation of services Variability Reliance on individuals to champion successful initiatives Variable commissioning knowledge and interest Data Issues of scale – falls ‘nihilism’ Measuring outcomes
The Future l l l l Sustaining services Creating consistency – managing the gaps Addressing falls risk factors – earlier identification and intervention Developing further CQUINs Involving patients in developing services Improving links with Public Health and General Practice Links with AHSNs / PSCs Links with other Falls Networks nationally via NHS England
Acknowledgements l To all members of the group who have enthusiastically supported the development and cohesiveness from 2009 onwards regardless of the oversight framework