
NEONATAL SPINAL SONOGRAPHY CASE BASED REVIEW OF NORMAL
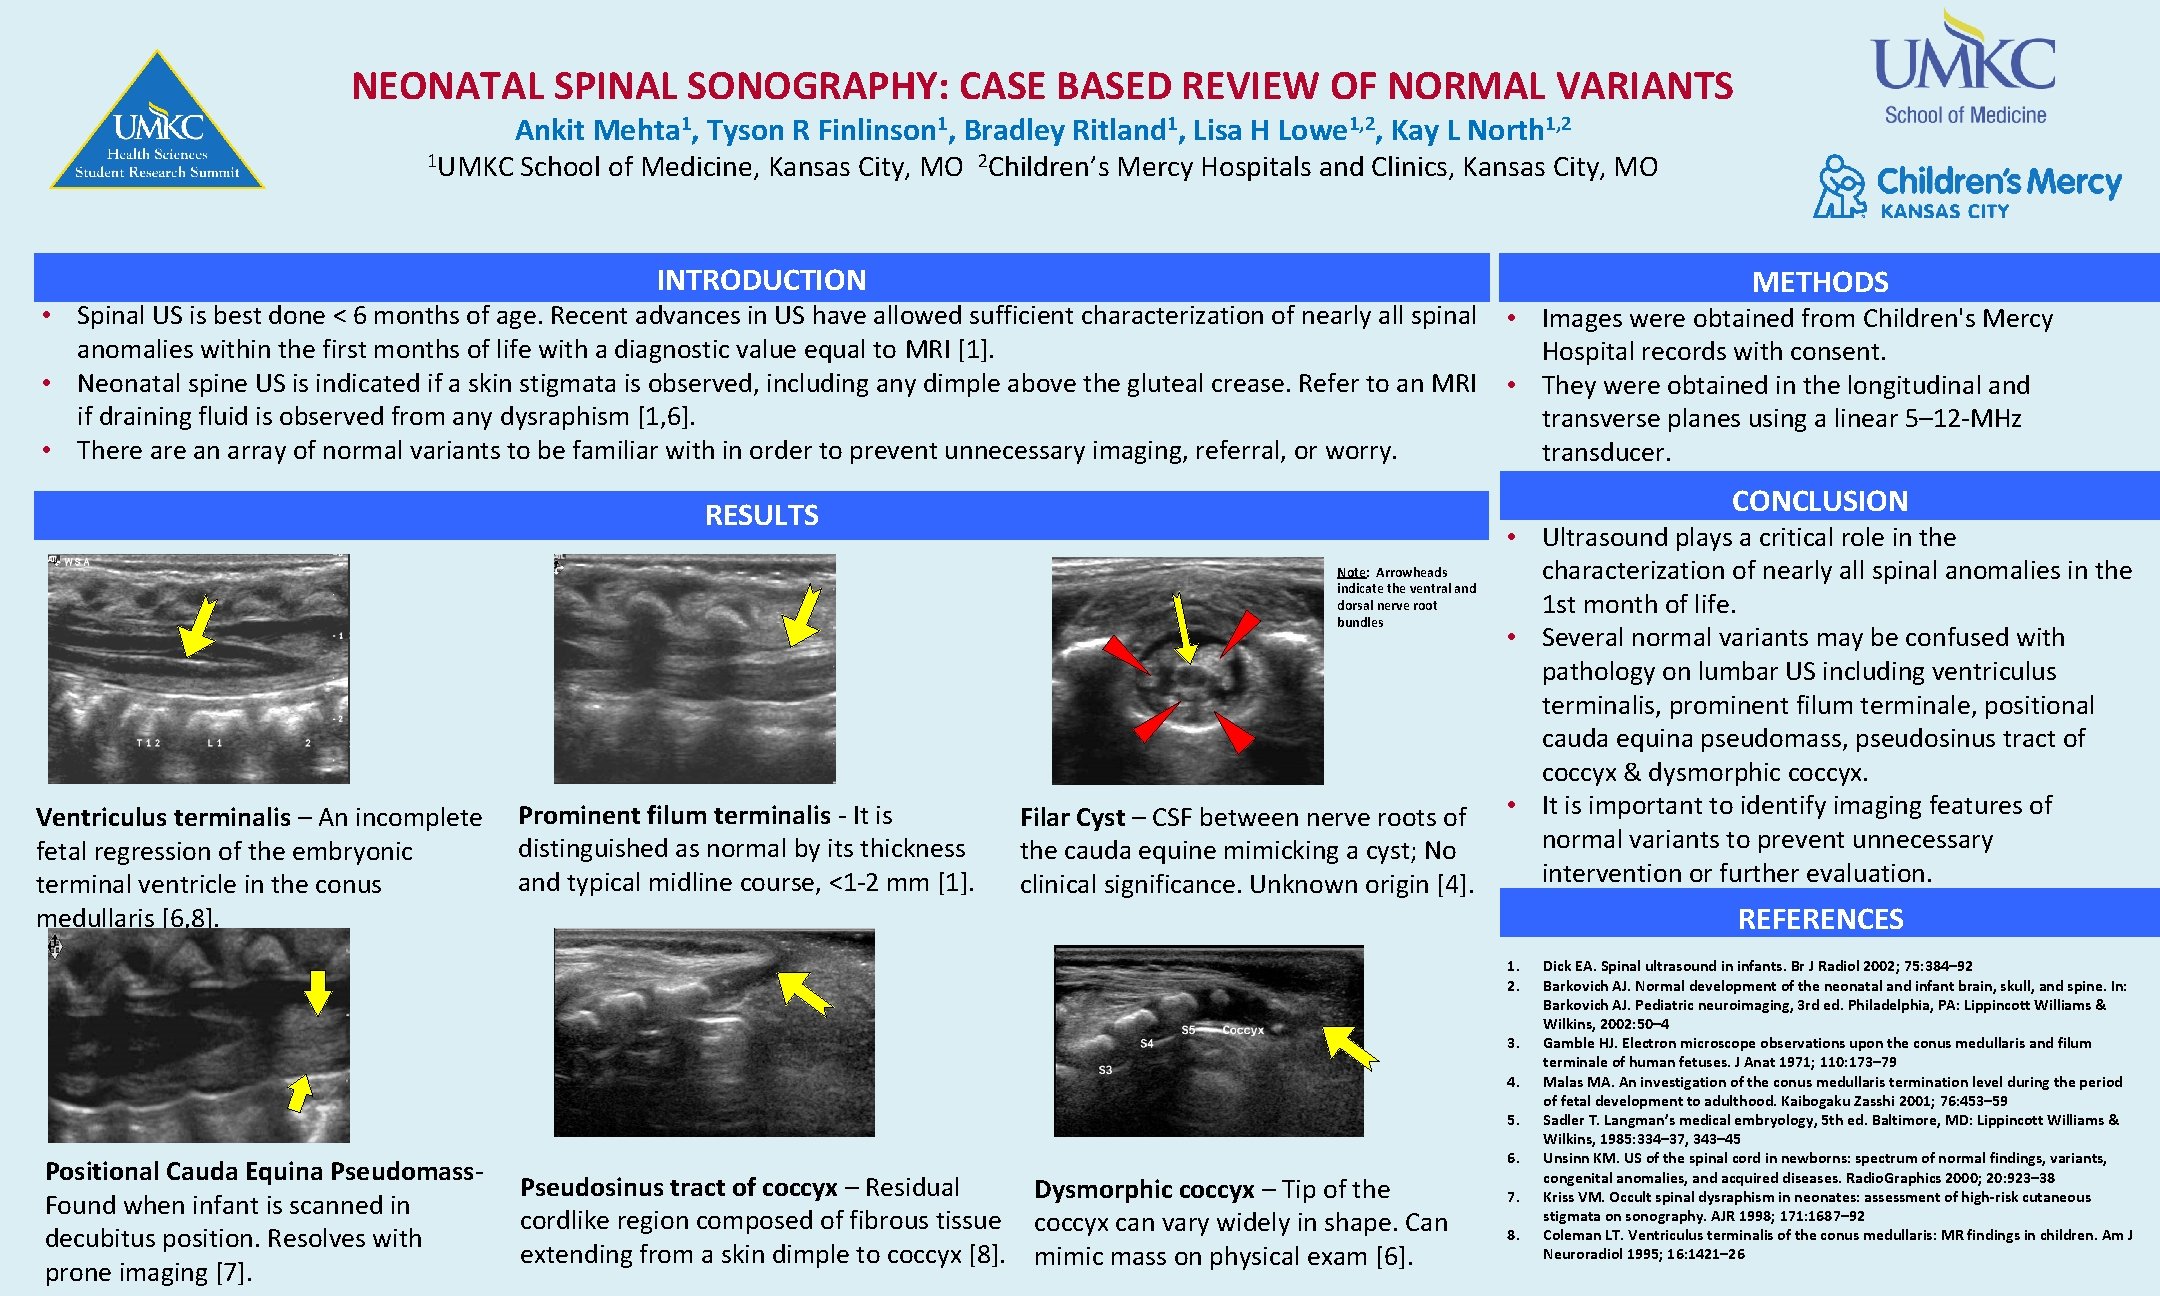
NEONATAL SPINAL SONOGRAPHY: CASE BASED REVIEW OF NORMAL VARIANTS 1 UMKC Ankit Mehta 1, Tyson R Finlinson 1, Bradley Ritland 1, Lisa H Lowe 1, 2, Kay L North 1, 2 School of Medicine, Kansas City, MO 2 Children’s Mercy Hospitals and Clinics, Kansas City, MO INTRODUCTION METHODS RESULTS CONCLUSION • Spinal US is best done < 6 months of age. Recent advances in US have allowed sufficient characterization of nearly all spinal • Images were obtained from Children's Mercy anomalies within the first months of life with a diagnostic value equal to MRI [1]. Hospital records with consent. • Neonatal spine US is indicated if a skin stigmata is observed, including any dimple above the gluteal crease. Refer to an MRI • They were obtained in the longitudinal and if draining fluid is observed from any dysraphism [1, 6]. transverse planes using a linear 5– 12 -MHz • There an array of normal variants to be familiar with in order to prevent unnecessary imaging, referral, or worry. transducer. Note: Arrowheads indicate the ventral and dorsal nerve root bundles Ventriculus terminalis – An incomplete fetal regression of the embryonic terminal ventricle in the conus medullaris [6, 8]. Prominent filum terminalis - It is distinguished as normal by its thickness and typical midline course, <1 -2 mm [1]. Filar Cyst – CSF between nerve roots of the cauda equine mimicking a cyst; No clinical significance. Unknown origin [4]. • Ultrasound plays a critical role in the characterization of nearly all spinal anomalies in the 1 st month of life. • Several normal variants may be confused with pathology on lumbar US including ventriculus terminalis, prominent filum terminale, positional cauda equina pseudomass, pseudosinus tract of coccyx & dysmorphic coccyx. • It is important to identify imaging features of normal variants to prevent unnecessary intervention or further evaluation. REFERENCES 1. 2. 3. 4. 5. Positional Cauda Equina Pseudomass. Found when infant is scanned in decubitus position. Resolves with prone imaging [7]. 6. Pseudosinus tract of coccyx – Residual Dysmorphic coccyx – Tip of the cordlike region composed of fibrous tissue coccyx can vary widely in shape. Can extending from a skin dimple to coccyx [8]. mimic mass on physical exam [6]. 7. 8. Dick EA. Spinal ultrasound in infants. Br J Radiol 2002; 75: 384– 92 Barkovich AJ. Normal development of the neonatal and infant brain, skull, and spine. In: Barkovich AJ. Pediatric neuroimaging, 3 rd ed. Philadelphia, PA: Lippincott Williams & Wilkins, 2002: 50– 4 Gamble HJ. Electron microscope observations upon the conus medullaris and filum terminale of human fetuses. J Anat 1971; 110: 173– 79 Malas MA. An investigation of the conus medullaris termination level during the period of fetal development to adulthood. Kaibogaku Zasshi 2001; 76: 453– 59 Sadler T. Langman’s medical embryology, 5 th ed. Baltimore, MD: Lippincott Williams & Wilkins, 1985: 334– 37, 343– 45 Unsinn KM. US of the spinal cord in newborns: spectrum of normal findings, variants, congenital anomalies, and acquired diseases. Radio. Graphics 2000; 20: 923– 38 Kriss VM. Occult spinal dysraphism in neonates: assessment of high-risk cutaneous stigmata on sonography. AJR 1998; 171: 1687– 92 Coleman LT. Ventriculus terminalis of the conus medullaris: MR findings in children. Am J Neuroradiol 1995; 16: 1421– 26
- Slides: 1