
Menstrual history Menarche 12 Menstruation Regular Interval 28

































- Slides: 40
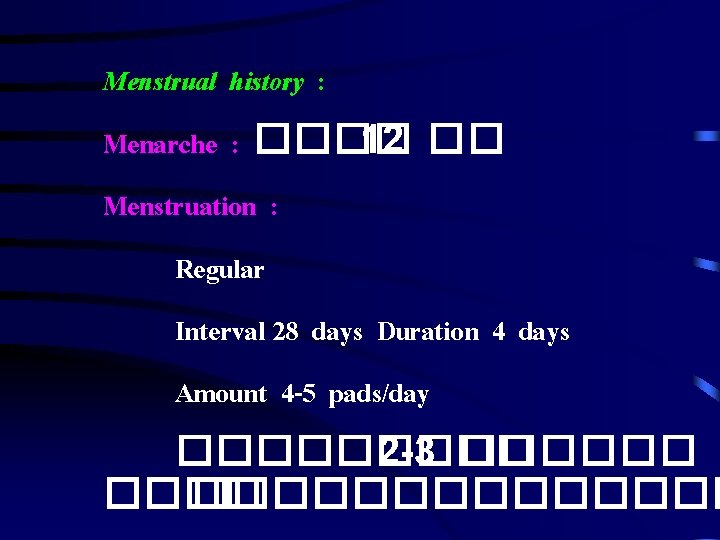
Menstrual history : Menarche : ���� 12 �� Menstruation : Regular Interval 28 days Duration 4 days Amount 4 -5 pads/day ����� 2 -3 �������
PE : A young Thai female, looked acutely ill, normal growth and body build , good consciousness and co-operative Vital signs : BT 38. 8 oc BP 110/70 mm. Hg PR 108/min RR 24/min Height 153 cm Body weight 45 Kg
HEENT : not pale , no icteric sclera Lymph node : no lymphadenopathy Breasts : no mass , no abnormal discharge Heart : normal S 1 S 2 , no murmur Lungs : clear , no adventitious sounds
Abdomen : no hepatosplenomegaly , tender at right side of lower abdomen , mild guarding , rebound tenderness , no palpable mass Extremities : no edema Neurological examination : WNL
Pelvic examination : MIUB : normal Vagina : foul smell, yellow discharge Cervix : clean, os closed , cervical motion tenderness at right side Uterus : N/S , A/V , tender Adnexa : tender at right side, no mass
Problems list • Acute lower abdominal pain with fever • Abnormal vaginal discharge • Peritonitis: Right lower abdominal tenderness , guarding , rebound tenderness Cervical motion tenderness at Rt side , Adnexal tenderness at Rt side
• ������� UTI • ����� Illegal abortion • Multiple sexual partners • Drinking
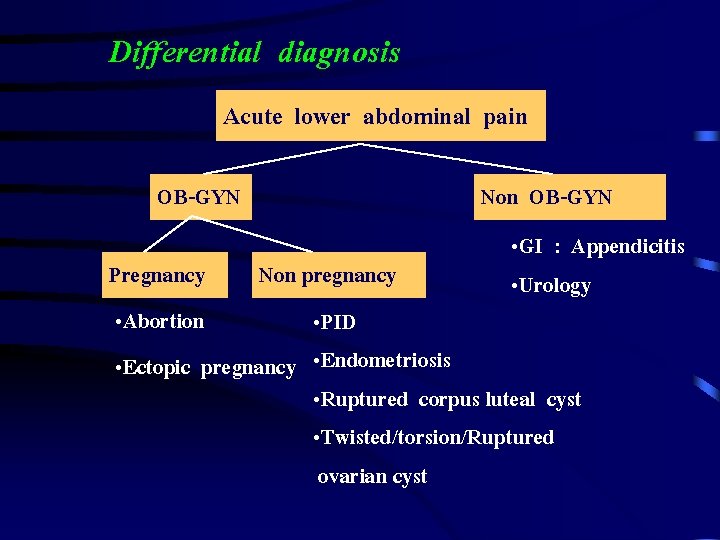
Differential diagnosis Acute lower abdominal pain OB-GYN Non OB-GYN • GI : Appendicitis • Urology Pregnancy Non pregnancy • Abortion • PID • Ectopic pregnancy • Endometriosis • Ruptured corpus luteal cyst • Twisted/torsion/Ruptured ovarian cyst
Investigation CBC , UA Blood chemistry ( BUN , Cr , LFT , Electrolytes( Serology : VDRL , HBs. Ag , Anti-HIV Septic workup : Hemoculture , cervical swab for gram stain and culture Ultrasound
Investigation Hematology : RBC 4. 35 x 106 /ul Hgb 12. 0 g/dl Hct 37. 0% MCV 85 fl MCH 27. 6 pg MCHC 32. 4 g/dl Platelets counts 335, 000 /ul WBC 22, 700 /ml Neu 96. 0 % Lym 12. 2 % Mono 1. 7% Eos 0. 1 %
Urinalysis Slightly turbid , sp. gr. 1. 015 , p. H 8. 0 Erythrocyte 4+ , Leukocyte Protein - trace , Glucose , Nitrite , Urobilinogen , Bilirubin , ketone - - neg. WBC / hpf 18 -20 RBC / hpf 70 -80 Sq. epithelium / hpf 8 -10 Bacteria / hpf 1+
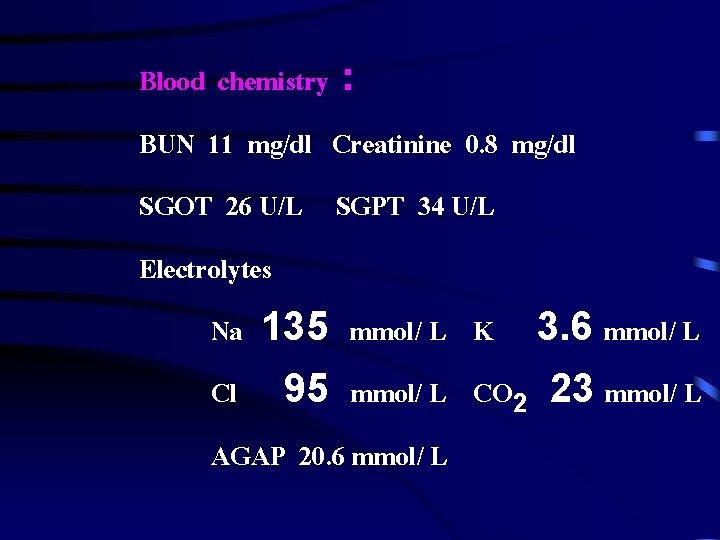
Blood chemistry : BUN 11 mg/dl Creatinine 0. 8 mg/dl SGOT 26 U/L SGPT 34 U/L Electrolytes Na 135 mmol/ L K Cl 3. 6 mmol/ L 95 mmol/ L CO 2 23 mmol/ L AGAP 20. 6 mmol/ L
Serology - all negative CReactive protein 96. 3 mg/l ( normal < 5 mg/l ) Hemoculture - no growth Urine culture - no growth Ultrasound - no abnormal findings
Diagnosis Acute PID
Diagnosis Minimal Criteria • Lower abdominal tenderness • Adnexal tenderness • Cervical motion tenderness
Additional criteria that support a diagnosis of PID include the following • Oral temperature >101 F (>38. 3 o. C( • Abnormal cervical or vaginal discharge • Elevated erythrocyte sedimentation rate • Elevated C-reactive protein • Laboratory documentation of cervical infection with N. gonorrhea or C. trachomatis
The definitive criteria for diagnosing PID, which are warranted in selected cases, include the following • Histopathologic evidence of endometritis on endometrial biopsy • Transvaginal sonography or other imaging techniques showing thickened fluid filled tubes with or without free pelvic fluid or tubo-ovarian complex • Laparoscopic abnormalities consistent with PID
Management • Hospitalization Criteria of admission • Uncertain of diagnosis • with pregnancy • adolescent • immunodeficiency • tuboovarian abscess • severe symptoms • can’t follow up • treatment of OPD case : no response
• Antibiotics treatment
��������������� Antibiotics �� ������ Triple therapy Ampicillin, Gentamicin, Metronidazole vs Gentamicin plus Clindamycin ������ line of • �������� management ������ lab investigation : CBC , BUN , Electrolyte , Hemoculture , Anti-HIV , HBs. Ag , VDRL
• �������� Regimen B Clindamycin 600 gm IV q 8 hr. mg ) Gentamicin 5 mg/kg ( ������� 240 ����� 5% D/W 100 cc IV drip �� 1 hr. ������� 48 hrs.
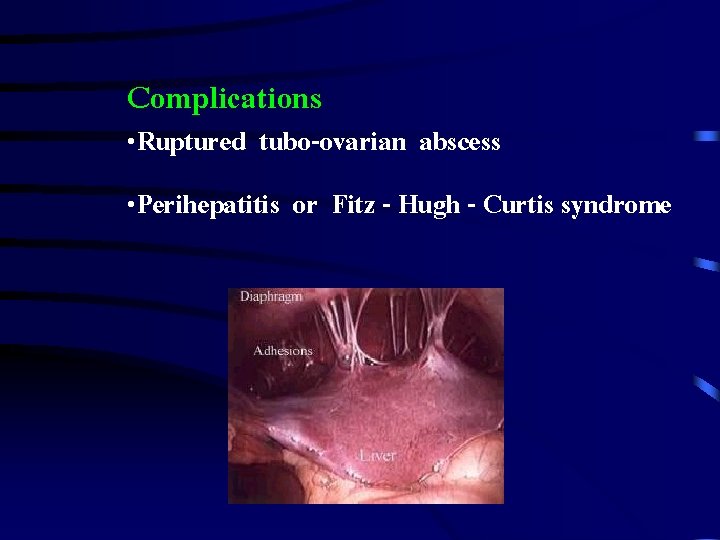
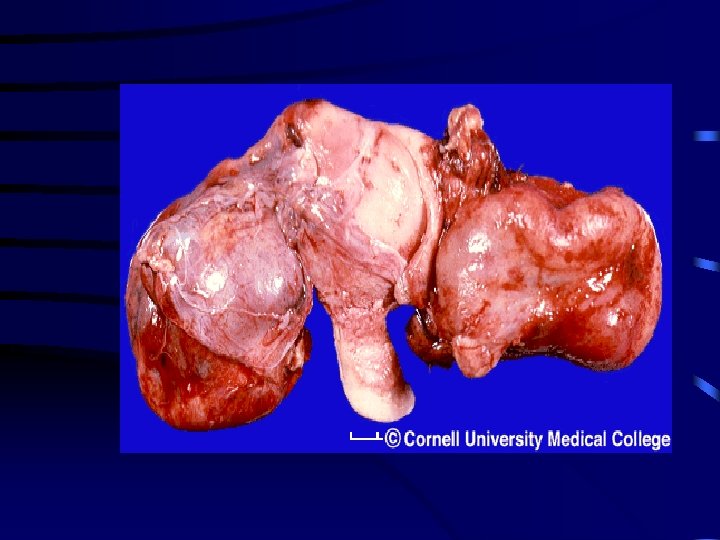
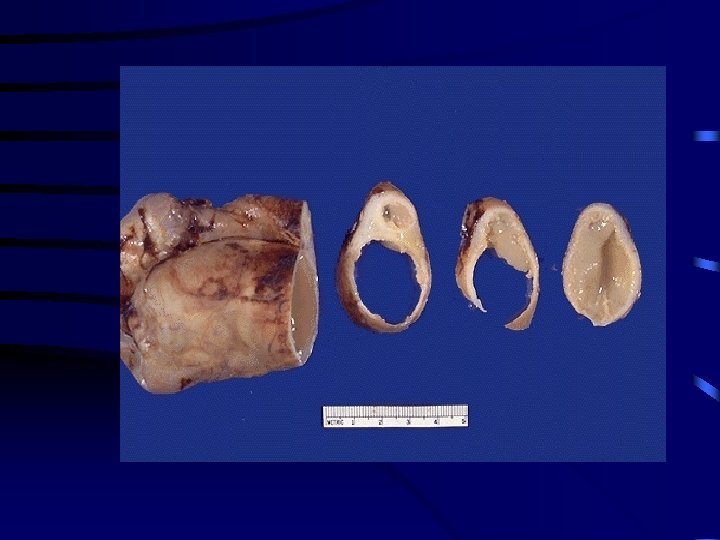
Complications • Ruptured tubo-ovarian abscess • Perihepatitis or Fitz - Hugh - Curtis syndrome
Complications • Increase risk of further episodes of PID • Increase incidence of ectopic pregnancy • Chronic pelvic pain • Infertility
Center of Disease Control regimen A : Cefotetan 2 g IV q 12 hrs. plus doxycycline 100 mg IV q 12 hrs until relieve signs &symptoms after 24 - 48 hrs. And then give doxycycline 100 mg orally 2 times for 14 days regimen B : Clindamycin 900 mg IV q 8 hrs. plus gentamicin loading dose ( 2 mg/kg of body weight ) IV or IM followed by a maintenance dose (1. 5 mg/kg ) every 8 hrs. until relieve signs & symptoms after 24 - 48 hrs. And then give doxycycline 100 mg orally 2 times or clindamycin 450 mg orally 4 times for 14 days