
Meeting Meaningful Use Stage2 A focus from the





































- Slides: 49
Meeting Meaningful Use Stage-2 A focus from the Laboratory Presented by: Michael Huppenthal mhuppen@jhmi. edu 1
Disclosure P. Michael Huppenthal • Presenter has no financial relationship with any commercial interest or conflicts of interest to this presentation. 2/25/2021 2
Presentation Objectives • Understand the basics of Meaningful Use and its implication to the Laboratory. • Understand the Meaningful Use Stages. • Understand Core, Menu, and Quality Measures. • Understand how one institution developed a committee with key stake-holder representation to meet MU-2 requirements. • Review details of implementing Stage 2 Core Measure #14 Send Reportable Lab Results to Public Health Agencies. • Review the Labs role in Stage 2 Core Measures 8 and 12. – Incorporate Clinical Lab Test Results as structured data – Summary of Care 2/25/2021 3
The Lingo: (Abbreviations) • • • • EP – Eligible Professional EH – Eligible Hospital CAH – Critical Access Hospital EHR – Electronic Health Record ELR – Electronic Lab Reporting LOINC – Logical Observation Identifiers Names and Codes SNOMED – Systematized Nomenclature of Medicine Clinical Terms RLR – Reportable Lab Results HHS – Health & Human Services ONC – Office of National Coordinator for Health Information Technology CMS – Center for Medicare & Medicaid Services CEHRT – Certified Electronic Health Record Technology HITSC – Health Information Technology Standards Committee ARRA – American Recovery and Reinvestment Act CCHIT - Certification Commission for Health Information Technology 4
What is Meaningful Use • A Federal government incentive program that rewards providers (EP) and organizations (EH) (CAH) that invest in Electronic Health Records (EHR) technology used by medical providers. – www. cdc. gov/EHRmeaningfuluse 5
Who defines the Program Health and Human Services Agencies • The Center for Medicaid and Medicare Services (CMS) – defines who is eligible – what you must do to participate • The Office of the National Coordinator of Health Information Technology (ONC) – Define what the certified health technology must accomplish. 2/25/2021 6
Complexity beyond “belief” • The regulations are detailed in thousands of pages of government documentation. • The final compliance with each objective and measure resides in your interpretation of the standard and your institutions final approach to meet the standard /objective / measure. 7
Show me the “Money” Stage 2 • To obtain incentive payments, you must demonstrate that the individual or organization is “meaningfully using the EHR”. • This is accomplished by interpreting the guidelines, developing a plan, and implementing an established set of core objectives, menu objectives, and quality measures, attesting and reporting as required. 8
$160 Billion • The American Recovery and Reinvestment Act (ARRA) allocated “Approximately $160 billion to fund programs to improve and preserve health care, health information technology, children and community services, scientific research and facilities, and community health and prevention initiatives. ” http: //www. hhs. gov/recovery/ • A significant portion of these funds are targeted to reward EH’s and EP’s who attest to be “meaningful users” of certified electronic health records with increases in Medicare and Medicaid payments. 9
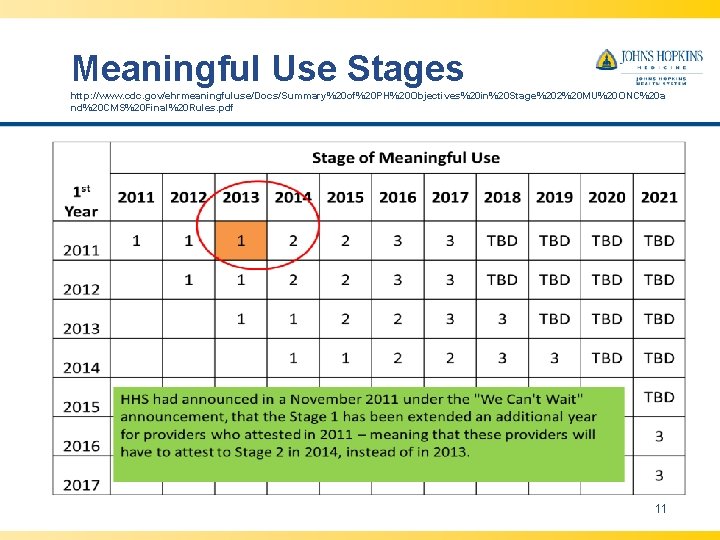
Phases of M. U. Attestation • The attesting entity (EP/EH) progress through M. U. stages of increasing difficulty. • JHH attested Stage 1 – Jan 2012 • JHH will attest Stage 2 – July 2014 10
Meaningful Use Stages http: //www. cdc. gov/ehrmeaningfuluse/Docs/Summary%20 of%20 PH%20 Objectives%20 in%20 Stage%202%20 MU%20 ONC%20 a nd%20 CMS%20 Final%20 Rules. pdf • Insert Chart 11
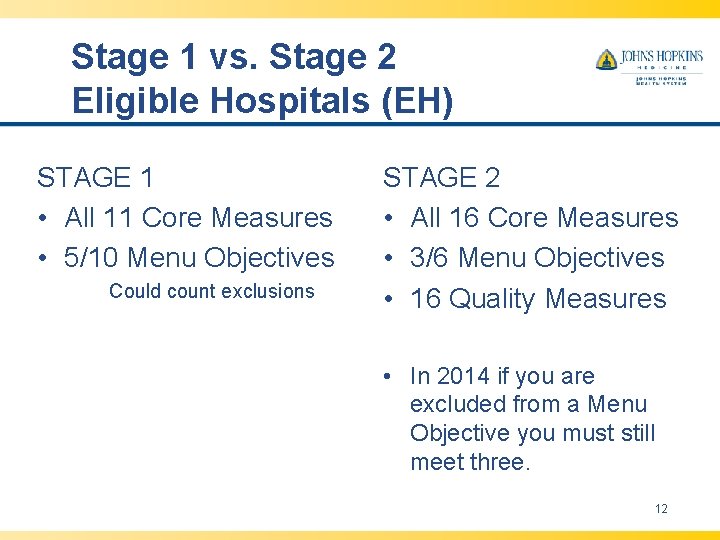
Stage 1 vs. Stage 2 Eligible Hospitals (EH) STAGE 1 • All 11 Core Measures • 5/10 Menu Objectives Could count exclusions STAGE 2 • All 16 Core Measures • 3/6 Menu Objectives • 16 Quality Measures • In 2014 if you are excluded from a Menu Objective you must still meet three. 12
Stage 2 Eligible Hospital Core Objective • • (1) Use computerized provider order entry (CPOE) for medication, laboratory, and radiology orders directly entered by any licensed healthcare professional who can enter orders into the medical record per state, local, and professional guidelines. (2) Record all of the following demographics: preferred language, sex, race, ethnicity, date of birth, date and preliminary cause of death in the event of mortality in the eligible hospital or CAH. (3) Record and chart changes in the following vital signs: height/length and weight (no age limit); blood pressure (ages 3 and over); calculate and display body mass index (BMI); and plot and display growth charts for patients 0 -20 years, including BMI. (4) Record smoking status for patients 13 years old or older. (5) Use clinical decision support to improve performance on high-priority health conditions. (6) Provide patients the ability to view online, download, and transmit information about a hospital admission. (7) Protect electronic health information created or maintained by the Certified EHR Technology through the implementation of appropriate technical capabilities. • (8) Incorporate clinical lab test results into Certified EHR Technology as structured data. • • (9) Generate lists of patients by specific conditions to use for quality improvement, reduction of disparities, research, or outreach. (10) Use clinically relevant information from Certified EHR Technology to identify patient-specific education resources and provide those resources to the patient. (11) The eligible hospital or CAH who receives a patient from another setting of care or provider of care or believes an encounter is relevant should perform medication reconciliation. • • (12) The eligible hospital or CAH who transitions their patient to another setting of care or provider of care or refers their patient to another provider of care provides a summary care record for each transition of care or referral. • (13) Capability to submit electronic data to immunization registries or immunization information systems except where prohibited, and in accordance with applicable law and practice. • (14) Capability to submit electronic reportable laboratory results to public health agencies, where except where prohibited, and in accordance with applicable law and practice. • (15) Capability to submit electronic syndromic surveillance data to public health agencies, except where prohibited, and in accordance with applicable law and practice. (16) Automatically track medications from order to administration using assistive technologies in conjunction with an electronic medication administration record (e. MAR). • • https: //www. cms. gov/Regulations-and- Guidance/Legislation/EHRIncentive. Programs/Downloads/Stage 2_Meaningful. Use. Spec. Sheet_Table. Contents_Eligible. Hospitals_CAHs. pdf 13
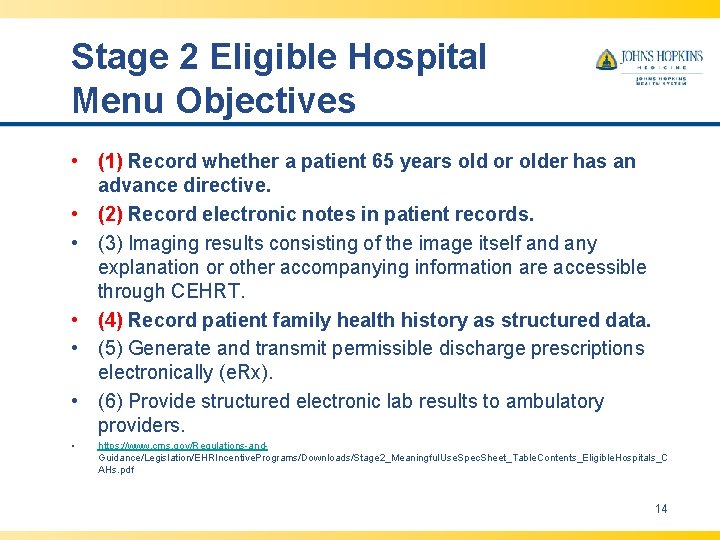
Stage 2 Eligible Hospital Menu Objectives • (1) Record whether a patient 65 years old or older has an advance directive. • (2) Record electronic notes in patient records. • (3) Imaging results consisting of the image itself and any explanation or other accompanying information are accessible through CEHRT. • (4) Record patient family health history as structured data. • (5) Generate and transmit permissible discharge prescriptions electronically (e. Rx). • (6) Provide structured electronic lab results to ambulatory providers. • https: //www. cms. gov/Regulations-and- Guidance/Legislation/EHRIncentive. Programs/Downloads/Stage 2_Meaningful. Use. Spec. Sheet_Table. Contents_Eligible. Hospitals_C AHs. pdf 14
29 Quality Measures • You must report to CMS a total of 16 quality measures in three different areas. – Patient and Family Engagement – Patient Safety – Care Coordination – Efficient Use of Healthcare Resources – Clinical Processes and Effectiveness. • There is no prescribed list. • Select measures that align with your Stage 1 measures or are existing internal quality initiatives. You may find measures for other programs that align with this requirement (TJC). 2/25/2021 15
How Johns Hopkins is Meeting Meaningful Use – Stage 2 (Lab) 2/25/2021 16
Johns Hopkins Institutions Meaningful Use 2 Plan • Health System is comprised of five Hospitals. • Variety of LIS and HIS platforms at each site. • Each Hospital has developed their own plan to implement Meaningful Use at different phases (quarters) and levels of attestation. • Attestation for EH and EP varies by site and EHR (Epic / Sunrise / Meditech / Mc. Kesson). 17
Steering Committee • The JHH site has 2 LIS’s and 3 EHR’s. • EH versus EP plan. • Multiple disciplinary teams work on meeting Core Objectives and Measures. • The Steering Committees meet every two weeks to report progress. • A dashboard on progress and barriers is shared with enterprise leadership. 18
EH Attestation to CMS • Details of each objective/measure are maintained by each working group. – Core Objectives (16) – Menu Objectives (3) – Clinical Quality Measures (16) • One centrally maintained “MU-2 Book of Evidence” will be submitted for attestation to CMS by each site for each plan. • The JHH C. F. O. will attest for the hospital. 19
The Silo of Lab • Focused on 2 objectives – EH S 2 Core 14: Send Reportable Lab Results to Public Health Agencies – EH S 2 Core 8: Incorporate Clinical Lab Test Results 20
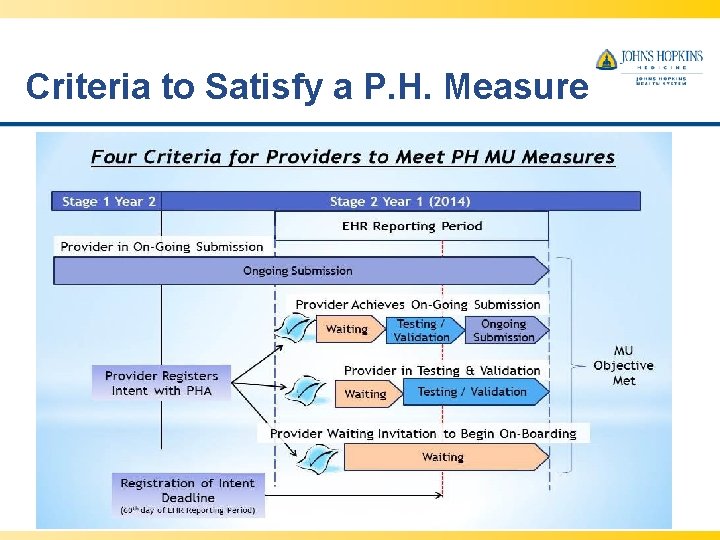
Is your LIS certified for Meaningful Use Stage 2 • For Stage 1 reporting of results to a Public Health Agency, the LIS did not have to be certified. • For Stage 2 reporting in 2014, the reporting must come from a “certified” system. • Certification Commission for Health Information Technology (CCHIT). – SCC Soft Lab 4. 0. 7 certified ONC 2014 (1/10/14) – SCC Soft Lab 4. 5. 4 certification (PENDING) 21
Criteria to Satisfy a P. H. Measure 2/25/2021 22
Reporting in Maryland (PH) DHMH • CRISP (MD Health Information Exchange) – One Feed with Flag on ELR reportable – Two Feeds, HIE and ELR • Soft LIS (primary reportable and the reflexed ELR reportable). • Elected to send separate ELR feed. 23
What needs to be sent • Obtain list of diseases and conditions to report to your DHMH (October 2008). • Do not assume their previous paper process will work with an electronic feed. (Immunosuppression) • Test Specific requirements (Social Security / N. O. K. ) 24
Negotiate the ELR Interface • Stage 2 requires a HL 7 – 2. 5. 1 or higher interface. • What are the required and optional fields? • What will the accepting system do when a required field is blank (home phone / SS #). • Does an outbound ELR 2. 5. 1 require an ADT feed that is HL 7 2. 5. 1 or higher ? • Upgrade vs. “Custom Fields” ! • Document your interface exceptions. • DO NOT forget to Register with your PH agency. 25
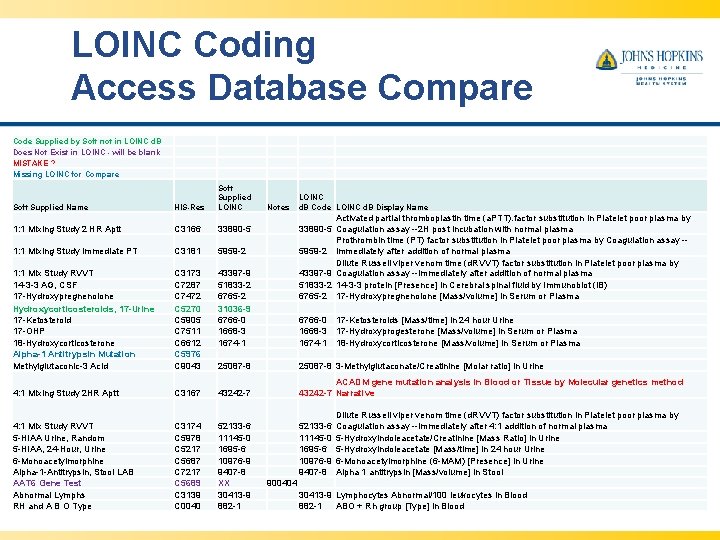
Start your LOINC Coding EARLY !!! • Process will take many months. • Second review of the initial coding. • Ask your Reference labs for a LOINC export of their entire database. • Multi-sites may be different codes. • Use the code associated with your method and reporting units. • Check and re-Check your selections. 2/25/2021 26
LOINC Coding Access Database Compare Code Supplied by Soft not in LOINC d. B Does Not Exist in LOINC - will be blank MISTAKE ? Missing LOINC for Compare Soft Supplied Name HIS-Res Soft Supplied LOINC 1: 1 Mixing Study 2 HR Aptt C 3166 33890 -5 1: 1 Mixing Study Immediate PT C 3181 5959 -2 1: 1 Mix Study RVVT 14 -3 -3 AG, CSF 17 -Hydroxypregnenolone Hydroxycorticosteroids, 17 -Urine 17 -Ketosteroid 17 -OHP 18 -Hydroxycorticosterone Alpha-1 Antitrypsin Mutation Methylglutaconic-3 Acid C 3173 C 7287 C 7472 C 5270 C 5905 C 7511 C 6612 C 5976 C 9043 43397 -9 51833 -2 6765 -2 31036 -9 6766 -0 1668 -3 1674 -1 25087 -8 Activated partial thromboplastin time (a. PTT). factor substitution in Platelet poor plasma by 33890 -5 Coagulation assay --2 H post incubation with normal plasma Prothrombin time (PT) factor substitution in Platelet poor plasma by Coagulation assay -5959 -2 immediately after addition of normal plasma Dilute Russell viper venom time (d. RVVT) factor substitution in Platelet poor plasma by 43397 -9 Coagulation assay --immediately after addition of normal plasma 51833 -2 14 -3 -3 protein [Presence] in Cerebral spinal fluid by Immunoblot (IB) 6765 -2 17 -Hydroxypregnenolone [Mass/volume] in Serum or Plasma 6766 -0 17 -Ketosteroids [Mass/time] in 24 hour Urine 1668 -3 17 -Hydroxyprogesterone [Mass/volume] in Serum or Plasma 1674 -1 18 -Hydroxycorticosterone [Mass/volume] in Serum or Plasma 25087 -8 3 -Methylglutaconate/Creatinine [Molar ratio] in Urine 4: 1 Mixing Study 2 HR Aptt C 3167 43242 -7 ACADM gene mutation analysis in Blood or Tissue by Molecular genetics method 43242 -7 Narrative 4: 1 Mix Study RVVT 5 -HIAA Urine, Random 5 -HIAA, 24 -Hour, Urine 6 -Monoacetylmorphine Alpha-1 -Antitrypsin, Stool LAB AAT 6 Gene Test Abnormal Lymphs RH and A B O Type C 3174 C 5978 C 5217 C 5687 C 7217 C 5689 C 3139 C 0040 52133 -6 11145 -0 1695 -6 10976 -9 9407 -8 XX 30413 -9 882 -1 52133 -6 11145 -0 1695 -6 10976 -9 9407 -8 900404 30413 -9 882 -1 Notes LOINC d. B Code LOINC d. B Display Name Dilute Russell viper venom time (d. RVVT) factor substitution in Platelet poor plasma by Coagulation assay --immediately after 4: 1 addition of normal plasma 5 -Hydroxyindoleacetate/Creatinine [Mass Ratio] in Urine 5 -Hydroxyindoleacetate [Mass/time] in 24 hour Urine 6 -Monoacetylmorphine (6 -MAM) [Presence] in Urine Alpha 1 antitrypsin [Mass/volume] in Stool Lymphocytes Abnormal/100 leukocytes in Blood ABO + Rh group [Type] in Blood
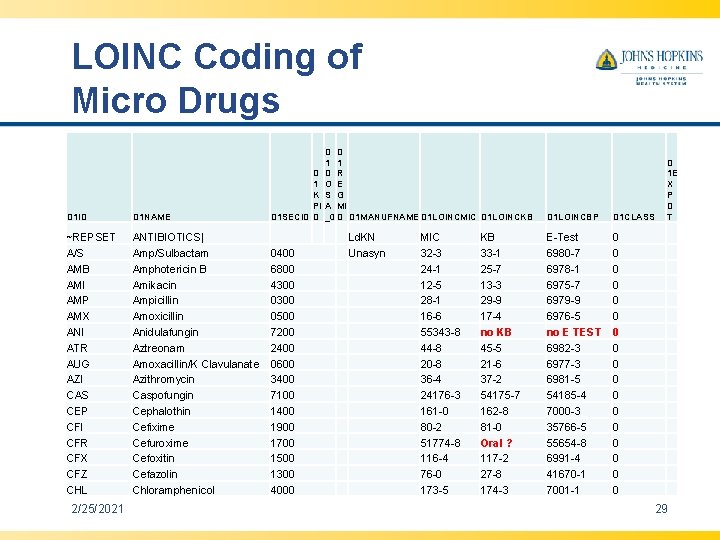
Not just the Test Database • For Soft. Mic, you must also LOINC code the Drugs. – MIC – KB (agar diffusion) – E-test (gradient strip) • Micro experts will need to assist. • Do not assume every drug can be coded. 2/25/2021 28
LOINC Coding of Micro Drugs D 1 ID D 1 NAME ~REPSET A/S AMB AMI AMP AMX ANI ATR AUG AZI CAS CEP CFI CFR CFX CFZ CHL ANTIBIOTICS| Amp/Sulbactam Amphotericin B Amikacin Ampicillin Amoxicillin Anidulafungin Aztreonam Amoxacillin/K Clavulanate Azithromycin Caspofungin Cephalothin Cefixime Cefuroxime Cefoxitin Cefazolin Chloramphenicol 2/25/2021 D 1 K PI D 1 SECID D 0400 6800 4300 0500 7200 2400 0600 3400 7100 1400 1900 1700 1500 1300 4000 D D 1 1 D R O E S G A MI _0 D D 1 MANUFNAME D 1 LOINCMIC D 1 LOINCKB Ld. KN Unasyn MIC 32 -3 24 -1 12 -5 28 -1 16 -6 55343 -8 44 -8 20 -8 36 -4 24176 -3 161 -0 80 -2 51774 -8 116 -4 76 -0 173 -5 KB 33 -1 25 -7 13 -3 29 -9 17 -4 no KB 45 -5 21 -6 37 -2 54175 -7 162 -8 81 -0 Oral ? 117 -2 27 -8 174 -3 D 1 LOINCBP D 1 CLASS E-Test 6980 -7 6978 -1 6975 -7 6979 -9 6976 -5 no E TEST 6982 -3 6977 -3 6981 -5 54185 -4 7000 -3 35766 -5 55654 -8 6991 -4 41670 -1 7001 -1 0 0 0 0 0 D 1 E X P D T 29
Micro Sources SNOMED • • • Where do you store the code? When do you report? Is this needed for Stage 2? Map in the HIS dictionary? SNOMED vs Concept ID Codes: Which did you load in the Organism file? 2/25/2021 30
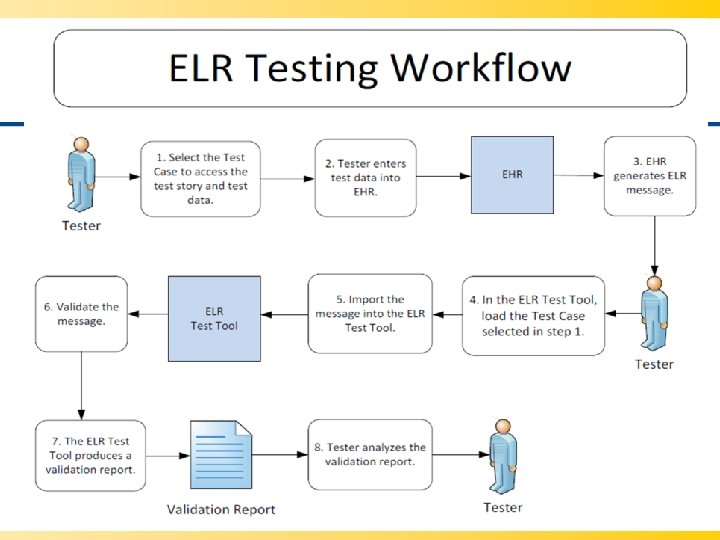
Test Procedure for Reportable Lab Results (170. 314. (f)(4) • Use the test procedures developed to evaluate conformance to the standard. – Record: Ability to enter LOINC encoded data into EHR. – Retrieve: Validate that the test results are accurate and complete. – Submit: Capability to electronically submit LOINC encoded results in a conformant HL 7 v 2. 5. 1 format. 2/25/2021 31
2/25/2021 32
170. 314(f)(4) Nine Test Scenarios • • • For this test procedure the Tester shall select one Test Case (and hence its associated test data) from each of the nine test scenarios listed: 1 – Maximally Populated Final Quantitative Result 2 – Final Quantitative Result 3 – Preliminary Multiple Coded Culture Results 4 – Final Single Coded Culture Result with Susceptibility Testing 5 A – Final Quantitative Result with Reflex Testing* 5 B – Final Quantitative Result with Reflex Testing* 6 – Final Titer Result 7 – Final Qualitative Result 8 – Final Multiple Qualitative Results 9 – Final Single Coded Culture Result *The Vendor has the option of supporting either Test Scenario 5 A or 5 B (support of both is preferred, but not required). 2/25/2021 33
Validation Determination Other Testing • Unit test early (typical interface validation). • Send both simple and complex results. • Organism reporting – just the reportable or the entire culture (determine preference). • Sending Prelim Results. • Amended Results. • Cancelled Results. 34
Documentation EH Stage 2 Core 14 • There is NO measure or report for this objective. • Document agreed to exceptions in the signed off interface specification. • Have “ALL” parties sign the interface document. • Keep documentation of all testing. • Obtain final sign off of your validated ELR. • Keep a copy of you PH registration certificate. • Prepare for Go-Live! 35
Maryland DHMH The specifications are not ELR “ready” • Diseases, Conditions, Outbreaks, & Unusual Manifestations • Reportable by Maryland Laboratories The regulations governing laboratory reporting were updated effective October 1, 2008. Table 1, below, copied from the Code of Maryland Regulations (COMAR) 10. 06. 01. 03 C, details the diseases, conditions, outbreaks, and unusual manifestations that are reportable in Maryland. The table has been altered from the exact COMAR version by the addition of information about the reporting of AIDS and HIV. In addition, Table 1 indicates when “clinical materials” should be submitted to the Maryland Department of Health and Mental Hygiene’s (DHMH) laboratory, as well as the timeframe for reporting. Several footnotes to the table elaborate on specific details, as do the following sections of this document: Legal Authority, What to Report, How to Report, When to Report, Where to Report, and Submitting Clinical Materials. The regulations apply to laboratories located within Maryland any that process human specimens obtained from an individual in Maryland. 8 pages of tables 36
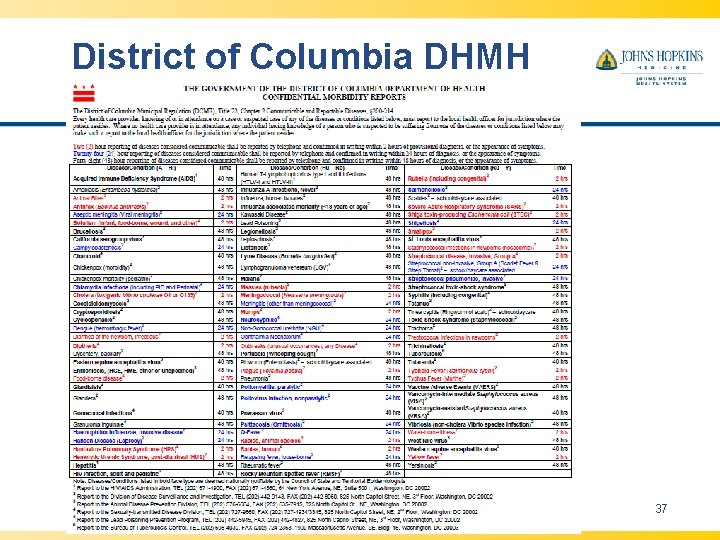
District of Columbia DHMH 2/25/2021 37
Attestation • JHH Pathology Director of Informatics will attest that we have satisfied the standards defined for stage 2 Core #14 EHR reporting to PH. – Must continue for the entire EHR reporting period. • Provide written attestation statement to our internal central I. T. M. U. -2 “book”. • The Hospital (EH) will attest 16 Core and 3 Menu objectives in July 2014. 38
MU 2 – C 8: Incorporate clinical lab results into EHR as structured data. MU 2 – C 12: Summary of Care 2/25/2021 39
The Labs Role Core Measure 8 and Core Measure 12 (EH/CAH) • For Stage 2, CMS states “We clarify that the measure incorporates all numeric/quantitative tests that report whole or decimal numbers. The structured data for the numeric/quantitative may include positive or negative affirmation and/or numerical format that would include a reference range of numeric results and/or ratios. ” 40
How does your organization interpret C 8 and C 12 • What is your interpretation of “certified technology” to transmit results to the HIS? • To meet this objective, are LOINC and SNOMED codes required in the outbound results interface? • Is this an HL 7 2. 5. 1 or higher interface? 41
JHH Decision • Agreed to Upgrade the Soft Outbound Results interface to Epic to HL 7 – 2. 5. 1 • All LOINC, SNOMED, Observation codes, and identifiers will be sent with each result. • Epic inbound results interface configured to accept all fields to fulfill the intent of using “certified technology” for Structured data and Summary of Care. • Future focus of Stage-3 ? 42
Stage 2 Measure (Core 8) • More that 55% of all clinical lab results ordered by “authorized” providers for patients admitted to its inpatient or ER department are either in a numerical format or a Neg/Pos affirmation and incorporated in “certified” EHR technology as structured data. 2/25/2021 43
Measurement • Numerator – Numeric / Pos / Neg results incorporated in a certified EHR as structured data. • Denominator – Number of tests ordered during the reporting period (individual and panel results). • There are NO Exclusions from this objective. 2/25/2021 44
Summary of Care (C 12) • CMS has specified a list of required information that must be in the summary of care paper report or electronic transmission and the measure states that documents must be used in 50% or more of transitions of care. • Part 2 states – more that 10% of such transactions must be electronically transmitted using “certified EHR technology”. – LOINC and HL 7 2. 5. 1 2/25/2021 45
Summary Words of Wisdom • Your hospital will need to rely on all of the MU-2 project teams. • All teams must succeed or your organization fails. • Refer to the final rulings frequently. • Closely follow the testing guidelines. • Use the CMS attestation test site. • Be prepared for an audit. 46
References • American Recovery and Reinvestment Act – – http: //www. hhs. gov/recovery/ http: //www. nejm. org/doi/full/10. 1056/NEJMp 0900665 • Centers for Medicare and Medicaid Services – – http: //www. cms. gov/Regulations-and-Guidance/Legislation/EHRIncentive. Programs/Stage_2. html http: //www. cdc. gov/ehrmeaningfuluse/Docs/Summary. pdf • Office of the National Coordinator Meaningful Use. – – http: //www. healthit. gov/ http: //en. wikipedia. org/wiki/Office_of_the_National_Coordinator_for_Health_Information_Technology 2/25/2021 47
Easy Short Read (17 pages) • Summary of Public Health Objectives in Stage 2 Meaningful Use ONC and CMS Final Rules • http: //www. cdc. gov/ehrmeaningfuluse/Docs/Summary. pdf 2/25/2021 48
QUESTIONS