
Medical Theraphy of Idiopathic OAT HyunJoo Kim M




















- Slides: 34
Medical Theraphy of Idiopathic OAT Hyun-Joo Kim M. D. Department of Urology Pochon CHA University
Medical Theraphy of Idiopathic OAT u Current Treatment Modalities u Considerations u Mission
OAT as a Diagnosis? Concept of OAT ≒ FEVER OAT is a Phenomenon !
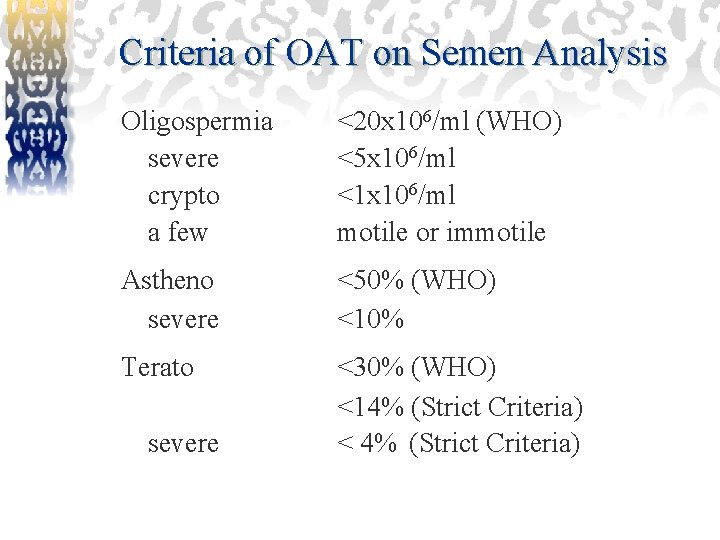
Criteria of OAT on Semen Analysis Oligospermia severe crypto a few <20 x 106/ml (WHO) <5 x 10⁶/ml <1 x 10⁶/ml motile or immotile Astheno severe <50% (WHO) <10% Terato <30% (WHO) <14% (Strict Criteria) < 4% (Strict Criteria) severe
Idiopathic v. s Specific u Specific • • • Causes Secondary Hypogonadism Varicocele Retrograde Ejaculation Infections Immunologic Infertility u Idiopathic Causes • All unknown causes
Prevalence of Male Infertility Normal/OAT 84. 3% Azoospermia 15. 7%a Obstructive 6. 3%b Non-obstructive a. 981/6242 semen analysis (95. 9 -97) b. 165/416 testis bx (95. 9 -97) c. 251/416 testis bx (95. 9 -97) from CHA 9. 4%c
Prevalence of Abnormal Semen Parameters u All parameter 43% u Motility 39% u Oligospermia 10% u Morphology 8% from Greenberg, 1987
Specific Causes v. s Idiopathic Varicocele u Obstructive u Mechanical u Endocrine u Developmental u Immunologic 39% 8% 8% u u 6% 5% 1% Idiopathic 33% from Schlegel and Pavlovich, 1997
Current Management Modality of Idiopathic OAT u Pharmacological u Sperm processing u ART
Management Idiopathic OAT: Pharmacological Treatment u Hormonal • • • Treatment Gn. RH HCG/HMG Purified or recombinant FSH Androgens Anti-Estrogens u Non-Hormonal Treatment • Kallikrein • Bromocriptine • Anti-Oxidant: Vit. C or E
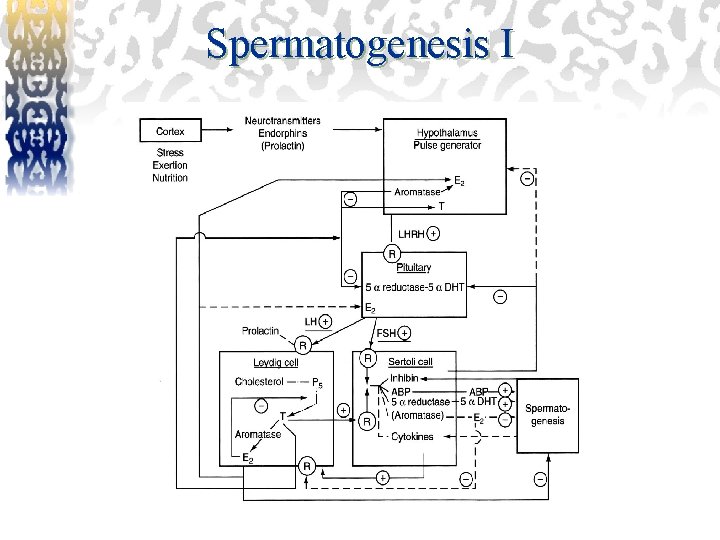
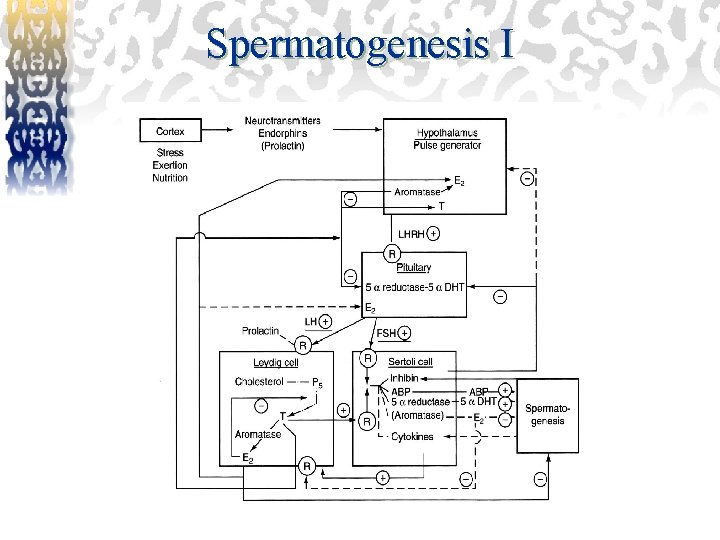
Spermatogenesis I
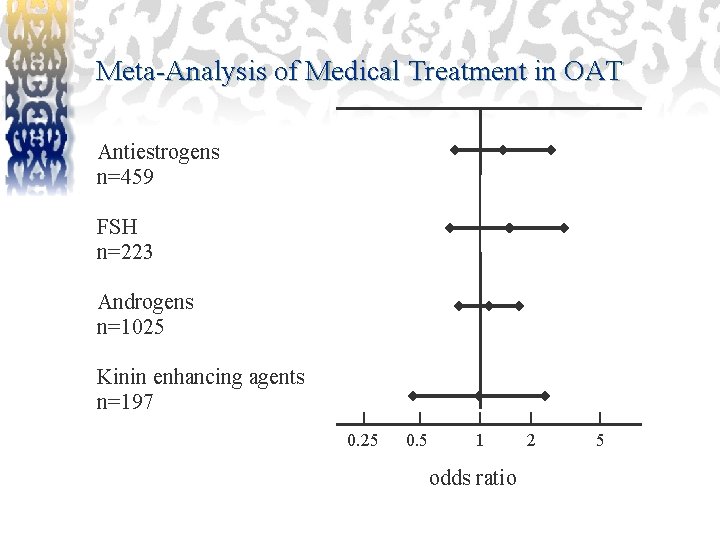
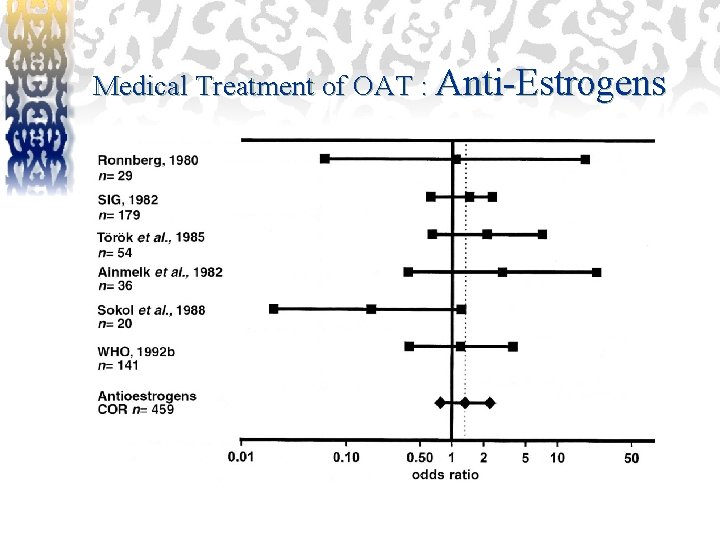
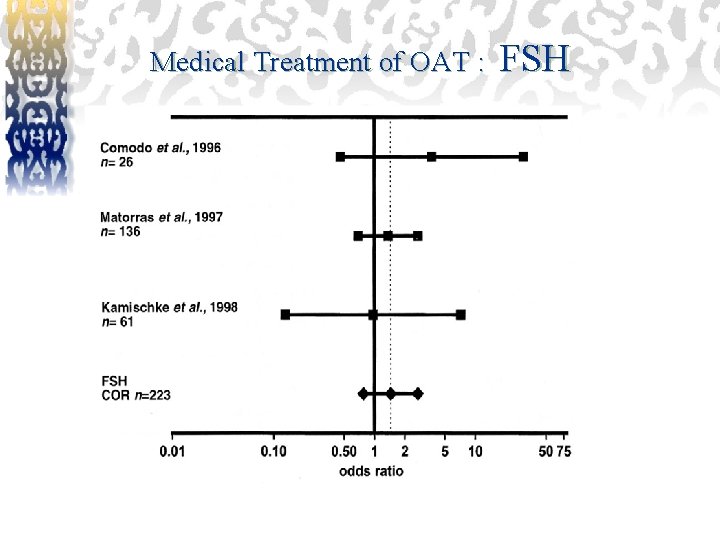
Meta-Analysis of Medical Treatment in OAT Antiestrogens n=459 FSH n=223 Androgens n=1025 Kinin enhancing agents n=197 0. 25 0. 5 1 odds ratio 2 5
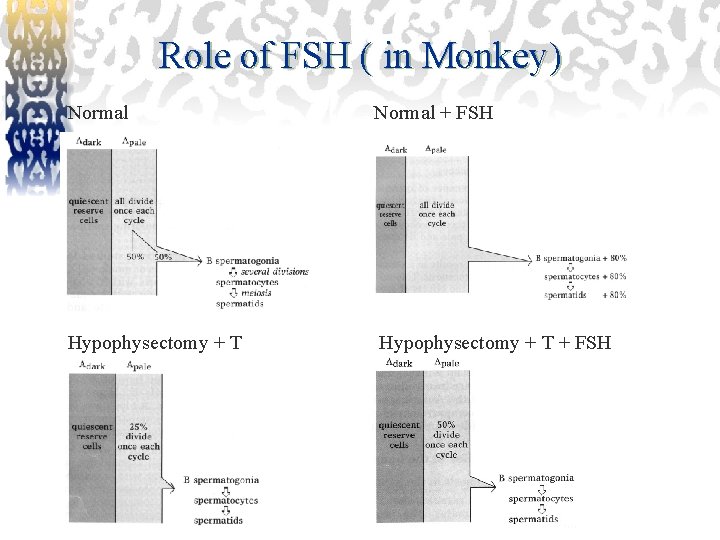
Role of FSH ( in Monkey) Normal + FSH Hypophysectomy + T + FSH
FSH on Spermatogenesis I u Quantitative Influence • Increase A-pale spermatogonia Spermatocyte, Spermatid u Qualititative Influence • Restore defective spermatozoal maturation (esp. acrosomal cap) u For adequate concentration of intratubular Testosterone • LH for T, FSH for ABP
FSH on Spermatogenesis II u Stimulate Sertoli cell to enhance FSH dependent functions u Support spermatogenesis without interfering negatively with Leydig cell physiology and without locally increasing Estrogen level u Modulate intra-testicular paracrine and autocrine mechanism
Variable Results of FSH Treatment u Dose: may not high enough u Frequency : short half-life u Duration : too short u Reduction in FSH receptor activity u Low proliferative activity of A-pale spermatogonia u Elevated endogenous level of FSH
Management Plan for Idiopathic OAT I Considerations: Female factor, Severity of OAT, Previous Treatment, P/E u Oligo: u u • T. Vol. (normal), FF(-): Empirical Tx > 3 mos. • T. Vol. <10 cc or FF(+): ART • Severe OAT: ART • A few motile/immotile: ICSI p. r. n) oocyte freezing Astheno: • >10%, FF(-): Empirical Tx > 3 mos. or IUI • <10%, FF(-): Empirical Tx > 3 mos. or ICSI p. r. n) T-Bx • 0%: Vital >20 -30% : ICSI Vital <10% : TESE-culture
Management Plan for Idiopathic OAT II u Terato: • General condition control • Empirical Tx > 3 mos. + IUI u Severe Terato: • General condition control • Empirical Tx > 3 mos. p. r. n) IUI or ICSI • FF(+): ICSI
Treatment of Male Infertility? u Relative Concept of FERTILITY u Consider u Natural Cumulative P. R Pregnancy or ART?
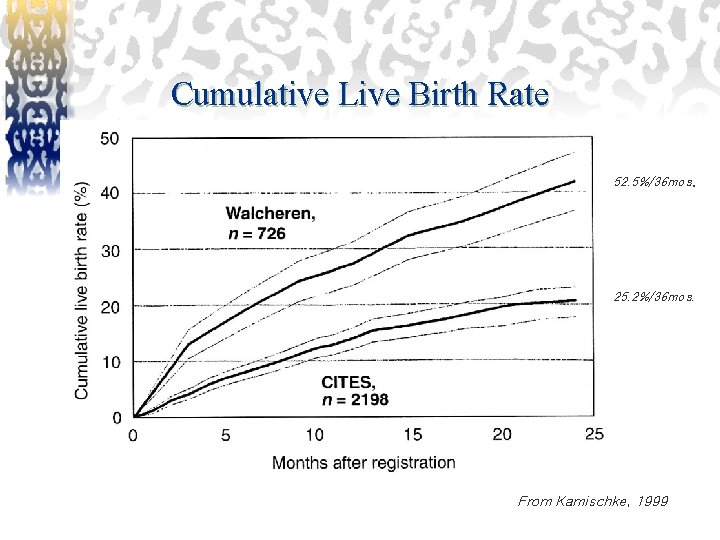
Cumulative Live Birth Rate 52. 5%/36 mos. 25. 2%/36 mos. From Kamischke, 1999
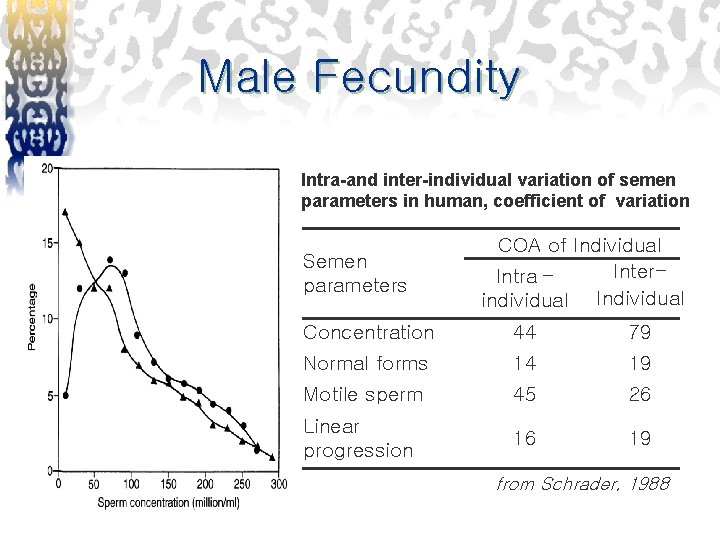
Male Fecundity Intra-and inter-individual variation of semen parameters in human, coefficient of variation Semen parameters COA of Individual Inter. Intra – individual Individual Concentration 44 79 Normal forms 14 19 Motile sperm 45 26 Linear progression 16 19 from Schrader, 1988
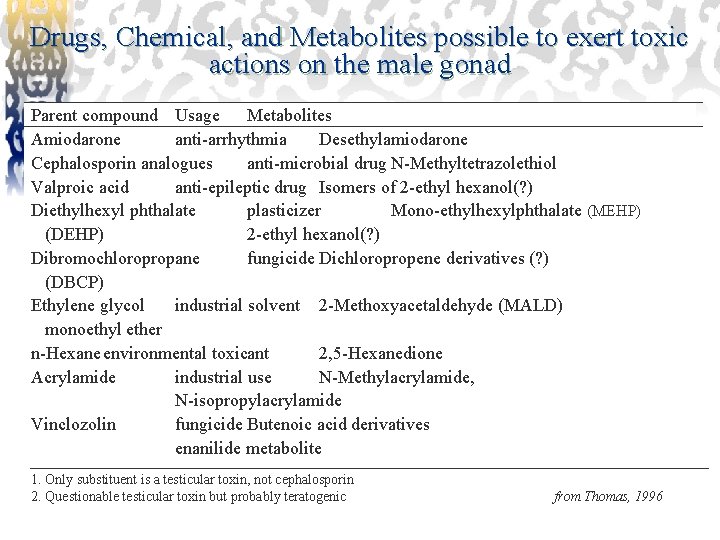
Drugs, Chemical, and Metabolites possible to exert toxic actions on the male gonad Parent compound Usage Metabolites Amiodarone anti-arrhythmia Desethylamiodarone Cephalosporin analogues anti-microbial drug N-Methyltetrazolethiol Valproic acid anti-epileptic drug Isomers of 2 -ethyl hexanol(? ) Diethylhexyl phthalate plasticizer Mono-ethylhexylphthalate (MEHP) (DEHP) 2 -ethyl hexanol(? ) Dibromochloropropane fungicide Dichloropropene derivatives (? ) (DBCP) Ethylene glycol industrial solvent 2 -Methoxyacetaldehyde (MALD) monoethyl ether n-Hexane environmental toxicant 2, 5 -Hexanedione Acrylamide industrial use N-Methylacrylamide, N-isopropylacrylamide Vinclozolin fungicide Butenoic acid derivatives enanilide metabolite 1. Only substituent is a testicular toxin, not cephalosporin 2. Questionable testicular toxin but probably teratogenic from Thomas, 1996
Environmental/Lifestyle factors to affect male fertility u u u Cigarette smoke Ingestion of female sex hormones Exposure to heavy metals(i. e. lead, arsenic) Alcohol Marijuana, anabolic steroids, cocaine Cancer chemotherapeutics Radiation exposure Increased testicular temperature Stress Lack of exercise Caffeine
Medical Treatment of OAT : Anti-Estrogens
Medical Treatment of OAT : FSH
Causes of Male Infertility u Pre-Testicular • Disorders of H-P-G axis u Testicular • Spermatogenic Defects u Post-Testicular • Epididymal Dysfunction • Obstructive change of passage • Infection of Accessary glands
Prevalence of Male Infertility u Pre-Testicular 8% u Testicular 80% (Idiopathic > 25%) u Post-Testicular 12% from Sigman, 1987
Spermatogenesis I
Testicular Causes: Spermatogenic Defects u Germ cell Defects u Somatic cell Defects u Communications Defects
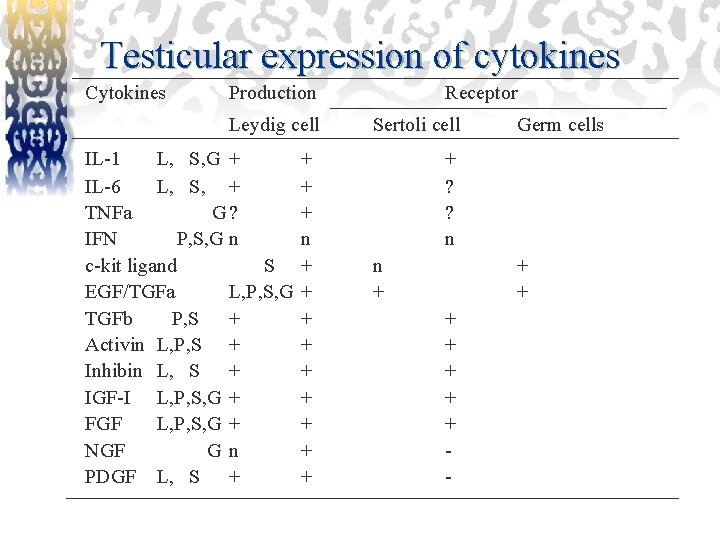
Testicular expression of cytokines Cytokines Production Leydig cell IL-1 L, S, G + IL-6 L, S, + TNFa G? IFN P, S, G n c-kit ligand S EGF/TGFa L, P, S, G TGFb P, S + Activin L, P, S + Inhibin L, S + IGF-I L, P, S, G + FGF L, P, S, G + NGF Gn PDGF L, S + + n + + + + + Receptor Sertoli cell Germ cells + ? ? n n + + + + -
Function of Testis u Dependent on Gonadotropins and Correct action of local growth factors u Major system • Endocrine System u Local factors • depend on Endocrine system • “act as an adjusted fine local relay for the endocrine system”
Spermatogenic Defects OAT from u Inadequate Gonadotropin activity u Imbalance in the intratesticular paracrine regulation u Mystery
Possible Diagnostic Tools of Spermatogenic Defects u Sperm chromosomal study u Gonadotropin assay u Germ cell and Somatic cell activity study u Receptors study
Medical Treatment of idiopathic OAT For the good results of treatment, Pt. SELECTION by Correct Diagnosis is mandatory!