
Lung Granulomas Soheir Mahfouz CHRONIC INFLAMMATION A SPECIFIC

















- Slides: 59
Lung Granulomas Soheir Mahfouz
CHRONIC INFLAMMATION A) SPECIFIC B) NON SPECIFIC Localized: Granuloma Localized----abscess Diffuse Occurs following acute inflammation
GRANULOMA Specific chronic inflammation Characterized by: n Being a localized collection of chronic inflammatory cells n Predominance of macrophages n Special microscopic picture
GRANULOMA n DEFINITION: Localized collection of chronic inflammatory cells forming granules, nodules or a tumor-like mass. Such lesions have a predominance of macrophages & have diagnostic microscopic picture i. e. specific features indicative of type of injurious agent.
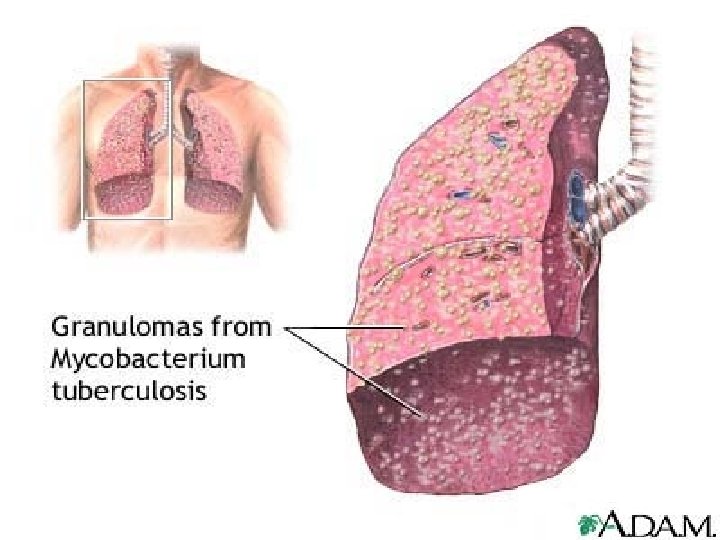
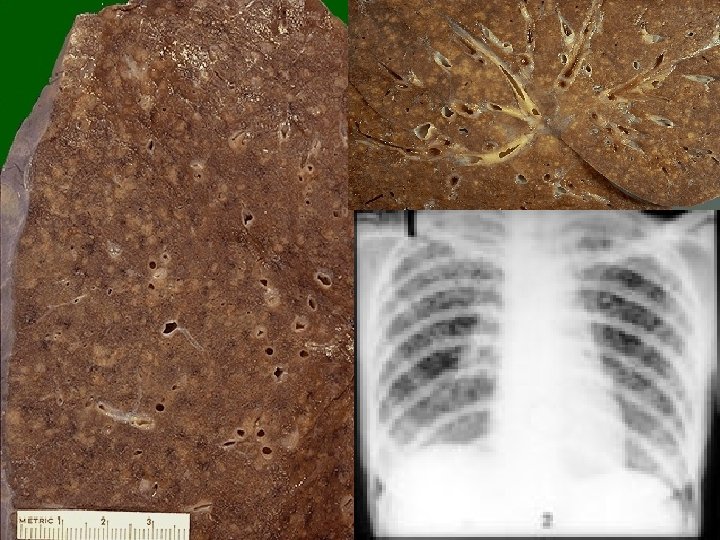
Basic reaction (BR) of GRANULOMA n GROSS: whitish firm tumor-like mass
BR: Granuloma-Microscopic n Chronic inflammatory cells & fibrosis: lymphocytes – plasma cellsfibroblasts & collagen fibers n Increased number of macrophages n Special feature specific to the granuloma
Types of Granulomas Infective Ø Bacterial 1. TB 2. Rhinoscleroma 3. Actinomycosis Ø Fungal Ø Parasitic 1. Bilharziasis Non infective Ø Foreign body Ø Idiopathic Ø Inorganic substance
Lung granulomas Bacterial: Tuberculosis, Actinomycosis n Fungal granulomas: histoplasmosis cryptococcosis, aspergillosis n Parasitic: hydatid, Entameba histolytica, microfilaria, bilharziasis n Idiopathic: sarcoidosis n
TUBERCULOSIS DEFINITION: Infective granulomatous disease caused by Mycobacterium tuberculosis ETIOLOGY: Organism: Mycobacterium tuberculosis (human or bovine). The bacteria have a lipid capsule (which stains with Ziehl Nielsen). They are gram +ve, acid fast bacilli & composed of a polysaccharideprotein body which is highly antigenic
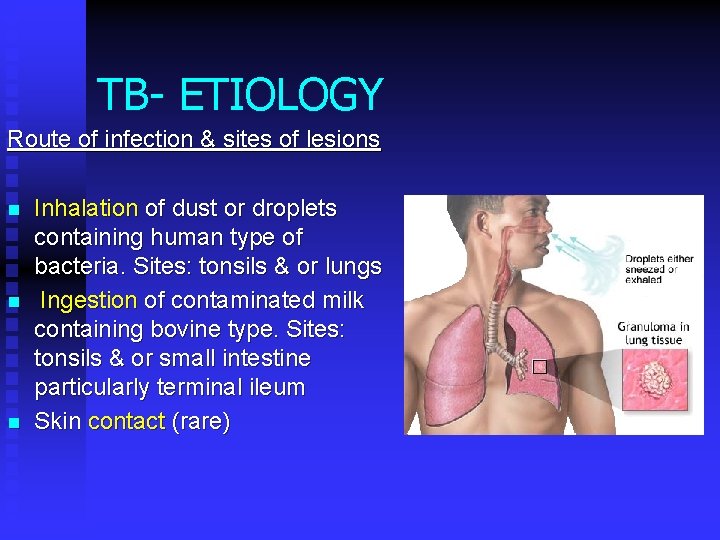
TB- ETIOLOGY Route of infection & sites of lesions n n n Inhalation of dust or droplets containing human type of bacteria. Sites: tonsils & or lungs Ingestion of contaminated milk containing bovine type. Sites: tonsils & or small intestine particularly terminal ileum Skin contact (rare)
MECHANISM OF TUBERCLE FORMATION 1. 2. Polysaccharide of bacilli attracts PNLs early but they can’t digest the lipid coat. Macrophages produce lipase that causes digestion of lipid giving a bubbly appearance to the cytoplasm & the cell transforms to an epithelioid cell. Most macrophages are unable to digest the actual organism which remains intracellularly dormant for years to be later possibly reactivated causing 2 ry TB
3 -The protein content of the organism is an antigenic stimulus & 10 -14 days after the first exposure, the lymph node produces T lymphocytes (in response to the antigenic bacterial protein) which release lymphokines & Gamma interferon. Lymphokines are responsible for: a) cytoxic effect on macrophages carrying organism b) Macrophage Chemotactic factor (MCF), attracts macrophages to the site, c) Macrophage migration inhibition factor keeps macrophages at site and prevents them from leaving area (MIF) & c) Macro-phage activating factor, which promotes bactericidal effect of macrophages at site of lesion (MAF) 4 -The lymphokines bring about cell destruction resulting in zone of caseation
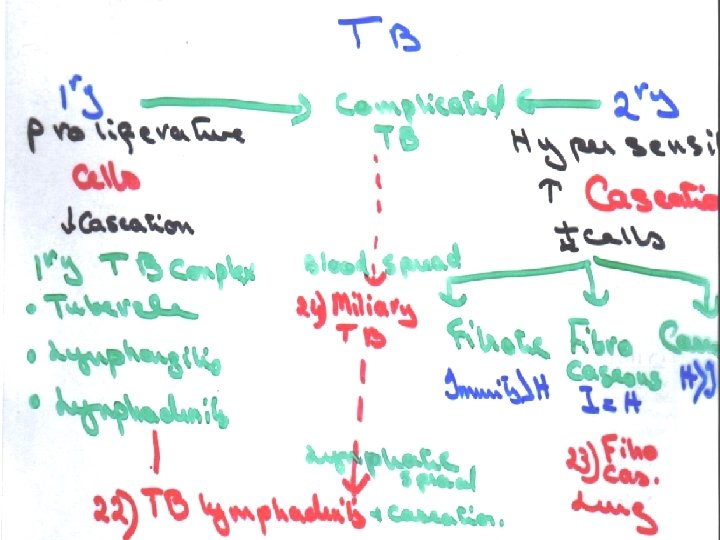
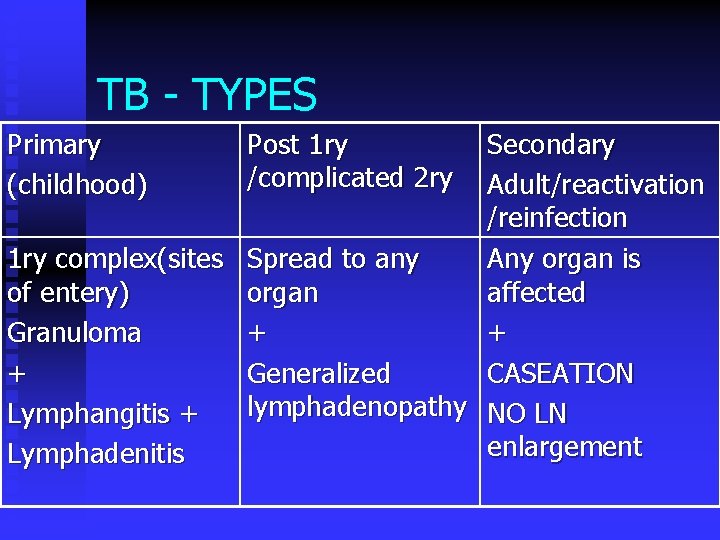
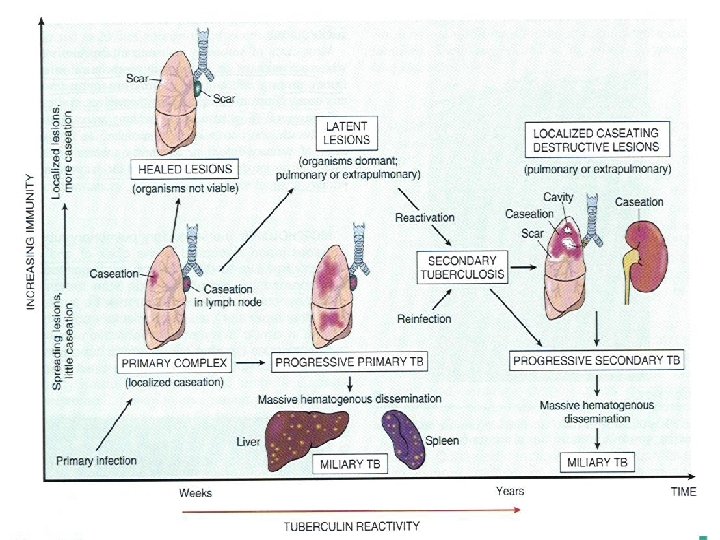
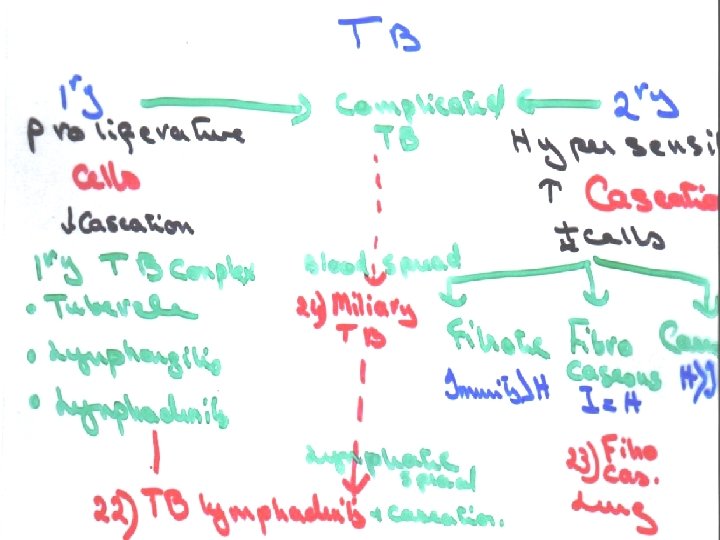
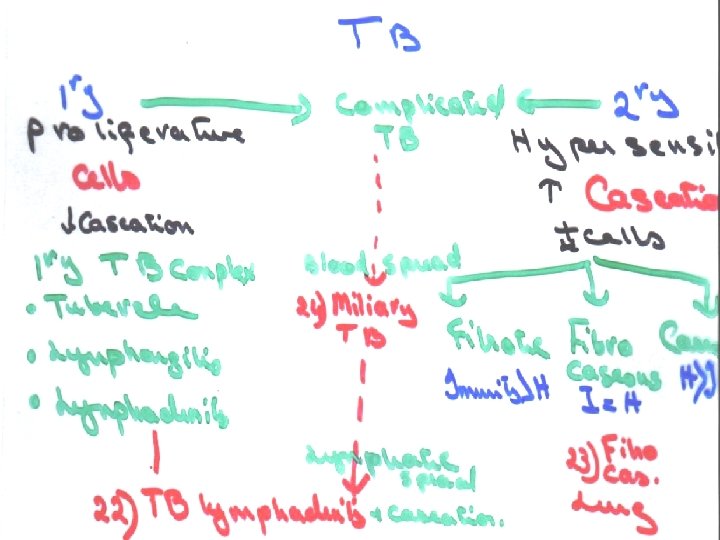
TB - TYPES Primary (childhood) Post 1 ry /complicated 2 ry Secondary Adult/reactivation /reinfection 1 ry complex(sites Spread to any Any organ is of entery) organ affected Granuloma + + + Generalized CASEATION lymphadenopathy NO LN Lymphangitis + enlargement Lymphadenitis
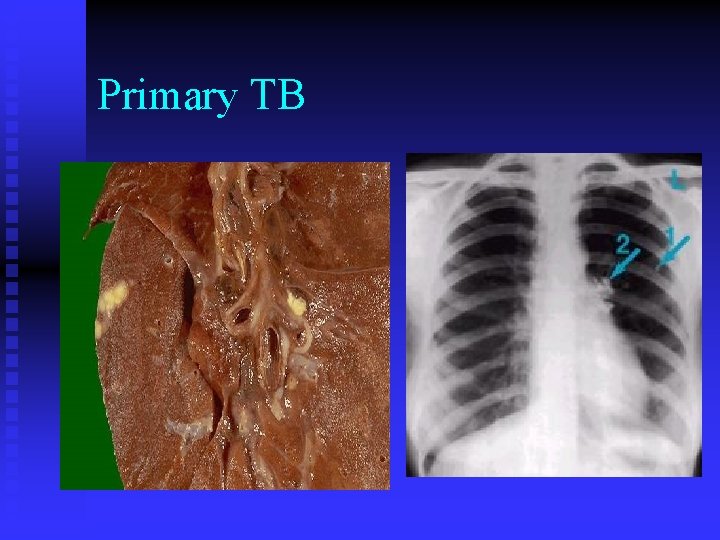
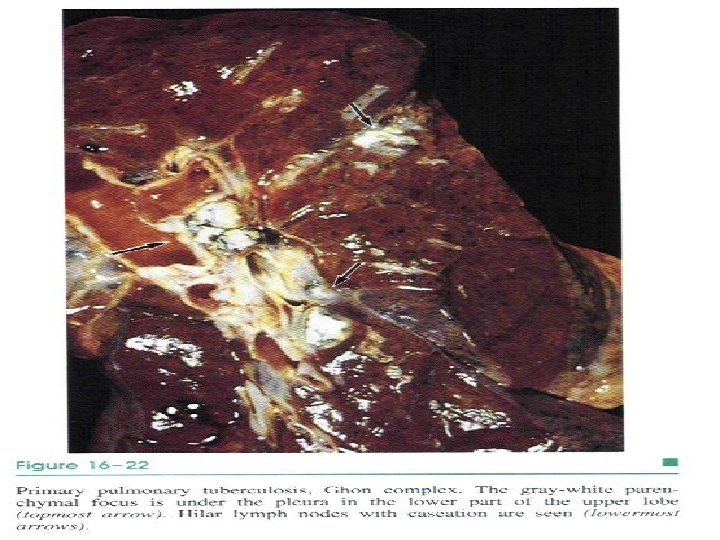
PATHOLOGY 1 ry TB GROSS Gohns focus is taken as an example. It is part of the primary pulmonary complex which is the Initial lung lesion Ghon’s focus (tubercle) + lymphangitis + lymphadenitis (hilar)
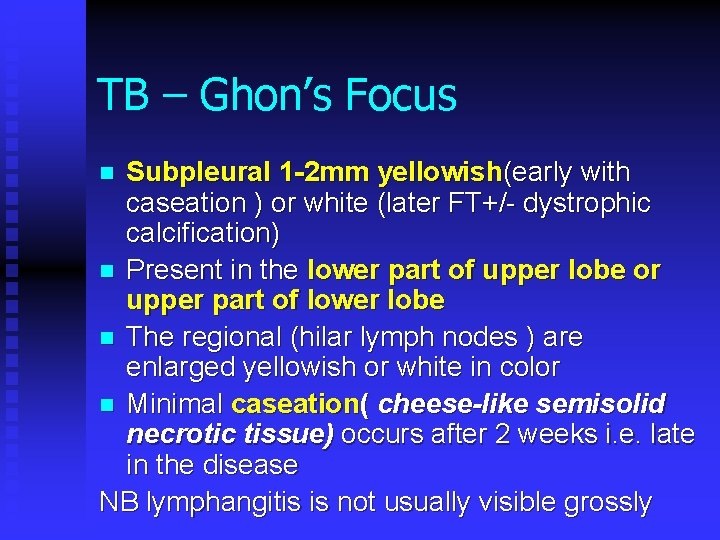
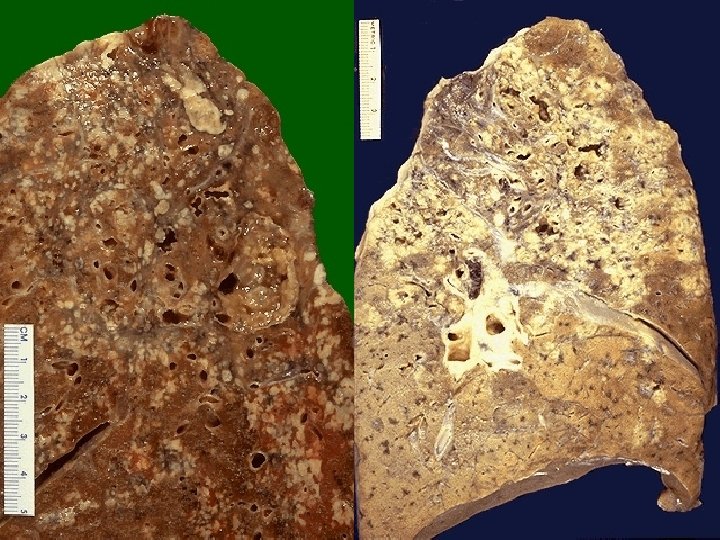
TB – Ghon’s Focus Subpleural 1 -2 mm yellowish(early with caseation ) or white (later FT+/- dystrophic calcification) n Present in the lower part of upper lobe or upper part of lower lobe n The regional (hilar lymph nodes ) are enlarged yellowish or white in color n Minimal caseation( cheese-like semisolid necrotic tissue) occurs after 2 weeks i. e. late in the disease NB lymphangitis is not usually visible grossly n
Primary TB
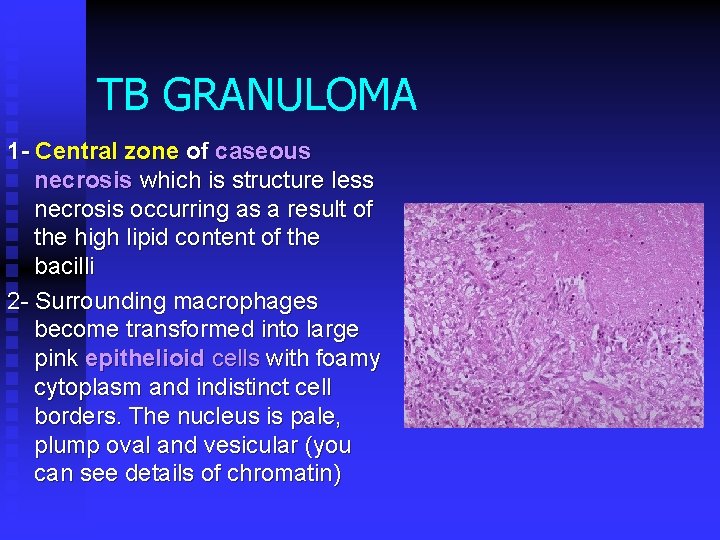
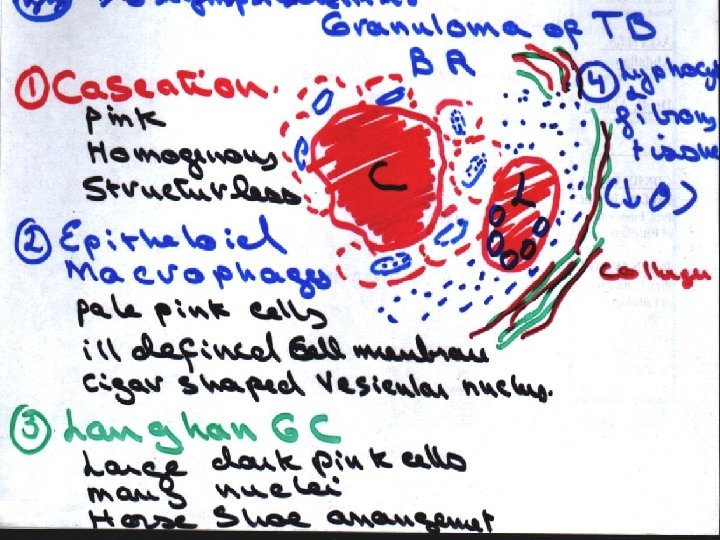
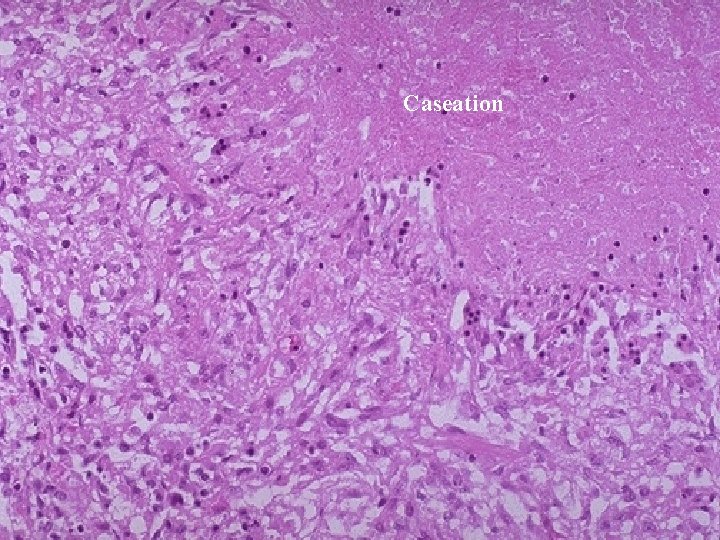
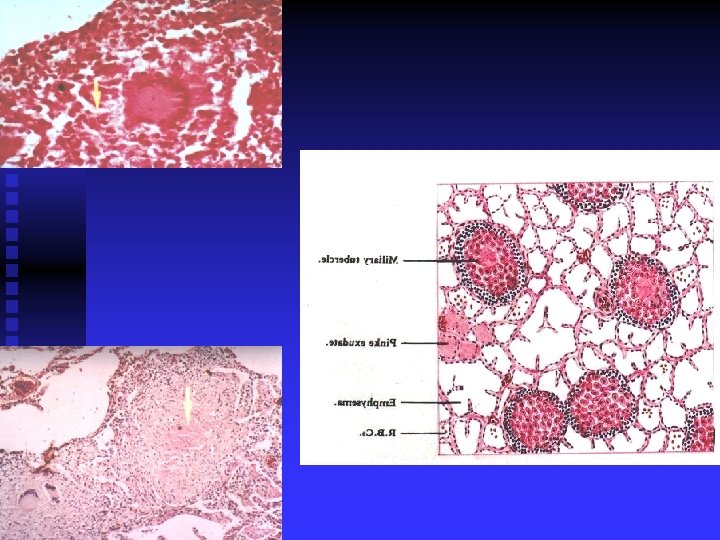
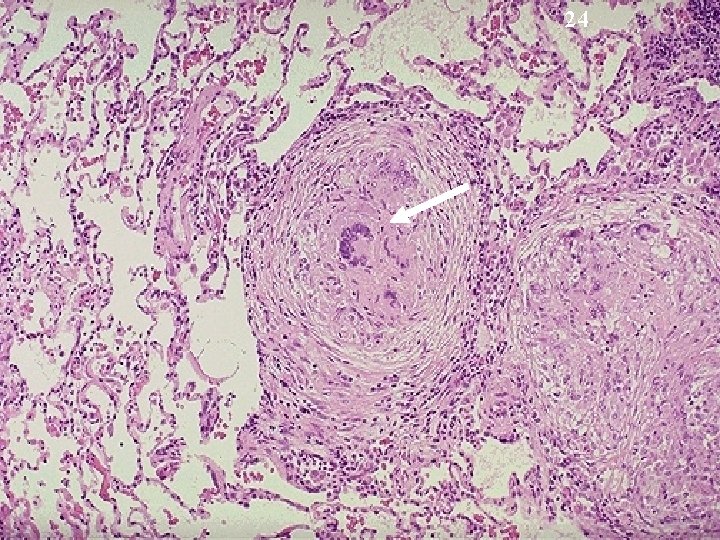
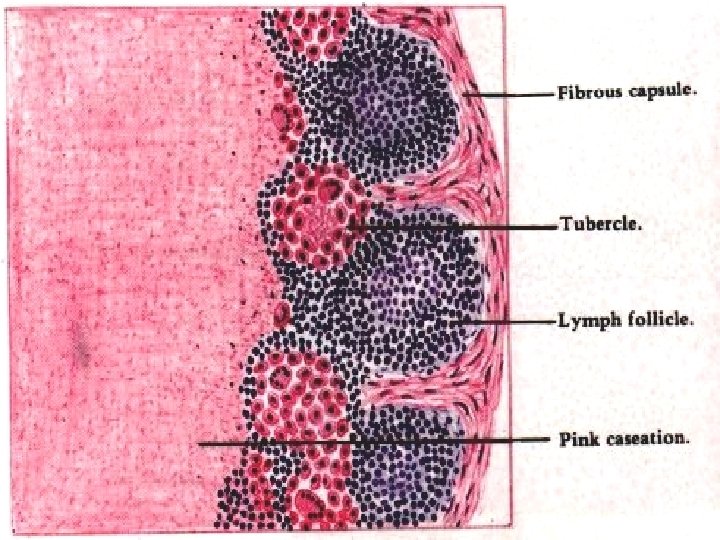
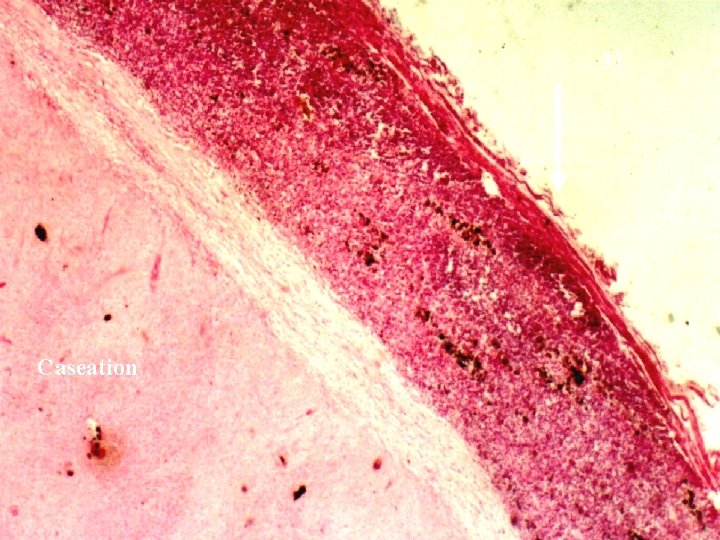
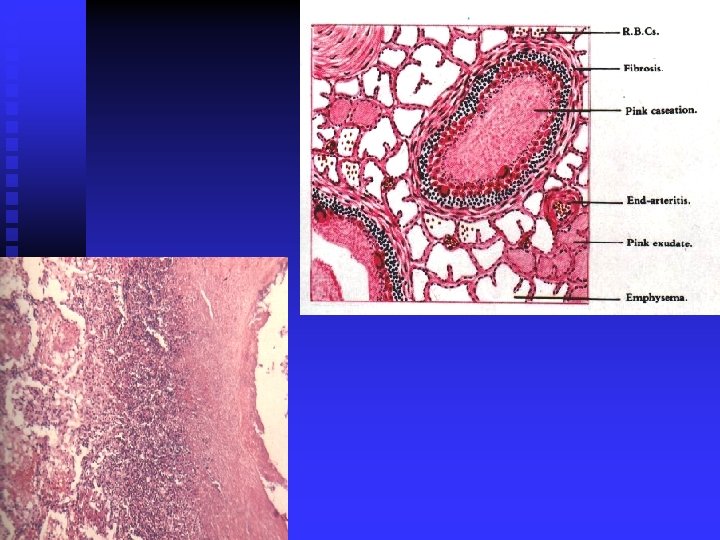
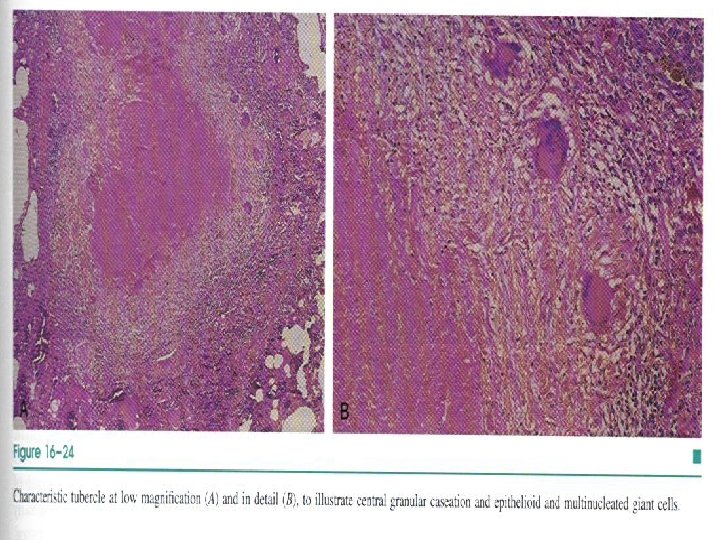
TB GRANULOMA 1 - Central zone of caseous necrosis which is structure less necrosis occurring as a result of the high lipid content of the bacilli 2 - Surrounding macrophages become transformed into large pink epithelioid cells with foamy cytoplasm and indistinct cell borders. The nucleus is pale, plump oval and vesicular (you can see details of chromatin)
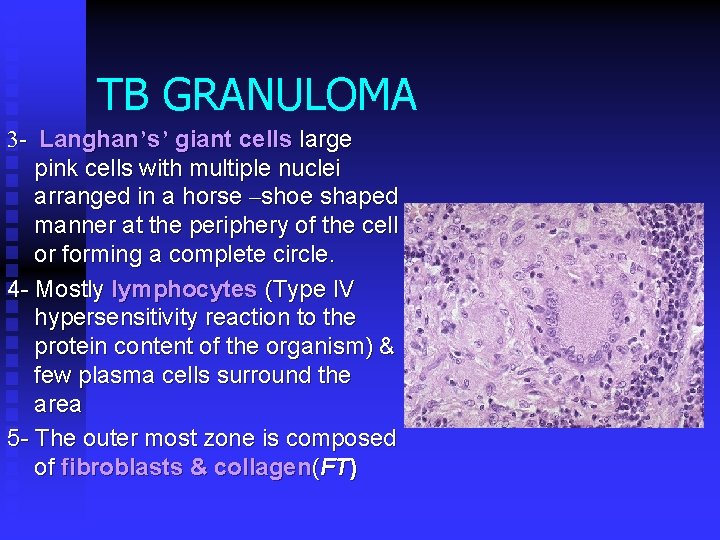
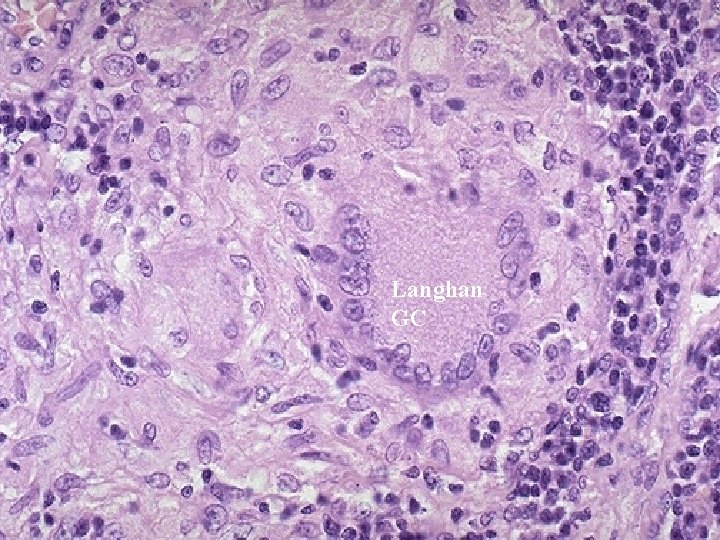
TB GRANULOMA 3 - Langhan’s’ giant cells large pink cells with multiple nuclei arranged in a horse –shoe shaped manner at the periphery of the cell or forming a complete circle. 4 - Mostly lymphocytes (Type IV hypersensitivity reaction to the protein content of the organism) & few plasma cells surround the area 5 - The outer most zone is composed of fibroblasts & collagen(FT)
Caseation
Langhan GC
1 ry TB FATE 1. Localization (95%): a-recovery & removal of bacteria or b- organism remains dormant in the scar tissue of the primary complex to be reactivated if immunity is lowered years later. 2. Spread of the primary complex if child is very debilitated resulting in Post primary TB(complicated TB in child)
24
32 Caseation
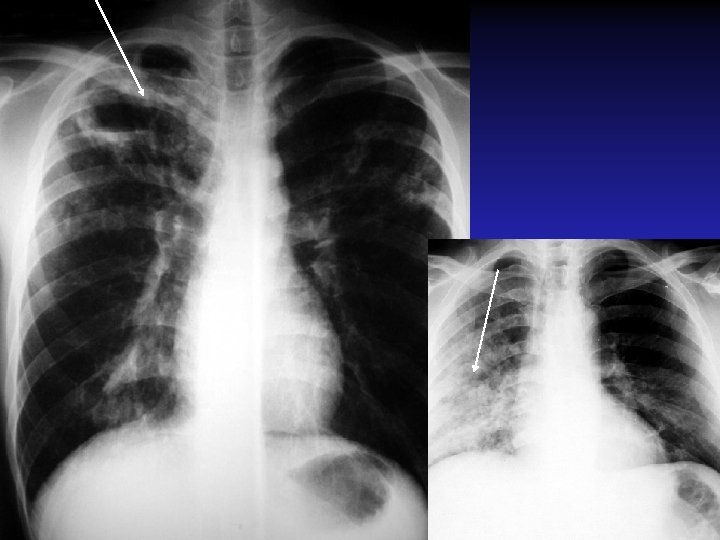
2 ry TB FIBROTIC n FIBROCASEOUS n TB CASEOUS PNEUMONIA n
Pulmonary TB complications Chronic destruction + Healing (C. inflam) 1 -Hemoptysis i. e. coughing of blood due to hemorrhage into bronchus 2 -Alveolar or bronchial rupture into pleura--Bronchopleural fistula or Pneumothorax (air in pleural cavity) 3 -Respiratory failure in diffuse caseous pneumonia or miliary TB
Pulmonary TB complications 4 -Right sided heart failure secondary to diffuse lung fibrosis, since this would elevate the pressure in the pulmonary artery producing corpulmonale (right sided heart failure 2 ry to lung disease) 5 -2 ry or systemic amyloidosis & dystrophic calcification (see cell injury) 6 -Bronchiectasis i. e. dilatation of bronchi 7 -Apical fibrosis may produce Horner's syndrome due to affection of peripheral nerves and blood vessels of the region.
DIAGNOSIS n n n Sputum BAL – effusions Biopsy Imaging — Chest radiography is frequently used to gauge whether or not the patient is likely to have active pulmonary TB, but the sensitivity and specificity are low Skin testing — Skin testing for TB is an epidemiologic tool to assess exposures and should not be performed as a test to include or exclude active pulmonary TB. It is neither sensitive nor specific. Culture - PCR
FUNGAL GRANULOMA DEFINITION: Infective suppurative granulomatous disease caused by fungal infections n LESIONS 1 Suppurative granuloma or 2 Chronic non specific suppurative inflammation n
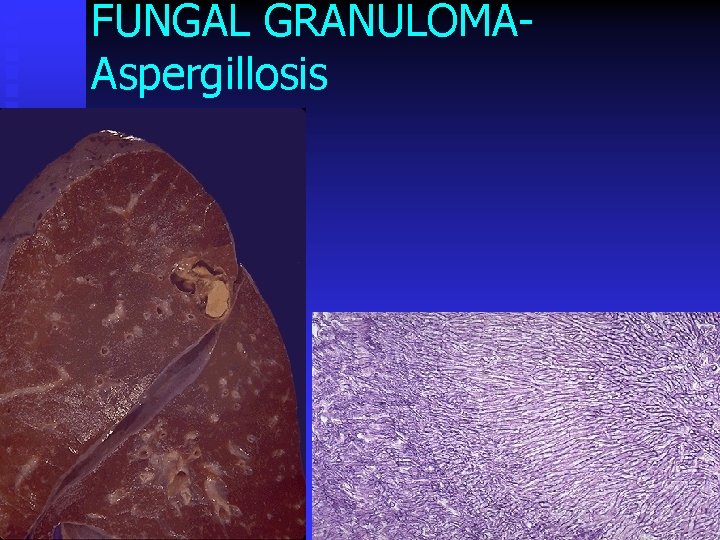
FUNGAL GRANULOMAAspergillosis
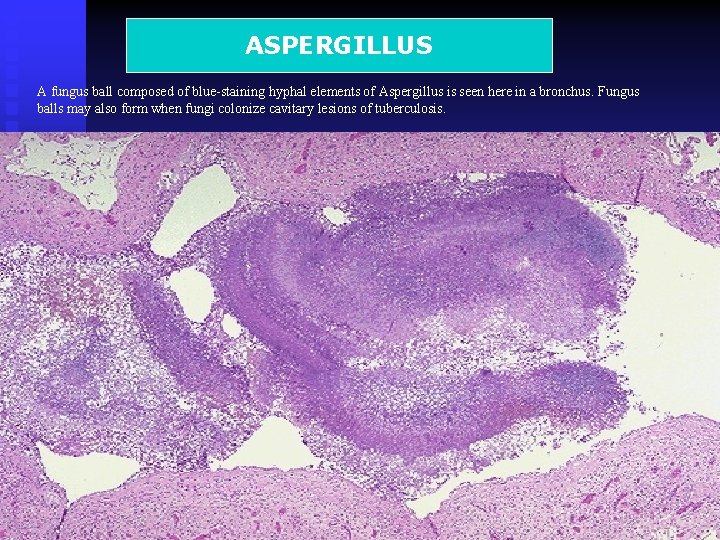
ASPERGILLUS A fungus ball composed of blue-staining hyphal elements of Aspergillus is seen here in a bronchus. Fungus balls may also form when fungi colonize cavitary lesions of tuberculosis.
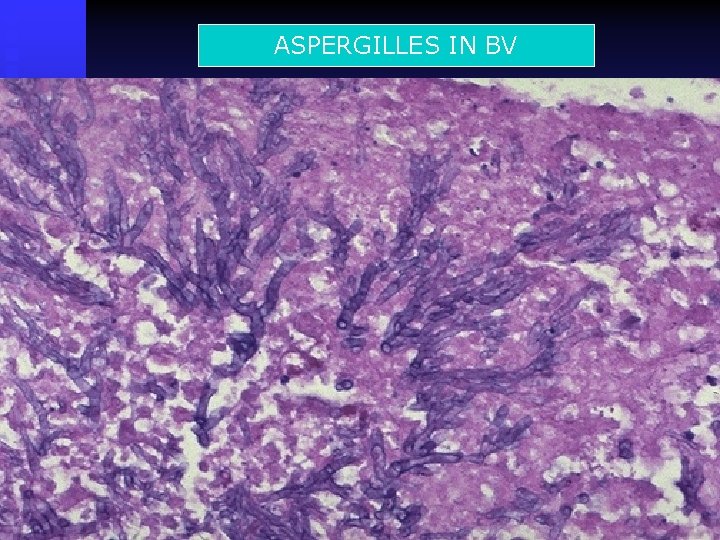
ASPERGILLES IN BV
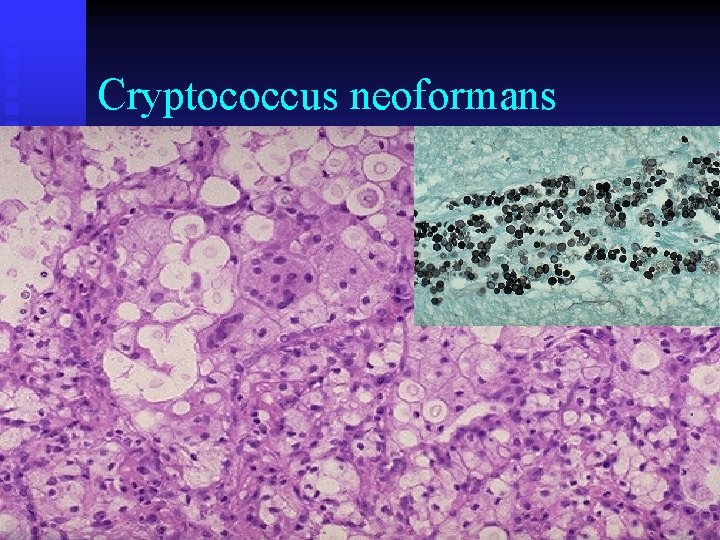
Cryptococcus neoformans
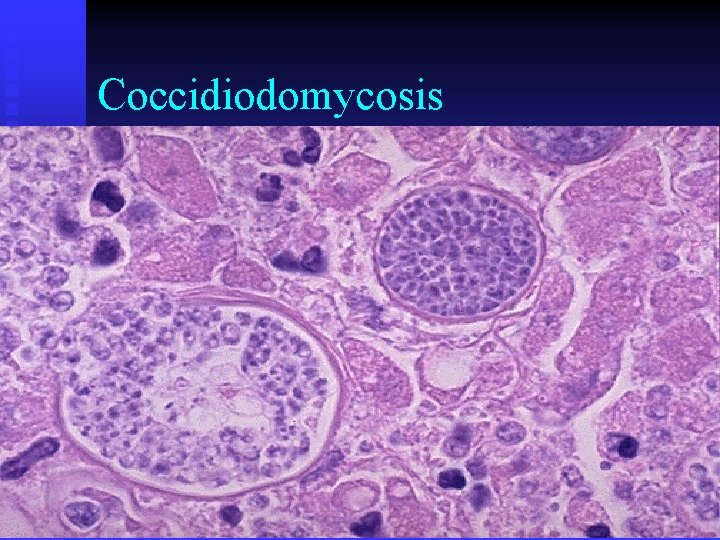
Coccidiodomycosis
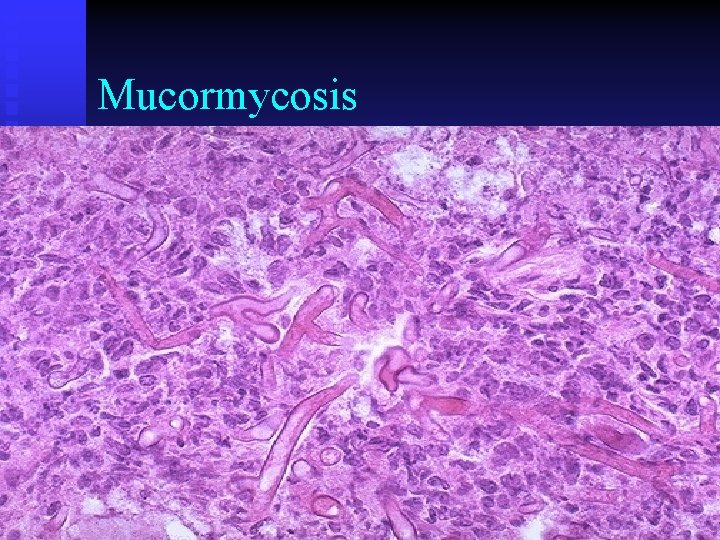
Mucormycosis
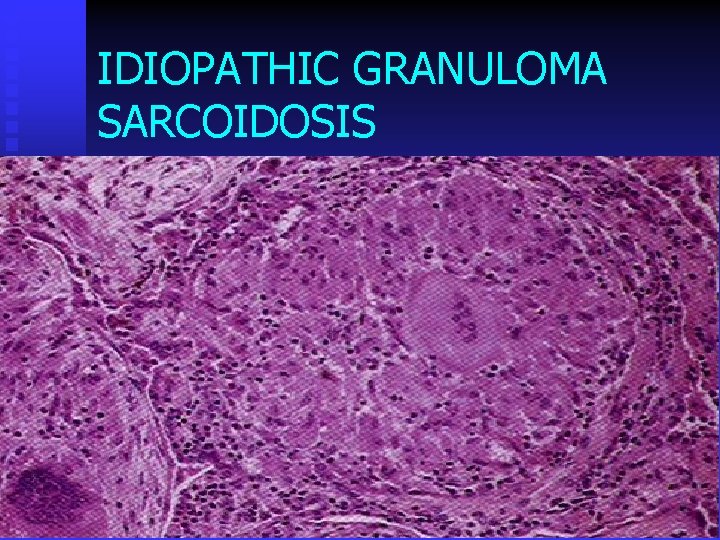
IDIOPATHIC GRANULOMA SARCOIDOSIS
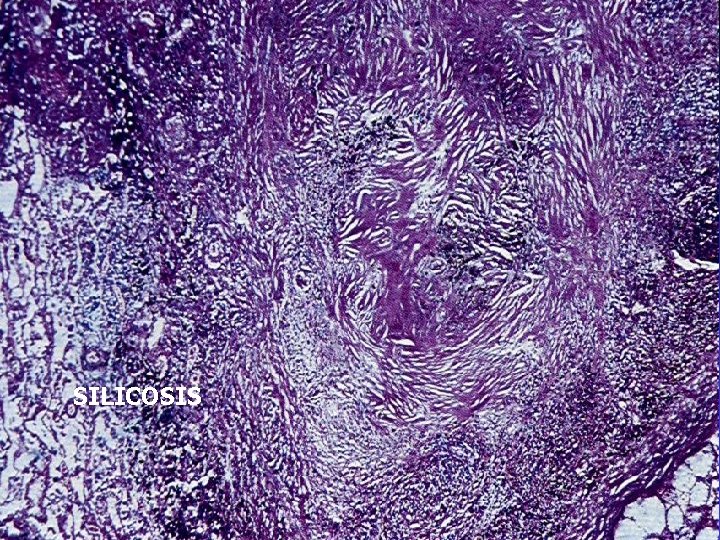
INORGANIC G. SILICOSOSIS
SILICOSIS
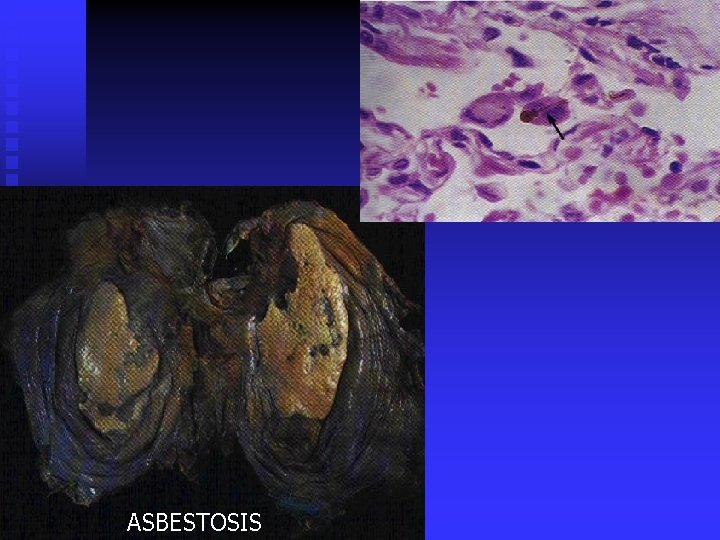
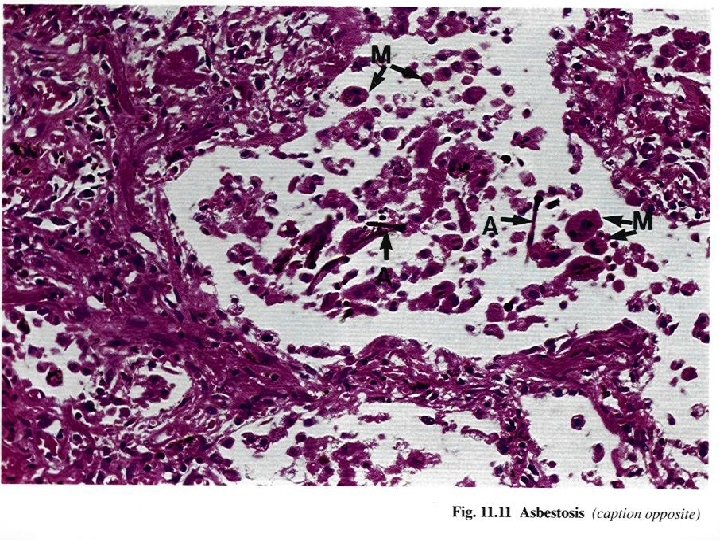
ASBESTOSIS
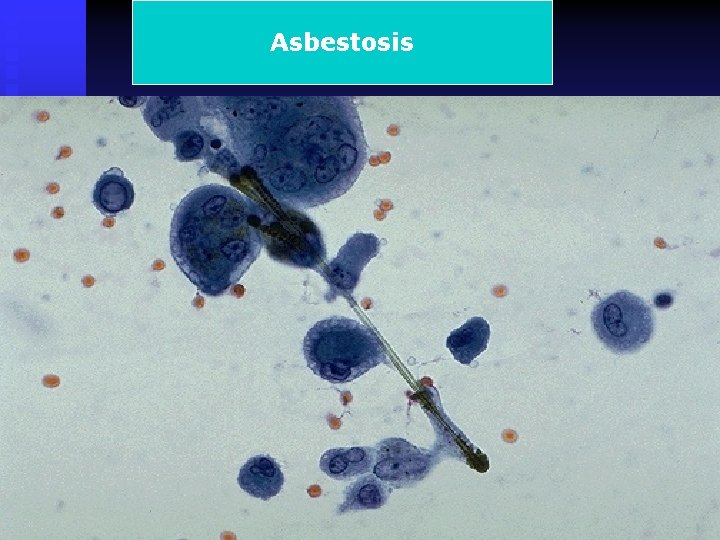
Asbestosis
Resources 1. Chandrasoma, P. & Taylor, C. R. : Concise Pathology. 3 d edition. Mc. Graw Hill Education 1997 2. El Hindawi, A. : Basic General Pathology. Faculty of Medicine, Cairo University 2009 3. Reid, R Callander, R Ramsden I, Roberts, F. Mac. Farlane, PS. Pathology Illustrated 6 th edition, Elsevier Science Health Science div 2005 4. Jones, E. & Morris, A. : Cell biology & Genetics. Mosby, London Philadelphia St. Louis, Sydney, Tokyo. 1998 5. Kumar, V. , Abbas A. K. Cotran, R. S. Robbins, & Cotran Basic Pathology. 7 h edition, W. B. Saunders Co. , Philadelphia, London, Toronto, Sydney, New York, Sydney & Tokyo. 2005 6. Stevens, J. & Lowe, J. : Pathology. Mosby. 1998 7. Underwood, J. C. E. : General and Systematic Pathology. 3 d edition. Churchill Livingstone. Edinburgh, London, Madrid, Melbourne, New York & Tokyo. 2000 8. Marbas, L. & Case E. Visual mnemonics for pathology. Blackwell publishing 2003 9 Soheir mahfouz Lecture Notes in Lower Respiratory tract Pathology 2007
Resources WEB http: //www. medicine. cu. edu. eg/beta/en/jcalpro/2428. html http: //www. kasralainy. edu. eg/elearning/ http: //www. pathmax. com/ http: //www. elc. cu. edu. eg/E-Courses. html http: //www-medlib. med. utah. edu/Web. Path/LABS/LABMENU. html#2 http: //www. med. uiuc. edu/Path. Atlasf/title. Page. html http: //www. medscape. com/pathologyhome http: //www. gwumc. edu/dept/path/2 F. HTM http: //www. path. uiowa. edu/virtualslidebox/ http: //web. med. unsw. edu. au/pathology/Pathmus/pathmus. htm#Interactive. Images http: //www. virtualpathology. leeds. ac. uk/ http: //histopathsho. 34 sp. com/index. html http: //pathology. class. kmu. edu. tw/index. htm http: //www. gla. ac. uk/faculties/medicine/teaching/Med. CALlist. htm