
Le malattie oncoematologiche ed i trapianti di cellule













- Slides: 82
Le malattie onco-ematologiche ed i trapianti di cellule staminali ematopoietiche Il Trapianto di cellule staminali emopoietiche in pazienti adulti Il ruolo del trapianto allogenico nel paziente con linfoma, mieloma, aplasia, malattie mieloproliferative croniche e malattie congenite dell’adulto Fabio Benedetti - CTMO Verona Venezia 14 maggio 2016 Università Cà Foscari
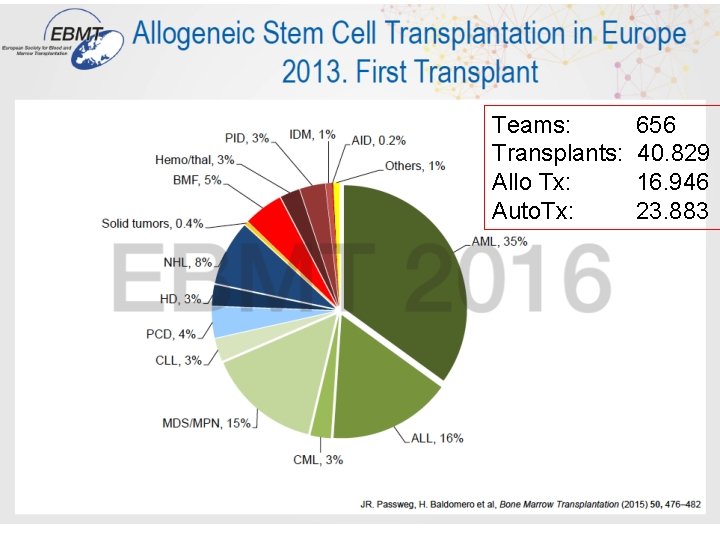
Teams: Transplants: Allo Tx: Auto. Tx: 656 40. 829 16. 946 23. 883
THALASSEMIA
Allotrapianto nella Thalassemia • malattia genetica (beta, alfa) • malattia non neoplastica • diffusa in Italia, medio oriente, Asia, Indonesia, Georgia, Armenia… • In Italia 3 milioni di portatori • primo trapianto in Seattle 1981 • primo trapianto a Pesaro 1981
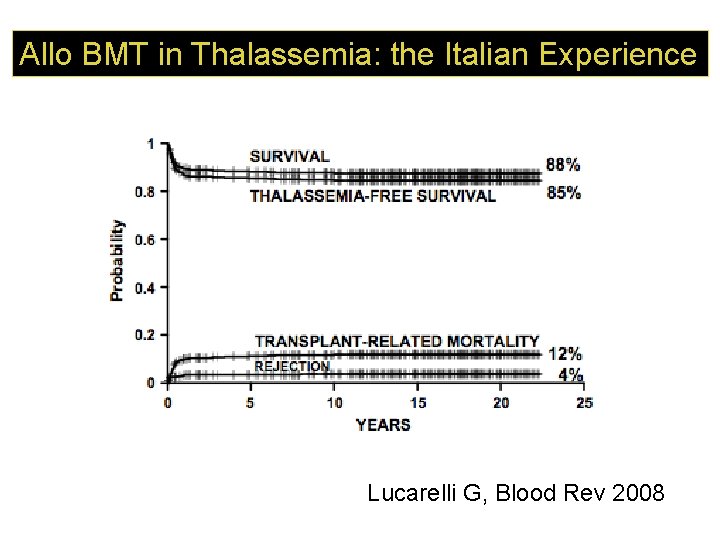
Allo BMT in Thalassemia: the Italian Experience Lucarelli G, Blood Rev 2008
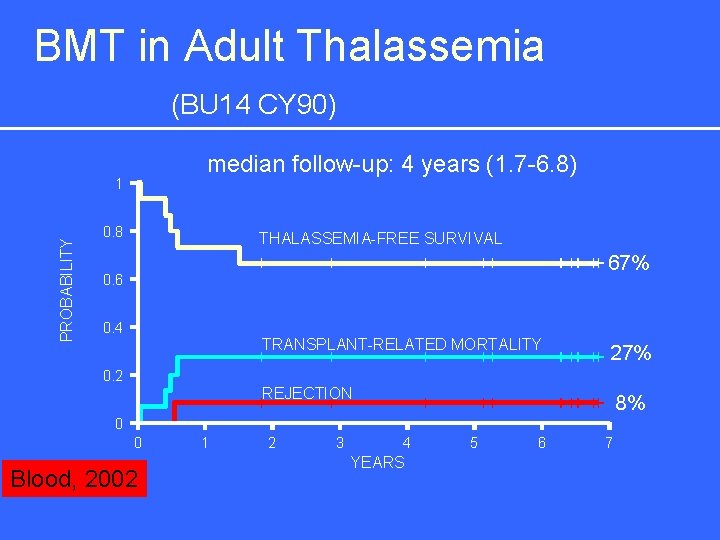
BMT in Adult Thalassemia (BU 14 CY 90) median follow-up: 4 years (1. 7 -6. 8) PROBABILITY 1 0. 8 THALASSEMIA-FREE SURVIVAL 67% 0. 6 0. 4 TRANSPLANT-RELATED MORTALITY 27% 0. 2 REJECTION 8% 0 0 Blood, 2002 1 2 3 4 YEARS 5 6 7
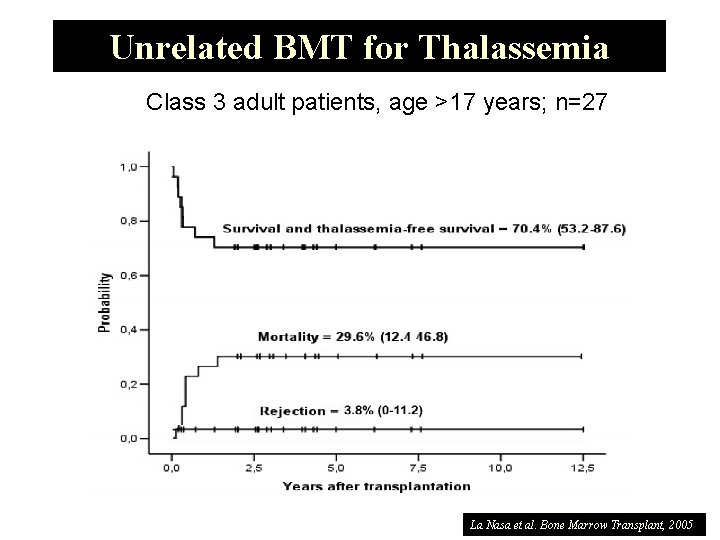
Unrelated BMT for Thalassemia Class 3 adult patients, age >17 years; n=27 La Nasa et al. Bone Marrow Transplant, 2005
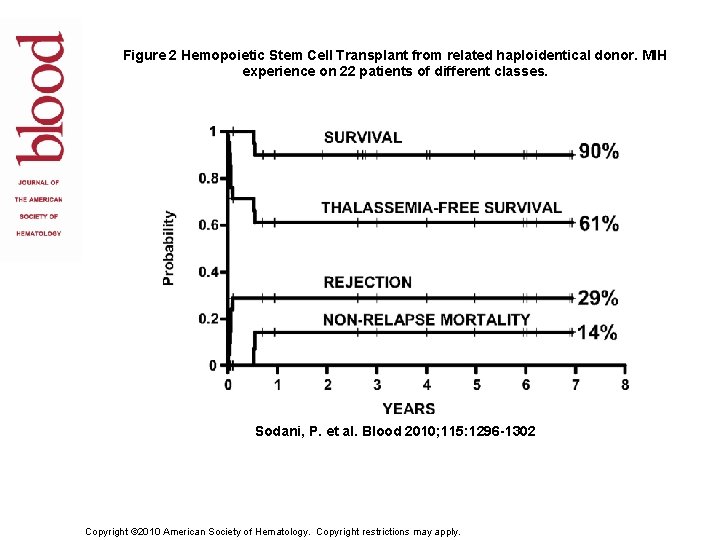
Figure 2 Hemopoietic Stem Cell Transplant from related haploidentical donor. MIH experience on 22 patients of different classes. Sodani, P. et al. Blood 2010; 115: 1296 -1302 Copyright © 2010 American Society of Hematology. Copyright restrictions may apply.
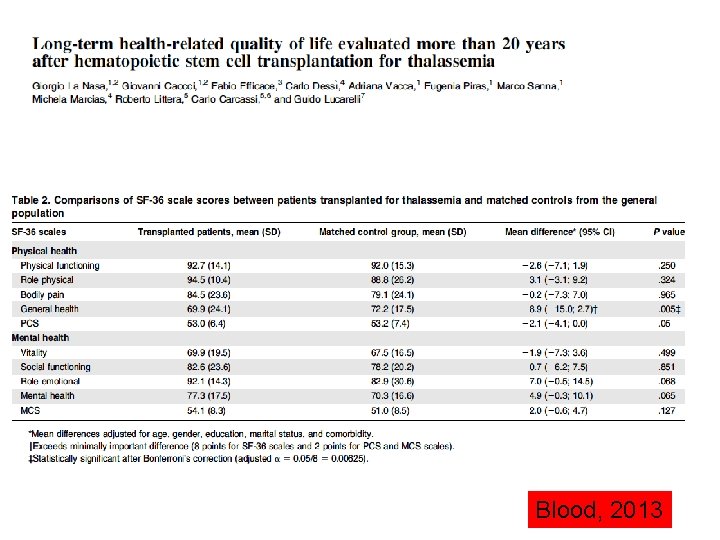
Blood, 2013
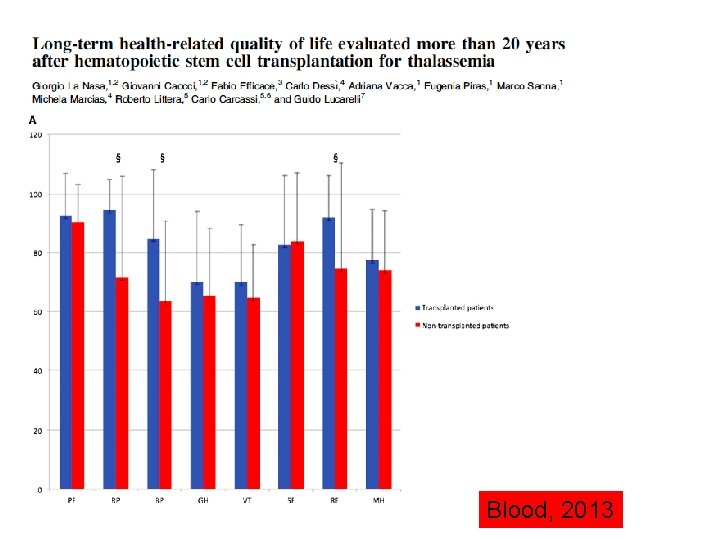
Blood, 2013
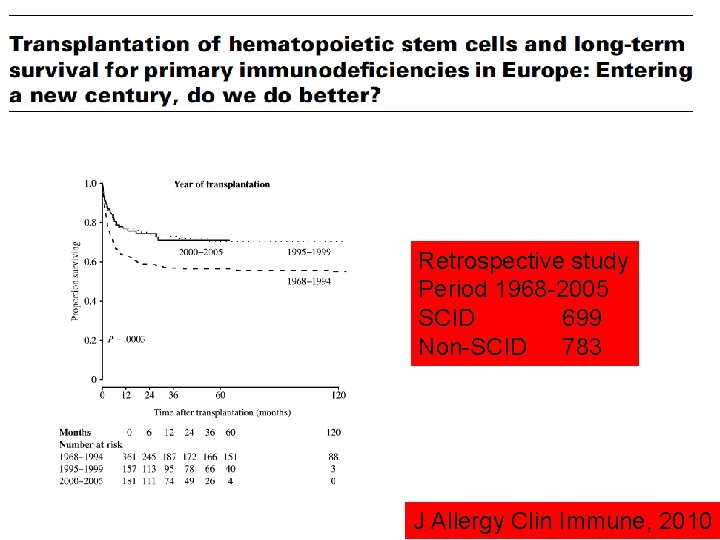
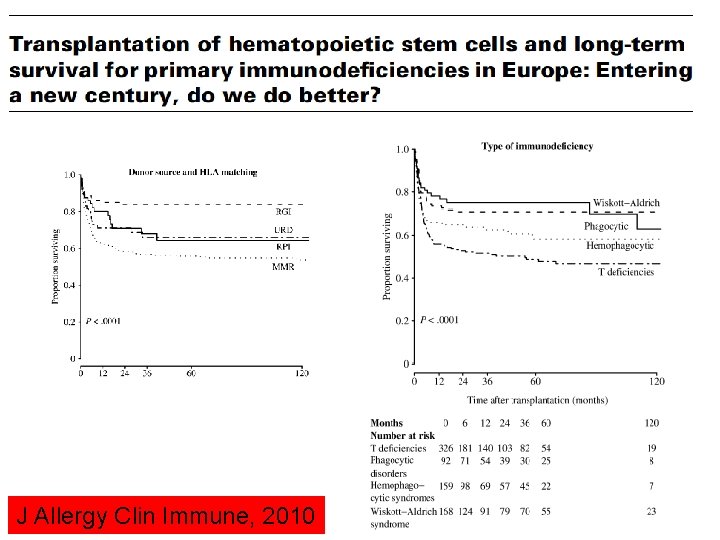
Retrospective study Period 1968 -2005 SCID 699 Non-SCID 783 J Allergy Clin Immune, 2010
J Allergy Clin Immune, 2010
Multiple Myeloma
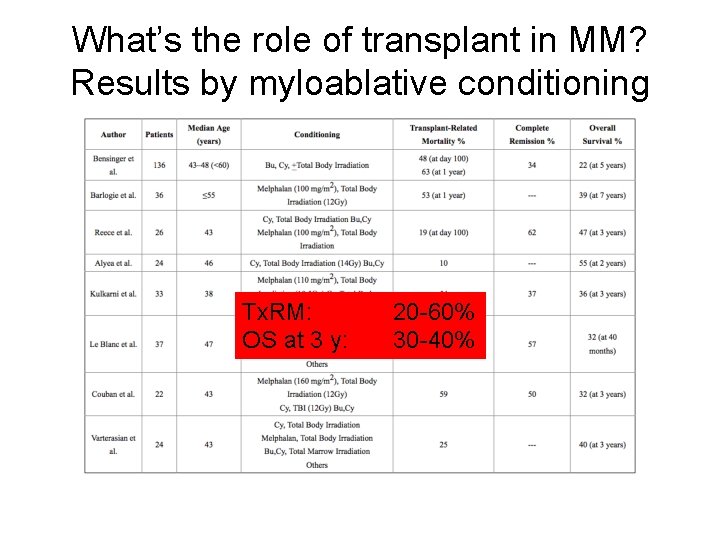
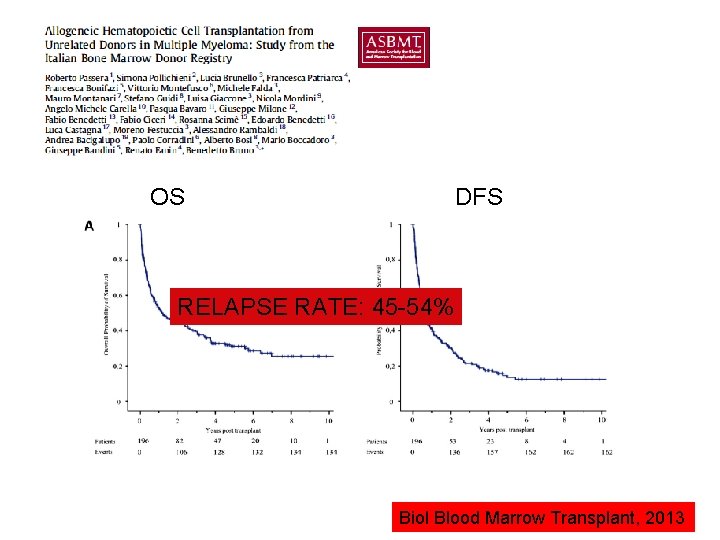
What’s the role of transplant in MM? Results by myloablative conditioning Tx. RM: OS at 3 y: 20 -60% 30 -40%
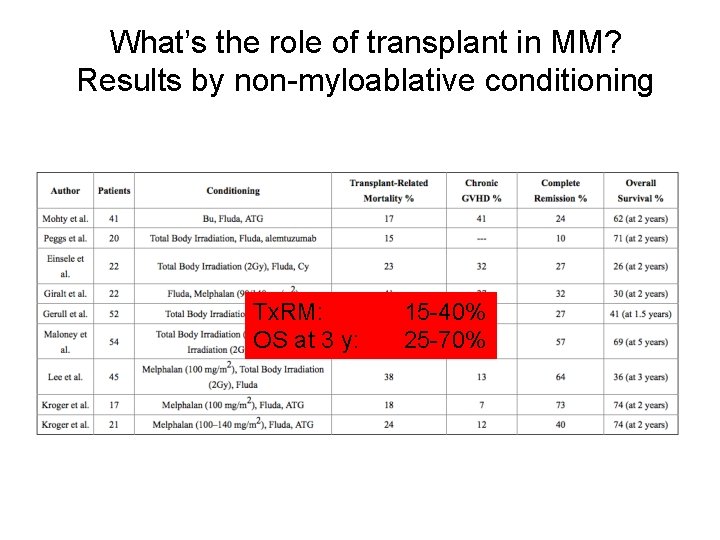
What’s the role of transplant in MM? Results by non-myloablative conditioning Tx. RM: OS at 3 y: 15 -40% 25 -70%
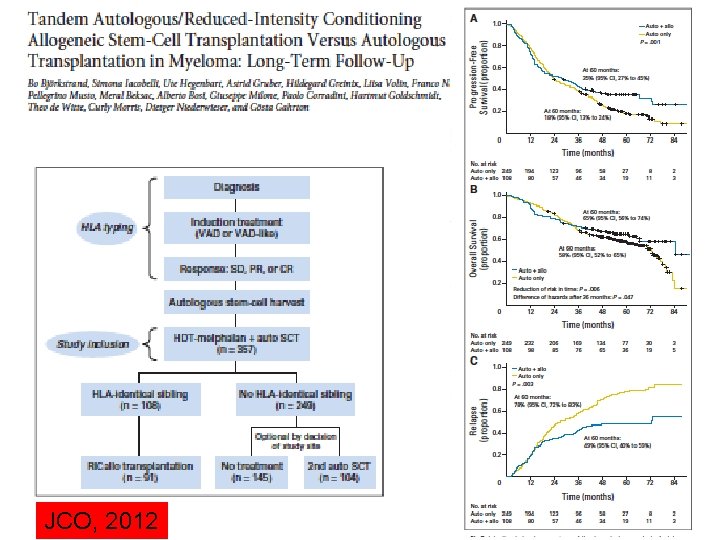
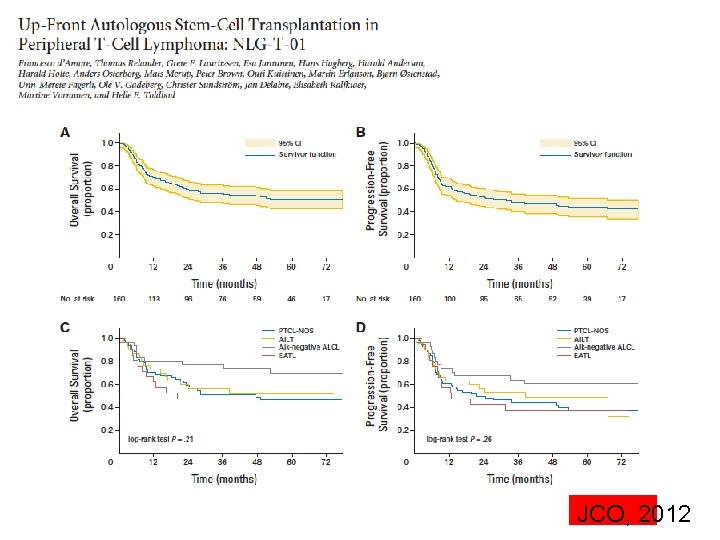
JCO, 2012
OS DFS RELAPSE RATE: 45 -54% Biol Blood Marrow Transplant, 2013
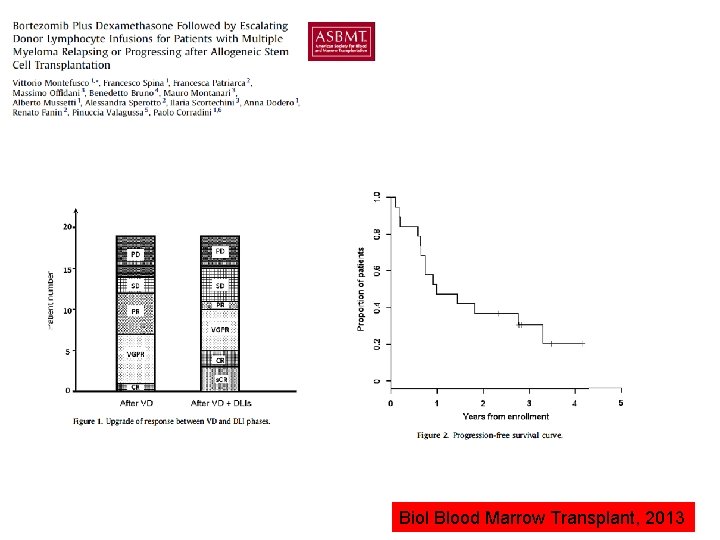
Biol Blood Marrow Transplant, 2013
BMT, 2016
SAA
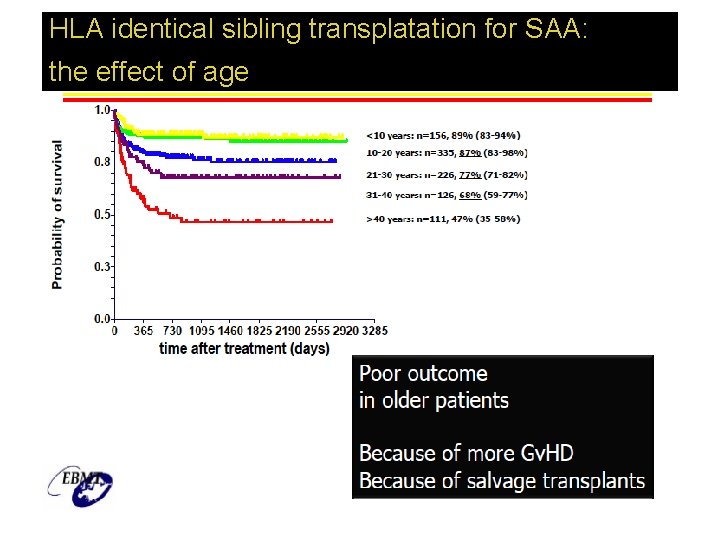
HLA identical sibling transplatation for SAA: the effect of age
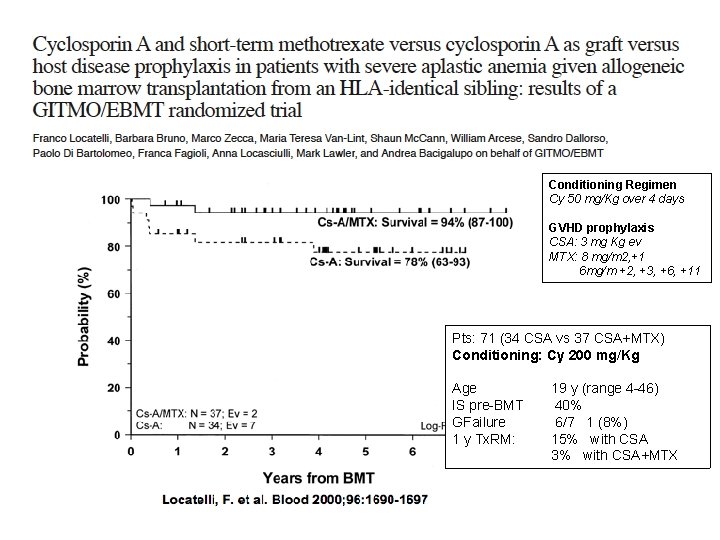
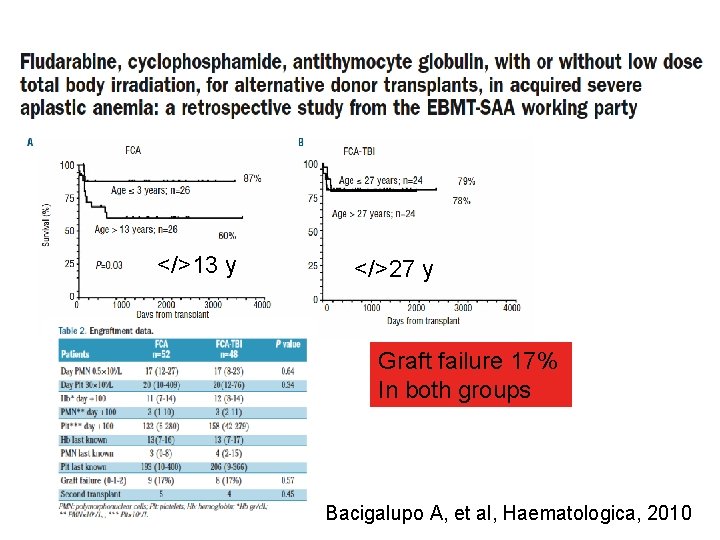
Conditioning Regimen Cy 50 mg/Kg over 4 days GVHD prophylaxis CSA: 3 mg Kg ev MTX: 8 mg/m 2, +1 6 mg/m +2, +3, +6, +11 Pts: 71 (34 CSA vs 37 CSA+MTX) Conditioning: Cy 200 mg/Kg Age IS pre-BMT GFailure 1 y Tx. RM: 19 y (range 4 -46) 40% 6/7 1 (8%) 15% with CSA 3% with CSA+MTX
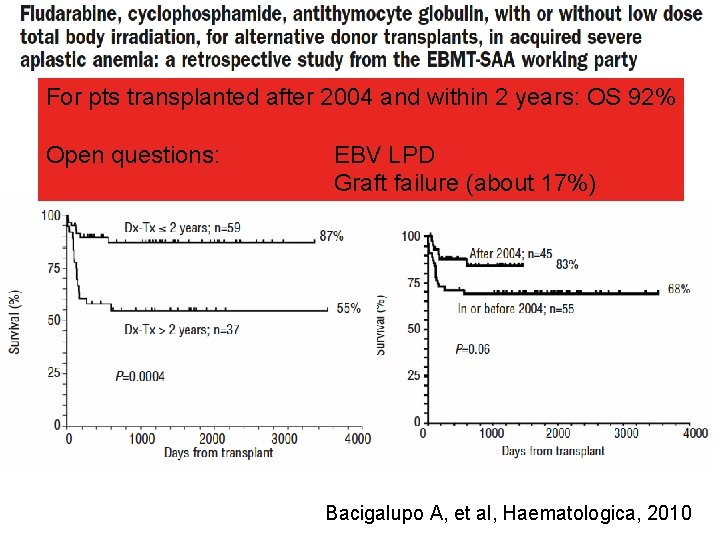
</>13 y </>27 y Graft failure 17% In both groups Bacigalupo A, et al, Haematologica, 2010
NHL
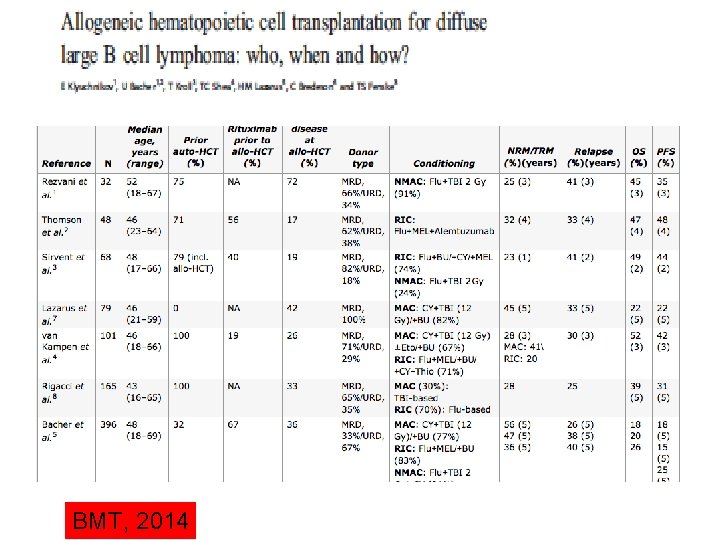
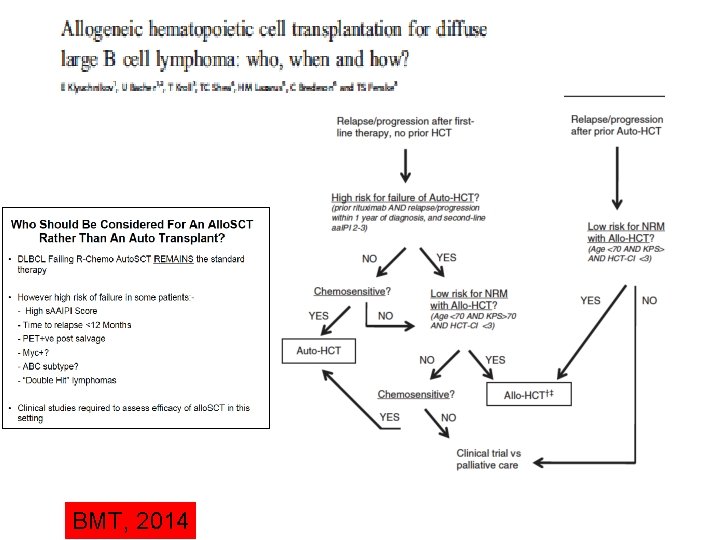
BMT, 2014
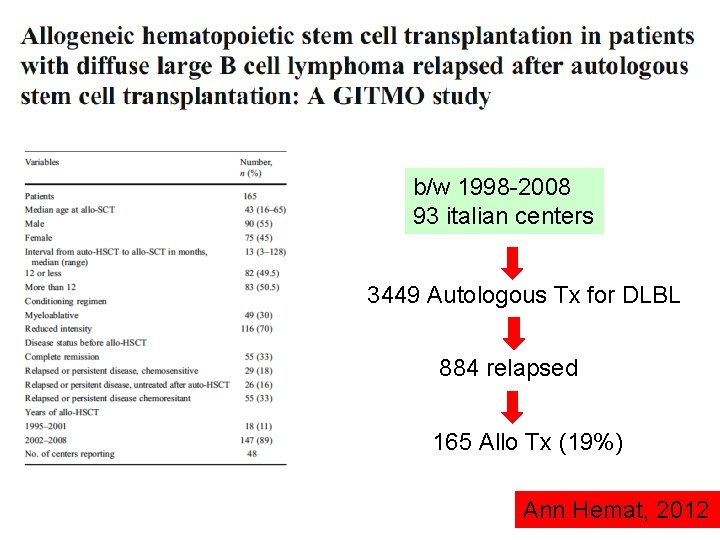
b/w 1998 -2008 93 italian centers 3449 Autologous Tx for DLBL 884 relapsed 165 Allo Tx (19%) Ann Hemat, 2012
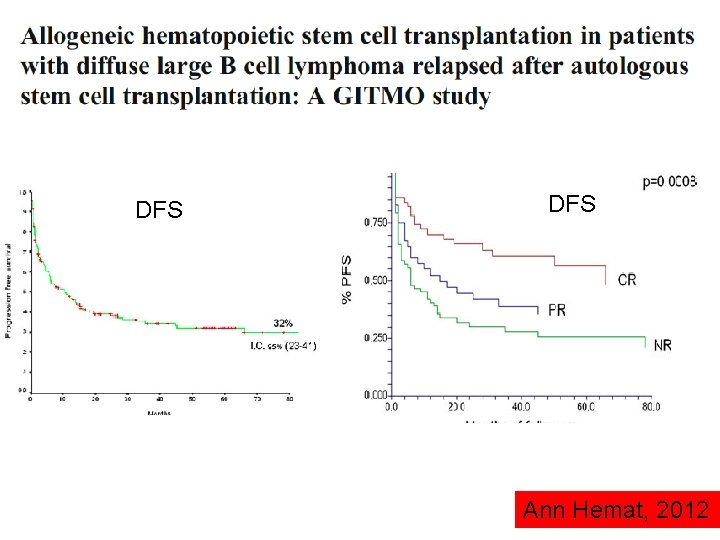
DFS Ann Hemat, 2012
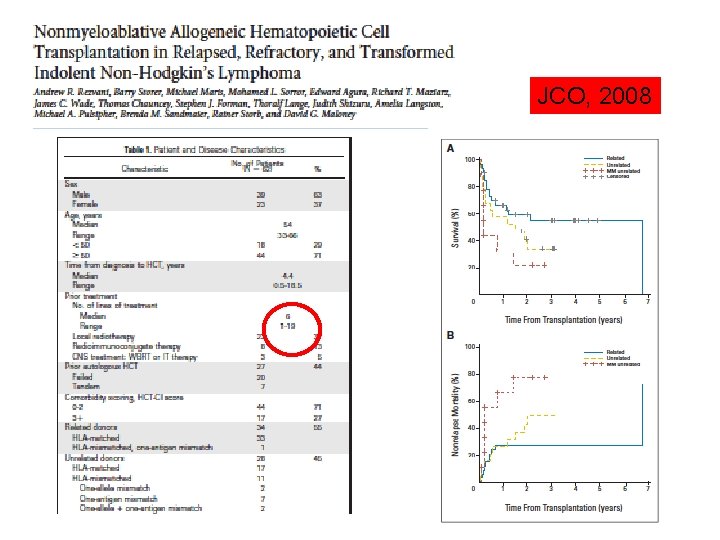
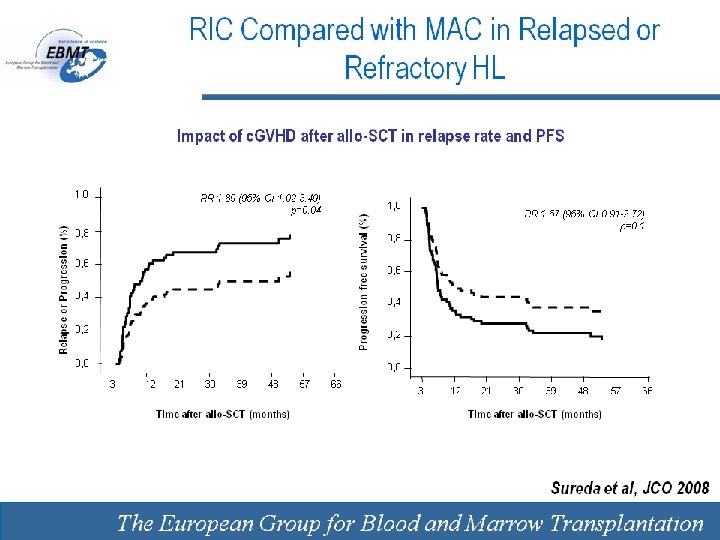
JCO, 2008
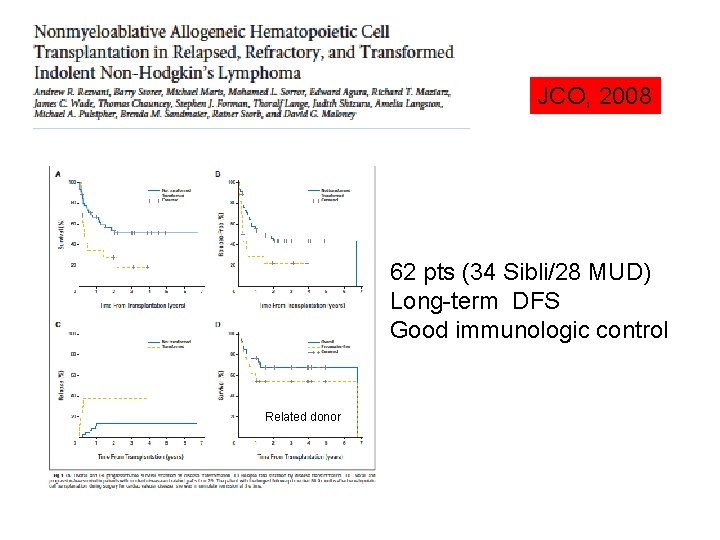
JCO, 2008 62 pts (34 Sibli/28 MUD) Long-term DFS Good immunologic control Related donor
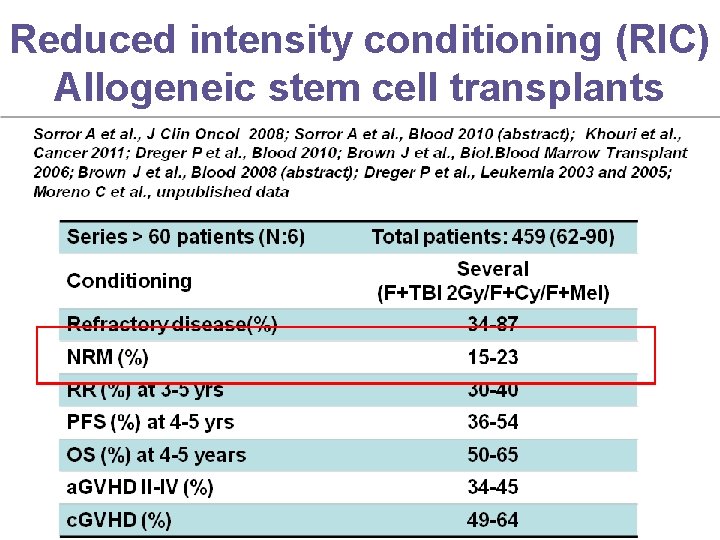
Reduced intensity conditioning (RIC) Allogeneic stem cell transplants
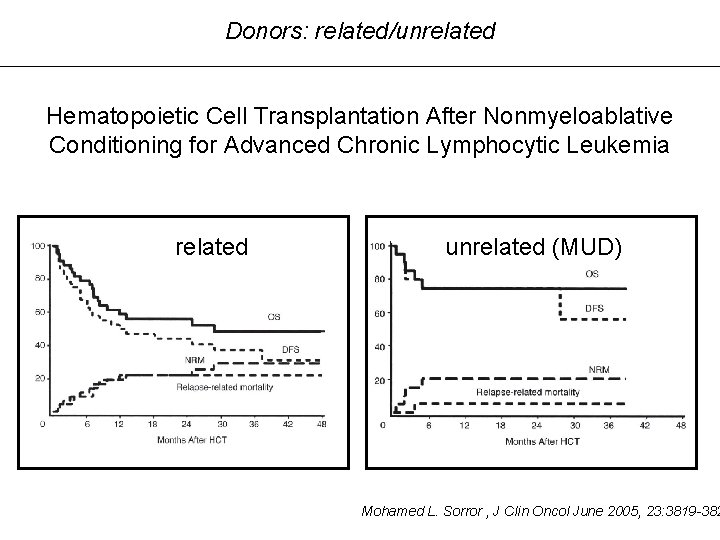
Donors: related/unrelated Hematopoietic Cell Transplantation After Nonmyeloablative Conditioning for Advanced Chronic Lymphocytic Leukemia related unrelated (MUD) Mohamed L. Sorror , J Clin Oncol June 2005, 23: 3819 -382
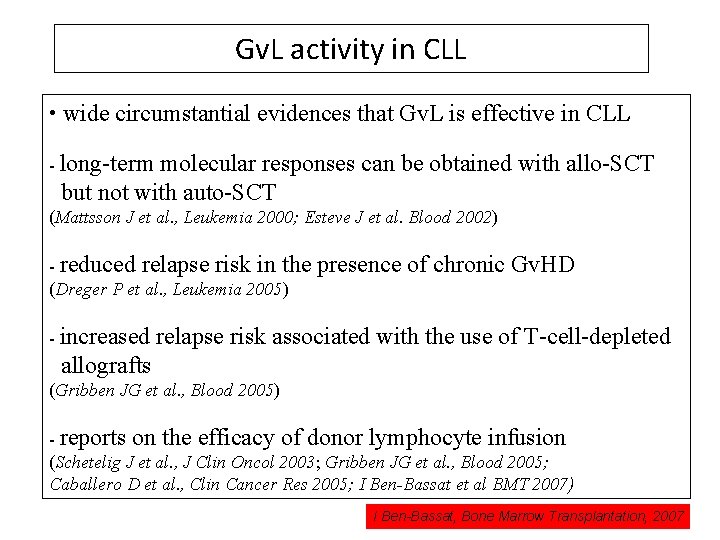
Gv. L activity in CLL • wide circumstantial evidences that Gv. L is effective in CLL - long-term molecular responses can be obtained with allo-SCT but not with auto-SCT (Mattsson J et al. , Leukemia 2000; Esteve J et al. Blood 2002) - reduced relapse risk in the presence of chronic Gv. HD (Dreger P et al. , Leukemia 2005) - increased relapse risk associated with the use of T-cell-depleted allografts (Gribben JG et al. , Blood 2005) - reports on the efficacy of donor lymphocyte infusion (Schetelig J et al. , J Clin Oncol 2003; Gribben JG et al. , Blood 2005; Caballero D et al. , Clin Cancer Res 2005; I Ben-Bassat et al BMT 2007) I Ben-Bassat, Bone Marrow Transplantation, 2007
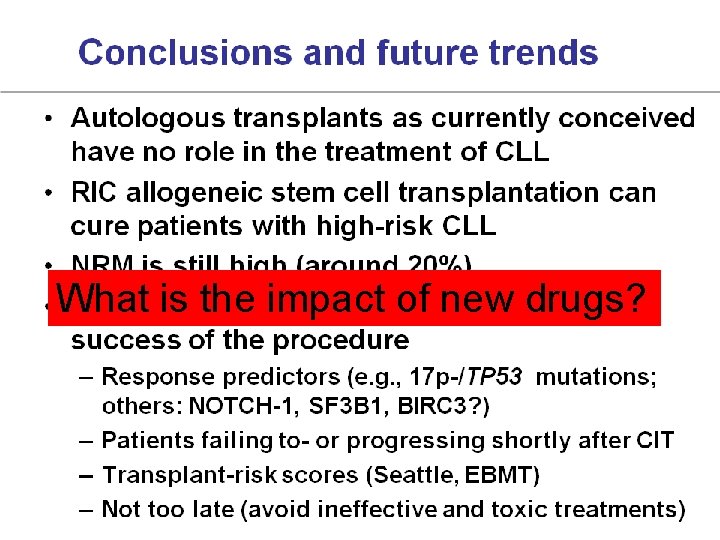
What is the impact of new drugs?
NHL-T
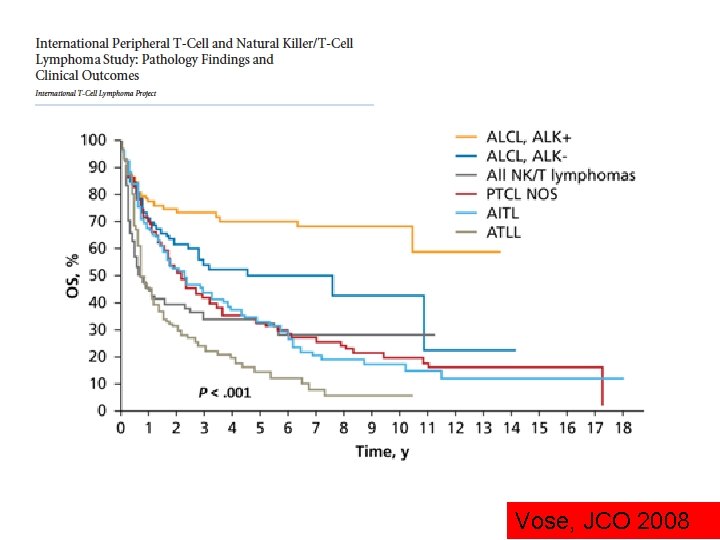
Vose, JCO 2008
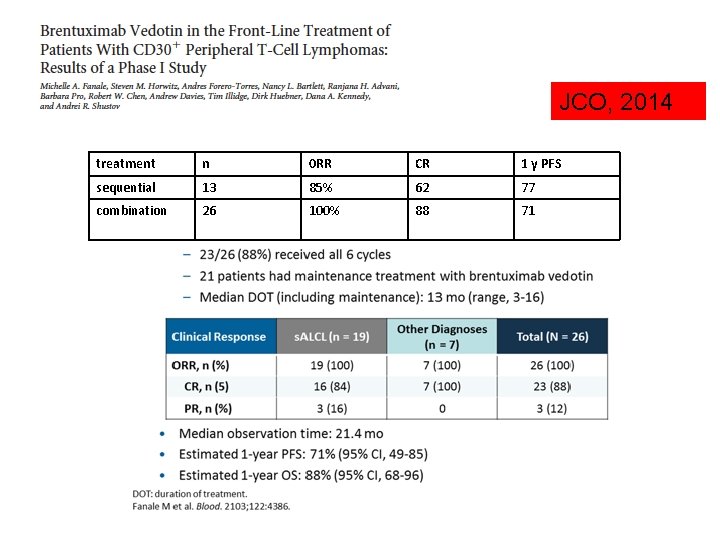
JCO, 2014 treatment n 0 RR CR 1 y PFS sequential 13 85% 62 77 combination 26 100% 88 71
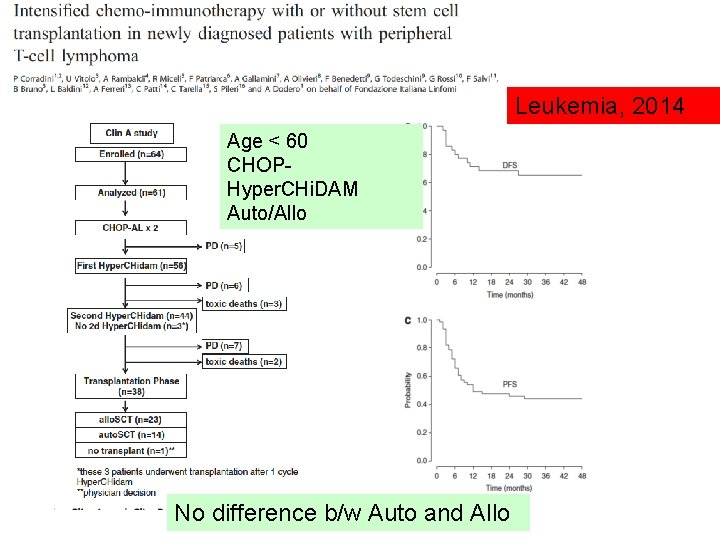
Leukemia, 2014 Age < 60 CHOPHyper. CHi. DAM Auto/Allo No difference b/w Auto and Allo
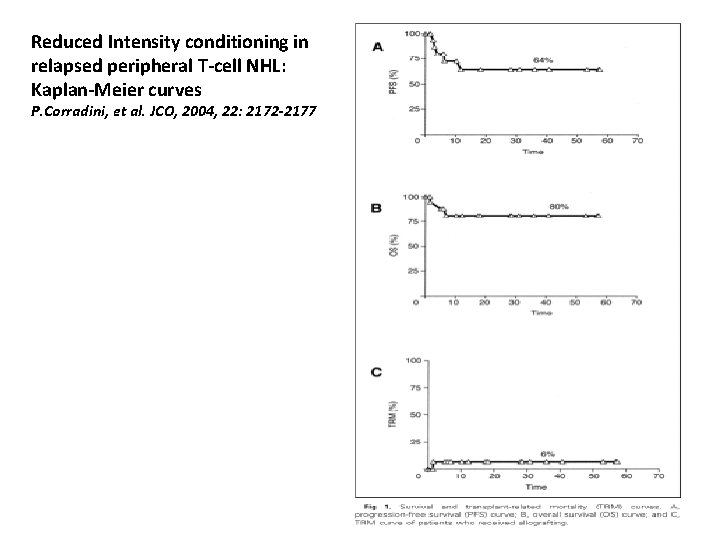
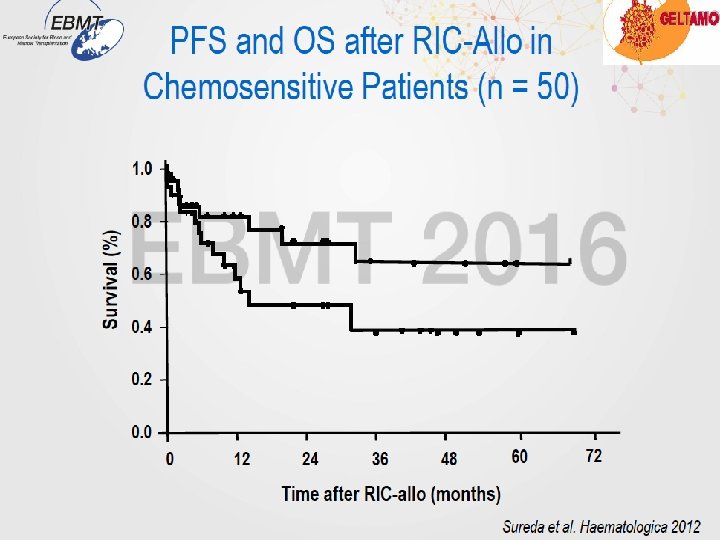
Reduced Intensity conditioning in relapsed peripheral T-cell NHL: Kaplan-Meier curves P. Corradini, et al. JCO, 2004, 22: 2172 -2177
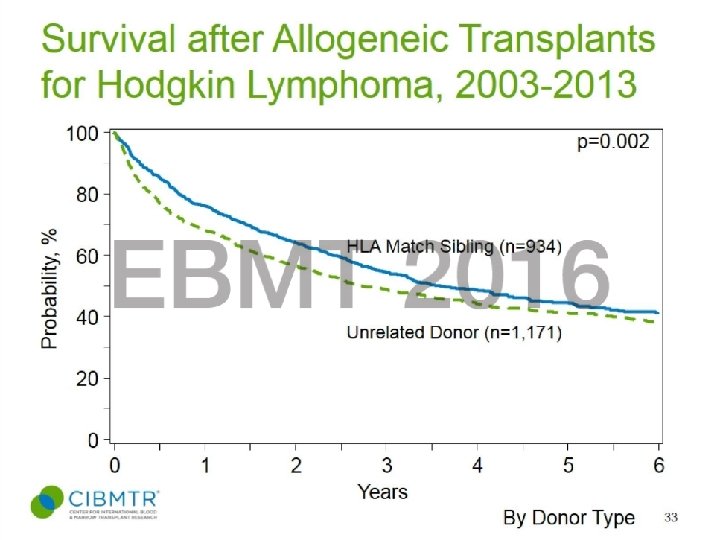
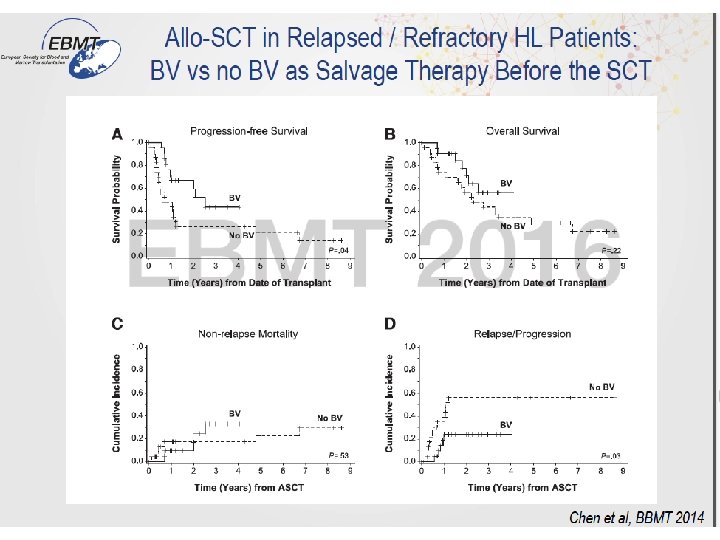
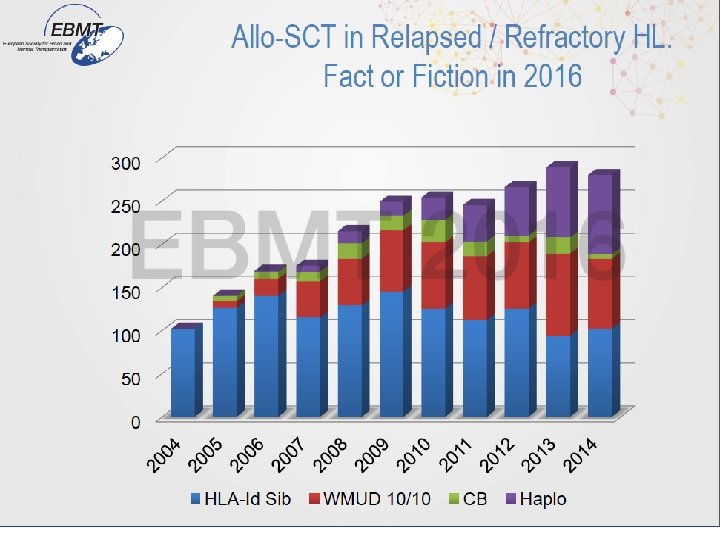
HD
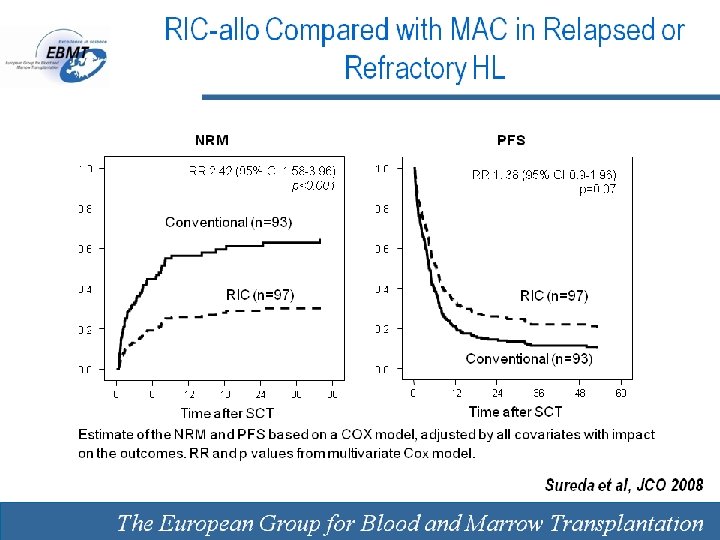
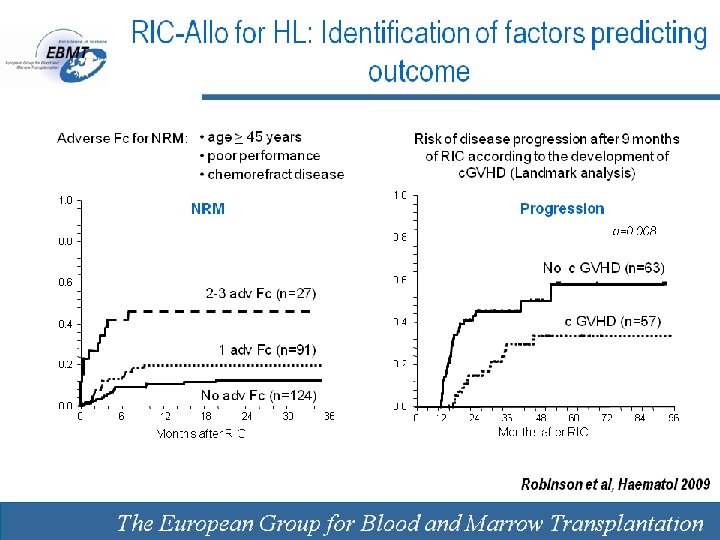
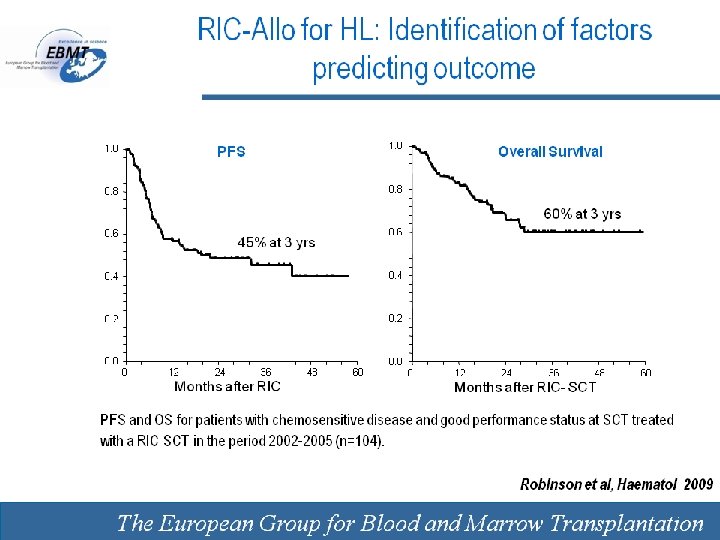
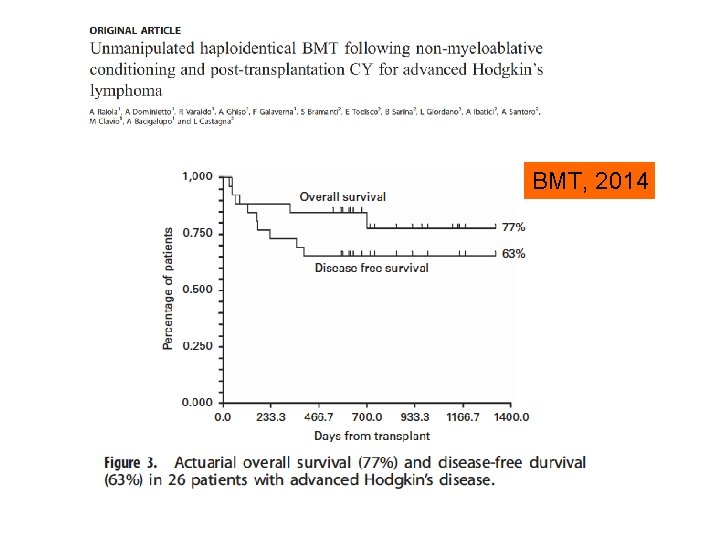
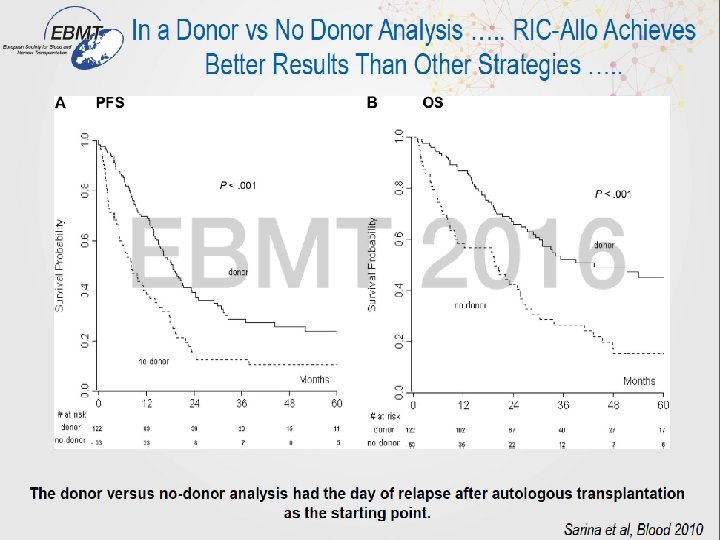
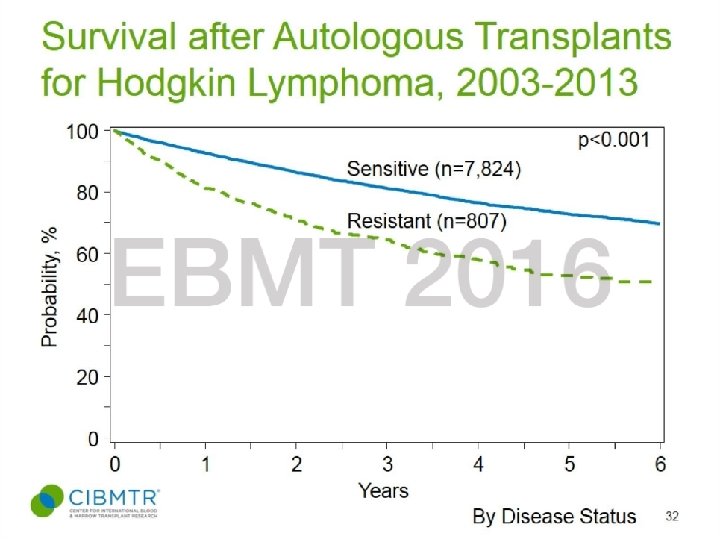
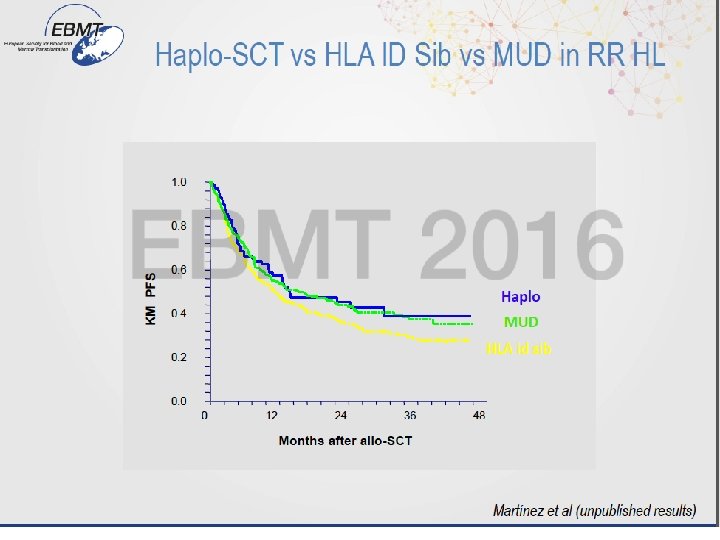
BMT, 2014
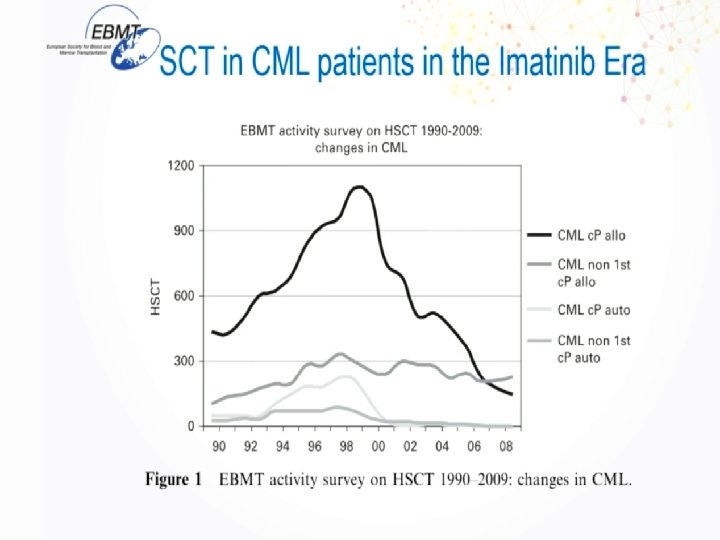
CML/MFI
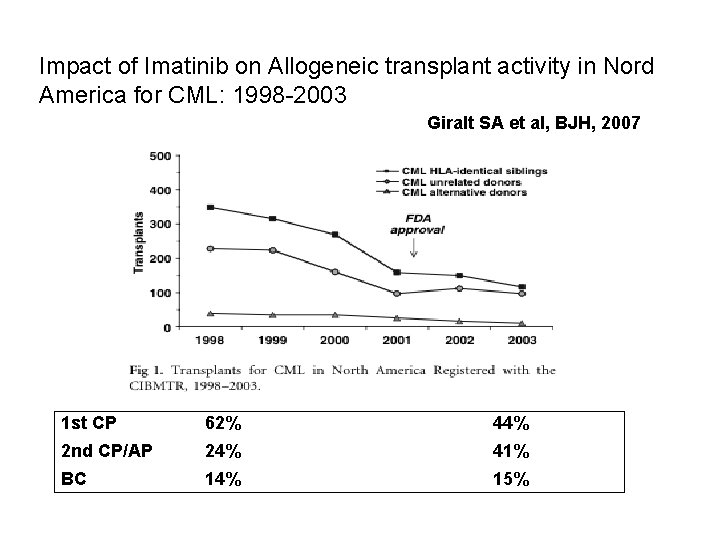
Impact of Imatinib on Allogeneic transplant activity in Nord America for CML: 1998 -2003 Giralt SA et al, BJH, 2007 1 st CP 62% 44% 2 nd CP/AP 24% 41% BC 14% 15%
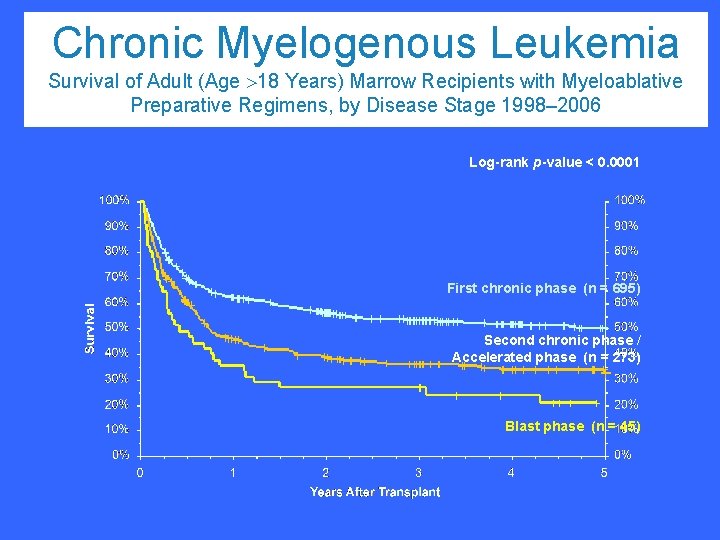
Chronic Myelogenous Leukemia Survival of Adult (Age >18 Years) Marrow Recipients with Myeloablative Preparative Regimens, by Disease Stage 1998– 2006 Log-rank p-value < 0. 0001 First chronic phase (n = 695) Second chronic phase / Accelerated phase (n = 273) Blast phase (n = 45)
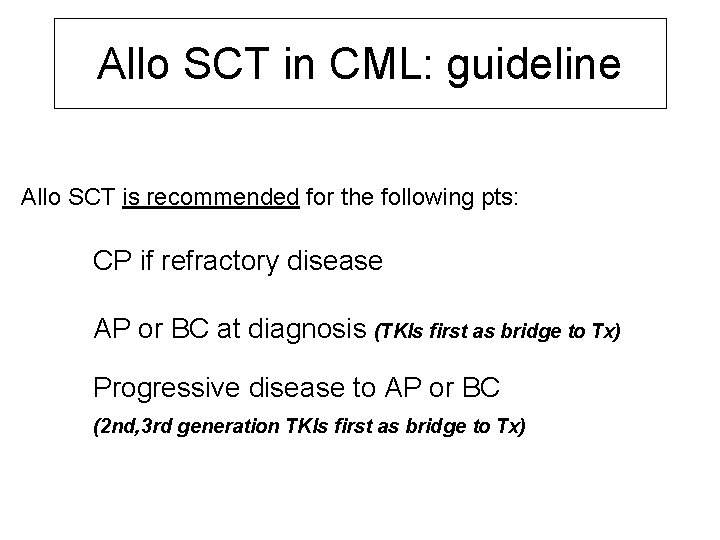
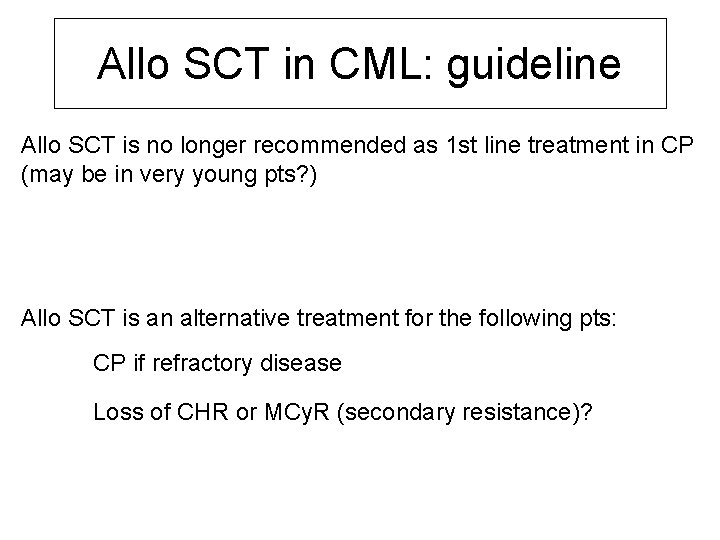
Allo SCT in CML: guideline Allo SCT is recommended for the following pts: CP if refractory disease AP or BC at diagnosis (TKIs first as bridge to Tx) Progressive disease to AP or BC (2 nd, 3 rd generation TKIs first as bridge to Tx)
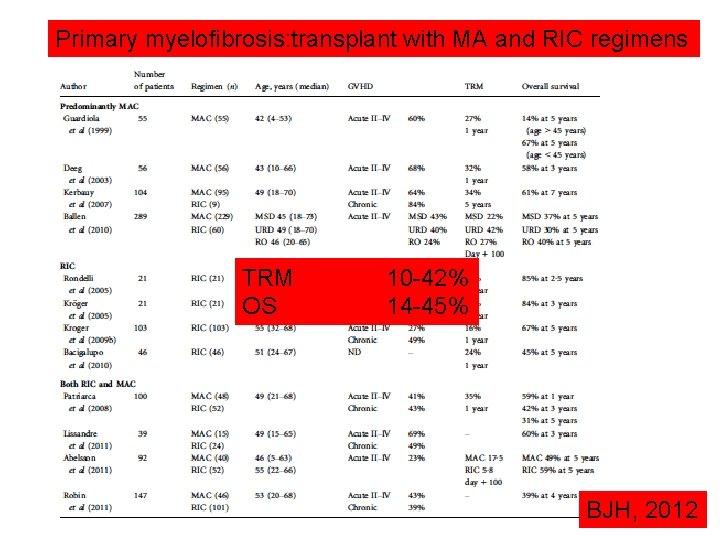
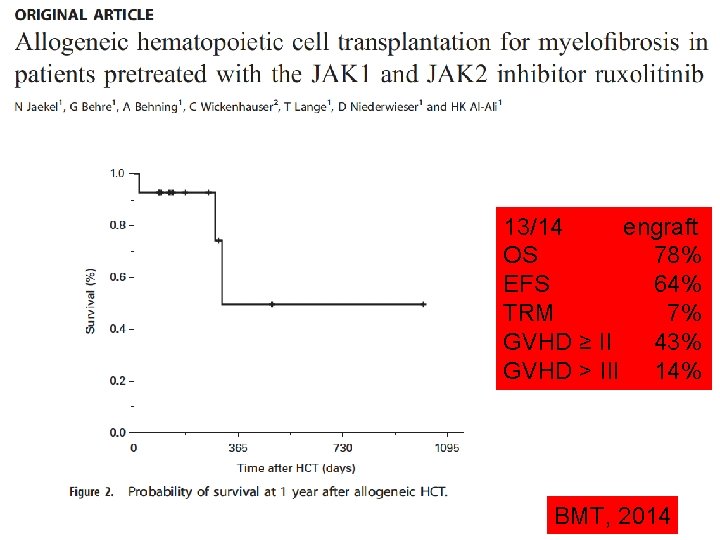
Primary myelofibrosis: transplant with MA and RIC regimens TRM OS 10 -42% 14 -45% BJH, 2012
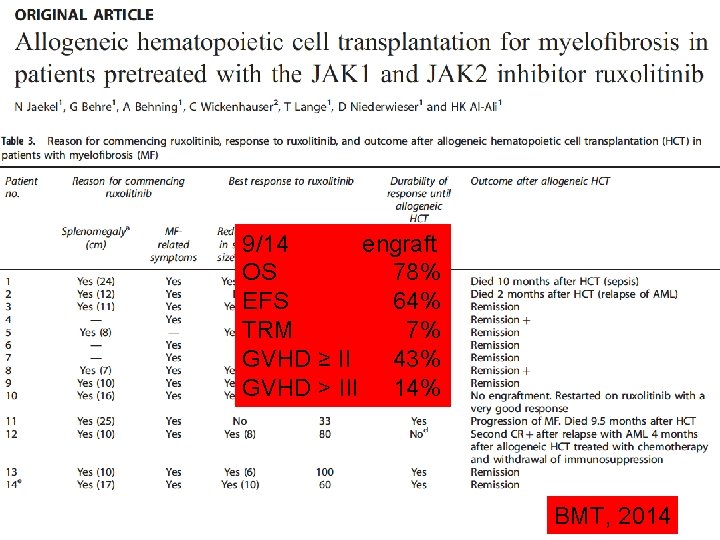
9/14 engraft OS 78% EFS 64% TRM 7% GVHD ≥ II 43% GVHD > III 14% BMT, 2014
thank you for your attention
BMT, 2014
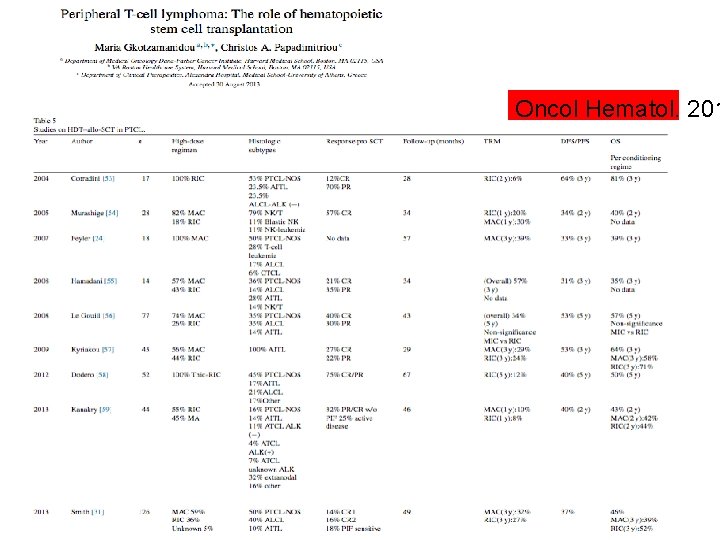
Oncol Hematol. 201
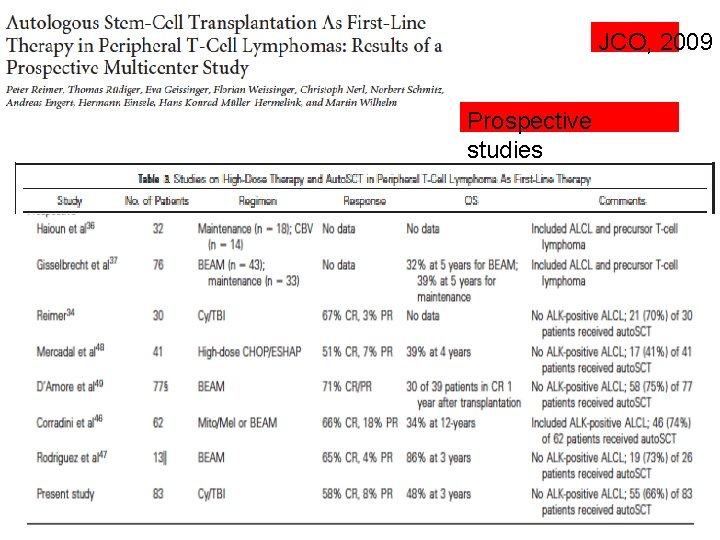
JCO, 2009 Prospective studies
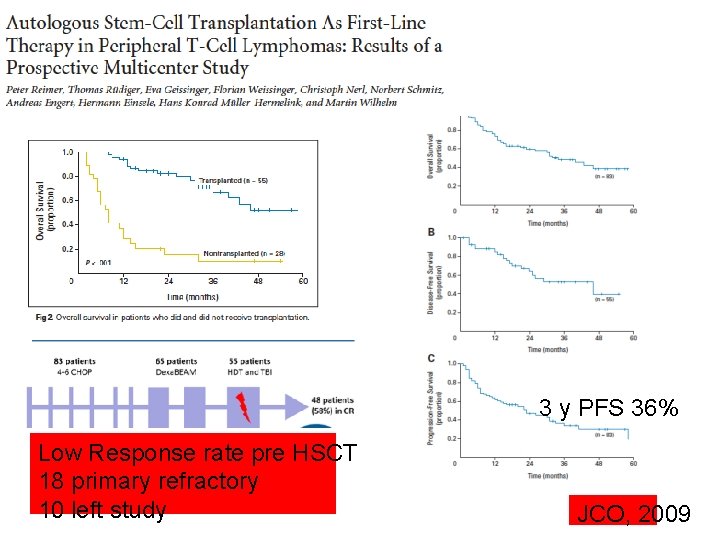
3 y PFS 36% Low Response rate pre HSCT 18 primary refractory 10 left study JCO, 2009
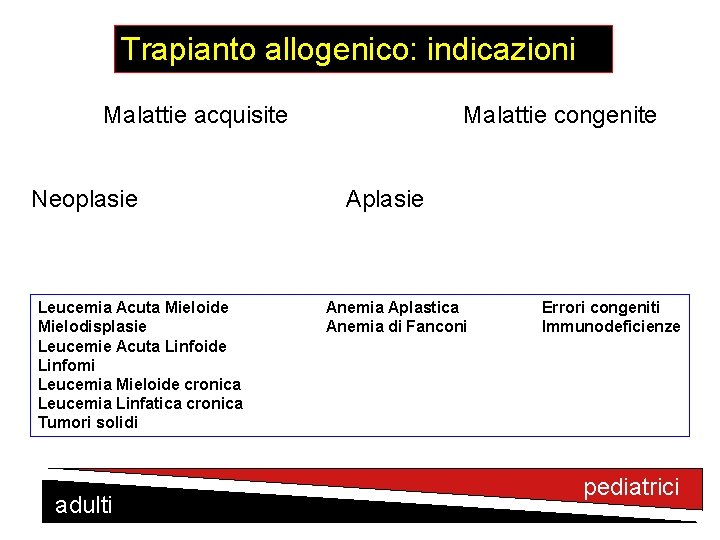
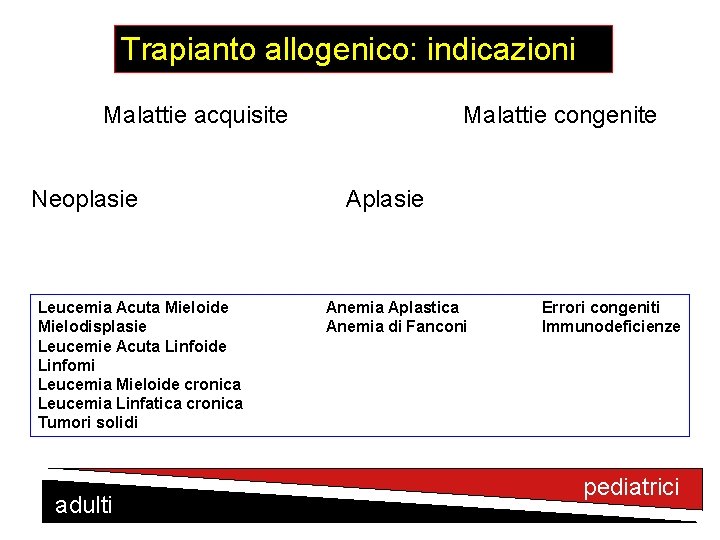
Trapianto allogenico: indicazioni Malattie acquisite Neoplasie Leucemia Acuta Mieloide Mielodisplasie Leucemie Acuta Linfoide Linfomi Leucemia Mieloide cronica Leucemia Linfatica cronica Tumori solidi adulti Malattie congenite Aplasie Anemia Aplastica Anemia di Fanconi Errori congeniti Immunodeficienze pediatrici
Trapianto allogenico: indicazioni Malattie acquisite Neoplasie Leucemia Acuta Mieloide Mielodisplasie Leucemie Acuta Linfoide Linfomi Leucemia Mieloide cronica Leucemia Linfatica cronica Tumori solidi adulti Malattie congenite Aplasie Anemia Aplastica Anemia di Fanconi Errori congeniti Immunodeficienze pediatrici
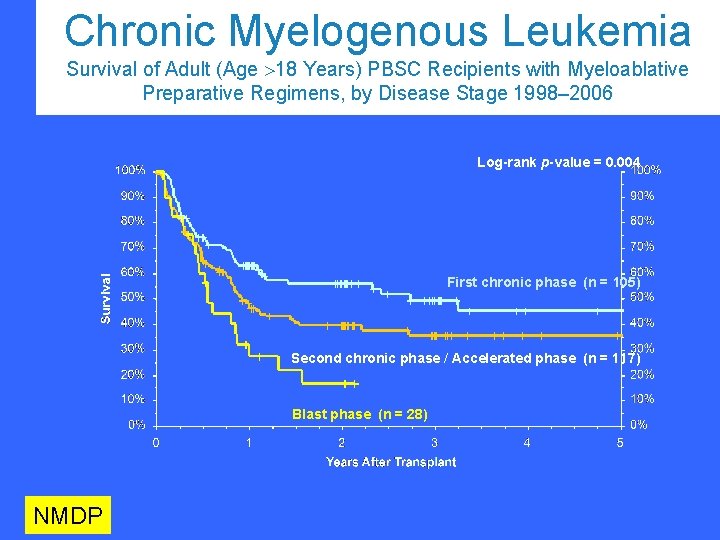
Chronic Myelogenous Leukemia Survival of Adult (Age >18 Years) PBSC Recipients with Myeloablative Preparative Regimens, by Disease Stage 1998– 2006 Log-rank p-value = 0. 004 First chronic phase (n = 105) Second chronic phase / Accelerated phase (n = 117) Blast phase (n = 28) NMDP
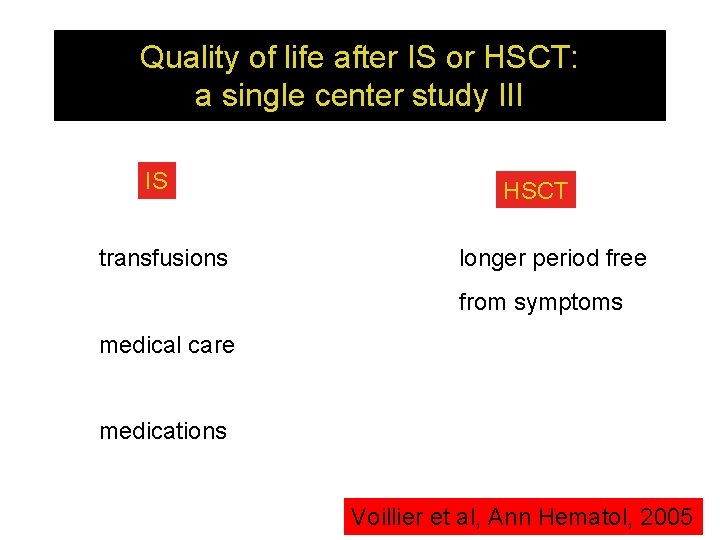
Quality of life after IS or HSCT: a single center study III IS transfusions HSCT longer period free from symptoms medical care medications Voillier et al, Ann Hematol, 2005
13/14 engraft OS 78% EFS 64% TRM 7% GVHD ≥ II 43% GVHD > III 14% BMT, 2014
HSCT from alternative donors for patients with SAA: conclusions • Should be adopted after 1 st line IS failure for patients <50 (for pts >50 consider PS etc) • High resolution HLA typing is mandatory • A 10/10 or 9/10 matched is recommended • Bone Marrow preferred • The unrelated search should be started early
Allo SCT in CML: guideline Allo SCT is no longer recommended as 1 st line treatment in CP (may be in very young pts? ) Allo SCT is an alternative treatment for the following pts: CP if refractory disease Loss of CHR or MCy. R (secondary resistance)?
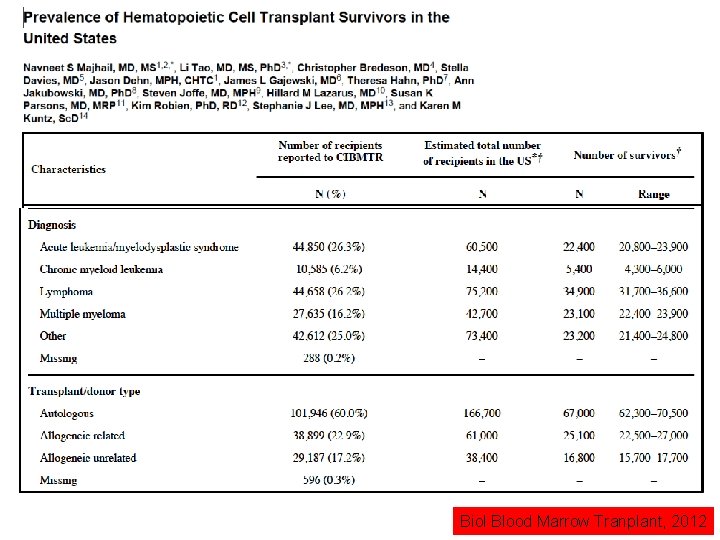
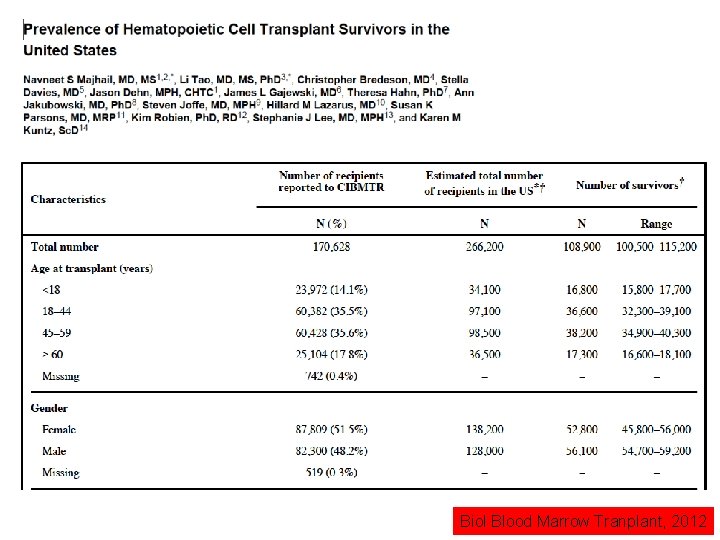
Biol Blood Marrow Tranplant, 2012
For pts transplanted after 2004 and within 2 years: OS 92% Open questions: EBV LPD Graft failure (about 17%) Bacigalupo A, et al, Haematologica, 2010
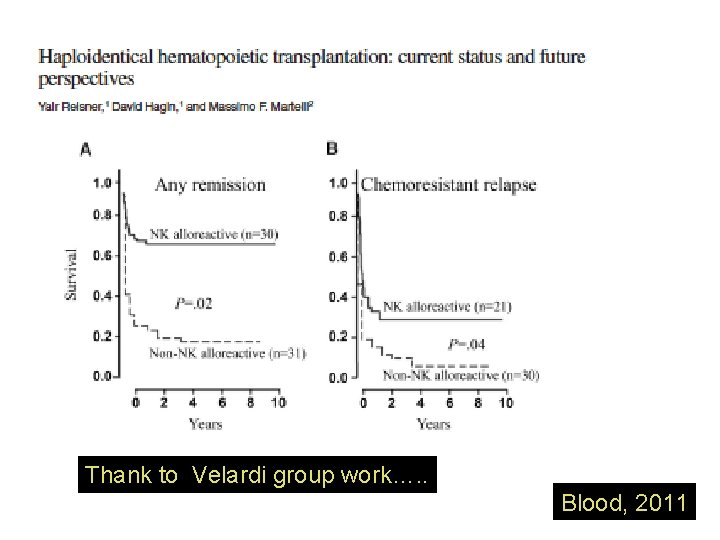
Thank to Velardi group work…. . Blood, 2011
Biol Blood Marrow Tranplant, 2012
JCO, 2012
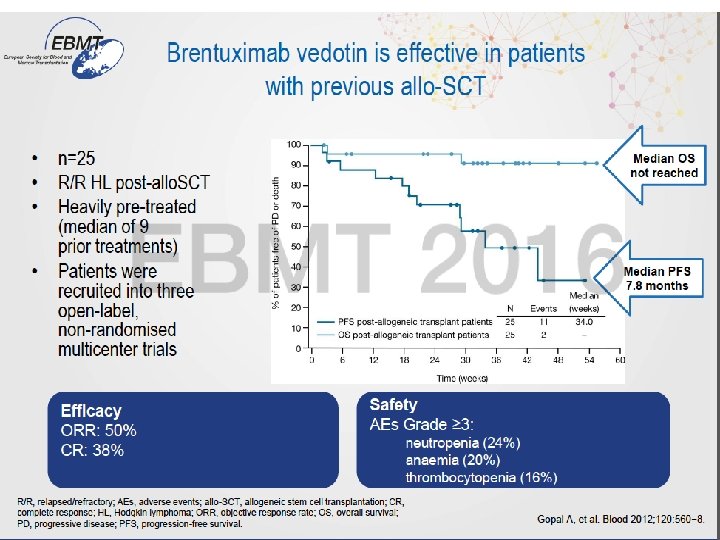
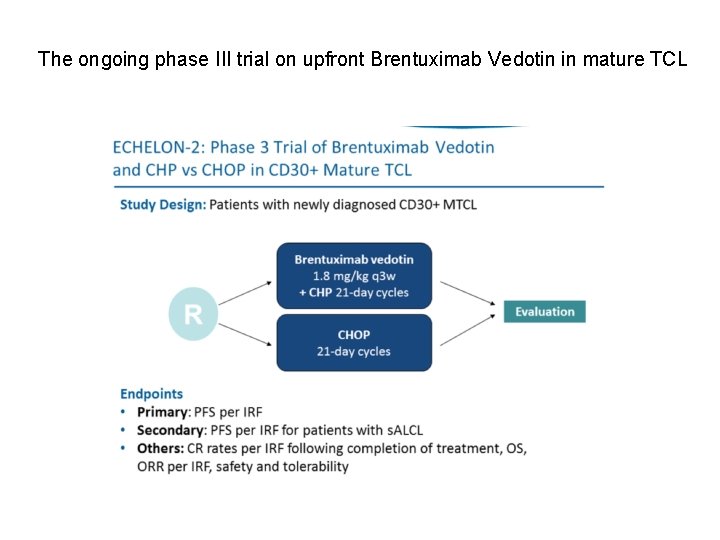
The ongoing phase III trial on upfront Brentuximab Vedotin in mature TCL