
LASIK Complication A AlMuammar LASIK Complication Intraoperative Poor














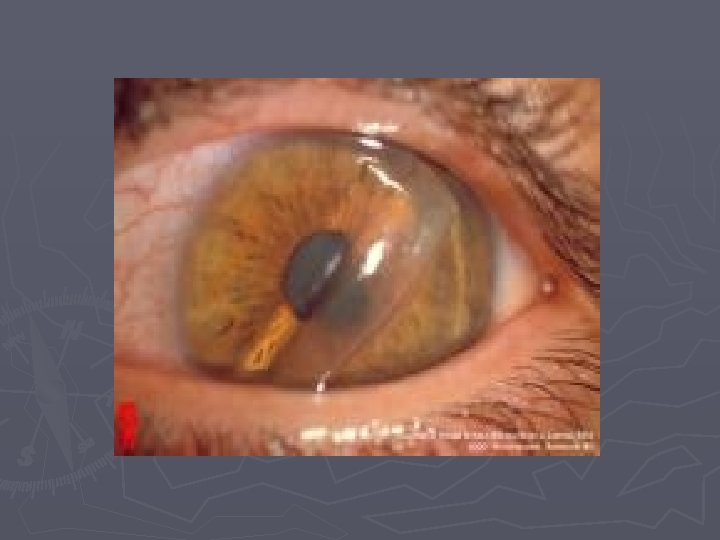
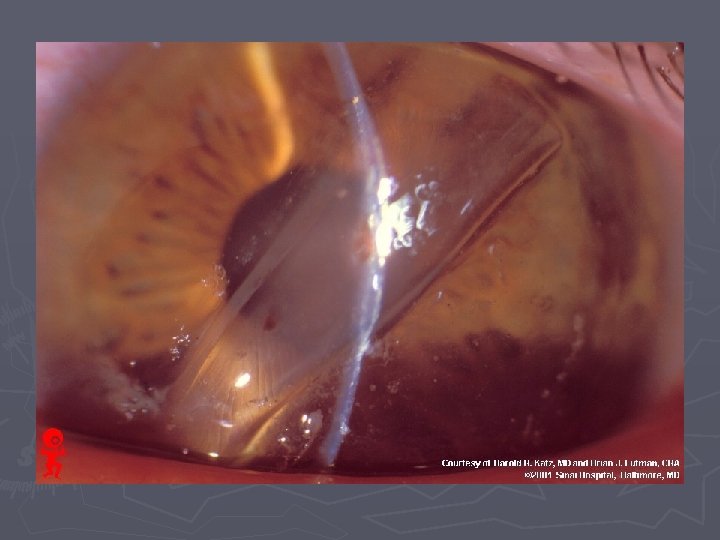

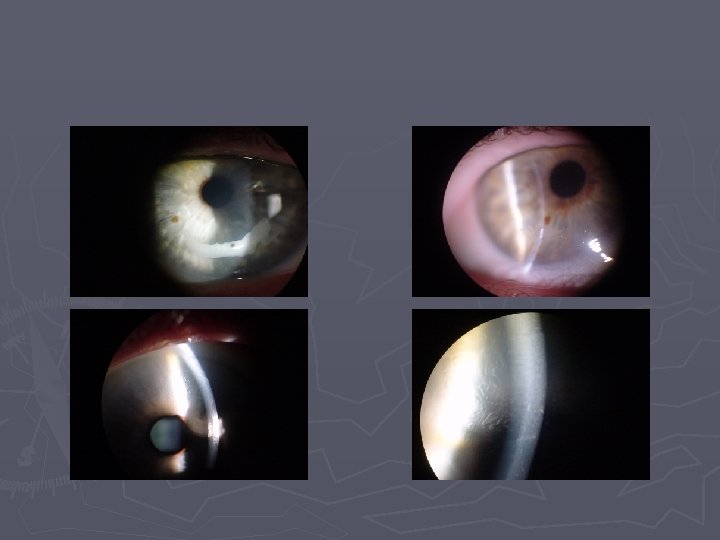


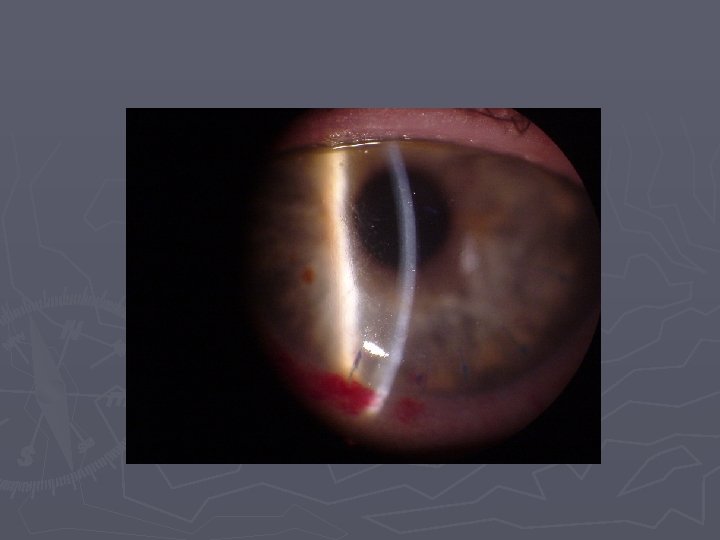







- Slides: 36
LASIK Complication A. Al-Muammar
LASIK Complication Intraoperative § Poor exposure ►Deep orbit, small eye, narrow palpebral fissure, drape, and lid speculum § § Difficulty in placing suction ring Lid injury Poor centration during laser ablation Water pooling ►Lateral canthotomy, facial nerve block, retrobulbar block, converting to PRK, or abandoning surgery
LASIK Complication Intraoperative § Inadequate suction ►Good suction ( IOP > 75 mm. Hg) would provide depth control during microkeratome pass ►Poor or broken suction can result in thin, buttonholes, or free cap ►Inadequate suction can be due to suction ports clogging by debris, drape, speculum, chemotic or redundant conjunctiva, or defect in suction line
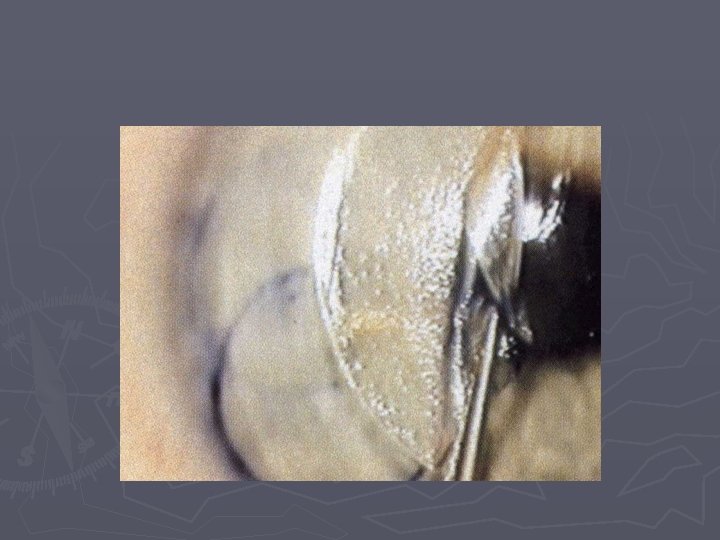
LASIK Complication Intraoperative § Flap complication ►Thin flap § The incidence of thin flap reported to vary between 0. 3% and 0. 75% § Flap considered to be thin when keratome cuts within or above Bowman’s layer § Recognized by shinny reflex on the stromal surface § It tends to occur with flat cornea or poor suction § Reposition the flap and abort the procedure § Deeper flap (20 -60 micrm) maybe recut 10 -12 weeks
LASIK Complication Intraoperative ►Buttonholes flap § A buttonholed flap occurs when microkeratome blade travels more superficially than intended and enters the epithelium/Bowman’s complex § Buttonholes maybe partial thickness if they transect Bowman’s layer or full thickness if they exit through the epithelium. § The incidence of buttonholes ranges between 0. 2% and 0. 56% § Buttonholes flap tend to occurs in case of steep cornea >48 D, resistance to cutting, or lack of synchronization between keratome movement and oscillatory blade movement
LASIK Complication Intraoperative ►Tx § § § Reposition the flap And wait 3 to 6 months before recutting Transepithelial PRK within 2 weeks
LASIK Complication Intraoperative § Irregular flap ►Abnormal shape/diameter/ or thickness flap ►Result from damaged microkeratome blades, irregular oscillation speed, or poor suction ►Incidence 0. 09%-0. 2% ►Reposition the flap and abort the procedure
LASIK Complication Intraoperative ►Incomplete flap § Created when the microkeratome blade comes to halt prior to reaching the intended location of the hinge § Incidence ranges between 0. 3% and 1. 2% § Microkeratome jamming due to either electrical failure or mechanical obstacles as lashes, drape, or loose epithelium § Unless enough space exists for ablation( 1 mm space between ablation and the edge), incomplete flap are best managed by immediate repositioning and postponing the procedure
LASIK Complication Intraoperative ► Free flap § Unintended free flap can occur with corneas flatter than 38 D prior to surgery, poor suction, or migration of suction ring. § Recent studies report an incidence between 0. 01% and 1% § If the flap is not visible on the surface of the cornea, then the flap could be inside the microkeratome head § Marking the cornea prior to surgery is very important for proper placement of free flap § If the cap has normal thickness and diameter, the ablation can still be performed. Flap repositioned using placed marks. A BCL applied to tamponade the cap. Suturing rarely necessary § Abnormal thin/irregular flap which is the usual case should be repositioned using sutures, and laser should be delayed § Early removal of sutures is important to minimize scarring § If the flap cant be retrieved, epithelium is allowed to heal as in PRK
LASIK Complication Intraoperative ►Decentered flap § Flap decenterations are attributable to an inexperienced surgeon improperly aligning the suction ring with the limbus or migration of the ring on the corneal surface when suction applied § Most surgeon will not proceed with laser unless the ablation can be placed 1 mm of the bed is left between the ablation peripheral bed and the flap margin § The Introduction of microkeratome with large diameter flap have reduced this problem
LASIK Complication Intraoperative ►Corneal perforation and anterior segment damage § Result from error in placing the plate that control the depth of the cut into instruments § Newer designs have eliminated the potential for these severe complications since they have a fixed depth plate and components of the microkeratome cannot be inserted incorrectly.
LASIK Complication Intraoperative ►Intraoperative bleeding § Corneal neovascularization from pannus, decentered flap, and large flap are the most common causes of intraoperative bleeding § Topical vasoconstrictors can be applied 3 to 5 minutes prior to surgery in high risk group § Tamponade any bleeding prior to flap lifting § Any blood that might interfere with laser should be irrigated
LASIK Complication postoperative ►Epithelial complication § Incidence reported to be around 5% § Epithelial defects more common in patients with abnormal epithelial adhesion as in EBMD, or patient with who develop epithelial defect in the first eye § Mild staining at the edge of the flap is common § Large defects are worrisome especially those with connection to the flap edge § Epithelial defect can increase the risk of infection, epithelial ingrowth, and DLK § Treated with BCL, or patch
LASIK Complication postoperative ►Pain § Most patients experience only mild discomfort following LASIK § Severe pain may herald more severe complication such as a displaced flap, DLK, or infection
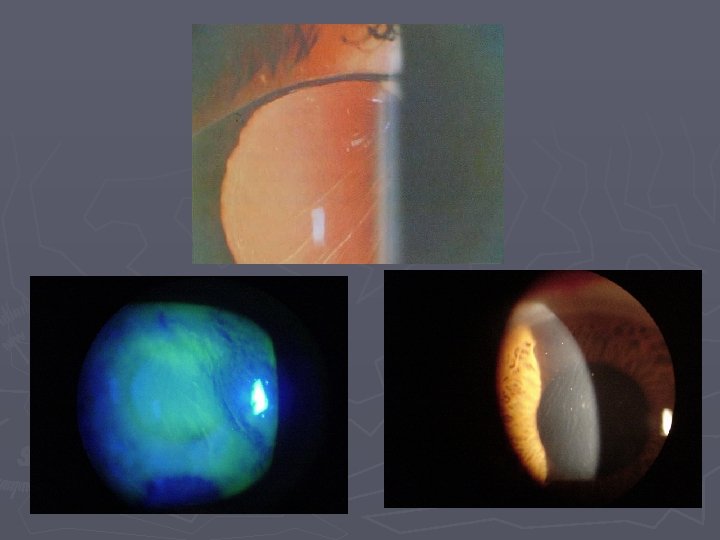
LASIK Complication postoperative ►Flap striae and wrinkles § Reported incidence between 0. 2% and 1. 5% § It is related to the disparity between the curvature of the posterior surface of the flap and the bed following complication § Large thin flap, improper BCL placement, removal of lid speculum, and eye rubbing can increase the risk of striae § Striae can be micro or macro. Retroillumination and fluorescein can help in detecting striae § Visually significant striae should be treated as soon as possible to avoid fixed striae § LASIK flap iron, lifting the flap =/- suture, and PTK are possible options to treat striae
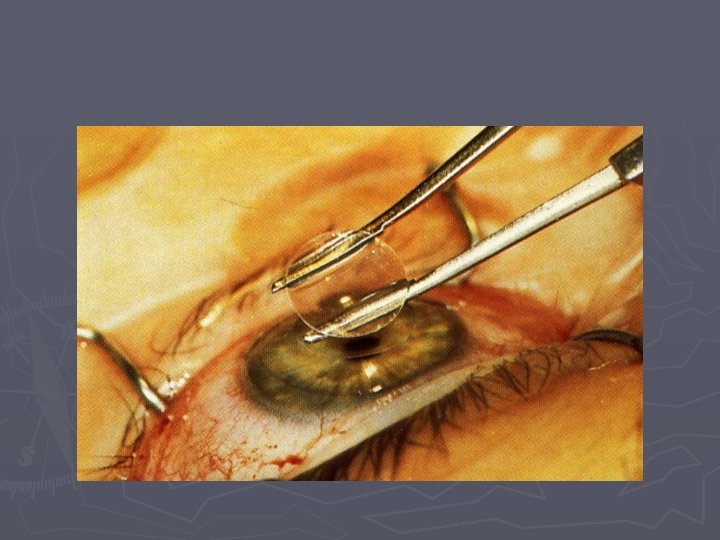
LASIK Complication postoperative ►Displaced flap § Emergency, should be repositioned as soon as possible to prevent infection, fixed folds, and epithelial ingrowth § Incidence have been reported to be 1. 1% and 2% (old reports) § Usually occur in the first 24 hrs after surgery § Eye lid rubbing, squeezing, and trauma especially with large thin flap are the main predisposing factor for displaced flap § Flap should be reflected, examined for epithelial cells or debris which should be scraped, the reposition the flap and apply BCL
LASIK Complication postoperative ►Epithelial ingrowth § Reported incidence vary between 1% and 2% § Possible mechanisms ► Mechanical dragging by keratome blade during keratectomy ► Backflow during irrigation carrying floating epithelial cells ► Ingrowth at the junction of the epithelium and keratotomy ► Implantation with instruments ► Cell migration through epithelial defect
LASIK Complication postoperative § Complications ► Decrease visual acuity ► Anterior stromal melt § Treatment ► Flap lifting ► Irrigation ► Scraping ► Alcohol ► PTK ► MMC ► suture
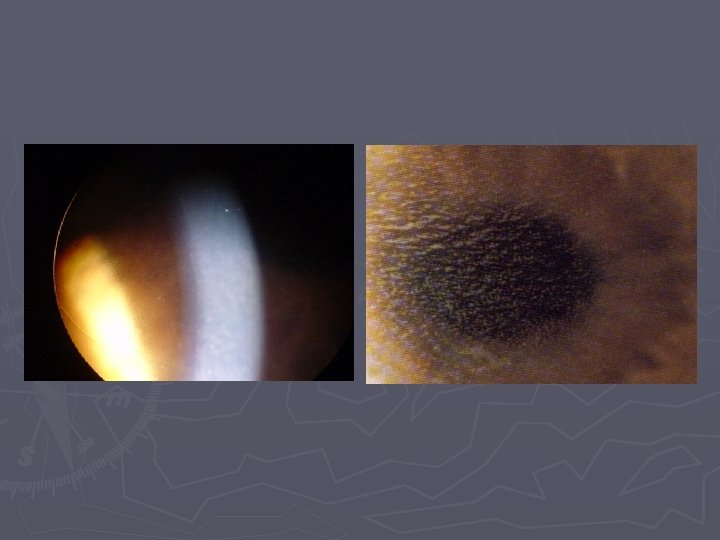
LASIK Complication postoperative ►lamellar interface debris ► Oil ► Mucous ► Particles from the sponge ► Metallic fragments from the Blade ► RBC ► Powder from gloves ► Lint fibres ► Lashes § Peripheral debris which not associated with keratitis or neovascularization can be left undisturbed § Central debris should be removed
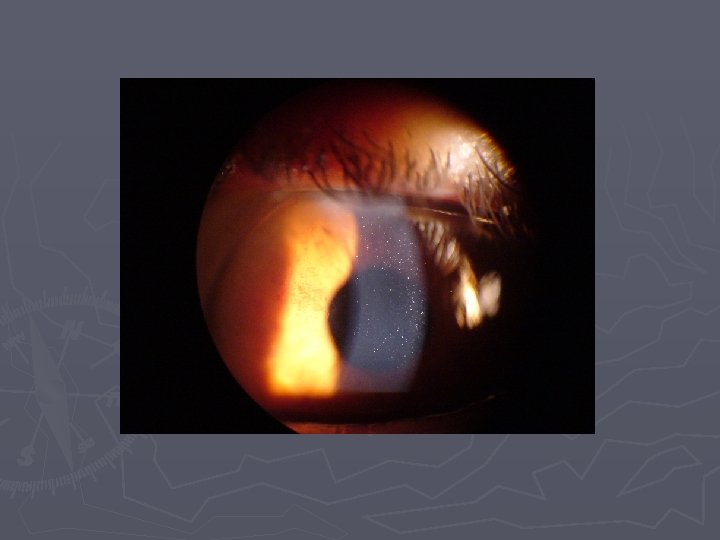
LASIK Complication postoperative ► Diffuse Lamellar Keratitis (DLK) § Diffuse non-infectious inflammation at the level of the interface during the first few days after LASIK § Reported incidence is highly variable, between 0. 2% and 3. 2% § Possible causes, most of these are based on speculation without supporting data ► Betadine ► Impure BSS ► Retained meibomian secretions ► Metallic debris ► Talc from gloves ► Thermal effect from the laser ► Lubricants on the microkeratome or blades ► Topical medications such as anesthetics ► Bacterial cell wall components (lipopolysaccharides) ► Endotoxins ► IL 1 released from corneal epithelial cells following cell injury or death
LASIK Complication postoperative § Stages ► Stage I seen on day 1 as white, granular cells in the periphery with sparing of the visual axis. ► Stage II seen on day 2 or 3, shows white cells in the visual axis ► Stage III involves an aggregation of cells clumped in the visual axis and associated with haze and reduce vision ► Stage IV involves central stromal necrosis, melt, and secondary hyperopia with irregular astigmatism
LASIK Complication postoperative ►Tx § Stage I and II, should be treated with intense topical steroid every 1 hr § If inflammation progressed even with steroid or patient presented with stage III or IV ► the flap should be lifted ► Cleaning ► profuse irrigation ► Culture for bacteria and fungus ► Topical steroid =/- oral steroid ► PTK/HCL
LASIK Complication postoperative ► Infection § Infectious agents that have been reported after LASIK include ► Virus ► Bacteria (including atypical mycobacterium and nocardia) ► Fungus ► Parasite § If infiltrate noted, it should be treated as infectious until proven otherwise § Infiltrate should be cultured …bacteria, fungus, acanthameoba, Ziehle-Nelson stain § Tx ► Abx ► Antifungal ► Antiviral ► Flap removal
LASIK Complication postoperative ►Dry eye § Neurotrophic in origin § Worse in patient who are known to have dry eye § Present with PEE and visual fluctuation § May last 6 to 8 months § Tx ► Tears ► Punctum plug
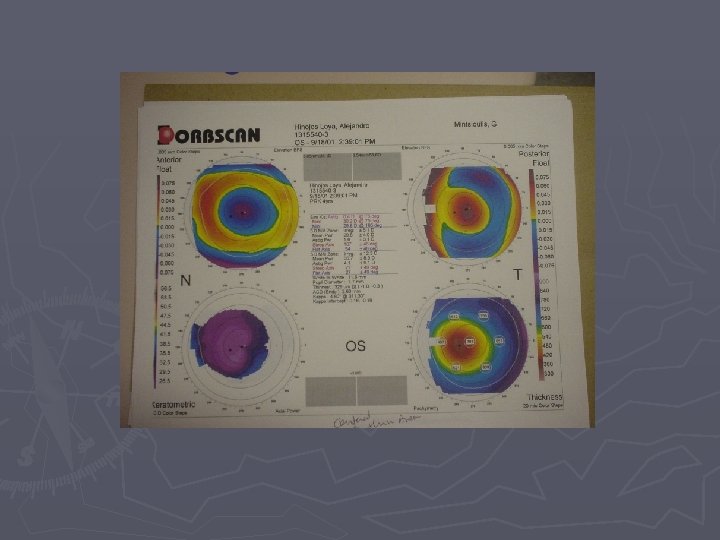
LASIK Complication postoperative ► Corneal ectasia Iatrogenic keratoconus like condition Minimum stromal bed thickness of 250 -300 microm should be left after laser ablation § Present as progressive myopia, or decrease visual acuity secondary to irregular astigmatism § Dx ► Orbscan ► Pachymetry § § § Tx ► RCL ► Corneal ► PKP ring
LASIK Complication psotoperative § Decentration § Irregular astigmatism § Glare, and haloes § Overcorrection § Undercorrection