
Laparoscopic Resection of Unruptured Tubal Pregnancy By Carly

Laparoscopic Resection of Unruptured Tubal Pregnancy By Carly Winegar

Anatomy Fallopian tubes Fimbriae Infundibulum Ampulla Isthmus Intramural Mesosalpinx
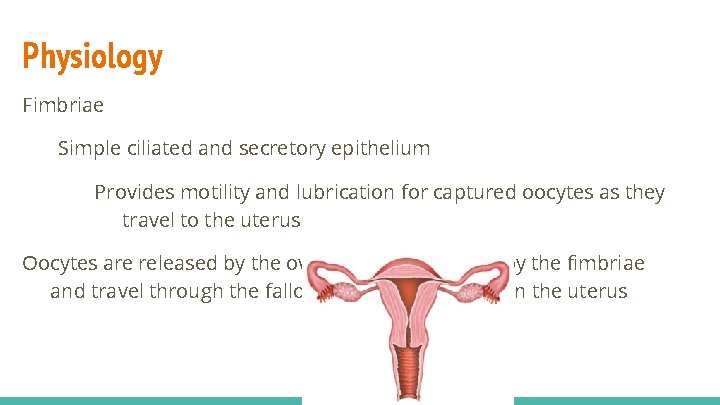
Physiology Fimbriae Simple ciliated and secretory epithelium Provides motility and lubrication for captured oocytes as they travel to the uterus Oocytes are released by the ovaries and are caught by the fimbriae and travel through the fallopian tubes to implant in the uterus
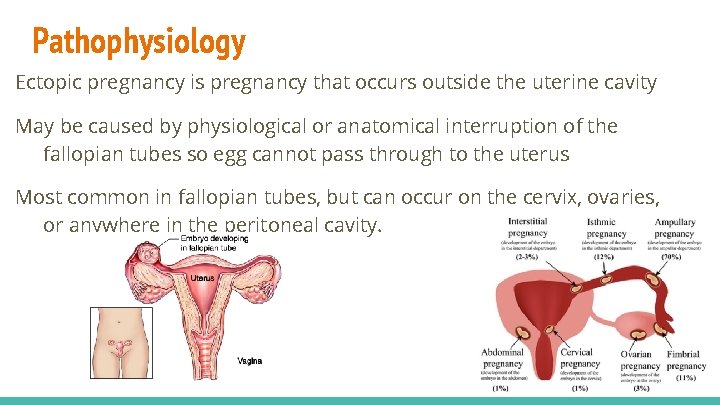
Pathophysiology Ectopic pregnancy is pregnancy that occurs outside the uterine cavity May be caused by physiological or anatomical interruption of the fallopian tubes so egg cannot pass through to the uterus Most common in fallopian tubes, but can occur on the cervix, ovaries, or anywhere in the peritoneal cavity.
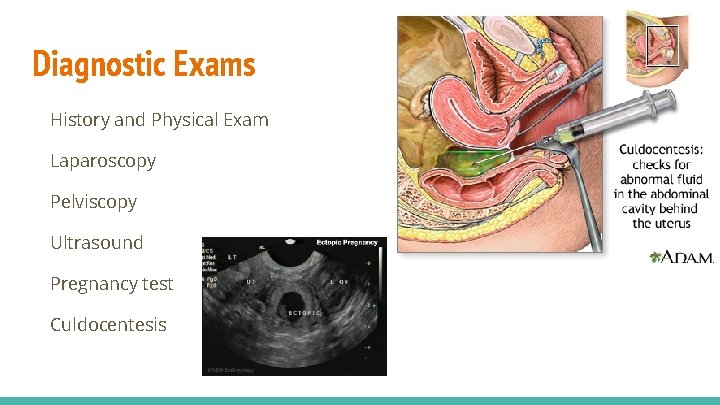
Diagnostic Exams History and Physical Exam Laparoscopy Pelviscopy Ultrasound Pregnancy test Culdocentesis
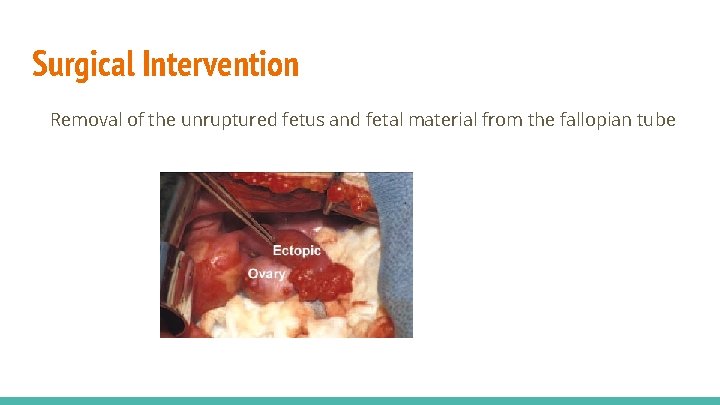
Surgical Intervention Removal of the unruptured fetus and fetal material from the fallopian tube
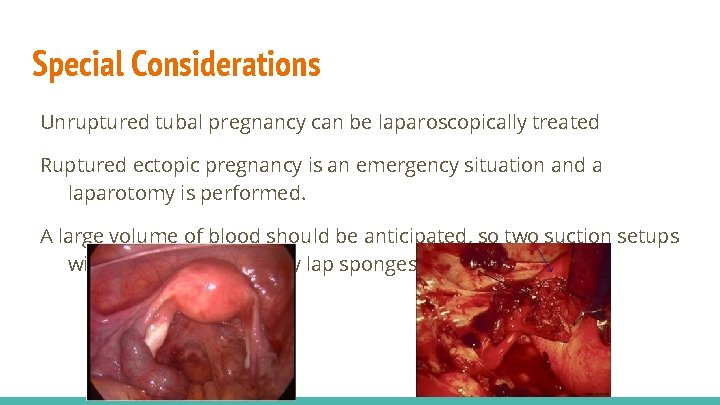
Special Considerations Unruptured tubal pregnancy can be laparoscopically treated Ruptured ectopic pregnancy is an emergency situation and a laparotomy is performed. A large volume of blood should be anticipated, so two suction setups will be needed and many lap sponges

Anesthesia General
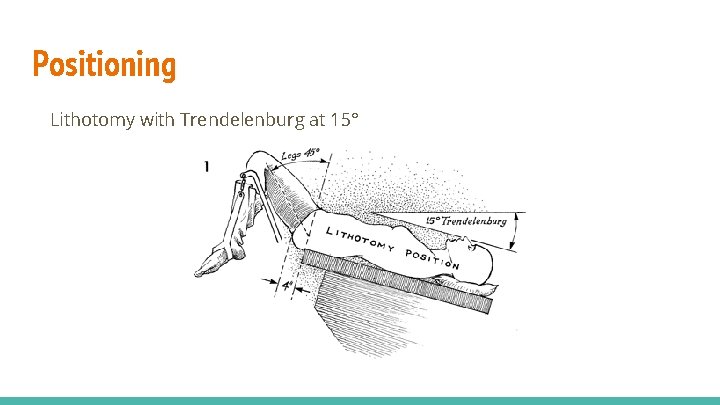
Positioning Lithotomy with Trendelenburg at 15°

Skin Prep Abdominal including vaginal prep Begin cleansing at the umbilicus, extending the prep from nipples to the mid-thighs. Continue over the labia, discarding each sponger after wiping the labia. Cleanse each inner thigh and discard the sponge. Prep the vaginal vault and cervix (as for D&C) using three spongesticks Perineum and anus are prepared last; discard
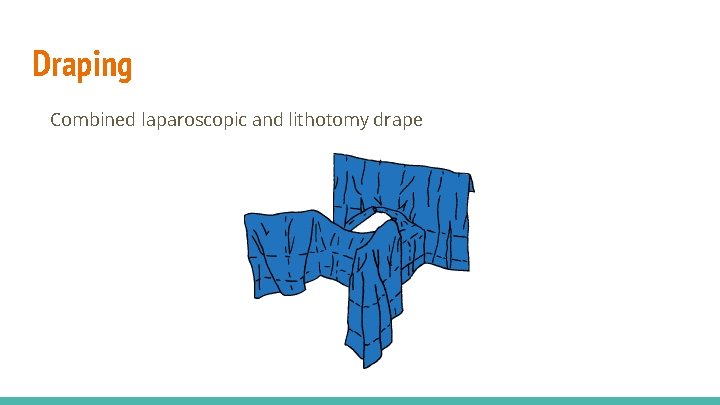
Draping Combined laparoscopic and lithotomy drape
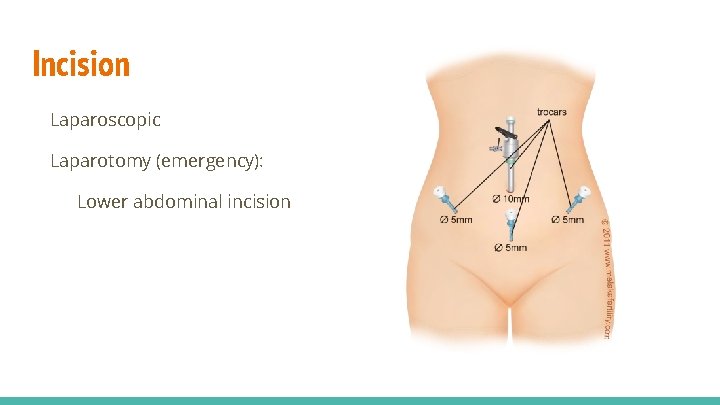
Incision Laparoscopic Laparotomy (emergency): Lower abdominal incision

Supplies Suction tubing Blades Perineal pad Bovie cord and tip Insufflation Tubing Sponges and dressing material
Equipment Laparoscopic equipment Suction Electrosurgical unit Sequential Compression Device Padded Stirrups Light Source CO 2 Insufflator

Instruments Laparoscopic Instrumentation Major laparotomy set Vaginal hysterectomy set D&C set Verres needle Trocars Camera
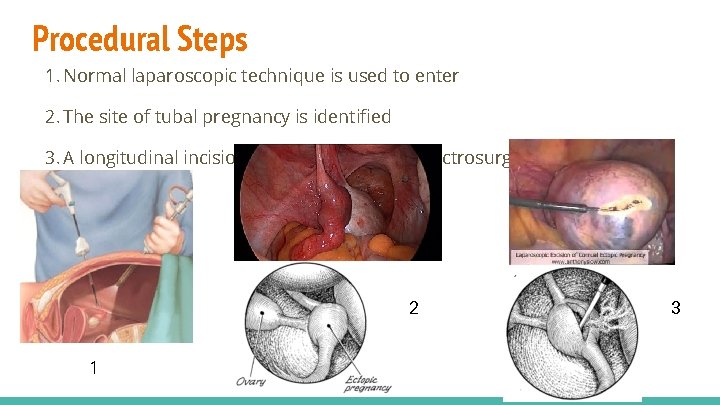
Procedural Steps 1. Normal laparoscopic technique is used to enter 2. The site of tubal pregnancy is identified 3. A longitudinal incision is made in the tube electrosurgically 2 1 3
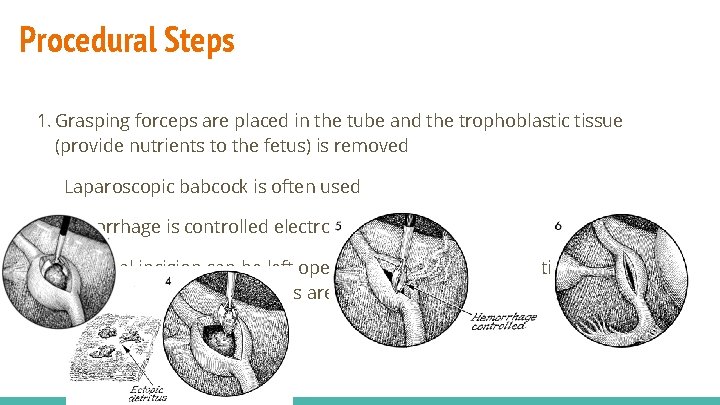
Procedural Steps 1. Grasping forceps are placed in the tube and the trophoblastic tissue (provide nutrients to the fetus) is removed Laparoscopic babcock is often used 2. Hemorrhage is controlled electrosurgically 3. The tubal incision can be left open to heal by second intention or fibrin glue is applied or fine sutures are placed
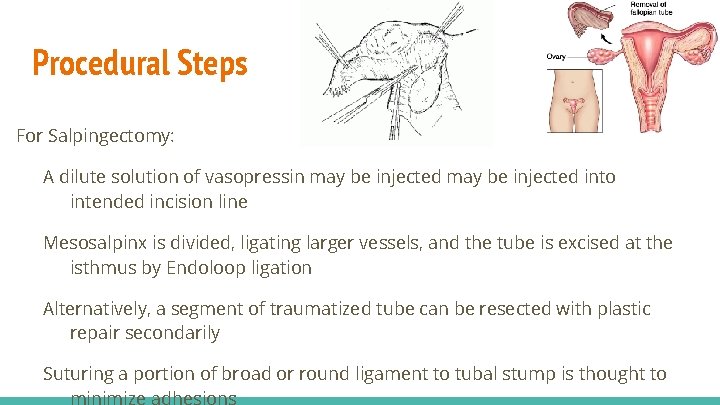
Procedural Steps For Salpingectomy: A dilute solution of vasopressin may be injected into intended incision line Mesosalpinx is divided, ligating larger vessels, and the tube is excised at the isthmus by Endoloop ligation Alternatively, a segment of traumatized tube can be resected with plastic repair secondarily Suturing a portion of broad or round ligament to tubal stump is thought to
Procedural Steps Peritoneal cavity is irrigated and blood and tissue debris are aspirated Pneumoperitoneum is released and the incisions are closed

Counts Initial Count when closing pelvic cavity Final Count
Dressing Material Band Aids or steri strip dressings applied Perineal pad placed
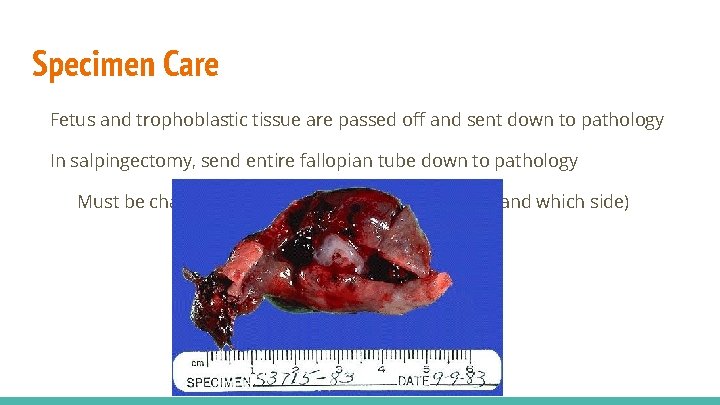
Specimen Care Fetus and trophoblastic tissue are passed off and sent down to pathology In salpingectomy, send entire fallopian tube down to pathology Must be charted that fallopian tube was removed (and which side)

Prognosis PACU should be aware of psychological grief associated with the loss of the fetus that can alter vital signs (heart rate, respiration rate, etc. ) If no complications, discharged in 1 -2 days Return to normal activities in 4 -6 weeks

Complications Postop SSI Hemorrhage Increased risk of future ectopic pregnancy Death

Wound Class/ Management Class II: Clean Contaminated

Tuboplasty
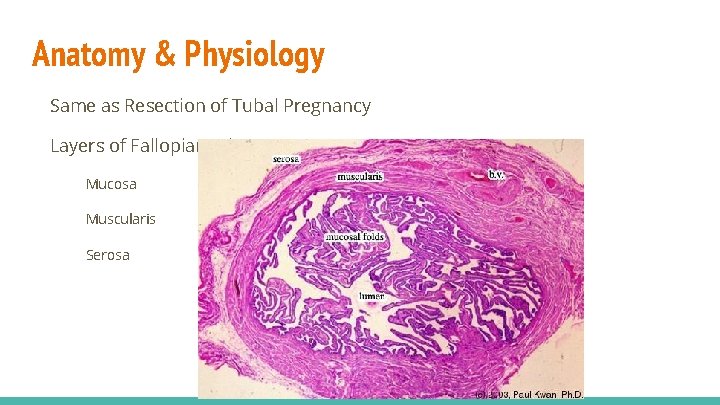
Anatomy & Physiology Same as Resection of Tubal Pregnancy Layers of Fallopian tubes Mucosa Muscularis Serosa
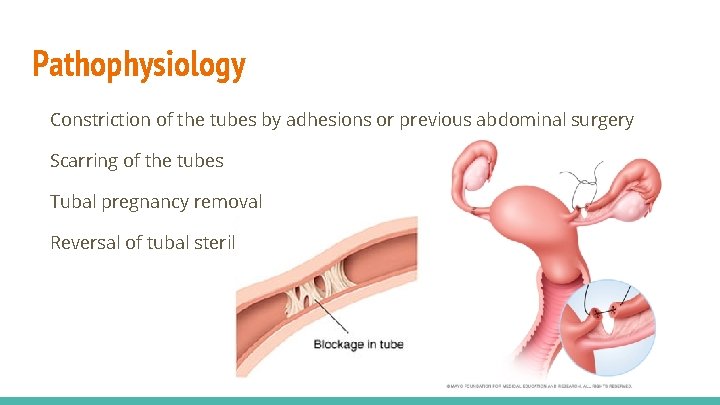
Pathophysiology Constriction of the tubes by adhesions or previous abdominal surgery Scarring of the tubes Tubal pregnancy removal Reversal of tubal sterilization
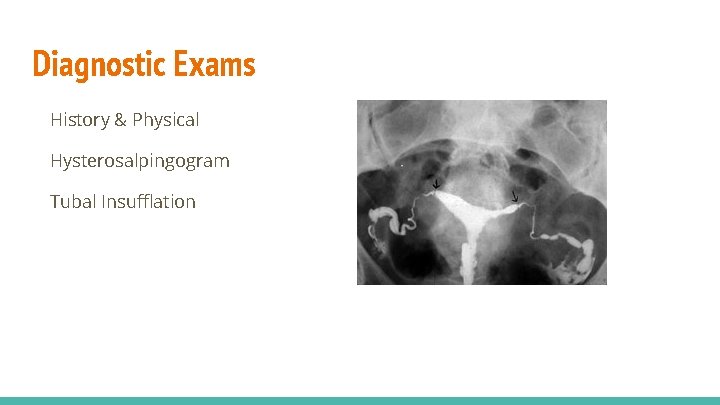
Diagnostic Exams History & Physical Hysterosalpingogram Tubal Insufflation
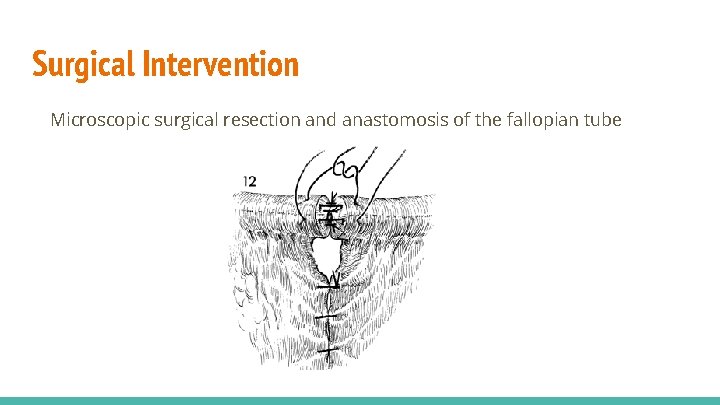
Surgical Intervention Microscopic surgical resection and anastomosis of the fallopian tube

Special Considerations Have diagnostic studies in OR Be familiar with microsurgical instruments that are used in procedure Surgeon and surgical assistant are looking through a microscope, so place instruments into their hands carefully and precisely. Do not pass instruments under the microscope lens
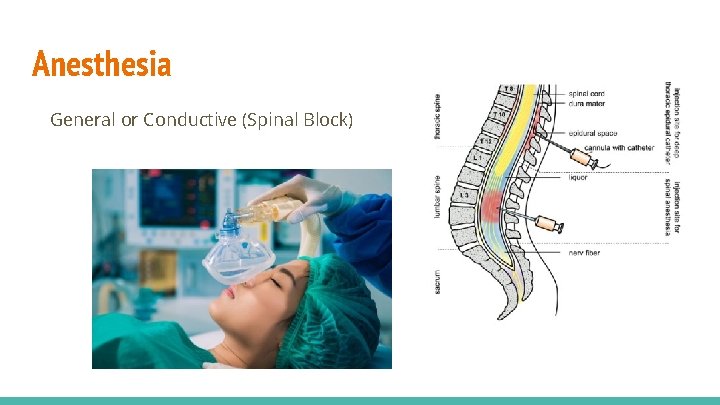
Anesthesia General or Conductive (Spinal Block)
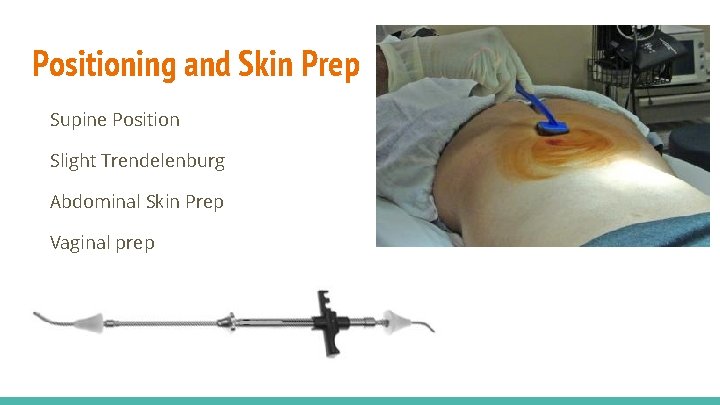
Positioning and Skin Prep Supine Position Slight Trendelenburg Abdominal Skin Prep Vaginal prep Cervical Cannula placed

Draping Laparotomy drape Drape the microscope
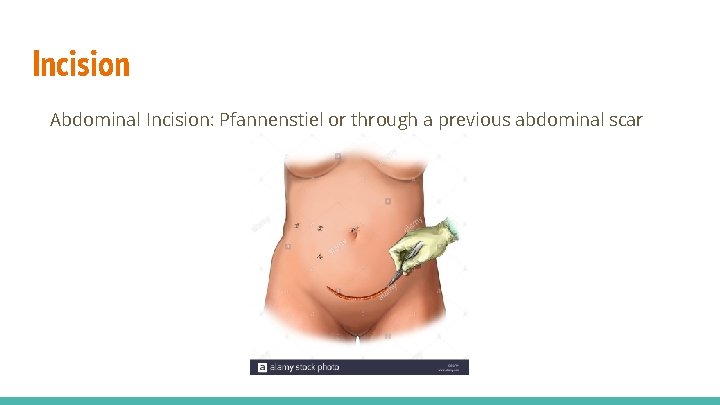
Incision Abdominal Incision: Pfannenstiel or through a previous abdominal scar

Supplies Microscope drape Microsurgical sutures of surgeon’s preference Indigo carmine dye Variety of syringes, needles and injection catheters Basin set Blades Suction tubing

Equipment Operating microscope Laparoscopy equipment, instrumentation and supplies for laparoscopic approach Sequential Compression Device Suction ESU

Instruments Microsurgical instruments Lacrimal duct probes Eye forceps Castroviejo needle holder Iris Scissors Bipolar coagulating forceps Electrosurgery needle tip
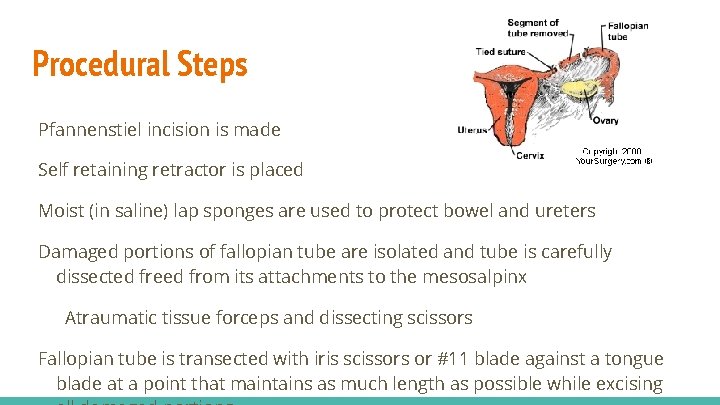
Procedural Steps Pfannenstiel incision is made Self retaining retractor is placed Moist (in saline) lap sponges are used to protect bowel and ureters Damaged portions of fallopian tube are isolated and tube is carefully dissected freed from its attachments to the mesosalpinx Atraumatic tissue forceps and dissecting scissors Fallopian tube is transected with iris scissors or #11 blade against a tongue blade at a point that maintains as much length as possible while excising
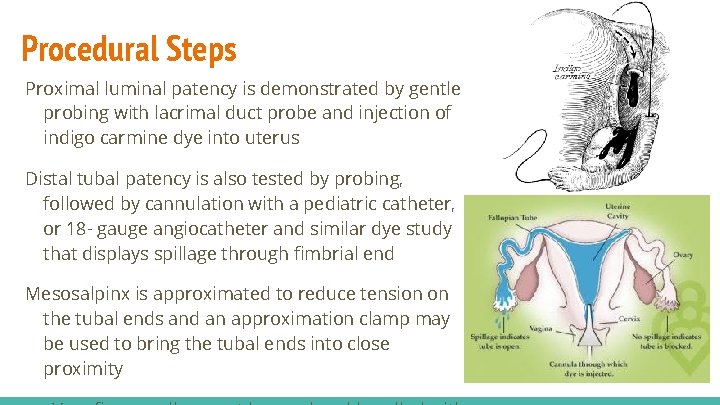
Procedural Steps Proximal luminal patency is demonstrated by gentle probing with lacrimal duct probe and injection of indigo carmine dye into uterus Distal tubal patency is also tested by probing, followed by cannulation with a pediatric catheter, or 18 - gauge angiocatheter and similar dye study that displays spillage through fimbrial end Mesosalpinx is approximated to reduce tension on the tubal ends and an approximation clamp may be used to bring the tubal ends into close proximity

Procedural Steps 2 -0 monofilament suture may be threaded through the lumen to assist with approximation and protection of it The sections of tube are sutured together at the 3 -, 6 -, and 9 -o’clock positions with interrupted 8 -0 synthetic absorbable suture Sutures are placed in muscularis only- no suture material should pass through the mucosa of the tube The 2 -0 monofilament stent is removed and a similar suture is passed at the 12 - o’clock position
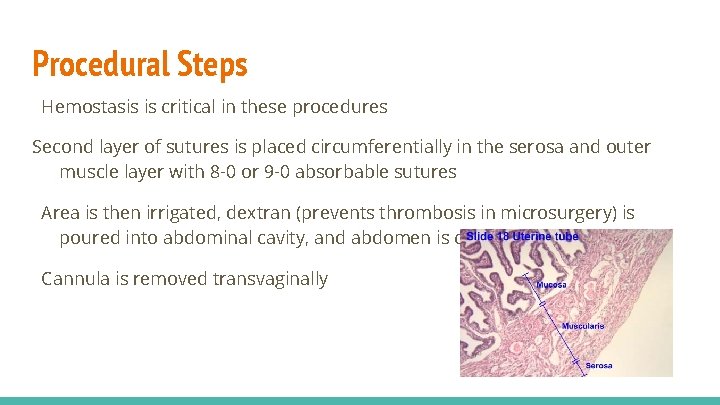
Procedural Steps Hemostasis is critical in these procedures Second layer of sutures is placed circumferentially in the serosa and outer muscle layer with 8 -0 or 9 -0 absorbable sutures Area is then irrigated, dextran (prevents thrombosis in microsurgery) is poured into abdominal cavity, and abdomen is closed. Cannula is removed transvaginally

Counts Initial Closing pelvic cavity Final

Dressing Material Sanitary napkin belt or T-binder Perineal Pad is placed

Specimen Care No specimen unless portions of fallopian tube need to be removed because of blockage or damage Send specimens to pathology

Prognosis No complications: Discharged same day of surgery or the next day Return to normal activities in 4 -6 weeks Successful potential to become pregnant

Complications Postop SSI Hemorrhage Ectopic pregnancy Continued infertility Abdominal Adhesions Death

Wound Class/ Management Class I: Clean

Works Cited http: //www. atlasofpelvicsurgery. com/6 Fallopian. Tubesand. Ovaries/4 Laparosco pic. Resectionof. Unruptured. Ectopic. Pregnancy/chap 6 sec 4. html https: //www. ncbi. nlm. nih. gov/pmc/articles/PMC 1477156/ http: //www. histology. leeds. ac. uk/female/oviduct. php https: //medlineplus. gov/ency/article/000895. htm https: //medlineplus. gov/ency/article/002916. htm https: //www. plannedparenthood. org/learn/pregnancy/ectopic-pregnancy
- Slides: 49