
Lab 4 Renal Function test RFT Khadija Balubaid
Lab (4): Renal Function test (RFT) Khadija Balubaid KAU-Faculty of Science- Biochemistry department Clinical biochemistry lab (Bioc 416) 2013

The Function of Urinary System 1. Excretion & Elimination: ( major function) removal of organic wastes products from body fluids (urea, creatinine, uric acid) 2. Homeostatic regulation: a. Water -Salt Balance(Regulates the body balance in water and minerals. (sodium, potassium, chloride, calcium and phosphate) b. Acid - base Balance(Maintains blood volume, pressure and p. H. ) 3. Endocrine function: produce hormones (erythropoietin, renin and prostaglandin).
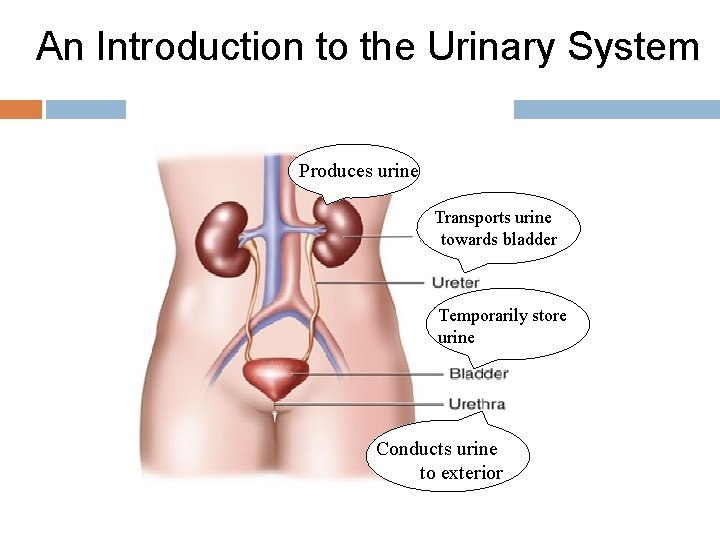
An Introduction to the Urinary System Produces urine Transports urine towards bladder Temporarily store urine Conducts urine to exterior
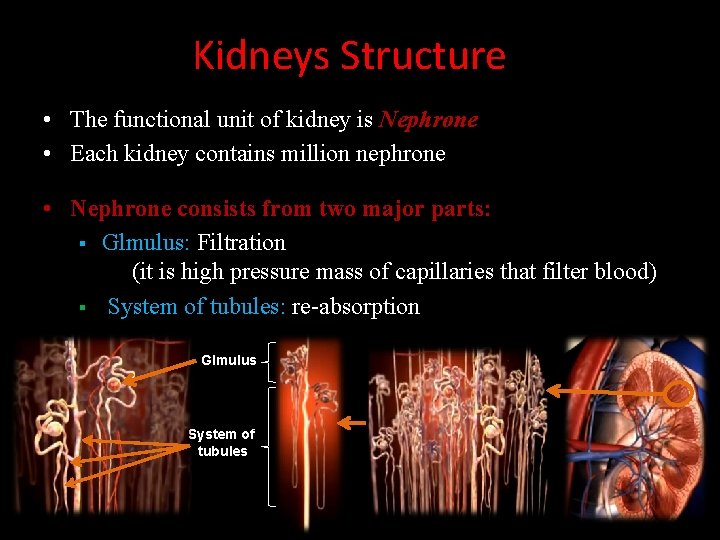
Kidneys Structure • The functional unit of kidney is Nephrone • Each kidney contains million nephrone • Nephrone consists from two major parts: § Glmulus: Filtration (it is high pressure mass of capillaries that filter blood) § System of tubules: re-absorption Glmulus System of tubules
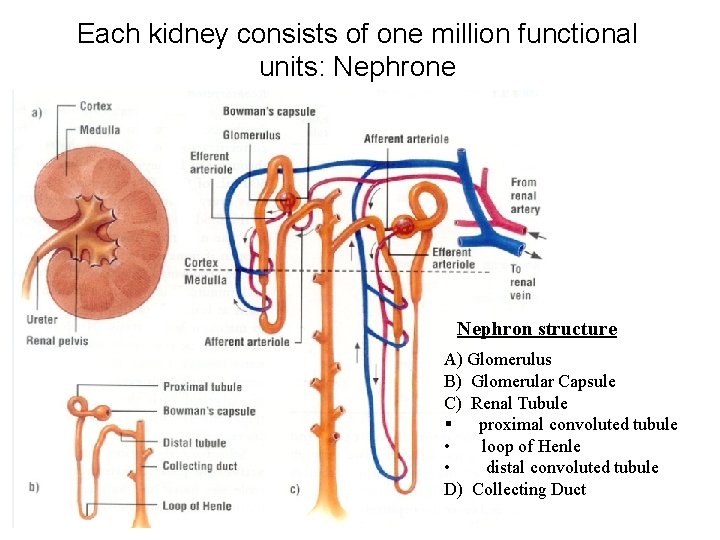
Each kidney consists of one million functional units: Nephrone Nephron structure A) Glomerulus B) Glomerular Capsule C) Renal Tubule § proximal convoluted tubule • loop of Henle • distal convoluted tubule D) Collecting Duct
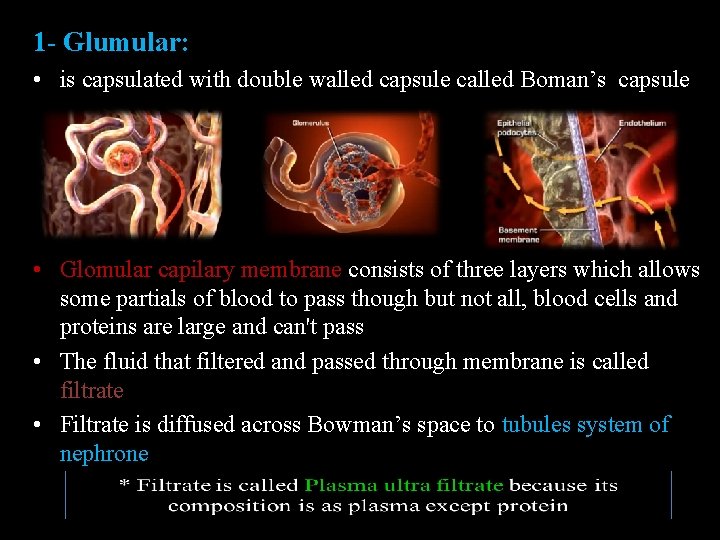
1 - Glumular: • is capsulated with double walled capsule called Boman’s capsule • Glomular capilary membrane consists of three layers which allows some partials of blood to pass though but not all, blood cells and proteins are large and can't pass • The fluid that filtered and passed through membrane is called filtrate • Filtrate is diffused across Bowman’s space to tubules system of nephrone

What gets filtered in the glomerulus ? Freely filtared (filterd = passed) • H 2 O • Elements : (Na+, K+, Cl-, Mg 2+ , PO 4) • Glucose • Urea • Creatinine • Insulin Not filtred (not passed) • Protein • Blood cells
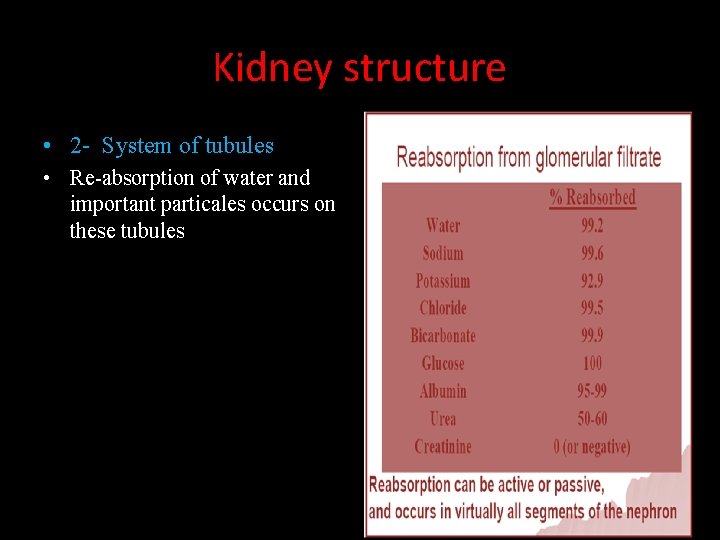
Kidney structure • 2 - System of tubules • Re-absorption of water and important particales occurs on these tubules
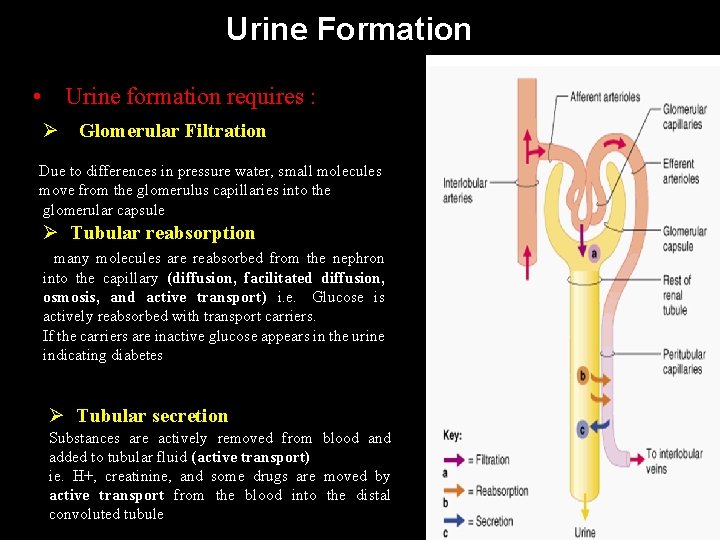
Urine Formation • Urine formation requires : Ø Glomerular Filtration Due to differences in pressure water, small molecules move from the glomerulus capillaries into the glomerular capsule Ø Tubular reabsorption many molecules are reabsorbed from the nephron into the capillary (diffusion, facilitated diffusion, osmosis, and active transport) i. e. Glucose is actively reabsorbed with transport carriers. If the carriers are inactive glucose appears in the urine indicating diabetes Ø Tubular secretion Substances are actively removed from blood and added to tubular fluid (active transport) ie. H+, creatinine, and some drugs are moved by active transport from the blood into the distal convoluted tubule
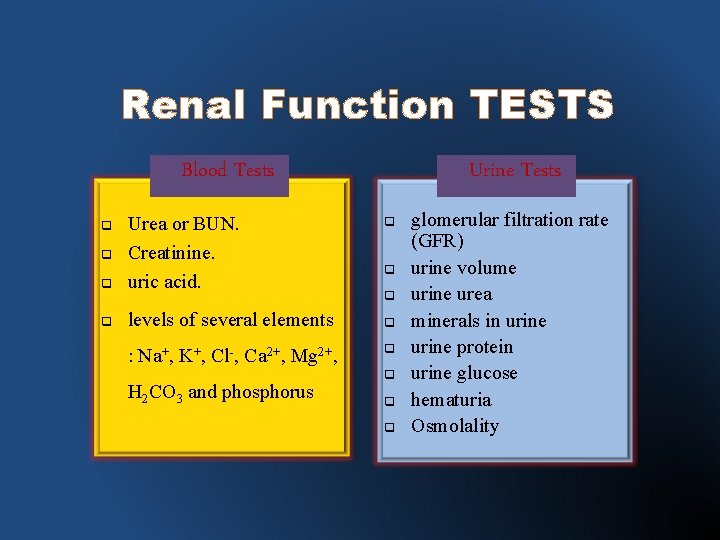
Renal Function TESTS Blood Tests q Urea or BUN. Creatinine. uric acid. q levels of several elements q q : Na+, K+, Cl-, Ca 2+, Mg 2+, H 2 CO 3 and phosphorus Urine Tests q q q q glomerular filtration rate (GFR) urine volume urine urea minerals in urine protein urine glucose hematuria Osmolality
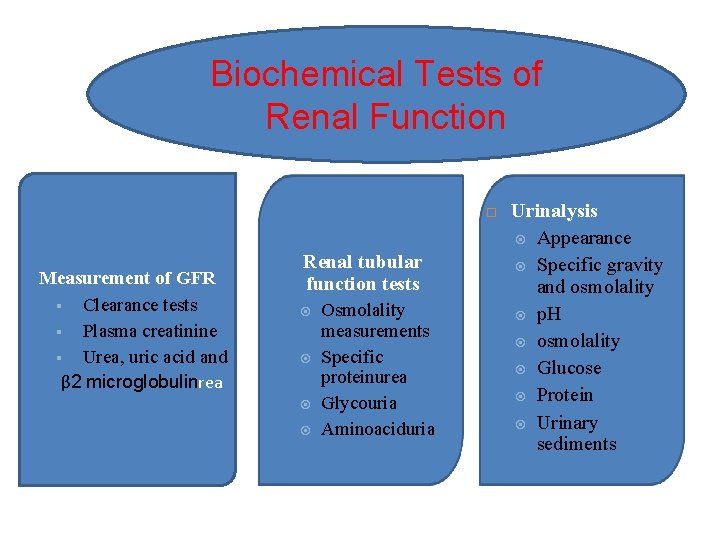
Biochemical Tests of Renal Function Measurement of GFR § Clearance tests § Plasma creatinine § Urea, uric acid and β 2 microglobulinrea Renal tubular function tests Osmolality measurements Specific proteinurea Glycouria Aminoaciduria Urinalysis Appearance Specific gravity and osmolality p. H osmolality Glucose Protein Urinary sediments
• Many factors can affect on kidney function leads to kidney damage; Ø Ø Ø Anatomical structure (congenital disease) Infections Diabetes Renal stones Smoking Diet and water v Most common causes : Diabetes and high blood pressure • Kidney damage occurs in stages that can early detected. • Abnormal results of kidney function tests may be obtained due to a temporary renal dysfunction. • Therefore, the test should be performed repeatedly and interpreted on the basis of a series of results.
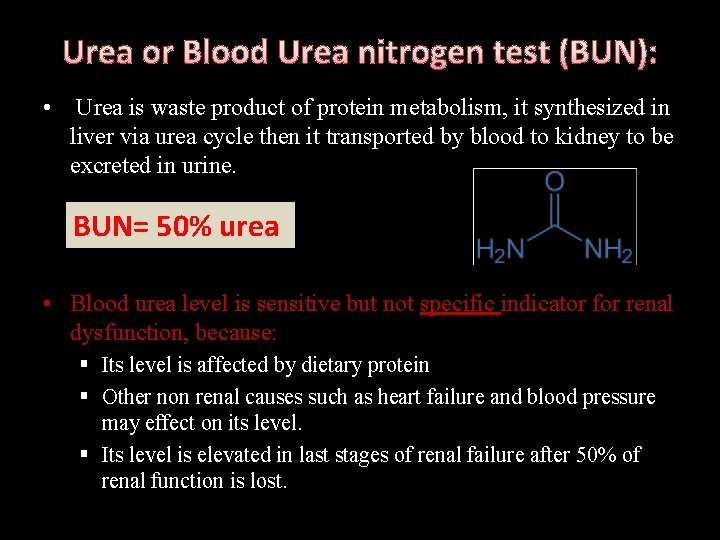
Urea or Blood Urea nitrogen test (BUN): • Urea is waste product of protein metabolism, it synthesized in liver via urea cycle then it transported by blood to kidney to be excreted in urine. BUN= 50% urea • Blood urea level is sensitive but not specific indicator for renal dysfunction, because: § Its level is affected by dietary protein § Other non renal causes such as heart failure and blood pressure may effect on its level. § Its level is elevated in last stages of renal failure after 50% of renal function is lost.

High serum urea can indicates: • Renal insufficiency. (due to obstruction or cancer) • Urinary tract blockage (by a kidney stone or tumor) • Heart failure (poor renal perfusion: low blood flow to kidney). • Dehydration (lack of fluid volume to excrete waste products). • High-protein diet • Some medicines. Low serum urea may be due to: • Very low protein diet as in malnutrition • Severe liver damage inhibits urea cycle, decrease urea formation and increase free ammonia leads to hepatic comma. • Overhydration.

Uric acid: • Is the end product of purine metabolism and excreted in urine. • Purine in body comes from food and break down of body cells. • Elevated level of uric acid in blood is one of the markers of kidney dysfunction.
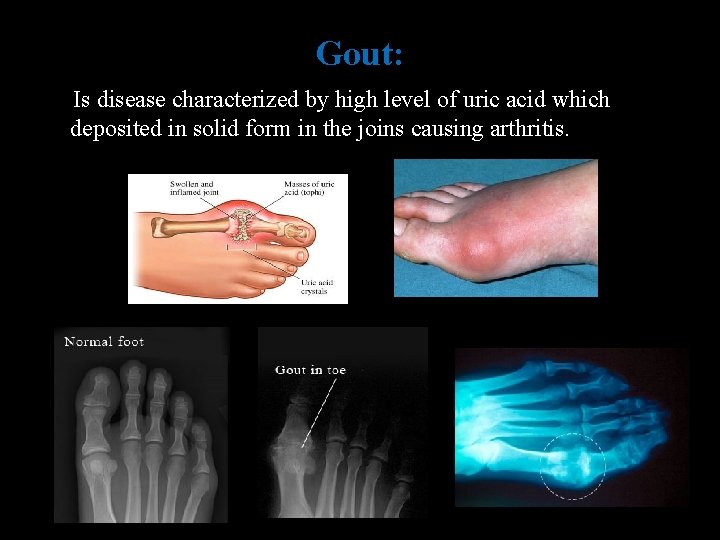
Gout: Is disease characterized by high level of uric acid which deposited in solid form in the joins causing arthritis.

High blood uric acid occurs in: • Gout • Renal failure (due to decreased excretion in urine) • Leukemia (increased turnover of cells) • Alcoholism • Toxaemia of pregnancy. • Diabetes Mellitues. • Starvation. • Drugs like diuretics. Low blood uric acid occurs in: - Liver diseases (cirrhosis) - Renal disease that decrease renal tubular re-absorption - Some drugs
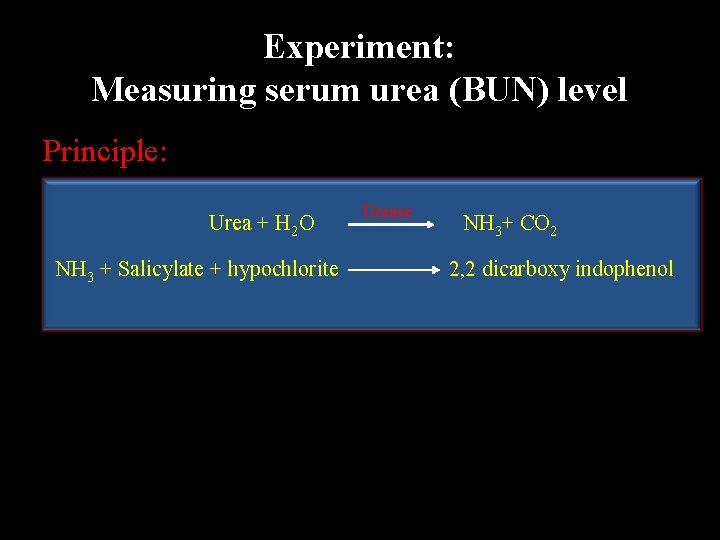
Experiment: Measuring serum urea (BUN) level Principle: Urease Urea + H 2 O NH 3+ CO 2 NH 3 + Salicylate + hypochlorite 2, 2 dicarboxy indophenol

Kit components Reagents: Sulfanalic acid reagent Sodium nitrate reagent Methanol reagent Bilirubinequavalent standard (5 mg/dl T. bil; 2. 5 mg/dl D. bil) • • •

Procedure:
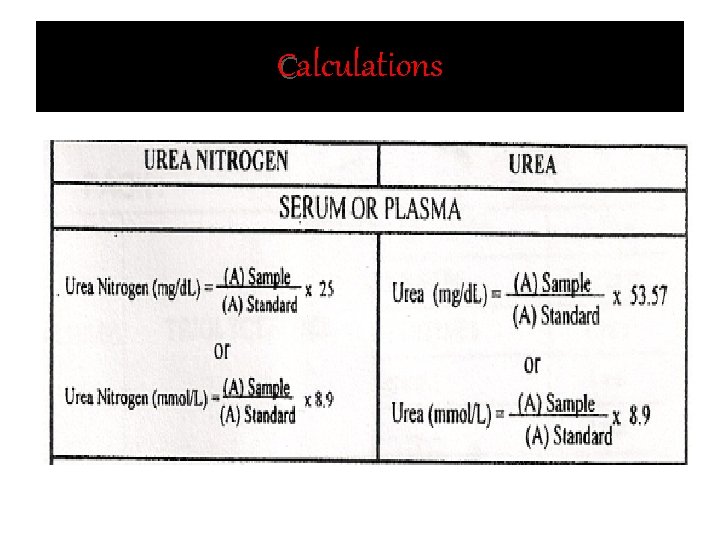
Calculations Abs of Bilirubinequavelant

Normal range BUN: 5 -23 mg/dl Urea: 10 -50 mg/dl
- Slides: 22