
Individual Family Medical Dental Life Plans Great News
























- Slides: 41
Individual & Family Medical, Dental & Life Plans
Great News!!! Our Individual Plan Portfolio is now complete! New Plans to fit all your clients needs. 2
New PPACA compliant plans !!!! Anthem Blue Cross Life & Health Insurance Policies §Smart. Sense Plus §Clear. Protection Plus §Core. Guard Plus §Lumenos HSA Plus §Premier Plus §Tonik 5000 Anthem Blue Cross Plans §PPO Share §HMOs 3
Quick Review of PPACA Mandates • Unlimited Lifetime Maximum • Dependents to Age 26 • Rescission Reform • Removal of Dollar limits on Essential Health Benefits • In Network Preventive Covered at 100% • No Pre-existing for children under age 19 4
Grandfathered vs Non-Grandfathered § Grandfathered members enrolled with an effective date on or before 03/23/10 § Non-Grandfathered members enrolled with an effective date between 03/24/10 and 09/22/10 5
Preventive Care Summary Adult Preventive Care Office Visits Screening Tests including the following: § Vision screening § Hearing screening § Cholesterol and Lipid level screening § Blood Glucose test to screen for Type II Diabetes § Prostate Cancer screenings including Digital Rectal Exam and PSA test § Breast exam and Mammography screening § Pelvic exam, Pap test and contraceptive management for females § Screening for sexually transmitted diseases § HIV test § Bone Density test to screen for osteoporosis § Colorectal Cancer screening including Fecal Occult Blood test, Barium Enema, § Flexible Sigmoidoscopy and screening Colonoscopy § Routine blood and urine screenings Immunizations § Hepatitis A § Hepatitis B § Tetanus, Diphtheria (Td) § Varicella (chicken pox) § Influenza (flu shot) § Pneumococcal Conjugate (pneumonia) § Human Papilloma Virus (HPV) § Measles, Mumps, Rubella (MMR) § Meningococcal Polysaccharide § Herpes Zoster (shingles) 6
Preventive Care Summary Cont. Well Baby and Well Child Preventive Care Office Visits § Screening Tests including the following: § Vision screening § Hearing screening § Screening for lead exposure § Pelvic exam, Pap test and contraceptive management for females Immunizations § Hepatitis A § Hepatitis B § Diphtheria, Tetanus, Pertussis (Dta. P) § Varicella (chicken pox) § Influenza (flu shot) § Pneumococcal Conjugate (pneumonia) § Human Papilloma Virus (HPV) § H. Influenza type b § Polio § Measles, Mumps, Rubella (MMR) § Meningococcal Polysaccharide § Rotavirus 7
Deductible Options Three options! § 2 - member maximum § Once 2 members each reach the deductible, the deductible is satisfied for the entire family. (Share PPO, HMO Plans) § Aggregate § When one or more family members’ eligible covered expenses (combined) meet the aggregate amount, the requirement is satisfied for all covered family members. (Lumenos HSA) § Embedded deductible § The family deductible can be satisfied by 2 or more family members. (Premier Plus, Smart. Sense Plus, Core. Guard Plus, Clear. Protection Plus) 8
Policy/Plan Terms § § § § Network Discounts- Negotiated costs between Anthem Blue Cross and our participating providers. Coinsurance- The percentage of the cost of covered services that the member is responsible for, after the annual deductible has been met. Deductible- The amount you have to pay each calendar year for covered services before your health plan starts paying. Out-Of-Pocket Maximum- The most that you would have to pay in a calendar year for deductible and coinsurance for in-network covered services. Formulary- a list of prescription drugs our health plans cover. Specialty Drugs- typically high in cost, scientifically engineered drugs used to treat complex, chronic conditions. Health Savings Account (HSA) – is a special bank account that can be set up by a member enrolled in a qualified HSA-compatible highdeductible health plan if they choose. Contributions to this account can be made with certain tax advantages if used for qualified health care expenses. 9
Find a plan that meets your clients needs You can achieve this by simply asking the following questions to your client: § PPO or HMO? § Are you looking for maternity coverage? § What type of prescription coverage are you looking for? Generic? Name brand? § What does your budget look like? § Are you looking for coverage that is comparable to group? 10
Things to keep in mind § Maternity and Pharmacy are the main cost drivers on each plan. § The higher the deductible option, the lower the premium. § If coming off of group coverage, enrollment under Individual is medically underwritten. § To increase client retention always include a quote for dental and life products. § Social security numbers are not needed to apply, only California residency for at least 3 months. § The earliest effective date available would be 15 calendar days after receipt of the application. § Writeable Applications can now be emailed to Application. Express@Anthem. com 11
“What are the plans that Anthem Blue Cross has to offer? ” 12
PPO Policies/Plans § § § § Premier Plus Smart. Sense Plus Clear. Protection Plus Core. Guard Plus Lumenos HSA Plus Tonik 5000 PPO Share 13
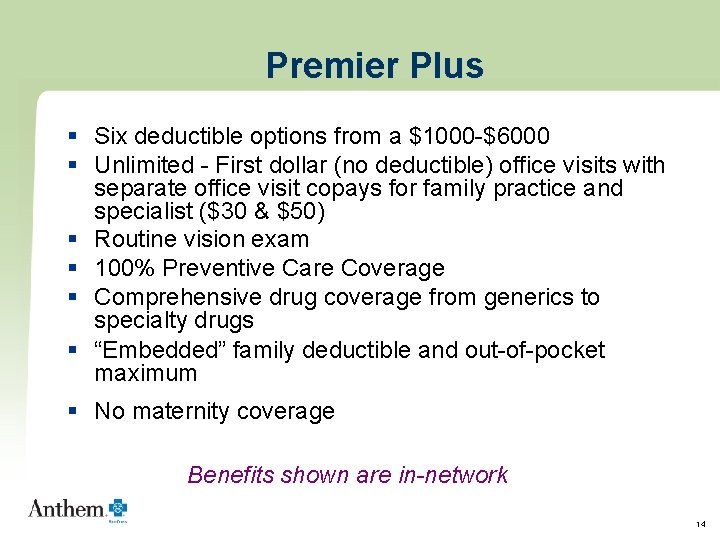
Premier Plus § Six deductible options from a $1000 -$6000 § Unlimited - First dollar (no deductible) office visits with separate office visit copays for family practice and specialist ($30 & $50) § Routine vision exam § 100% Preventive Care Coverage § Comprehensive drug coverage from generics to specialty drugs § “Embedded” family deductible and out-of-pocket maximum § No maternity coverage Benefits shown are in-network 14
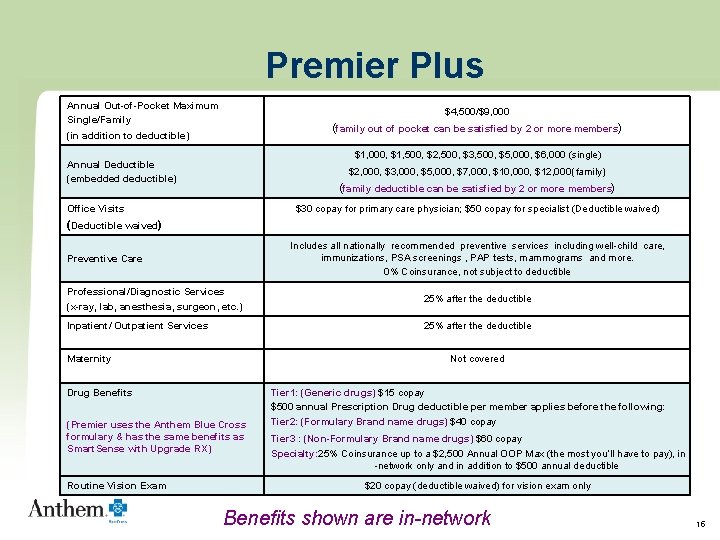
Premier Plus Annual Out-of-Pocket Maximum Single/Family $4, 500/$9, 000 (family out of pocket can be satisfied by 2 or more members) (in addition to deductible) $1, 000, $1, 500, $2, 500, $3, 500, $5, 000, $6, 000 (single) Annual Deductible (embedded deductible) $2, 000, $3, 000, $5, 000, $7, 000, $10, 000, $12, 000 (family) (family deductible can be satisfied by 2 or more members) Office Visits $30 copay for primary care physician; $50 copay for specialist (Deductible waived) Includes all nationally recommended preventive services including well-child care, immunizations, PSA screenings , PAP tests, mammograms and more. 0% Coinsurance, not subject to deductible Preventive Care Professional/Diagnostic Services (x-ray, lab, anesthesia, surgeon, etc. ) 25% after the deductible Inpatient/ Outpatient Services 25% after the deductible Maternity Not covered Drug Benefits (Premier uses the Anthem Blue Cross formulary & has the same benefits as Smart. Sense with Upgrade RX) Routine Vision Exam Tier 1: (Generic drugs) $15 copay $500 annual Prescription Drug deductible per member applies before the following: Tier 2: (Formulary Brand name drugs) $40 copay Tier 3 : (Non-Formulary Brand name drugs) $60 copay Specialty: 25% Coinsurance up to a $2, 500 Annual OOP Max (the most you’ll have to pay), in -network only and in addition to $500 annual deductible $20 copay (deductible waived) for vision exam only Benefits shown are in-network 15
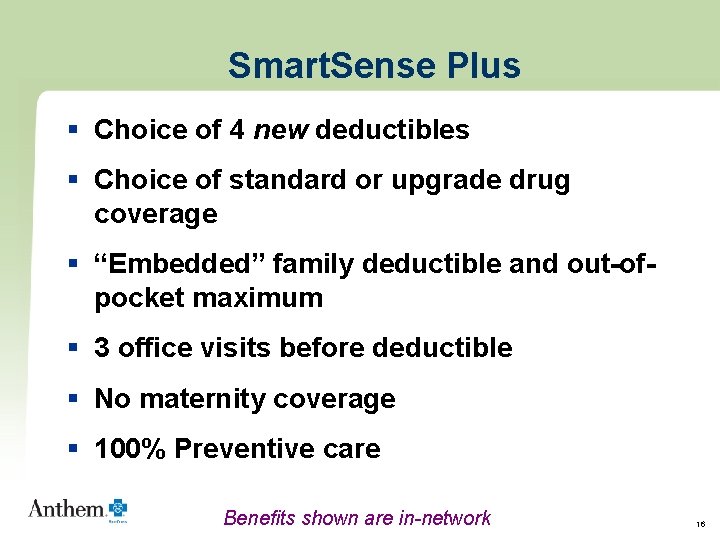
Smart. Sense Plus § Choice of 4 new deductibles § Choice of standard or upgrade drug coverage § “Embedded” family deductible and out-ofpocket maximum § 3 office visits before deductible § No maternity coverage § 100% Preventive care Benefits shown are in-network 16
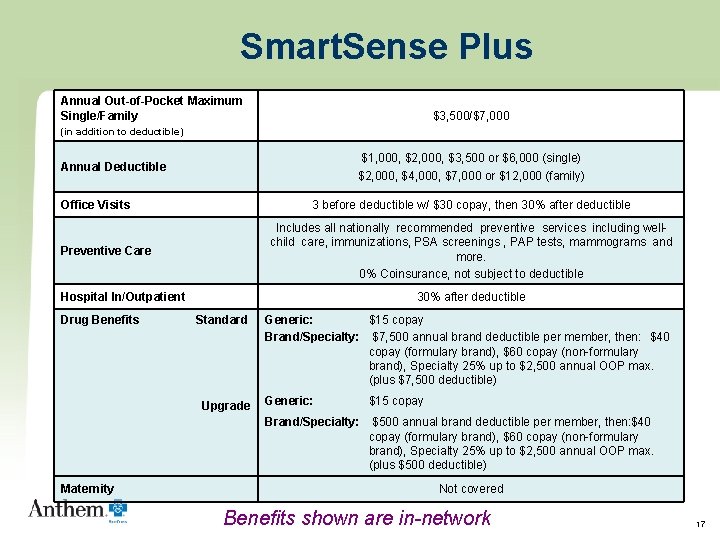
Smart. Sense Plus Annual Out-of-Pocket Maximum Single/Family $3, 500/$7, 000 (in addition to deductible) $1, 000, $2, 000, $3, 500 or $6, 000 (single) $2, 000, $4, 000, $7, 000 or $12, 000 (family) Annual Deductible Office Visits 3 before deductible w/ $30 copay, then 30% after deductible Includes all nationally recommended preventive services including wellchild care, immunizations, PSA screenings , PAP tests, mammograms and more. 0% Coinsurance, not subject to deductible Preventive Care Hospital In/Outpatient Drug Benefits 30% after deductible Standard Upgrade Maternity Generic: $15 copay Brand/Specialty: $7, 500 annual brand deductible per member, then: $40 copay (formulary brand), $60 copay (non-formulary brand), Specialty 25% up to $2, 500 annual OOP max. (plus $7, 500 deductible) Generic: $15 copay Brand/Specialty: $500 annual brand deductible per member, then: $40 copay (formulary brand), $60 copay (non-formulary brand), Specialty 25% up to $2, 500 annual OOP max. (plus $500 deductible) Not covered Benefits shown are in-network 17
Lumenos HSA Plus Consumer-Driven Health Plans (CDHPs) § § § HSA-compatible 100% coverage after deductible Preventive care benefits Various deductible options Special programs for Smoking Cessation and Weight Management § Powerful online health management tools § Access to our 24 -Hour nurse Line Benefits shown are in-network 18
Lumenos HSA Plus HSA Account Annual Out-of-Pocket Maximum (in addition to deductible) § Funded by subscriber, up to maximum limit set by U. S. Treasury § Unused dollars rollover year-to-year § Subscriber “owns” HSA 0% Annual Deductible Single: $3, 000/$4, 500/$5, 950 Family: $3, 500/ $5, 500 (Aggregate Deductible) or Family: $7, 500/$11, 900 (Embedded Deductible) Coinsurance after deductible 0% Office Visits 0% Preventive Care (nationally recommended services) $0 (deductible waived) Hospital In/ Outpatient 0% Maternity Drug Benefits Not covered 0% Benefits shown are in-network 19
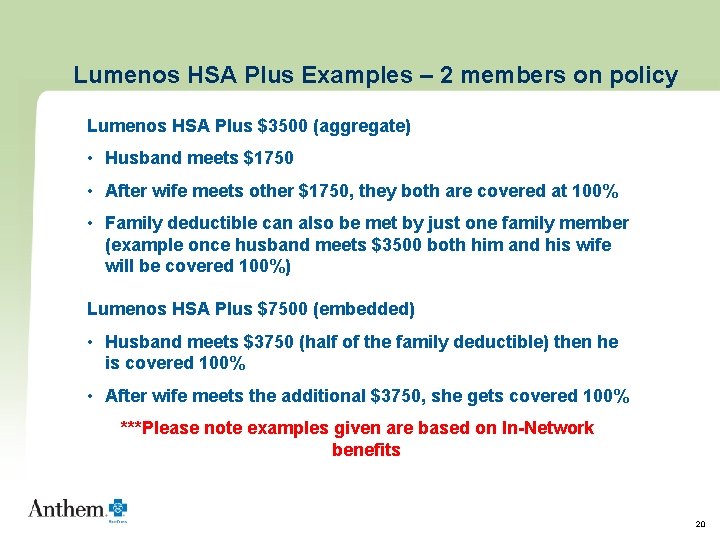
Lumenos HSA Plus Examples – 2 members on policy Lumenos HSA Plus $3500 (aggregate) • Husband meets $1750 • After wife meets other $1750, they both are covered at 100% • Family deductible can also be met by just one family member (example once husband meets $3500 both him and his wife will be covered 100%) Lumenos HSA Plus $7500 (embedded) • Husband meets $3750 (half of the family deductible) then he is covered 100% • After wife meets the additional $3750, she gets covered 100% ***Please note examples given are based on In-Network benefits 20
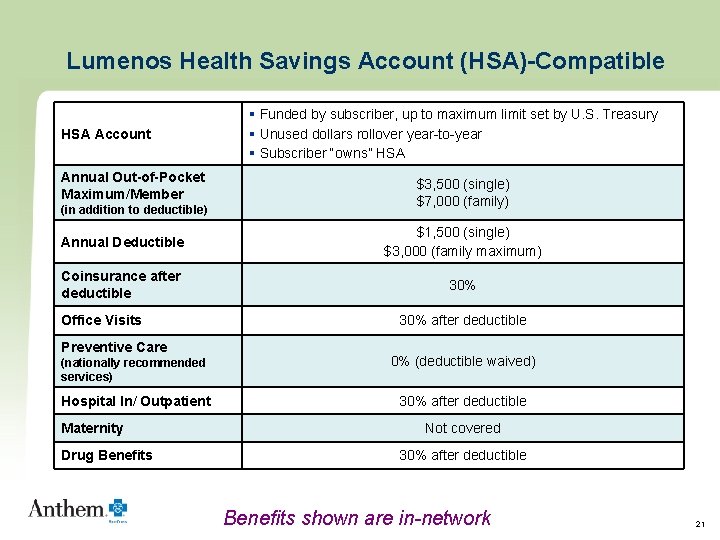
Lumenos Health Savings Account (HSA)-Compatible HSA Account Annual Out-of-Pocket Maximum/Member (in addition to deductible) § Funded by subscriber, up to maximum limit set by U. S. Treasury § Unused dollars rollover year-to-year § Subscriber “owns” HSA $3, 500 (single) $7, 000 (family) Annual Deductible $1, 500 (single) $3, 000 (family maximum) Coinsurance after deductible 30% Office Visits Preventive Care 30% after deductible (nationally recommended services) 0% (deductible waived) Hospital In/ Outpatient 30% after deductible Maternity Drug Benefits Not covered 30% after deductible Benefits shown are in-network 21
Lumenos Health Savings Account (HSA)-Compatible With Maternity HSA Account Annual Out-of-Pocket Maximum/Member § Funded by subscriber, up to maximum limit set by U. S. Treasury § Unused dollars rollover year-to-year § Subscriber “owns” HSA $0 (in addition to deductible) Annual Deductible $5, 000 (single) $10, 000 (family maximum) Coinsurance after deductible 0% Office Visits Preventive Care 0% after deductible (nationally recommended services) 0% (deductible waived) Hospital In/ Outpatient 0% after deductible Maternity 0% after deductible Drug Benefits 0% after deductible Benefits shown are in-network 22
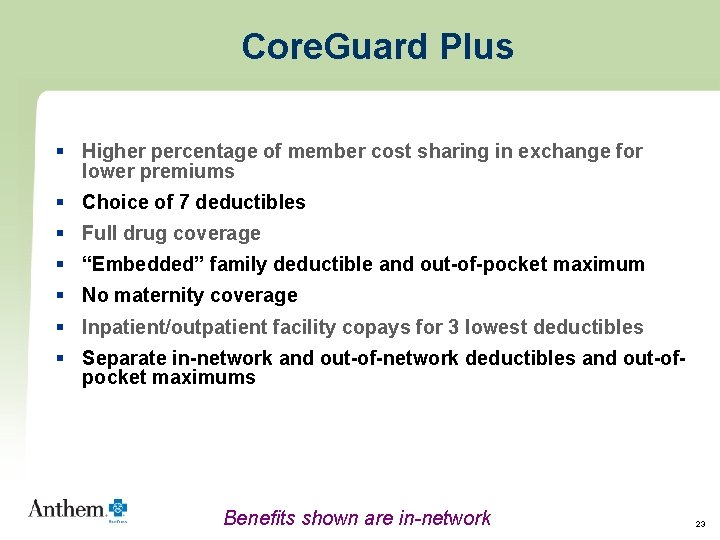
Core. Guard Plus § Higher percentage of member cost sharing in exchange for lower premiums § Choice of 7 deductibles § Full drug coverage § “Embedded” family deductible and out-of-pocket maximum § No maternity coverage § Inpatient/outpatient facility copays for 3 lowest deductibles § Separate in-network and out-of-network deductibles and out-ofpocket maximums Benefits shown are in-network 23
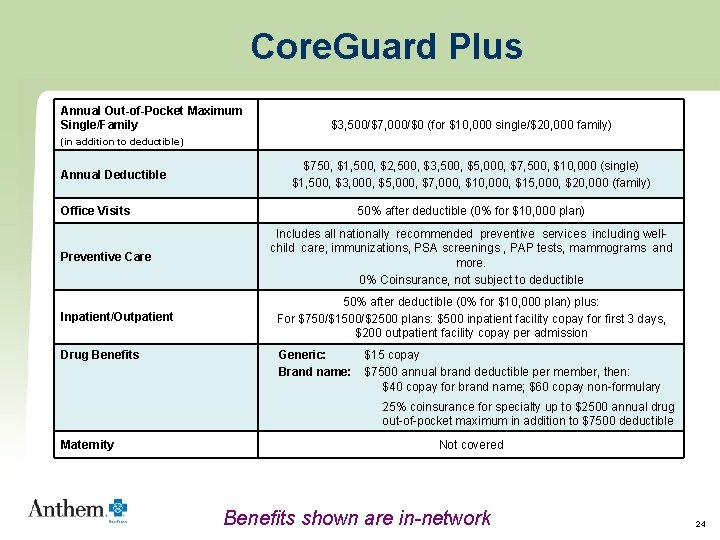
Core. Guard Plus Annual Out-of-Pocket Maximum Single/Family $3, 500/$7, 000/$0 (for $10, 000 single/$20, 000 family) (in addition to deductible) Annual Deductible $750, $1, 500, $2, 500, $3, 500, $5, 000, $7, 500, $10, 000 (single) $1, 500, $3, 000, $5, 000, $7, 000, $10, 000, $15, 000, $20, 000 (family) Office Visits Preventive Care Inpatient/Outpatient Drug Benefits 50% after deductible (0% for $10, 000 plan) Includes all nationally recommended preventive services including wellchild care, immunizations, PSA screenings , PAP tests, mammograms and more. 0% Coinsurance, not subject to deductible 50% after deductible (0% for $10, 000 plan) plus: For $750/$1500/$2500 plans: $500 inpatient facility copay for first 3 days, $200 outpatient facility copay per admission Generic: Brand name: $15 copay $7500 annual brand deductible per member, then: $40 copay for brand name; $60 copay non-formulary 25% coinsurance for specialty up to $2500 annual drug out-of-pocket maximum in addition to $7500 deductible Maternity Not covered Benefits shown are in-network 24
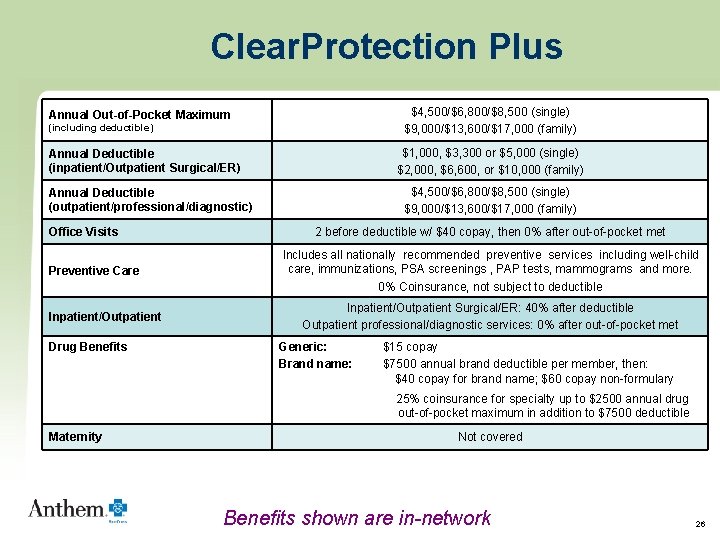
Clear. Protection Plus § Two deductible levels (negotiated rates apply before and after meeting deductible) § Lower deductible for Inpatient/Outpatient Surgical and Emergency Room § Higher deductible for Outpatient/Professional/Diagnostic (this deductible is equal to the plan out-of-pocket maximum) § Two deductibles work together to meet out-of-pocket maximum § 2 office visits before deductible § Full drug coverage § “Embedded” family deductible and out-of-pocket maximum § No maternity coverage § Coverage for generic and brand name prescription drugs Benefits shown are in-network 25
Clear. Protection Plus $4, 500/$6, 800/$8, 500 (single) $9, 000/$13, 600/$17, 000 (family) Annual Out-of-Pocket Maximum (including deductible) $1, 000, $3, 300 or $5, 000 (single) $2, 000, $6, 600, or $10, 000 (family) Annual Deductible (inpatient/Outpatient Surgical/ER) $4, 500/$6, 800/$8, 500 (single) $9, 000/$13, 600/$17, 000 (family) Annual Deductible (outpatient/professional/diagnostic) Office Visits Preventive Care Inpatient/Outpatient Drug Benefits 2 before deductible w/ $40 copay, then 0% after out-of-pocket met Includes all nationally recommended preventive services including well-child care, immunizations, PSA screenings , PAP tests, mammograms and more. 0% Coinsurance, not subject to deductible Inpatient/Outpatient Surgical/ER: 40% after deductible Outpatient professional/diagnostic services: 0% after out-of-pocket met Generic: Brand name: $15 copay $7500 annual brand deductible per member, then: $40 copay for brand name; $60 copay non-formulary 25% coinsurance for specialty up to $2500 annual drug out-of-pocket maximum in addition to $7500 deductible Maternity Not covered Benefits shown are in-network 26
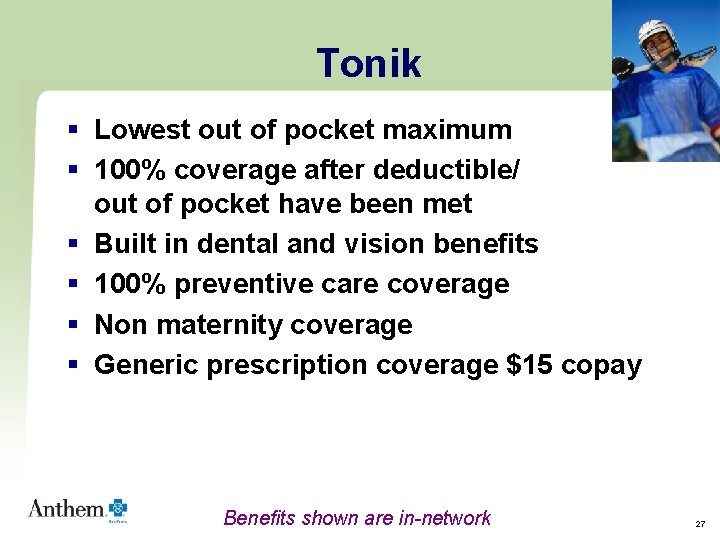
Tonik § Lowest out of pocket maximum § 100% coverage after deductible/ out of pocket have been met § Built in dental and vision benefits § 100% preventive care coverage § Non maternity coverage § Generic prescription coverage $15 copay Benefits shown are in-network 27
Tonik 5000 Annual Out-of-Pocket Maximum/Member $0 (in addition to deductible) Annual Deductible $5, 000 Coinsurance after deductible 0% Office Visits Preventive Care $20 copay/first 4 visits, then 0% after deductible (nationally recommended services) $0 (deductible waived) Hospital In/ Outpatient $0 after deductible Maternity Not covered Dental $0 for cleanings, exams, and X-rays Vision $25 for basic eyeglass lenses and receive up to $100 towards frames or $80 towards contact lenses every 24 months Drug Benefits $15 for a 30 -day supply Benefits shown are in-network 28
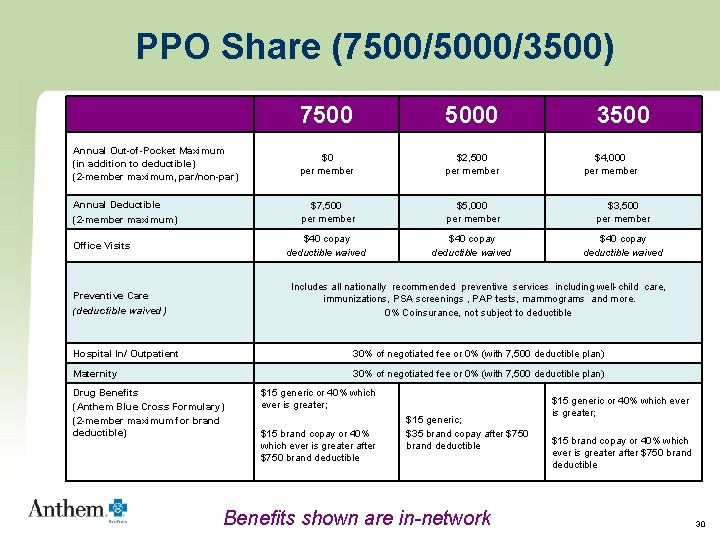
PPO Plans PPO Share (7500/5000/3500) Comprehensive PPO plans § Once deductible is met, member pays 0% or 30% co-insurance (depending on plan) for most covered services § Deductible waived for office visits, annual physical exam and preventive care § Maternity coverage § Generic and Brand name prescription coverage Benefits shown are in-network 29
PPO Share (7500/5000/3500) 7500 5000 Annual Out-of-Pocket Maximum (in addition to deductible) (2 -member maximum, par/non-par) $0 per member $2, 500 per member Annual Deductible (2 -member maximum) $7, 500 per member $5, 000 per member $3, 500 per member $40 copay deductible waived Office Visits 3500 $4, 000 per member Includes all nationally recommended preventive services including well-child care, immunizations, PSA screenings , PAP tests, mammograms and more. 0% Coinsurance, not subject to deductible Preventive Care (deductible waived) Hospital In/ Outpatient 30% of negotiated fee or 0% (with 7, 500 deductible plan) Maternity 30% of negotiated fee or 0% (with 7, 500 deductible plan) Drug Benefits (Anthem Blue Cross Formulary) (2 -member maximum for brand deductible) $15 generic or 40% which ever is greater; $15 brand copay or 40% which ever is greater after $750 brand deductible $15 generic; $35 brand copay after $750 brand deductible Benefits shown are in-network $15 generic or 40% which ever is greater; $15 brand copay or 40% which ever is greater after $750 brand deductible 30
HMO Plans § HMO Saver § Individual HMO § Select HMO 31
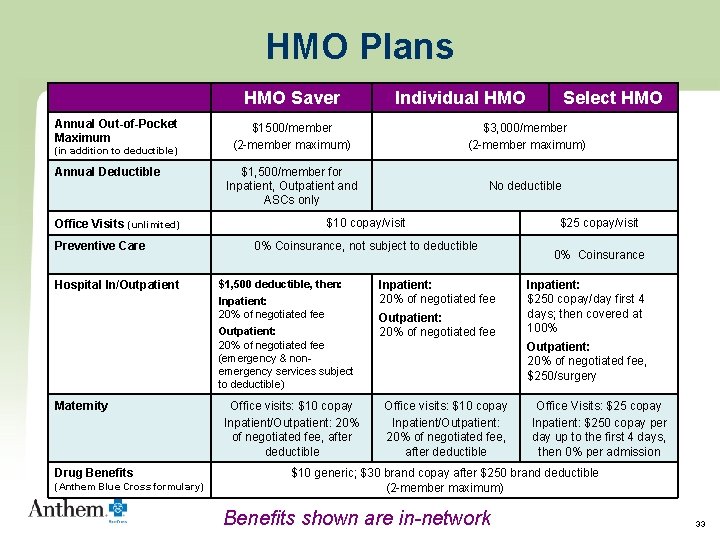
HMO Plans HMO Saver, Individual HMO, Select HMO § First dollar coverage on: § Office visits § Generic drugs § Preventive care § Unlimited office visits with set copays § Coverage for services from doctors and hospitals in HMO network § Comprehensive drug plan § Maternity coverage Benefits shown are in-network 32
HMO Plans HMO Saver Annual Out-of-Pocket Maximum (in addition to deductible) Annual Deductible Hospital In/Outpatient $3, 000/member (2 -member maximum) $1, 500/member for Inpatient, Outpatient and ASCs only No deductible $10 copay/visit 0% Coinsurance, not subject to deductible $1, 500 deductible, then: Inpatient: 20% of negotiated fee Outpatient: 20% of negotiated fee (emergency & nonemergency services subject to deductible) Maternity Drug Benefits (Anthem Blue Cross formulary) Select HMO $1500/member (2 -member maximum) Office Visits (unlimited) Preventive Care Individual HMO Office visits: $10 copay Inpatient/Outpatient: 20% of negotiated fee, after deductible Inpatient: 20% of negotiated fee Outpatient: 20% of negotiated fee $25 copay/visit 0% Coinsurance Inpatient: $250 copay/day first 4 days; then covered at 100% Outpatient: 20% of negotiated fee, $250/surgery Office visits: $10 copay Inpatient/Outpatient: 20% of negotiated fee, after deductible Office Visits: $25 copay Inpatient: $250 copay per day up to the first 4 days, then 0% per admission $10 generic; $30 brand copay after $250 brand deductible (2 -member maximum) Benefits shown are in-network 33
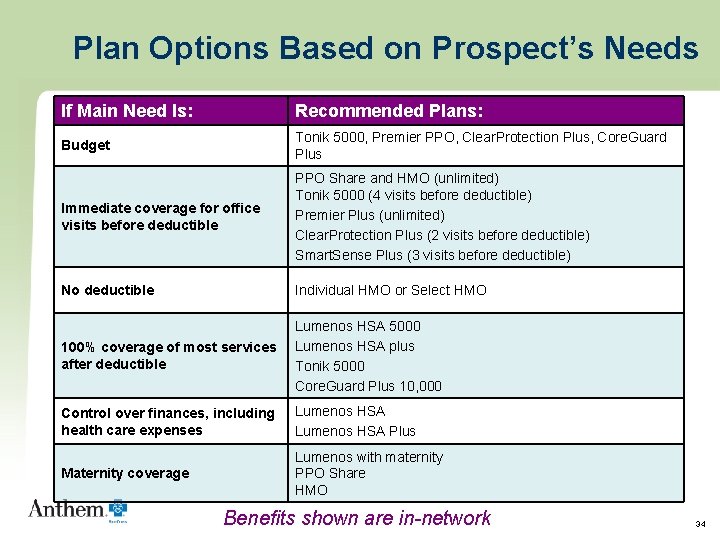
Plan Options Based on Prospect’s Needs If Main Need Is: Recommended Plans: Budget Tonik 5000, Premier PPO, Clear. Protection Plus, Core. Guard Plus Immediate coverage for office visits before deductible PPO Share and HMO (unlimited) Tonik 5000 (4 visits before deductible) Premier Plus (unlimited) Clear. Protection Plus (2 visits before deductible) Smart. Sense Plus (3 visits before deductible) No deductible Individual HMO or Select HMO 100% coverage of most services after deductible Lumenos HSA 5000 Lumenos HSA plus Tonik 5000 Core. Guard Plus 10, 000 Control over finances, including health care expenses Lumenos HSA Plus Maternity coverage Lumenos with maternity PPO Share HMO Benefits shown are in-network 34
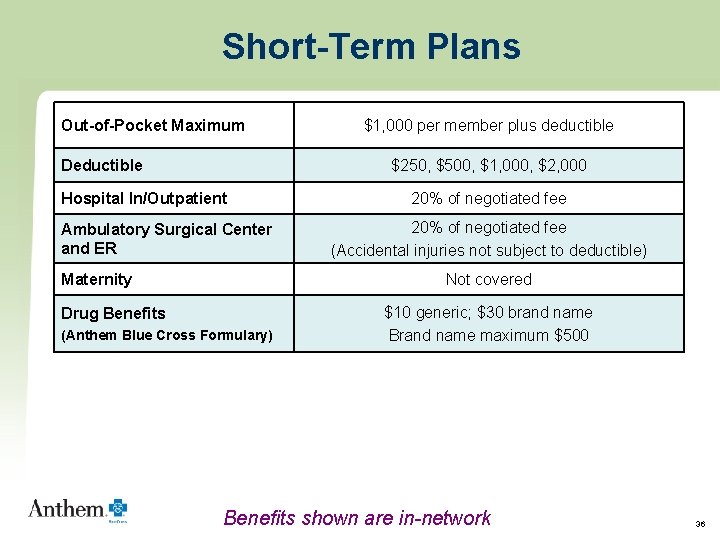
Short-Term Plans § Coverage from 30 to 180 days § Choice of deductible level § Easy application process § Streamlined underwriting § No maternity § Member-level-rated 35
Short-Term Plans Out-of-Pocket Maximum Deductible $1, 000 per member plus deductible $250, $500, $1, 000, $2, 000 Hospital In/Outpatient Ambulatory Surgical Center and ER Maternity 20% of negotiated fee (Accidental injuries not subject to deductible) Not covered Drug Benefits (Anthem Blue Cross Formulary) $10 generic; $30 brand name Brand name maximum $500 Benefits shown are in-network 36
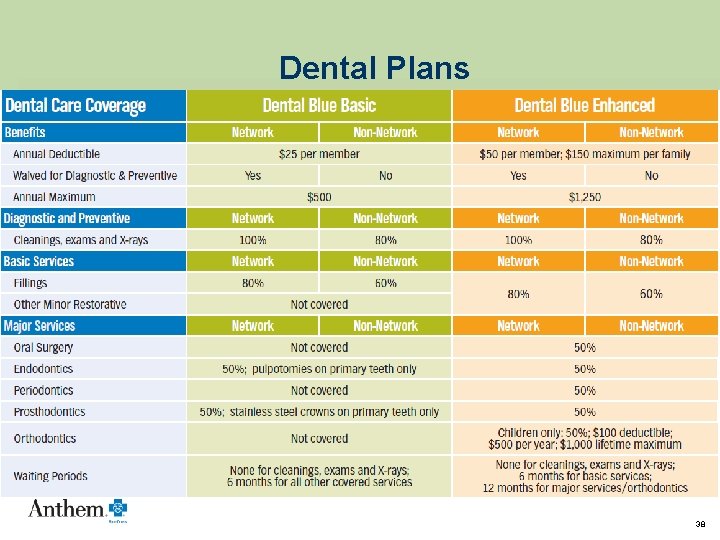
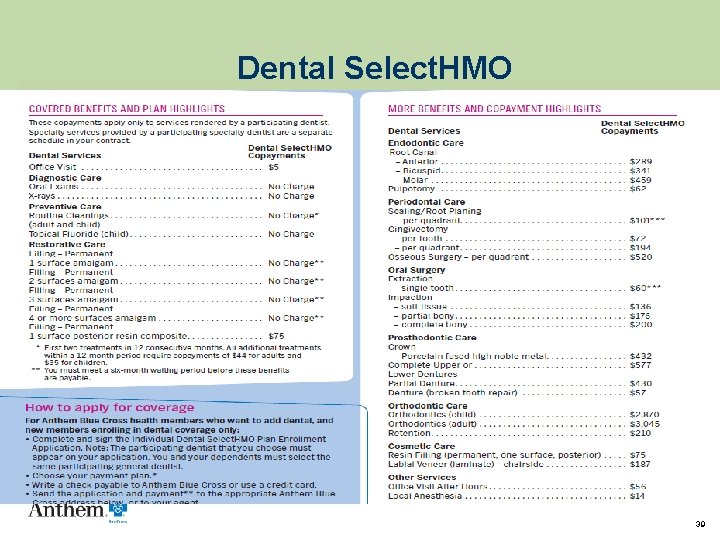
Dental Plans Three Individual dental options: §Dental Blue Basic* §Dental Blue Enhanced* §Dental Select. HMO** • *Anthem Blue Cross Life & Health Insurance Company • **Anthem Blue Cross 37
Dental Plans 38
Dental Select. HMO 39
Individual Life Insurance Term Life Insurance § Anyone who qualifies for one of medical plans can purchase: § $15, 000, $30, 000, $50, 000, $75, 000 or $100, 000 (if over age 19) § $15, 000 or $30, 000 (ages 1 -19) 40
Health • Dental • Life Thank You for Selling Anthem Blue Cross! 41