
Indicatie lymfadenectomie bij pelviene tumoren Jaarcongres VVOG 18

Indicatie lymfadenectomie bij pelviene tumoren Jaarcongres VVOG 18 en 19 oktober 2012 Bredene Koen Traen OLV ziekenhuis Aalst
Lymfadenectomie • Pelviene lymfadenectomie • Para-aortale lymfadenectomie

VWOG aanbevelingen 2012 • Cervixcarcinoom • Endometriumcarcinoom • Ovariumcarcinoom

Cervixcarcinoom
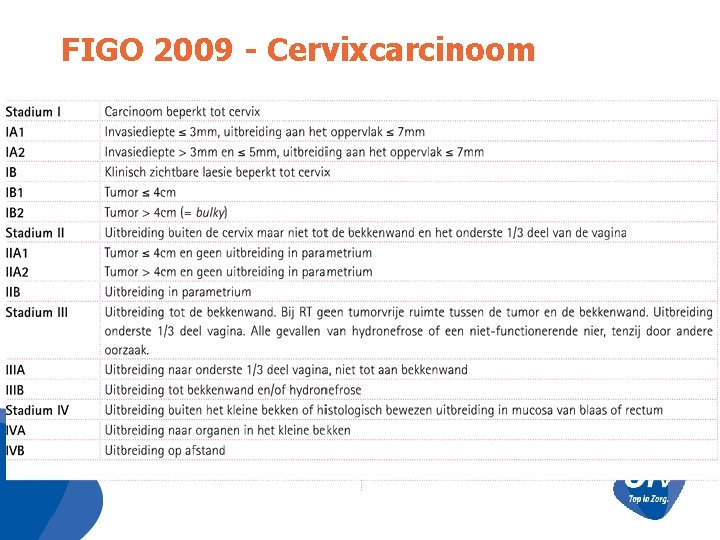
FIGO 2009 - Cervixcarcinoom

VWOG aanbeveling • IA 1 conisatie of hysterectomie (CAVE! LVSI+) • IA 2 radicale hysterectomie + pelviene LN Trend naar minder radicale heelkunde • IB 1 IIA 1 radicale hysterectomie + pelviene LN Chemoradiatie goed alternatief • Bulky of locally advanced -> chemoradiatie NACT + radicale heelkunde kan alternatief zijn

Indicaties pelviene lymfadenectomie VWOG aanbeveling • Pelviene lymfadenectomie als essentiëel onderdeel van primaire heelkundige behandeling early stage cervical cancer • Minstens 20 bekkenlymfeklieren • Sentinel in studieverband

Indicaties para-aortale lymfadenectomie VWOG aanbeveling • Stadium IB 2 en IIA 2 “Sommige auteurs beschouwen chemoradiatie met bestralingsvolume op basis van chirurgische stadiëring als de referentiebehandeling…” • Stadium IIB “Tenzij een betere prognostische stratificatie is er echter geen bewezen therapeutisch voordeel voor chirurgische stadiëring” • Stadium IIIB “Geïndividualiseerde stralingsplannen gebaseerd op chirurgische staging (para-aortale klieren) wordt gereserveerd voor patiënten in goede algemene toestand. ”

• Kan Sentinel pelviene lymfadenectomie vervangen bij primaire heelkunde voor IA 2, IB 1 en IIA 1? • Para-aortale lymfadenectomie voorafgaand aan chemoradiatie voor IB 2, IIA 2, IIB, IIIB en IVA ?

Voordelen Sentinel • Identificatie van de Sentinel LN op aberrante locaties
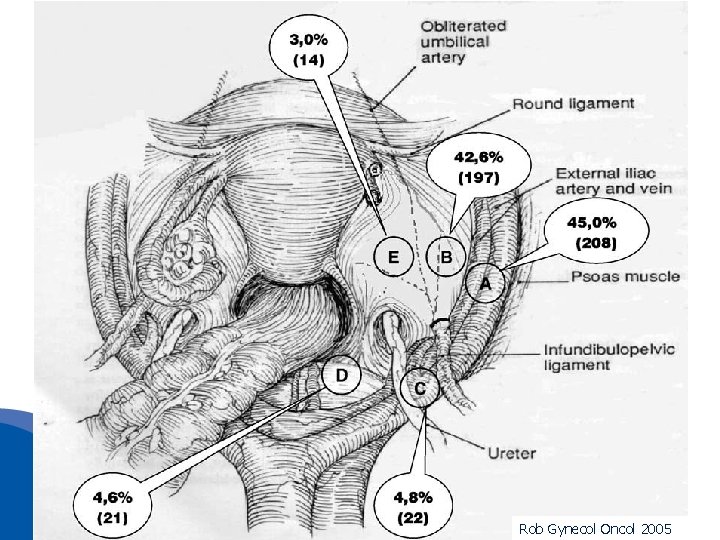
Rob Gynecol Oncol 2005
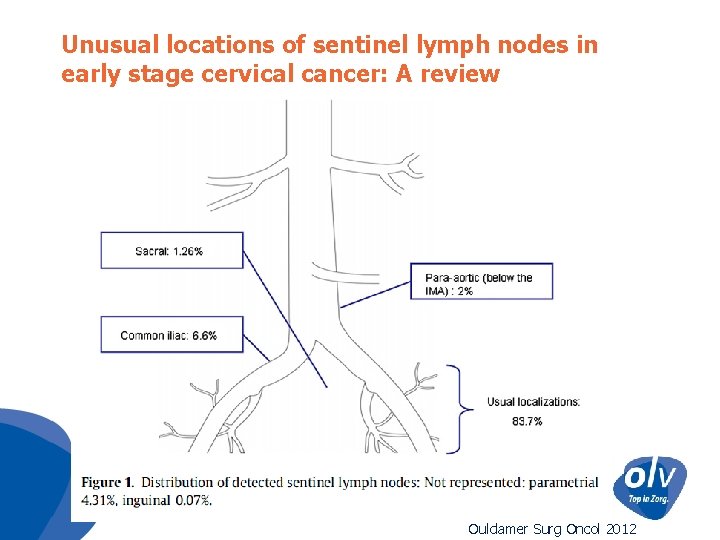
Unusual locations of sentinel lymph nodes in early stage cervical cancer: A review Ouldamer Surg Oncol 2012

Voordelen Sentinel • • Identificatie Sentinel op aberrante locaties Ultrastaging Detectie micrometastasen Minder morbiditeit Vermijden 85% onnodige pelviene LND (N -) Verhogen pick up rate LN M+ Peroperatoir pos Sentinel – > stop heelkunde – plan chemoradiatie – > Para-aortale lymfadenectomie?

Probleem ? • Schrik voor vals-negatieven • Ervaring nodig (N = 30 ? )

Techniek • Tc colloïd + patent blue • Injectie in normaal cervicaal stroma • Scannen bekkenwanden, presacraal en paraaortaal

Sentinel lymph node mapping in cervical cancer: the future? • Steeds bilateraal (zo slechts unilaterale SN -> contralateraal pelviene LND) • Hemipelvis per hemipelvis evalueren – Neg SN unilateraal zegt niets over andere zijde – Neg SN contralateraal aan LN M+ is niet vals negatief Eiriksson, Covens BJOG 2012
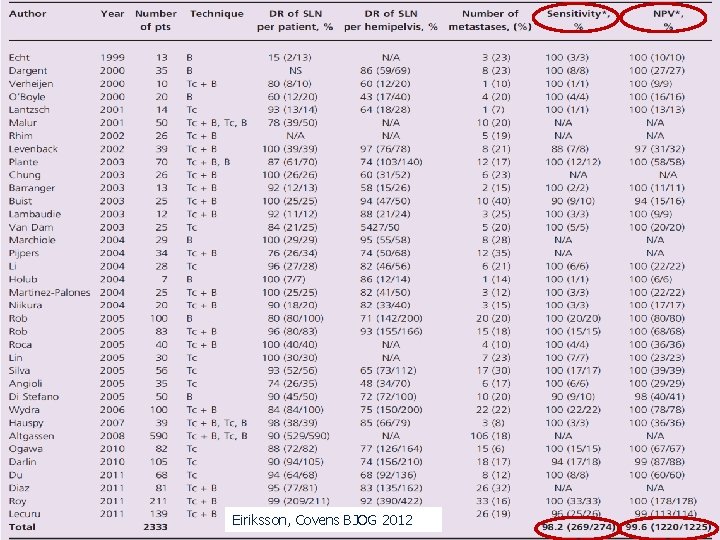
Eiriksson, Covens BJOG 2012

Besluit Sentinel • Tc colloïd + patent blue • Steeds bilateraal (zo slechts unilaterale SN -> conralateraal pelviene LND) • Zeer hoge detectierate • Zeer weinig vals-negatieven • Tumoren tot 2 cm?

• Kan Sentinel pelviene lymfadenectomie vervangen bij primaire heelkunde voor IA 2, IB 1 en IIA 1? • Para-aortale lymfadenectomie voorafgaand aan chemoradiatie voor IB 2, IIA 2, IIB, IIIB en IVA ?

Indicaties para-aortale lymfadenectomie VWOG aanbeveling • Stadium IB 2 en IIA 2 “Sommige auteurs beschouwen chemoradiatie met bestralingsvolume op basis van chirurgische stadiëring als de referentiebehandeling…” • Stadium IIB “Tenzij een betere prognostische stratificatie is er echter geen bewezen therapeutisch voordeel voor chirurgische stadiëring. ” • Stadium IIIB “Geïndividualiseerde stralingsplannen gebaseerd op chirurgische staging (para-aortale klieren) wordt gereserveerd voor patiënten in goede algemene toestand. ”
Para-aortale staging voor chemoradiatie bij locally advanced cervixcarcinoom (LACC) • Doel: bestralingsveld uitbreiden • Rationale: 10 -25% positieve PAO LN • Pet of PET-CT meest sensitieve imaging modality • PET of PET-CT vals negatief in 5 -17%
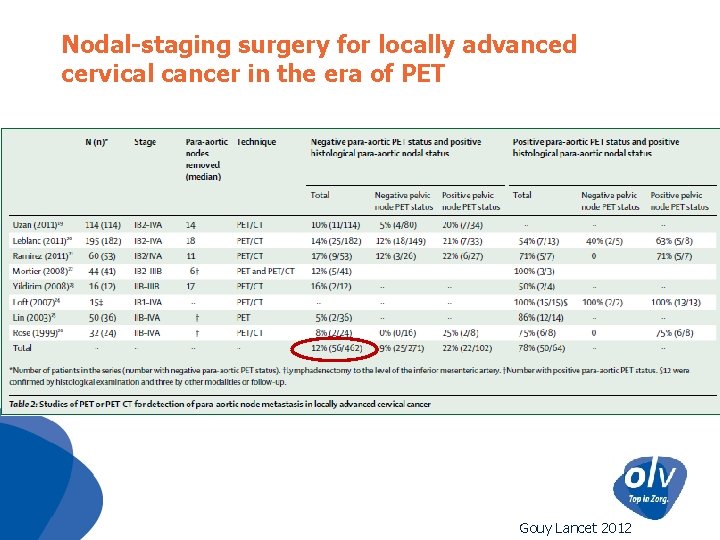
Nodal-staging surgery for locally advanced cervical cancer in the era of PET Gouy Lancet 2012

Para-aortale staging voor chemoradiatie bij locally advanced cervixcarcinoom • 12% positieve PAO LN bij PET-negatieve PAO LN • Gouden standaard laparoscopische (extraperitoneale) para-aortale LND – Ernstige complicaties 0 -7% – Symptomatische lymfocoele 10% • Tot AMI of tot vena renalis?
Para-aortale staging tot AMI? • Vergote – Tot AMI – Mean 6 LN – 7/38 pos LN (18%) – Geen PAO recidieven • Merlot – Tot v. renalis – Mean? – 22/84 pos LN (26%) – 8/22 boven en onder AMI – 1/22 enkel boven AMI Vergote IJGC 2002 Merlot ESGO 2011
Therapeutic value of pretherapeutic extraperitoneal laparoscopic staging of locally advanced cervical carcinoma • Leblanc 2007 – – Retrospectief N = 184 LACC -> 181 PAO LND 8/181 onmogelijk 44/181 pos PAO LN (24%) Therapeutisch effect? Leblanc Gynecol Oncol 2007
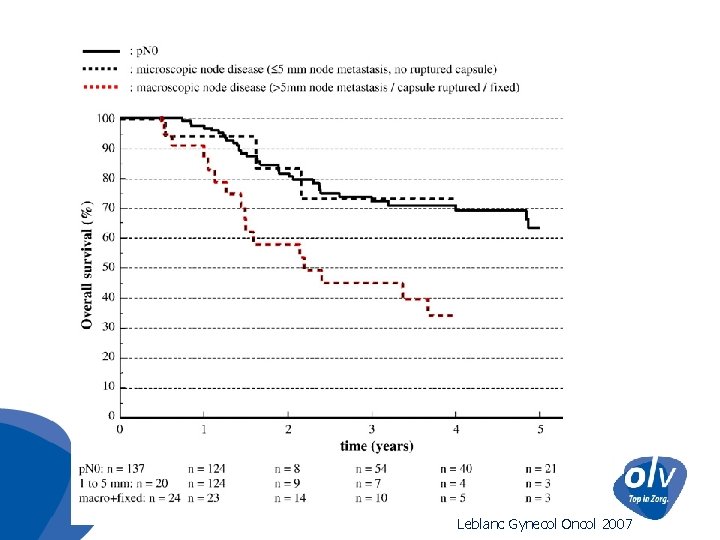
Leblanc Gynecol Oncol 2007

Effect van para-aortale staging op survival • Leblanc 2007 – Therapeutisch effect? Geen survival verschil tussen N 0 of M+ ≤ 5 mm • Resultaten 2 RCT’s afwachten Leblanc Gynecol Oncol 2007

Endometriumcarcinoom

Endometriumcarcinoom • Endometrioïd endometriumcarcinoom • Niet-endometrioïd endometriumcarcinoom • FIGO 2009
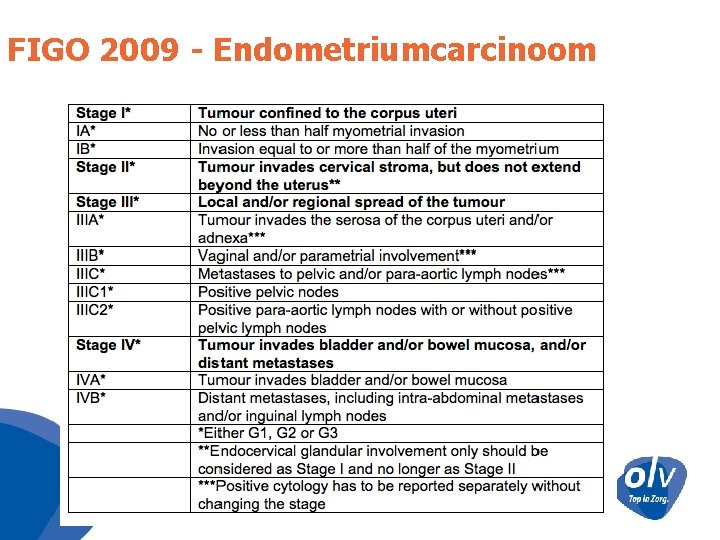
FIGO 2009 - Endometriumcarcinoom

Techniek lymfadenectomie VWOG • Pelvien – Iliaca externa, interna, communis en fossa obturatoria – Minstens 6 lymfeklieren per zijde (of 11 in totaal) • Para-aortaal Tot inmonding vena ovarica rechts + vena renalis links

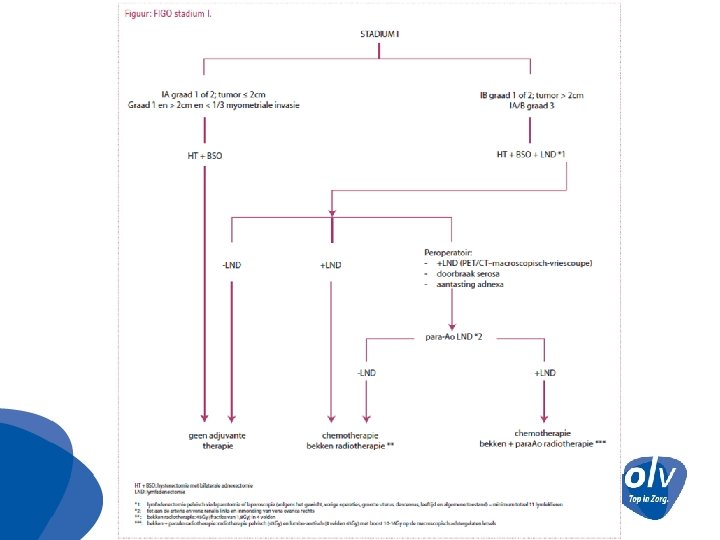
Indicaties pelviene lymfadenectomie VWOG • Endometrioïd endometriumcarcinoom – Stadium I Graad 3 – Stadium IB – Stadium I - diameter > 2 cm • Behalve graad 1 > 2 cm en < 1/3 invasie myometrium – Stadium IIIA + IIIC 1 en IIIC 2

Indicaties para-aortale lymfadenectomie VWOG • Positieve pelviene lymfeklieren CT – PET – VC - macroscopisch • Doorbraak serosa of aantasting adnex (stadium IIIA)

• Is lymfadenectomie wel nodig? • Indicaties Sentinel? • Indien lymfadenectomie, steeds ook para-aortale lymfadenectomie?

Geen lymfadenectomie meer na MRC ASTEC trial?
MRC ASTEC • RCT (N = 1408) • UK • Proven endometrial carcinoma thought preoperatively to be confined to the uterus • TAH + BSO -> randomisatie +/- pelviene lymfadenectomie Astec Lancet 2009
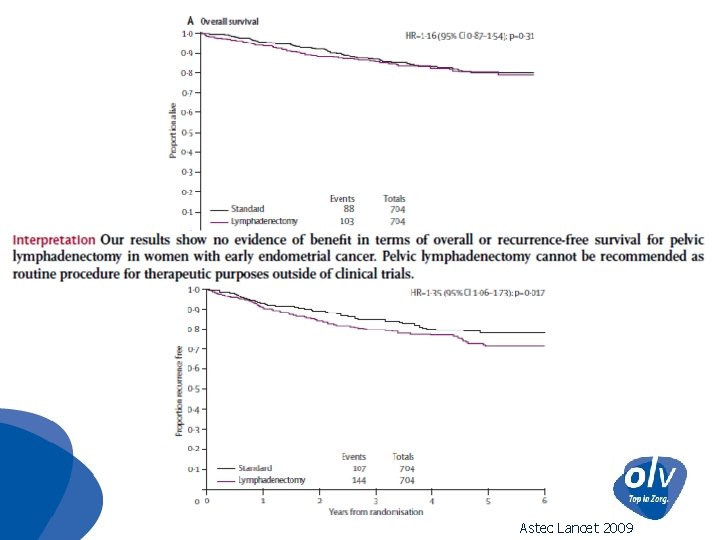
Astec Lancet 2009

Geen pelviene lymfadenectomie meer na ASTEC ? • Median nodes 12 ( 35% < 10 LN) Geen systematische pelviene lymfadenectomie • 45 % low risk early stage 45 % geen pelviene lymfadenectomie aangewezen • Tot 20 % non-endometrioïd Inadequate staging • Geen para-aortale lymfadenectomie • Met OS > 85%-88% is studie te klein om verschil in survival te meten

Geen pelviene lymfadenectomie bij laag risico ? • • • N = 385 (1999 – 2008) EE G 1 of 2 – FIGO (2009) IA - < 2 cm 80/385 lymfadenectomie (1/80 + LN) 11 recidieven – geen enkel thv LN Morbiditeit + kost hoger bij lymfadenectomie GEEN LYMFADENECTOMIE BIJ LOW RISK Dowdy Gynecol Oncol 2012

• Is lymfadenectomie wel nodig? • Indicaties Sentinel? • Indien lymfadenectomie, steeds ook para-aortale lymfadenectomie?
Sentinel bij endometriumcarcinoom? • Single institution series • Techniek cervicaal, subserosaal, hysteroscopisch Patent blue + Tc colloïd • Detection rates 44%-100% Kang Gynecol Oncol 2011

Sentinel bij endometriumcacinoom? • • • SENTI-ENDO N = 111 (9 centra) Patent blue + Tc colloïd cervicaal 5/111 SN para-aortaal 19/111 + pelv LN unilateraal geen vals negatieve SN wel 2 contralateraal en 1 para-aortaal vals negatief SENTINEL in STUDIEVERBAND Ballester Lancet Oncol 2011

• Is lymfadenectomie wel nodig? • Indicaties Sentinel? • Indien lymfadenectomie, steeds ook para-aortale lymfadenectomie?

Indicaties para-aortale lymfadenectomie VWOG • Positieve pelviene lymfeklieren CT – PET – VC - macroscopisch • Doorbraak serosa of aantasting adnex (stadium IIIA)
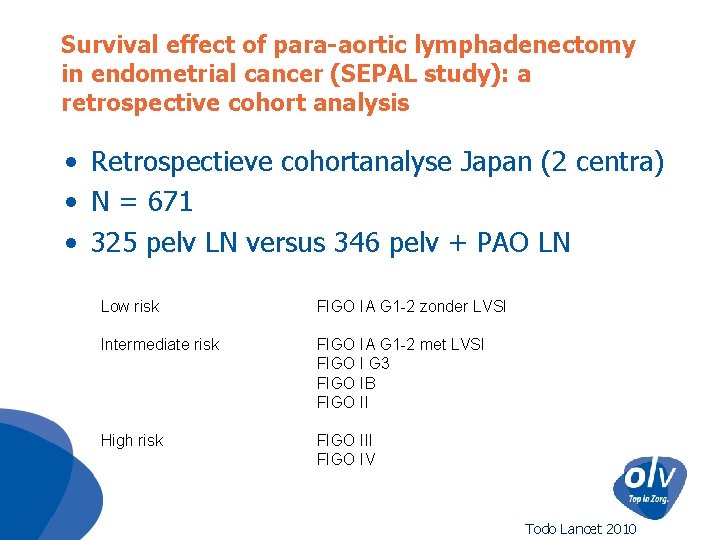
Survival effect of para-aortic lymphadenectomy in endometrial cancer (SEPAL study): a retrospective cohort analysis • Retrospectieve cohortanalyse Japan (2 centra) • N = 671 • 325 pelv LN versus 346 pelv + PAO LN Low risk FIGO IA G 1 -2 zonder LVSI Intermediate risk FIGO IA G 1 -2 met LVSI FIGO I G 3 FIGO IB FIGO II High risk FIGO III FIGO IV Todo Lancet 2010
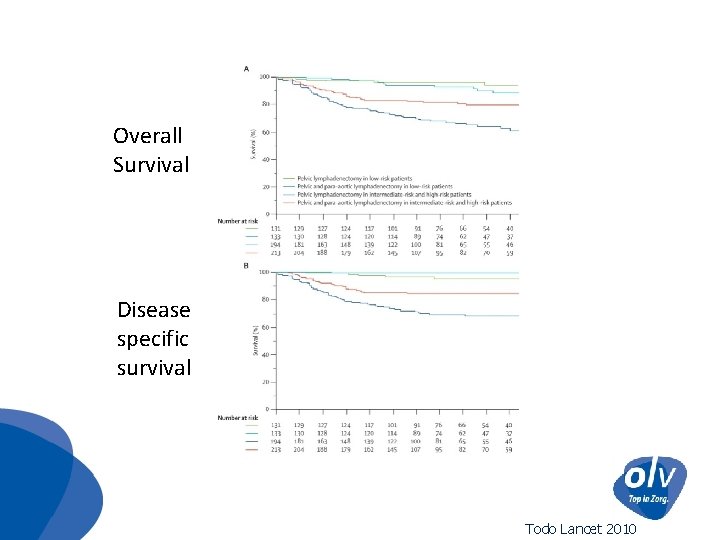
Overall Survival Disease specific survival Todo Lancet 2010
Survival effect of para-aortic lymphadenectomy in endometrial cancer (SEPAL study): a retrospective cohort analysis • Retrospectief • Vergelijking tussen 2 centra • Meer chemotherapie in pelvien + PAO LN groep • Meer radiotherapie in pelvien LN groep • Morbiditeit? Todo Lancet 2010
Para-aortale lymfadenectomie? • 281 intermediate and high risk • Pelvien + PAO lymfadenectomie • 63/281 positieve LN – 33% pelvien – 51% pelvien + PAO – 16% PAO • 77% (20/26) pos PAO LN = boven IMA Mariani Gynecol Oncol 2008
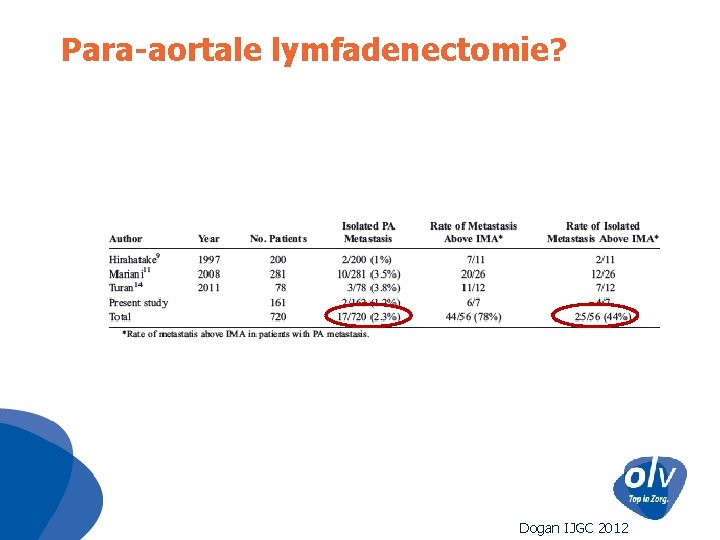
Para-aortale lymfadenectomie? Dogan IJGC 2012

Para-aortale lymfadenectomie? • Indien para-aortale lymfadenectomie, tot vena renalis • Uitbreiden indicaties para-aortale lymfadenectomie?

Ovariumcarcinoom


VWOG aanbevelingen epitheliaal ovariumcarcinoom • Stadium I : pelviene + PAO LND Uitzondering: IA G 1 • Stadium II-IV: pelviene + PAO LND bij alle patiënten waarbij optimale debulking mogelijk is

• Systematische pelviene en para-aortale lymfadenectomie bij alle patiënten met stadium II-IV bij wie optimale debulking mogelijk is?
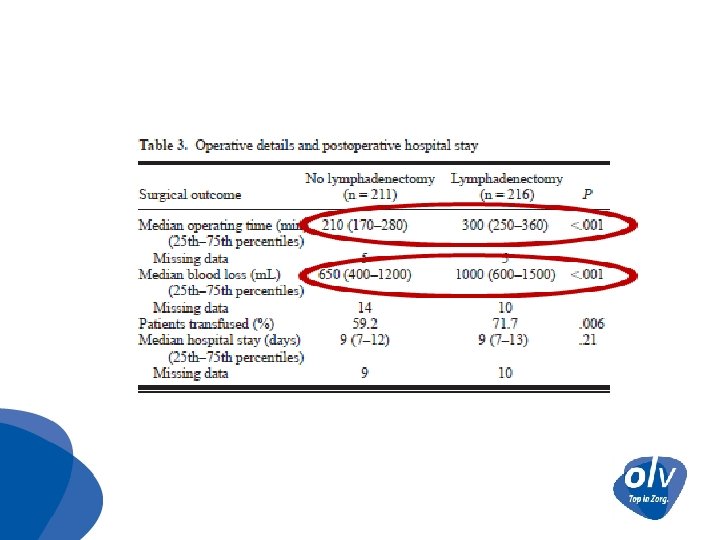
Systematic aortic and pelvic lymphadenectomy versus resection of bulky nodes only in optimally debulked advanced ovarian cancer: a RCT • N = 452 • Systematic lymphadenctomy versus resection of bulky nodes • Median N LN 51 versus 4 • 70% pos LN versus 42% Benedetti Panici JCO 2005
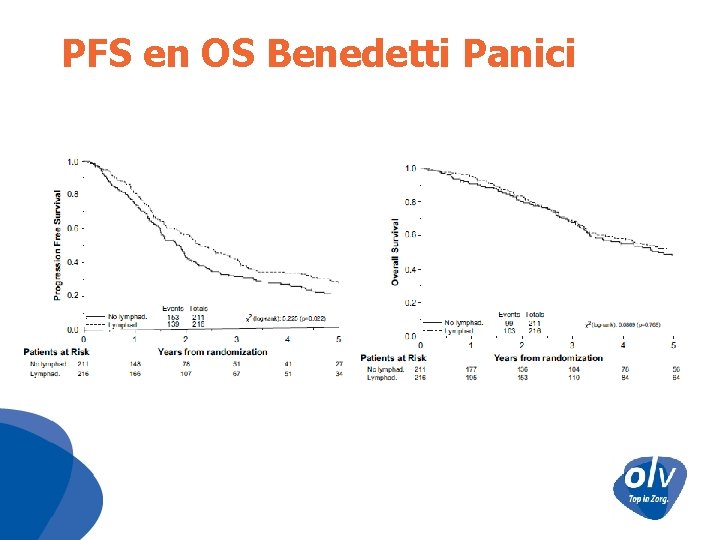
PFS en OS Benedetti Panici
Systematic aortic and pelvic lymphadenectomy versus resection of bulky nodes only in optimally debulked advanced ovarian cancer: a RCT • Significante verbetering PFS • Geen verschil OS • Slechts 37% complete debulking
Potential role of lymphadenectomy in advanced ovarian cancer: a combined exploratory analysis of 3 prospectively randomized phase III multicenter trials • • N= 1924 Retrospectief Geen randomisatie Beslissing tot lymfadenectomie ‘left to the discretion of each surgeon’ Du Bois JCO 2010
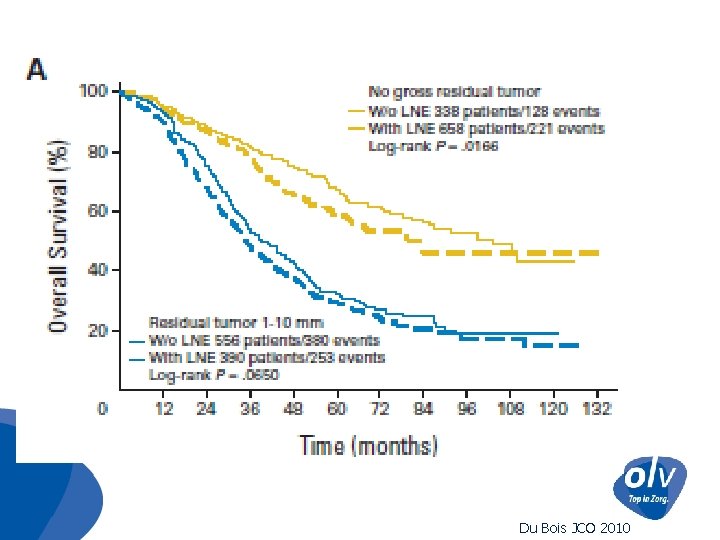
Du Bois JCO 2010
Potential role of lymphadenectomy in advanced ovarian cancer: a combined exploratory analysis of 3 prospectively randomized phase III multicenter trials “Our data suggest that lymphadenectomy should be restricted to patients in whom the removal of clinically suspect lymph node metastases improves the residual disease status” Resultaat 2 RCT’s afwachten

- Slides: 63