
Household Size Income Statements HSIS Child and Adult


























- Slides: 37
Household Size. Income Statements (HSIS) Child and Adult Care Food Program (CACFP) Wisconsin Department of Public Instruction Child Care Institutions Outside of School Hours Care Centers
Print these forms NOW: • Household Size-Income Statement • Parent Letter • Household Size-Income Scale Guidance Memorandum #1 C: http: //dpi. wi. gov/communitynutrition/cacfp/child-care/memos
Household Size-Income Statement (HSIS) • Required for children claimed free or reduced • Income form to determine financial need of child (free, reduced, non-needy) • Required for Household Size-Income Record
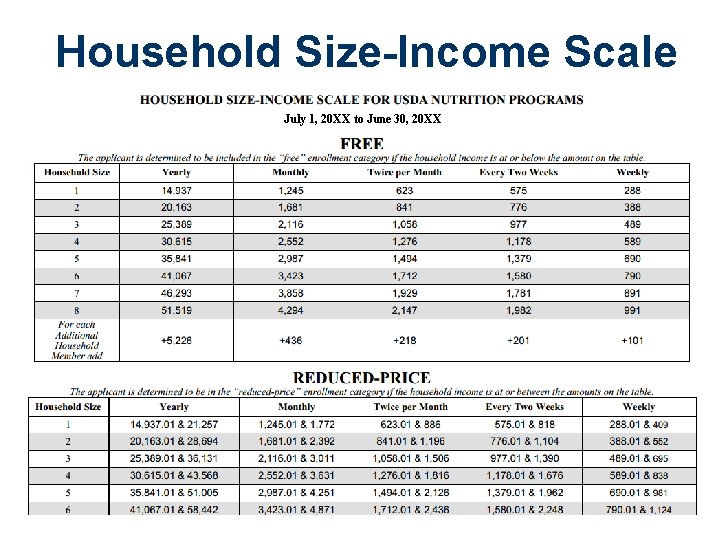
Parent Letter • Provides information about CACFP eligibility and completing the income statement • Income scale to help determine free or reduced eligibility
Household Size-Income Scale July 1, 20 XX to June 30, 20 XX
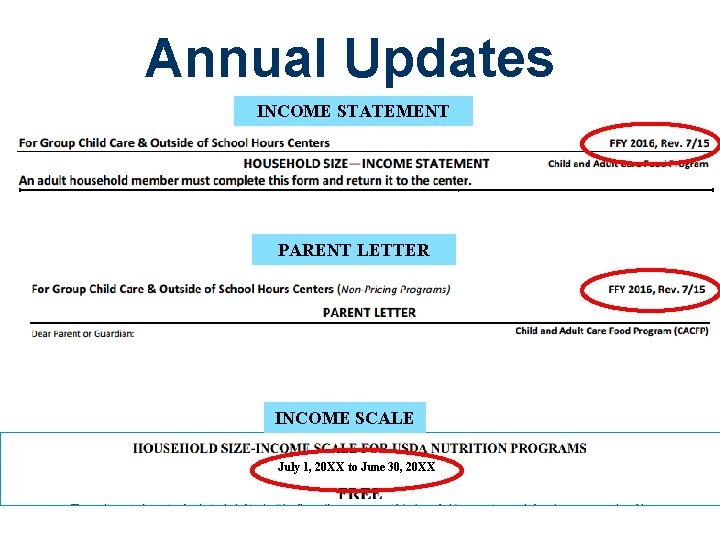
Annual Updates INCOME STATEMENT PARENT LETTER INCOME SCALE July 1, 20 XX to June 30, 20 XX
Distribute HSIS and Parent Letter • Begin CACFP • New families • Annual basis Collect HSIS back from parents
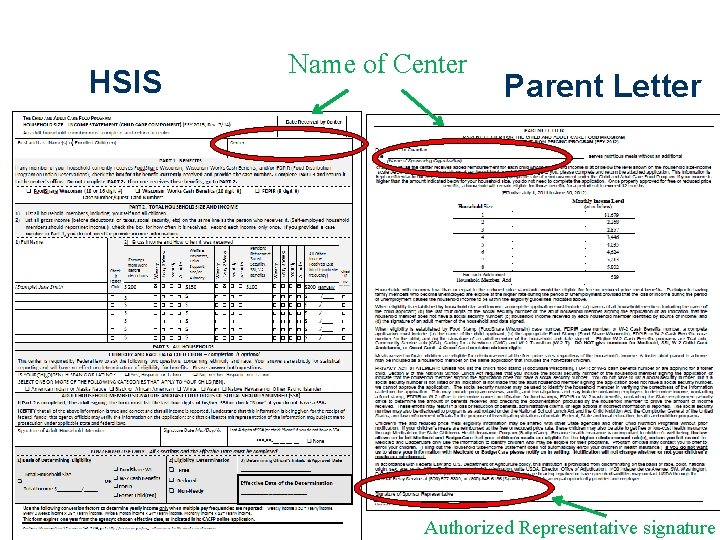
HSIS Name of Center Parent Letter Authorized Representative signature
REVIEWING AND DETERMINING HSIS
Determining Official • Reviews, approves and determines HSIS • • Authorized Representative Food Program Manager Director Owner • Completes HSIS For Center Use Only FOR CENTER USE ONLY – All 3 sections and the Effective Date must be completed 2)Eligibility Determination 3) Determining Official’s Initials & 1) Basis of Determining Eligibility Food. Share WI Approval Date Free _______________ Total Household Size _____ OR W-2 Cash Benefits __ Reduced Effective Date of the Determination FDPIR Total Income $_____/_____ Foster Child(ren) Non-Needy _______________
Names of Child(ren) The Child and Adult Care Food Program HOUSEHOLD SIZE—INCOME STATEMENT (CHILD CARE COMPONENT) (FFY 2015, Rev. 7/14) An adult household member must complete and return to center. First and Last Name(s) of Enrolled Child(ren) Jim Cobb, Jack Cobb, Joe Smith Center Peaceful Playhouse Day Care Center • Child’s first and last name • Siblings may be listed on one HSIS • If different last names, list the first and last name of each child
Part 1: Benefits PART 1: BENEFITS If any member of your household currently receives Food. Share Wisconsin, Wisconsin Works Cash Benefits, and/or FDPIR (Food Distribution Program on Indian Reservations), check the box for the benefit currently received and provide the case number. Complete PART 3 and return it to the center’s office. Do not complete PART 2. If no one receives these benefits, go to PART 2. Food. Share Wisconsin (10 or 16 Digit ) Wisconsin Works Cash Benefits (10 Digit ) FDPIR (9 Digit #) Case Number/Quest Card Number: _____________________ • Automatically qualifies a child as FREE • SNAP (Food. Share Wisconsin) • Wisconsin Works (W-2) Cash Benefits • FDPIR (Food Distribution Program on Indian Reservation)
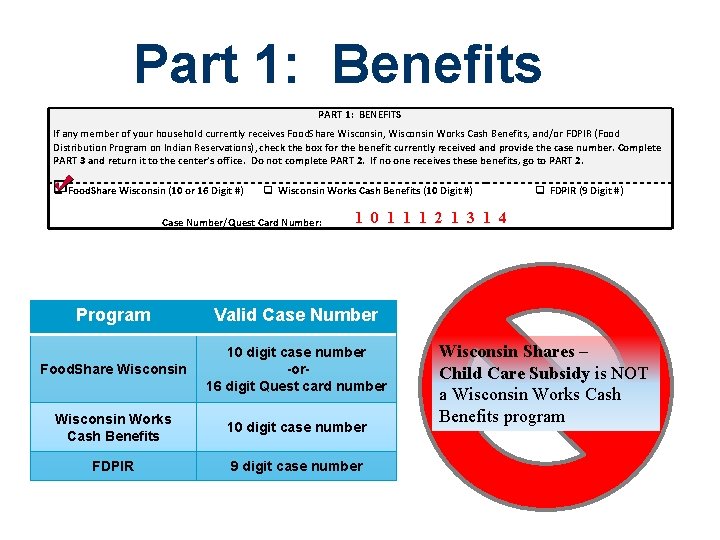
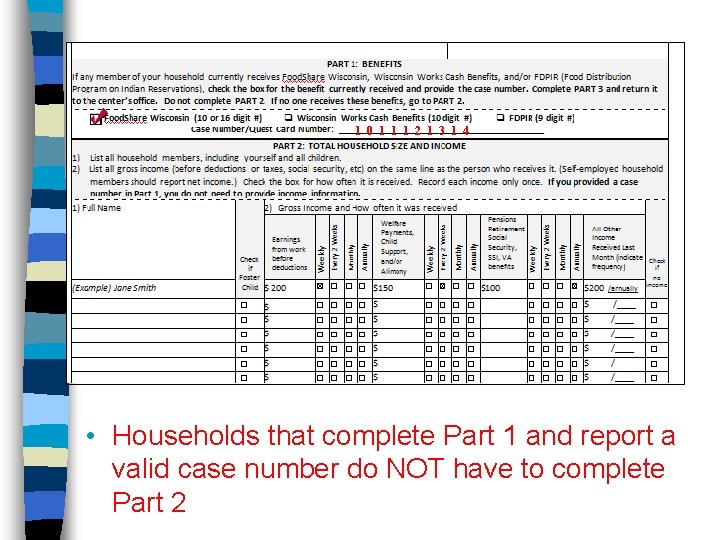
Part 1: Benefits PART 1: BENEFITS If any member of your household currently receives Food. Share Wisconsin, Wisconsin Works Cash Benefits, and/or FDPIR (Food Distribution Program on Indian Reservations), check the box for the benefit currently received and provide the case number. Complete PART 3 and return it to the center’s office. Do not complete PART 2. If no one receives these benefits, go to PART 2. Food. Share Wisconsin (10 or 16 Digit #) Wisconsin Works Cash Benefits (10 Digit #) FDPIR (9 Digit #) 1 0 1 1 1 2 1 3 1 4 Case Number/Quest Card Number: _____________________ Program Valid Case Number Food. Share Wisconsin 10 digit case number -or 16 digit Quest card number Wisconsin Works Cash Benefits 10 digit case number FDPIR 9 digit case number Wisconsin Shares – Child Care Subsidy is NOT a Wisconsin Works Cash Benefits program
ADULT HOUSEHOLD MEMBER SIGNATURE AND LAST FOUR DIGITS OF SOCIAL SECURITY NUMBER (SS#) If Part 2 is completed, the adult signing the form must list the last four digits of his/her SS# or check “None” if you do not have a SS#. I CERTIFY that all of the above information is true and correct and that all income is reported. I understand that this information is being given for the receipt of federal funds; that agency officials may verify the information on the application; and that deliberate misrepresentation of the information may subject me to prosecution under applicable state and federal laws. Last 4 digits of SS# (or check “None” if you do not have a SS#) Signature Date Mo. /Day/Yr. Signature of Adult Household Member Randall Cobb 10/16/20 XX ***-**-__ __ None FREE! FOR CENTER USE ONLY – All 3 sections and the Effective Date must be completed 2)Eligibility Determination 3) Determining Official’s Initials & 1) Basis of Determining Eligibility Food. Share WI Approval Date Free _______________ Total Household Size _____ OR W-2 Cash Benefits __ Reduced Effective Date of the Determination FDPIR Total Income $_____/_____ Foster Child(ren) Non-Needy _______________
1 0 1 1 1 2 1 3 1 4 • Households that complete Part 1 and report a valid case number do NOT have to complete Part 2
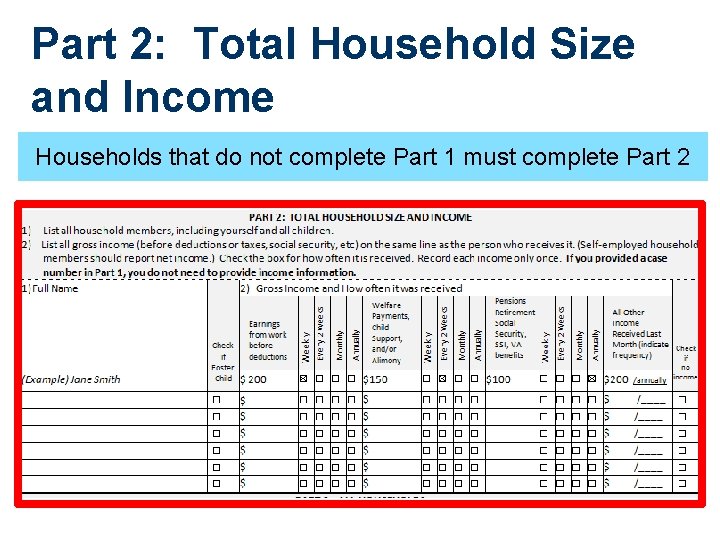
Part 2: Total Household Size and Income Households that do not complete Part 1 must complete Part 2
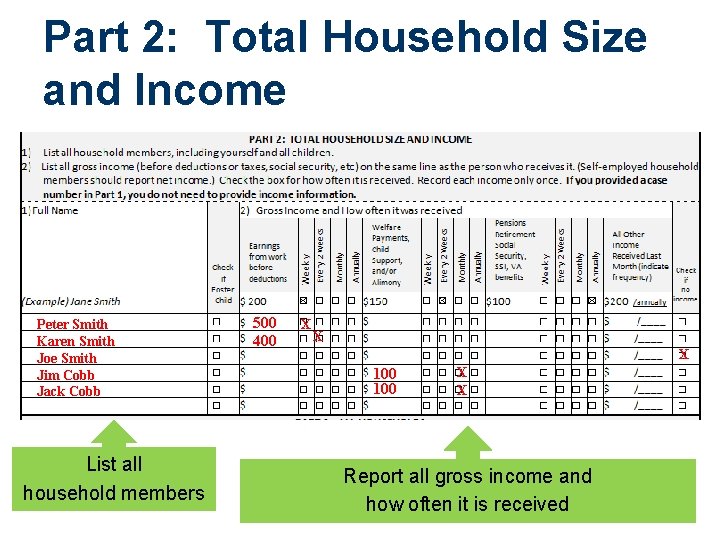
Part 2: Total Household Size and Income Peter Smith Karen Smith Joe Smith Jim Cobb Jack Cobb List all household members 500 400 X X X 100 X X Report all gross income and how often it is received
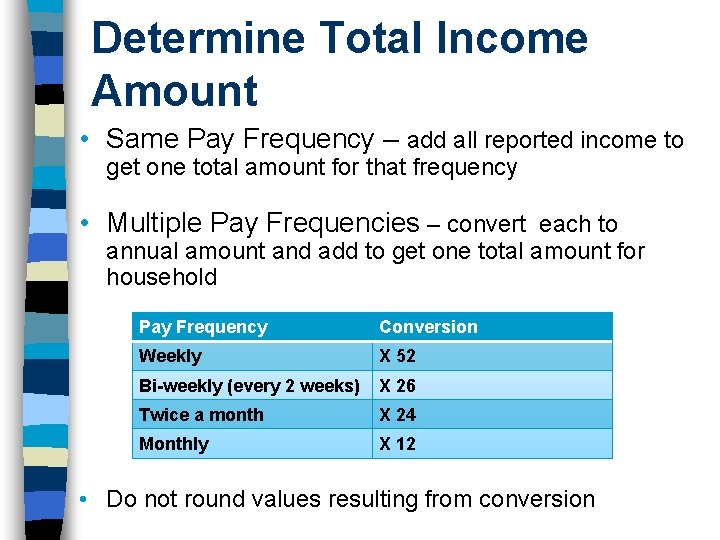
Determine Total Income Amount • Same Pay Frequency – add all reported income to get one total amount for that frequency • Multiple Pay Frequencies – convert each to annual amount and add to get one total amount for household Pay Frequency Conversion Weekly X 52 Bi-weekly (every 2 weeks) X 26 Twice a month X 24 Monthly X 12 • Do not round values resulting from conversion
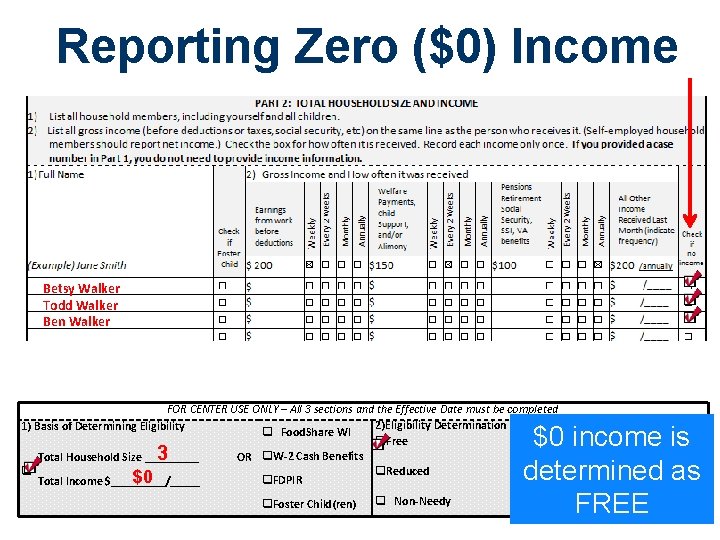
Reporting Zero ($0) Income Betsy Walker Todd Walker Ben Walker FOR CENTER USE ONLY – All 3 sections and the Effective Date must be completed 2)Eligibility Determination 3) Determining Official’s Initials & 1) Basis of Determining Eligibility Food. Share WI Approval Date Free _______________ Total Household Size _____ OR W-2 Cash Benefits __ Reduced Effective Date of the Determination $0 FDPIR Total Income $_____/_____ 3 Foster Child(ren) Non-Needy $0 income is determined as _______________ FREE ______
Households above Income Eligibility Guidelines • Determined as Non-needy • Not required to turn in a HSIS Above Guidelines N/A
Foster Child(ren) • Foster children are eligible for free meals when the child’s care and placement is responsibility of the State or the child is placed with a caretaker by a court of law A child permanently placed in a home is considered a member of the household, not a foster child
Households with foster and non-foster children • Determine non-foster children based on benefits or household size and income • Can include foster child as a household member
Kinship Care is Not Foster Care • Kinship Care is when children reside with a relative rather than be placed in a foster home or other type of out-of-home placement • Must complete HSIS • Part 1 – qualifying assistance program OR • Part 2 – report income
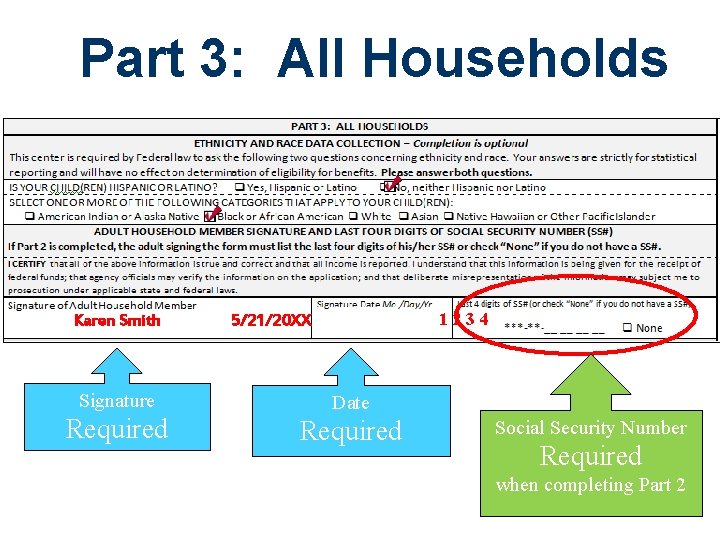
Part 3: All Households Karen Smith 5/21/20 XX 1 2 3 4 Signature Date Required Social Security Number Required when completing Part 2
HSIS is Incomplete When… Part 1: Benefits • Box indicating benefit program is not checked • Missing or invalid case number Part 2: Total Household Size and Income • Parent does not report income and the “Check if no income” box is not checked • Parent does not indicate pay frequency • Missing household members/income Part 3: All Households • Missing parent/guardian signature • Parent/guardian does not date the form • Missing social security number when Part 2 is completed These statements are NON-NEEDY until complete information is obtained
Obtain Missing Information • Return to or contact parent • Get info over the phone (not parent signature/date) • Record missing information • Who provided info • Date • Your initials • Any changes • Cross off invalid info • Do not use white out HSIS is Non-Needy until it is complete
HSIS DETERMINATION AND EFFECTIVE DATE
HSIS Effective Date CHOOSE ONE • Date of Determining Official Approval • Household Member Signature Date
Date of Determining Official Approval Date DO reviews, determines and approves the HSIS FOR CENTER USE ONLY – All 3 sections and the Effective Date must be completed 2)Eligibility Determination 3) Determining Official’s Initials & 1) Basis of Determining Eligibility Food. Share WI Approval Date Free MB 10/20/20 XX _______________ Total Household Size _____ OR W-2 Cash Benefits __ Reduced Effective Date of the Determination FDPIR Total Income $_____/_____ Foster Child(ren) Non-Needy _______________ 10/XX ______
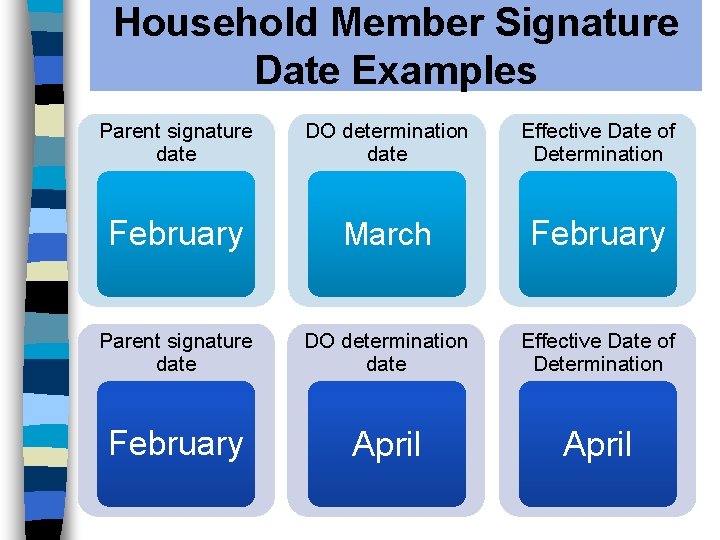
Household Member Signature Date the Household Size-Income Statement was signed and dated by the adult household member Karen Smith 4/16/20 XX 1234 FOR CENTER USE ONLY – All 3 sections and the Effective Date must be completed 2)Eligibility Determination 3) Determining Official’s Initials & 1) Basis of Determining Eligibility Food. Share WI Approval Date Free ________________ W-2 Cash Benefits MB 5/21/20 XX Total Household Size _____ OR Reduced Effective Date of the Determination FDPIR Total Income $_____/_____ Foster Child(ren) Non-Needy 4/XX ________________ HSIS must be complete at time of submission for this method to apply Agency may NEVER date the income statement for the parent/guardian
Household Member Signature Date Examples Parent signature date DO determination date Effective Date of Determination February March February Parent signature date DO determination date Effective Date of Determination February April
Effective Date of Incomplete Forms Completed AFTER Initial Submission • After ALL missing information is obtained • Determine the form free, reduced or non-needy FOR CENTER USE ONLY – All 3 sections and the Effective Date must be completed 2)Eligibility Determination 3) Determining Official’s Initials & 1) Basis of Determining Eligibility Food. Share WI Approval Date Free MB 12/20/20 XX _______________ Total Household Size _____ OR W-2 Cash Benefits __ Reduced Effective Date of the Determination FDPIR Total Income $_____/_____ Foster Child(ren) Non-Needy 12/XX _______________
Using Date of Determination for Entire Federal Fiscal Year • Must choose one method for ALL complete HSIS • Indicate in online contract • Consistently apply to all HSIS for entire federal fiscal year (October 1 – September 30)
HSIS Valid for 12 Months • From Effective Month of Determination 10/20 XX Example nth o M e v Effecti of ion t a n i m Deter Oct X Nov Dec • Effective Month of Determination = October • HSIS will expire October 31 st of following year Form Expires Jan Feb Mar Apr May Jun Jul Aug Sep Oct 31 st
Collect New HSIS Annually • Collect new statements from all families • Same time each year • Prevent incorrectly reporting a child as Free or Reduced with an expired HSIS on file • Do this in October!
What to do Next • Watch Household Size-Income Record (HSIR) webcast
Thank you! The U. S Department of Agriculture prohibits discrimination against its customers, employees, and applicants for employment on the bases of race, color, national origin, age, disability, sex, gender identity, religion, reprisal, and where applicable, political beliefs, marital status, familial or parental status, sexual orientation, or all or part of an individual’s income is derived from any public assistance program, or protected genetic information in employment or in any program or activity conducted or funded by the Department. (Not all prohibited bases will apply to all programs and/or employment activities. ) If you wish to file a Civil Rights program complaint of discrimination, complete the USDA Program Discrimination Complaint Form, found online at http: //www. ascr. usda. gov/complaint_filing_cust. html, or at any USDA office, or call (866) 632 -9992 to request the form. You may also write a letter containing all of the information requested in the form. Send your completed complaint form or letter to us by mail at U. S. Department of Agriculture, Director, Office of Adjudication, 1400 Independence Avenue, S. W. , Washington, D. C. 20250 -9410, by fax (202) 690 -7442 or email at program. intake@usda. gov. Individuals who are deaf, hard of hearing or have speech disabilities may contact USDA through the Federal Relay Service at (800) 877 -8339; or (800) 845 -6136 (Spanish). USDA is an equal opportunity provider and employer.