
Hb A 1 c Glycated proteins Monitoring long
Hb. A 1 c
Glycated proteins • Monitoring long term glucose control • Retrospective index of the integrated plasma glucose • Is not subject to the wide fluctuations • Adjunct to blood glucose determination • not for the diagnosis of diabetes mellitus

Hemoglobin • Human adult hemoglobin – Hb. A 97%of the total, Hb. A 2 2. 5%, Hb. F 0. 5% • Minor hemoglobins – Hb. A 1 a Hb. A 1 b, Hb. A 1 c collectively referred to as Hb. A 1 – fast hemoglobins

• Glycation – Nonenzymatic addition of a sugar residue to amino groups – Neoglycoprotein, Glycation • Hb. A 1 a 1; – fructose 1, 6 diphosphate • Hb. A 1 a 2 – glucose 6 phosphate • Hb. A 1 b – pyruvic acid • Hb. A 1 C – glucose – major fraction 80% of Hb. A 1
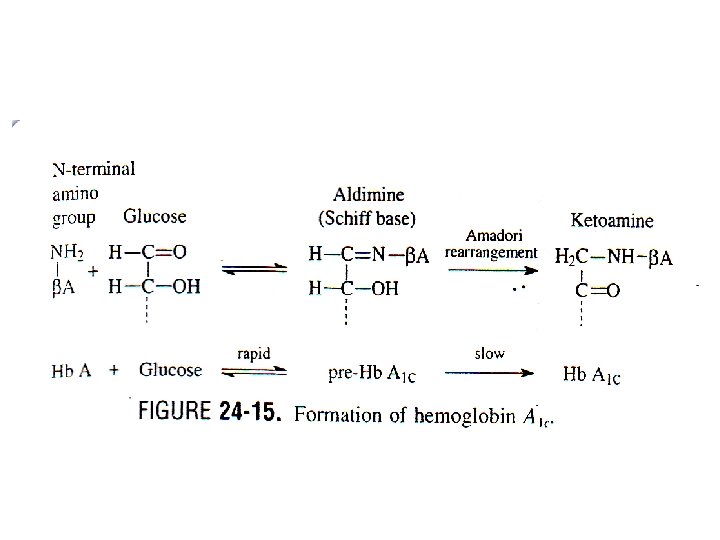

• Hb A 0 – Glycation at lysine residues , or α chain – measured by affinity chromatography • Blood levels of Glycated hemoglobin – Depends • on the life span of red cells • the blood glucose concentration

Glycated Hb • Free of day to day fluctuations • Unaffected by exercise or recent food ingestion • Recent glucose values provide larger contributions to glycated Hb than earlier values. • The plasma glucose in the preceding one month makes up 50% of the Hb. A 1 c whereas days 60120 determine only 25%. • blood glucose over the preceding 6 -8 week
Interpretation of Glycated hemoglobin • sources of errors – Low Glycated hemoglobin • hemolytic disease • shortened red blood cell survival • recent blood loss • High Glycated hemoglobin – Iron deficiency anemia – the effect of hemoglobin variants such as Hb F, S and C

• Carbamylated Hb • Labile intermediates pre Hb A 1 C, Schiff base • depends on the specific method of analysis • Labile fraction – changes rapidly with acute changes in blood glucose – spuriously alter Glycated Hb values

• Pre-Hb A 1 c – amounts to 5 -8% of total Hb A 1 in normal people – 8 -30 % in patients with diabetes • Glycated Hb should be routinely monitored at least every 3 month in all insulin treated patients

Clinical utility of Glycated Hb • For glycemic control to decrease long term complications of diabetes mellitus • To reduce the risk of retinopathy, nephropathies, and neuropathy • to delay the onset and to slow the progression of these complications

• Study; a 10% lower Hb A 1 c was assocated with a 45% lower risk of retinopathy • An index of long term blood glucose concentration in patients with diabetes mellitus • The goal is blood glucose control
Methods for the determination of glycated hemoglobin • selection of method – Including sample volume, patient population, and cost • most widely used technique – affinity chromatography In the United States • methods based on charge
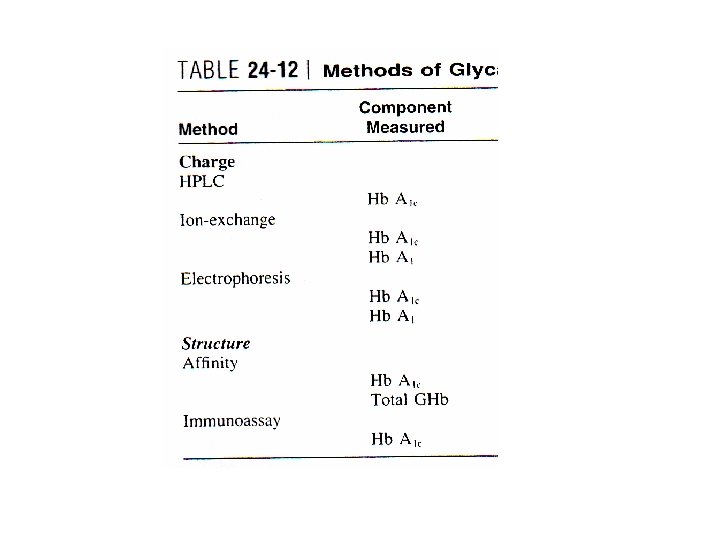
• Total glycated hemoglobin (A 1+A 0), Hb. A 1 (Hb. A 1 a 1+A 1 a 2+A 1 b+A 1 c). • In Europe – HPLC and ion-exchange with less use of affinity chromatography
Ion exchange chromatography • Hemoglobin variants are separated based on charge difference • Bed – cation exchange resin (negatively charged) • Procedure – hemolysis of the patient sample, a buffer is applied and the eluent collected. – Elution • The ionic strength and p. H of the eluent buffer are selected so that glycated hemoglobins are less positively charged

Ion exchange chromatography • A second buffer of different ionic strength to elute the more positively charged main Hb fraction – this is read as total Hb • glycated Hb is expressed as percentage of total Hb
Ion exchange chromatography • Modifications – Flow rates are accelerated by centrifugation – Batch technique • agitation of resin with hemolysate to adsorb Hb A – Using two different buffers to separate Hb. A 1 a+b from A 1 c
Factors affecting Ion exchange chromatography • The temperature of the reagents and columns – thermostatting the columns – applying a correction factor • Control of p. H and ionic strength • Sample storage condition • different minicolumns exhibit wide variability in performance
Factors affecting Ion exchange chromatography • The labile pre-Hb A 1 fraction – produce elevated results • Hb. F – elutes with Hb. A 1 produce falsely elevated results • Alteration of charge on Hb – carbamylated Hb, alcoholism, lead poisoning and acetylated Hb • Hb. S, Hb. C and their glycated derivatives; misleading low values for Hb. A 1
HPLC • The principle – Cation exchange chromatography • Procedure – Application of hemolysate – Elution • stepped elution – phosphate buffer of increasing ionic strength – Detection • absorbance at 415 and 690 nm
HPLC • Good resolution of Hb A 1 a+b from Hb. A 1 c – with sodium phosphate-cyanide buffer at different p. H values • Elution as one peak (Hb. A 1) – A rapid system – evaluation • with a dual wavelength detector at 405 for Hb. A 1 and 546 for Hb. A – Interference • Hb variants Hb C Hb F carbamylated and acetylated forms of Hb
HPLC • Quantification – Integrating the area under the peaks • An automated system – Step gradients • using three phosphate buffers of increasing ionic strength – Detection • at 415 and 690 nm – both Hb A 1 c and Hb. A 1 is reported – Variant Hb are resolved (Hb F, S and C)
HPLC • HPLC methods – have excellent precision – recommended as reference method • interference – Carbamylated and acetylated Hb and possibly other derivatives • slightly higher results

Electrophoresis • Agar gel at p. H 6. 3 resolution of Hb A and Hb. A 1 • The gel contains negatively charged moieties • Quantification performed by scanning densitometry at 415 nm • Hb. A 1 c is also commercially available • Results agree with that of HPLC or column but are less precise • Minor variations in p. H, ionic strength or temperature have little effect on results • Hb. F migrates the same as Hb. A 1 and causes falsely elevated value • Hb C and S do not • The labile form should be removed
Isoelectric focusing • Principle; migration in gel containing a p. H gradient • Matrix; acrylamide gel • p. H range of 6 -8 • On completion the gels are fixed and then scanned by a microdensitometer • Hb A 1 c resolved from Hb. A 1 a, A 1 b, S and F • Results showed close agreement with other methods • The equipment is expensive

Immunoassay • Anti serum raised against purified human Hb. A 1 c • Available methods • RIA format • Enzyme immunoassay format • Agglutination inhibition
Immunoassay • Antibodies raised against the Amadori product of glucose (ketoamine linkage) plus the first few amino acids at the Nterminal of β-chain • Agglutinator; a synthetic polymer containing multiple copies of the immunoreactive portion of Hb. A 1 c, light scattering
Immunoassay • Excellent precision • The antibodies do not recognize labile intermediates or other glycated hemoglobins • Other Hb variants such as Hb. F, A 2, S, carbamylated Hb are not detected. • Correlate well with HPLC but exhibit lower values • Due to different calibration, detection by HPLC of substances other than Hb. A 1 c
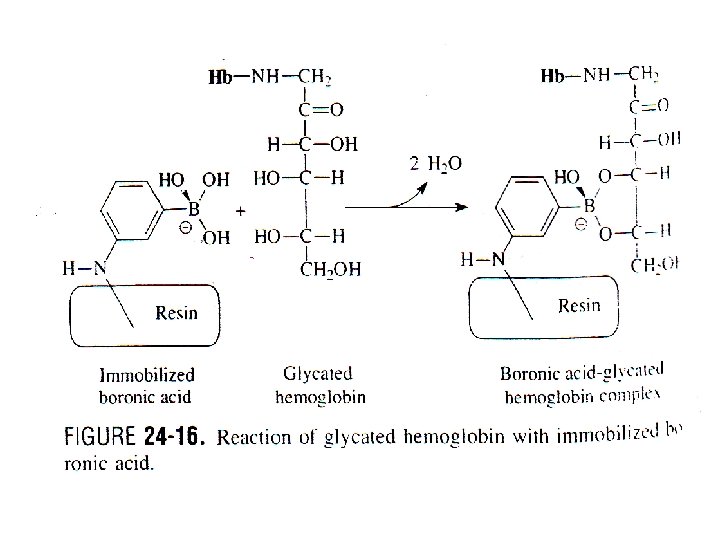
Affinity chromatography • Principle – m-aminophenyl boronic acid is immobilized by cross linking to beaded agarose or other matrix (e. g. , glass fiber) – The boronic acid react with the cis-diol groups of glucose – Dissociation • By Sorbitol – Detection • Absorbance of bound and non bound fractions measured at 415 nm
Affinity chromatography • Advantage – No interference non glycated Hb – Negligible interference from the labile intermediate form – Unaffected by variations in temperature – Reasonably good precision – Hemoglobin variants • Hb F, S, and C produce little effect
Affinity chromatography • Report – Affinity methods measure total glycated Hb – Commercially available systems are calibrated to also report a Hb. A 1 c standardized value

• Specimen – Patients need not be fasting – Venous blood containing EDTA, oxalate, or fluoride – Whole blood my be stored at 4°C for up to 1 week – storage at -20°C or 80°C is not recommended

• heparinized samples – should be assayed within 2 days and may not be suitable for other methods (electrophoresis)

• Preparation of hemolysate – Packed cell • Centrifuge – remove the plasma and buffy coat • Wash with saline – Removal of labile glycated Hb • Incubation of RBC in saline • in buffer solutions at p. H 5 to 6 • by dialysis or ultrafiltration of hemolysate

• Preparation of column – Bring the column to room temperature – Remove the caps – Pour off upper buffer – Add equilibration buffer let drain and discard the eluate

Assay standardization • The absence of a reference method and a single glycated Hb standard has generated confusion • Interlaboratory comparisons are not possible • calibration – significantly improves precision and facilitates direct comparison of results obtained by different methods

Assay standardization • Calibrator – lyophilized hemolysate assayed by a precise HPLC method for Hb A 1 c • adoption of a universal standard will enhance the clinical utility of glycated Hb
Reference interval • Values for glycated Hb are expressed as a percentage of total Hb • Three major glyacted Hb species – Hb. A 1, Hb. A 1 c, or total glycated Hb • Reference intervals vary depending on – method – the glycated Hb component – whether the labile fraction is included
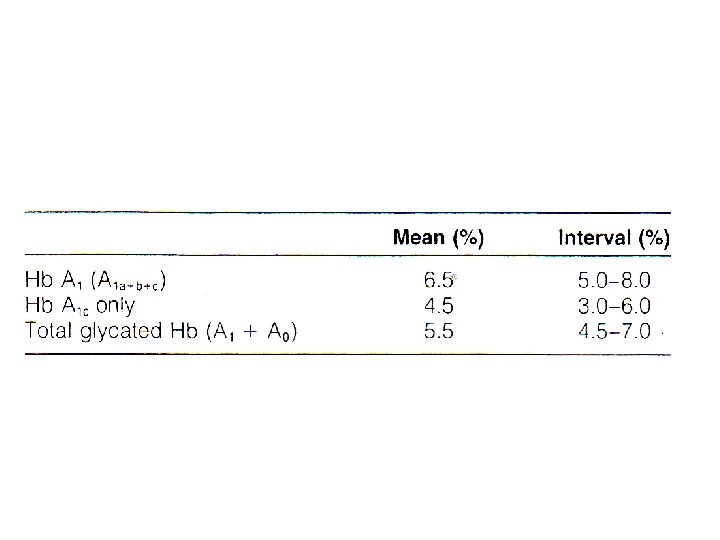

Reference intervals • Reference intervals show some increase with age • poorly controlled diabetes – values may extent to twice the upper limit of the reference interval • Values grater than 20% should prompt further studies • There is no specific level of Hb. A 1 c below which the risk of diabetic complications is eliminated completely

Reference intervals • Each laboratory should establish its own nondiabetic reference interval • Assay precision is important; each 1% change = 25 -35 mg/dl change
- Slides: 43