
Haematological Neoplasia l l l Leukemias Acute Chronic




























- Slides: 66
Haematological Neoplasia: l l l Leukemias - Acute & Chronic Lymphomas - Hodgkins & Non-Hodgkins (T cell, B cell, histiocytic & others) Premalignant Conditions: Myeloproliferative syndromes (MPS) Myelodysplastic syndromes (MDS) 1
Lymphomas
Introduction: l l l Neoplastic lymphoid proliferation Two types – Hodgkins & Non-Hodgkins. Fever, lymphadenopathy, Immunodeficiency / autoimmune syndrome Viral, genetic, unknown etiology. Lack of programmed cell death - Apoptosis 3
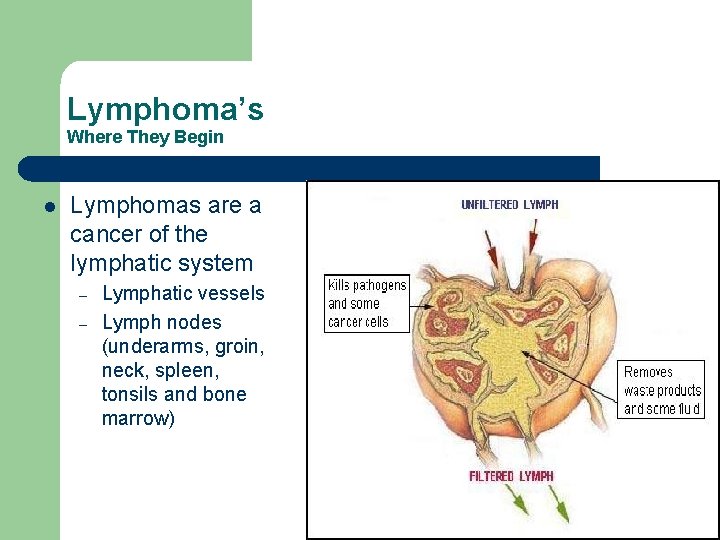
Lymphoma’s Where They Begin l Lymphomas are a cancer of the lymphatic system – – Lymphatic vessels Lymph nodes (underarms, groin, neck, spleen, tonsils and bone marrow) 4
Lymphoma’s Where They Begin l l The Lymphatic system is our bodies main fight against infection Lymphocytes (B-cell and T-cell) – – Carried through our lymphatic system and help our bodies fight infection Lymphocytes are carried through the lymph vessels as well as the blood stream, so cancer can start in nodes and spread anywhere throughout the body. 5
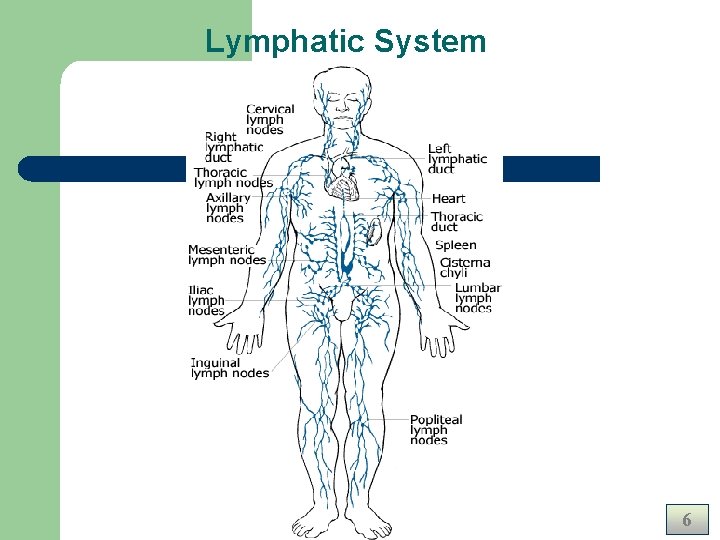
Lymphatic System 6
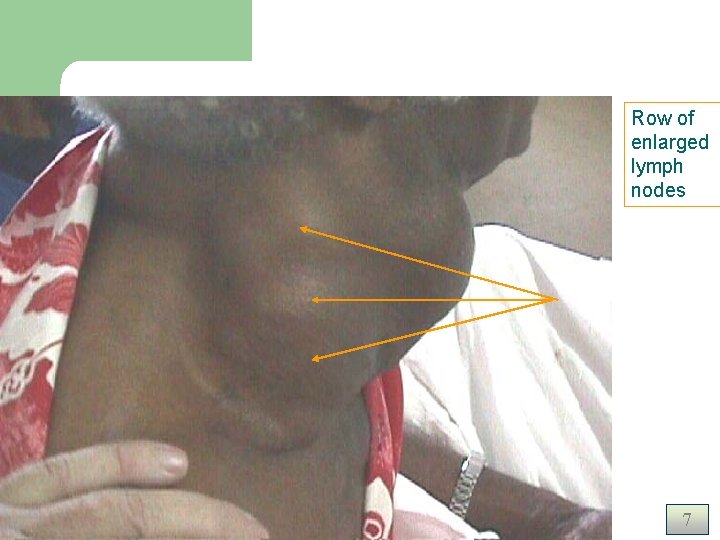
Lymphoma Row of enlarged lymph nodes 7
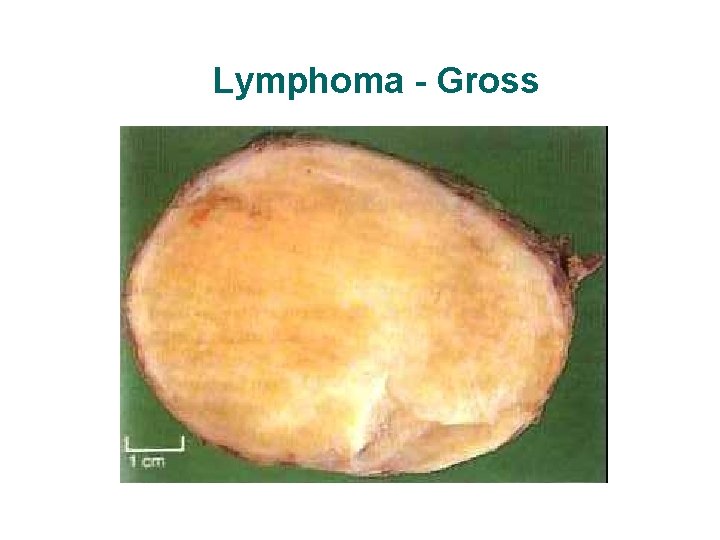
Lymphoma - Gross
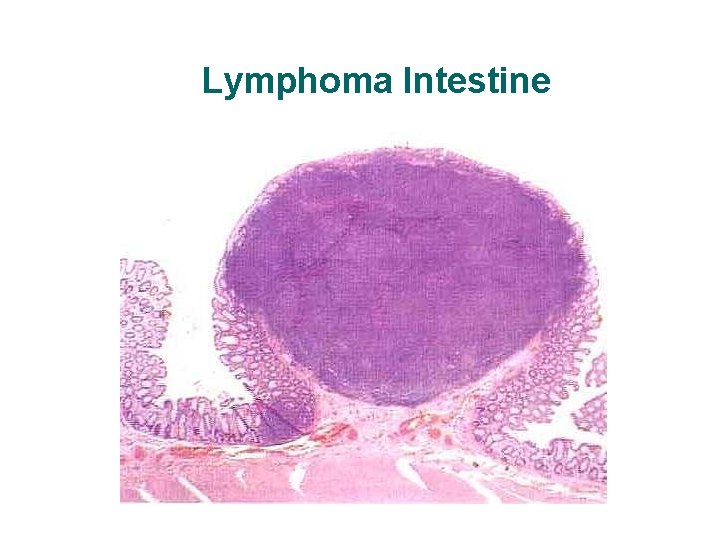
Lymphoma Intestine
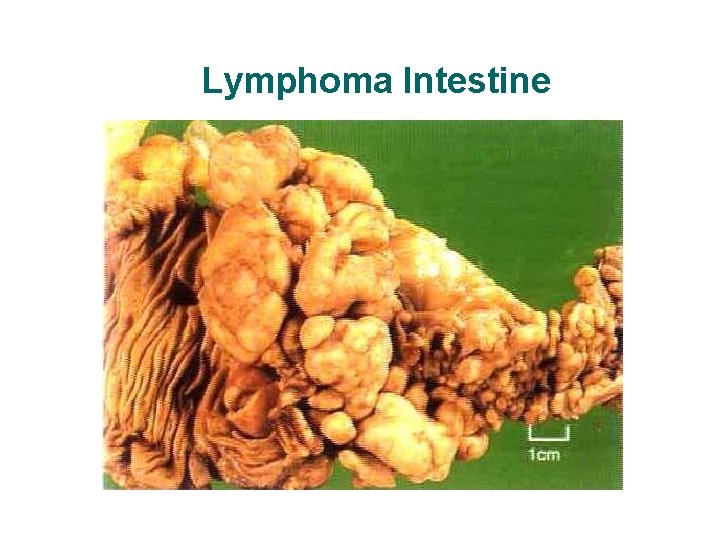
Lymphoma Intestine
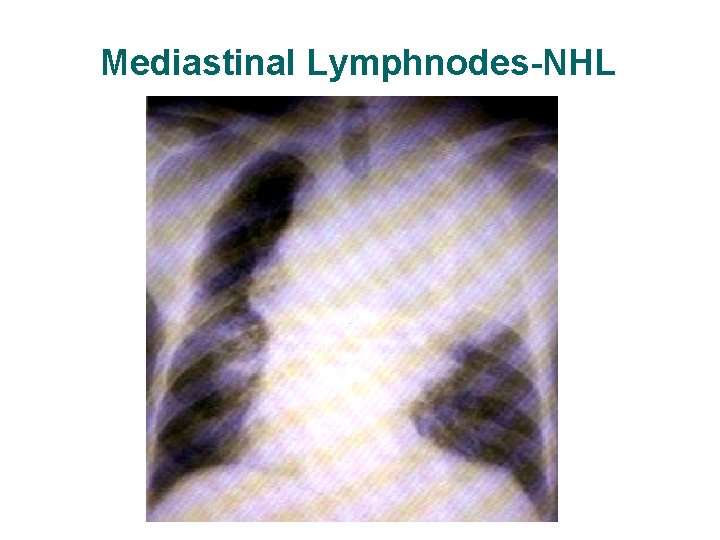
Mediastinal Lymphnodes-NHL
Hodgkins Lymphoma (HL)
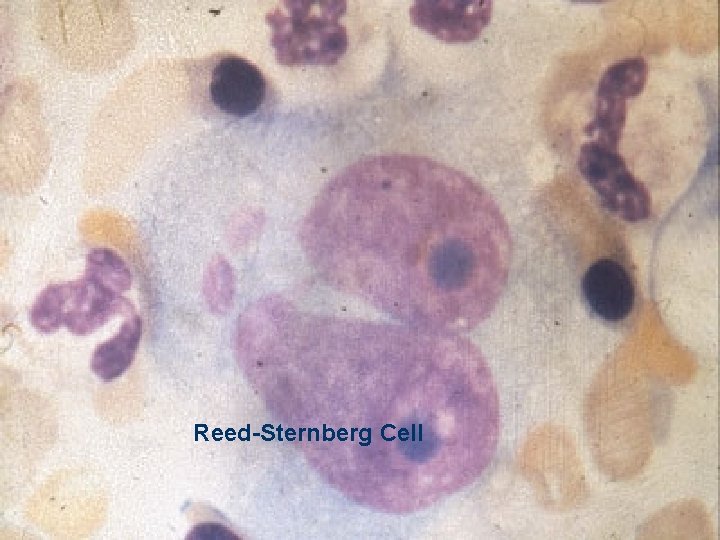
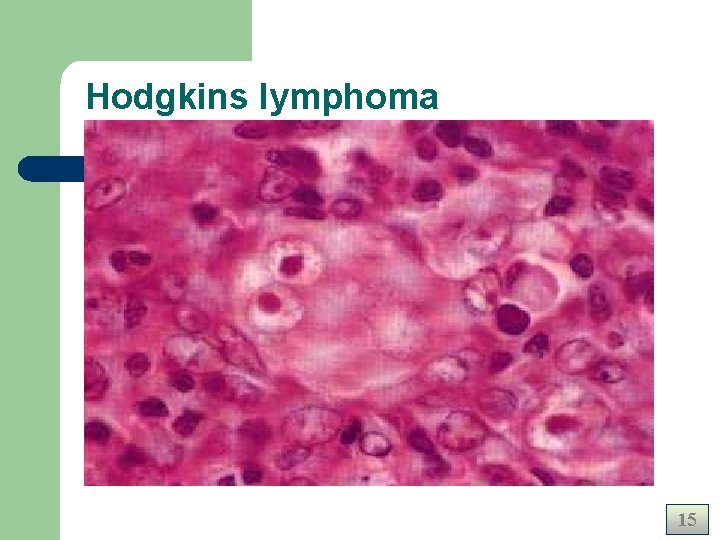
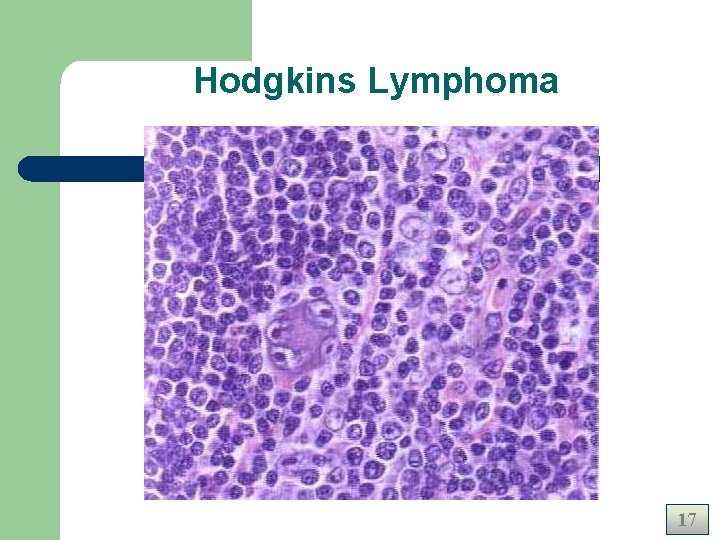
Hodgkin’s Disease l l l Is a malignant lymphoma characterized by the presence of atypical, multinucleated giant cell (Reed. Sternberg cell) The disease is slightly more common in men Most patients have asymptomatic lymphadenopathy at the time of diagnosis – The initial site of nodal involvement is: l l l Cervical (65 -80%) Axillary (10 -15%) Inguinal (6 -12%) 13
Reed-Sternberg Cell 14
Hodgkins lymphoma 15
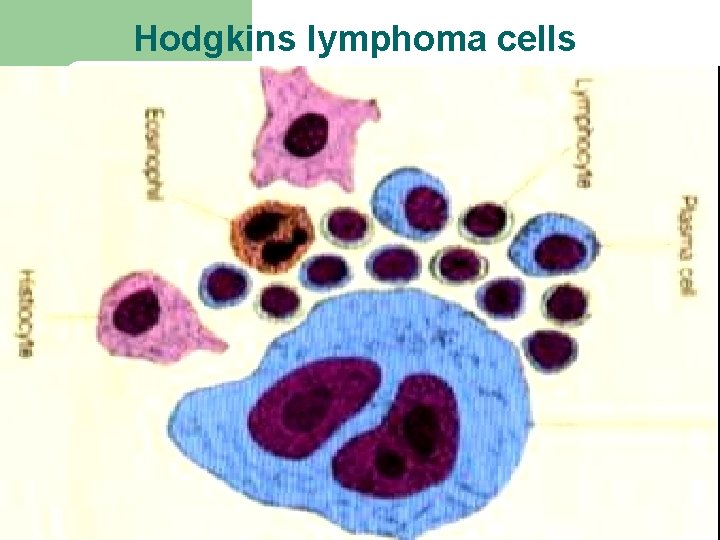
Hodgkins lymphoma cells 16
Hodgkins Lymphoma 17
Causes/Risk Factors l l l The exact cause of Hodgkin’s disease is unknown. Also, a virus called Epstein-Barr may be involved with an increased risk of Hodgkin’s. Also, Agent Orange, used during the Vietnam War is linked with the development of Hodgkin’s. Siblings of a Hodgkin’s victim are more at risk for developing the disease. It is more common for men to have the disease. Hodgkin’s occurs most often in those between 15 and 34 or over the age of 55. 18
Classification of Hodgkin’s Disease l Treatment depends on – – – The anatomic distribution of the disease and the presence or absence of specific symptoms The stage of the disease The histopathologic subtype 19
Classification of Hodgkin’s Disease l The Rye classification – Based on four histopathologic subtypes l Lymphocytes predominance l Nodular sclerosis l Mixed cellularity l Lymphocytes depletion 20
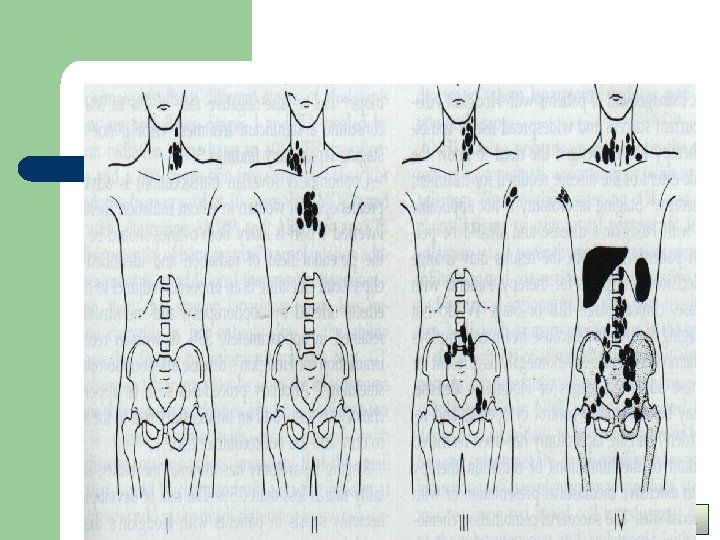
Classification of Hodgkin’s Disease l Histopathologic diagnosis – – l Is made by lymph node biopsy Nodes from the lower cervical or axillary areas provide the best tissue for evaluation Ann Arbor staging classification – A classification based on anatomic distribution of the disease l Stage I disease – Stage IV disease 21
22
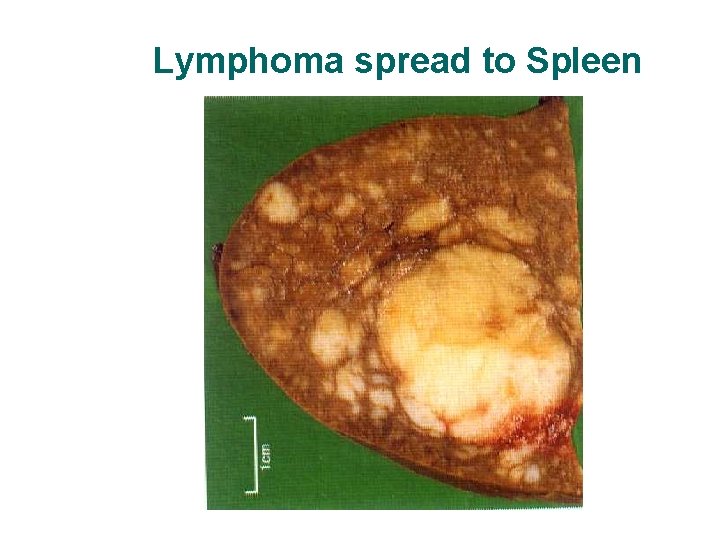
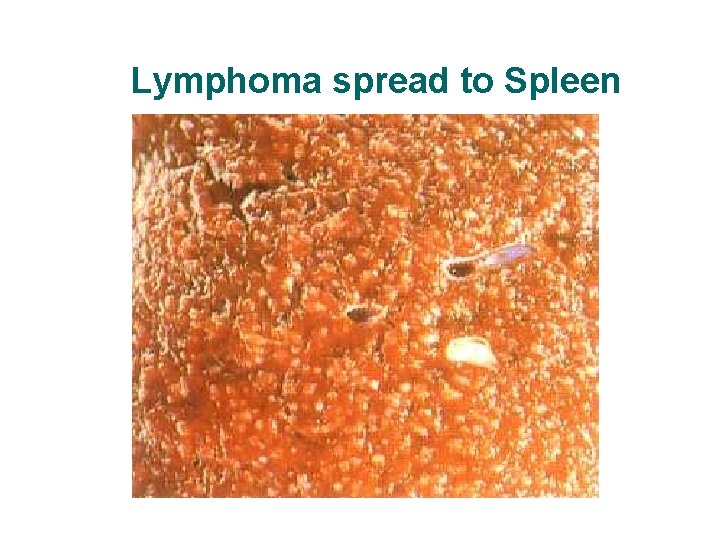
Splenic Involvement l l The probability of splenic involvement increases with increasing spleen size The absence of splenomegaly does not exclude splenic involvement Upon gross examination of the spleen a grayish white nodule ranging from several millimeters to several centimeters is apparent with Hodgkin’s disease Liver involvement with Hodgkin’s disease rarely occurs in the absence of splenic disease 23
Classifications l Classic Hodgkin’s divisions – – Nodular Sclerosing Mixed Cellularity Lymphocyte rich Lymphocyte depleted 24
Nodular Sclerosing l l l >60% of cases Connective tissue RS cells Lacunar cells other cells 25
Mixed Cellularity l l 15 – 30% cases Mixed cells – – – – Lymphocytes Histocytes Eosinophils Plasma cells RS cells Variants +Necrosis 26
Lymphocyte rich l l l <5% cases Large numbers of Lymphocytes May suppress other cells RS cells Not to be confused with LP Hodgkin’s 27
Lymphocyte depleted l l l <1% cases Lymphocytes rare RS cells predominate 28
Symptoms & Presentation l l l l Swollen, painful lymph nodes Fatigue, etc. Generalized iching Appetite, weight loss Neck %/or back pain Hair loss Night sweats 29
Hodgkin’s Disease l Symptoms such as fever, night sweats, weight loss and pruritus are indicative of widespread involvement and are unfavorable prognostic signs – l A typical fever pattern is a high-temperature alternating for a few days with an afebrile period Many patients have a mild normochromic, normocytic anemia – – 1/3 have a leukocytosis due to a neutrophil increase Eosinophilia is frequently present 30
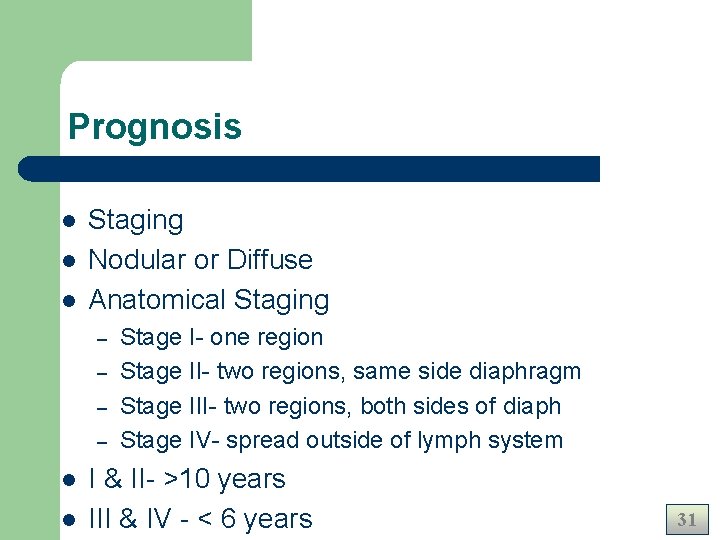
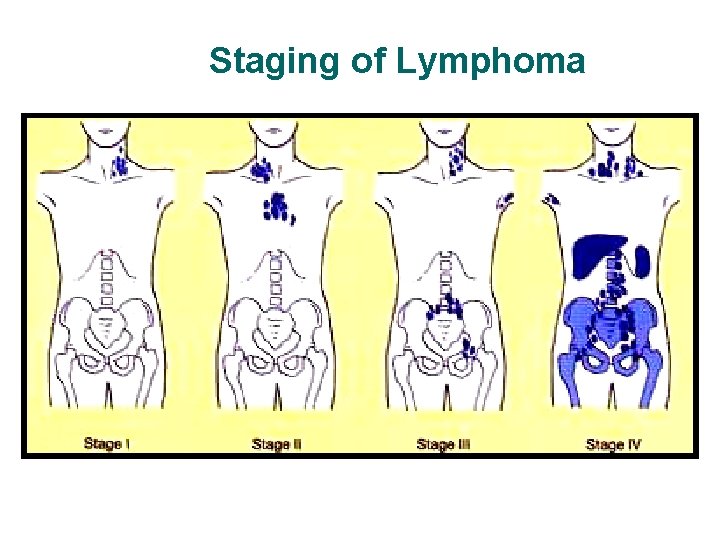
Prognosis l l l Staging Nodular or Diffuse Anatomical Staging – – l l Stage I- one region Stage II- two regions, same side diaphragm Stage III- two regions, both sides of diaph Stage IV- spread outside of lymph system I & II- >10 years III & IV - < 6 years 31
Current Treatment of Hodgkin’s Disease l l l Integrates radiation therapy and combination chemotherapy to achieve the maximum potential for cure Untreated Hodgkin’s has a five-year survival rate of 5% The Stanford experience-patients at all stages have survival rate of 86% – Patients in stage IV have a generally poor prognosis 32
Non-Hodgkins Lymphoma (NHL)
NON- Hodgkin’s Lymphoma l l l Absence of Reed-Sternberg Cells May result from damage to DNA that controls growth of cells in immune system Increased incidence in immunodeficiency 34
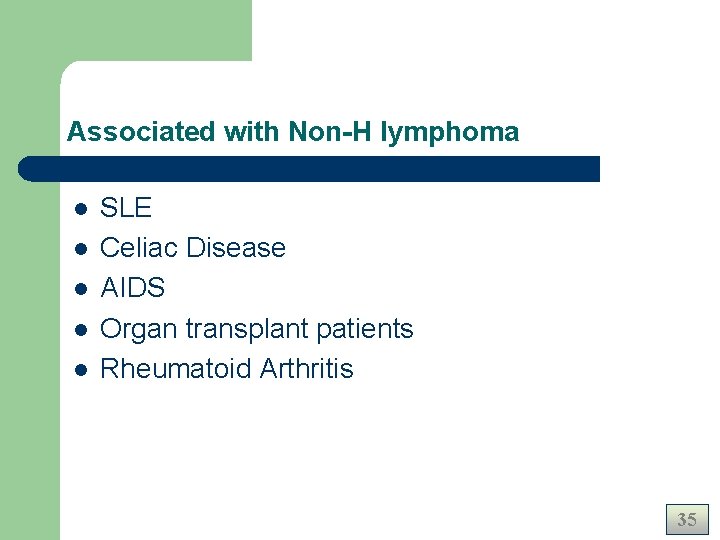
Associated with Non-H lymphoma l l l SLE Celiac Disease AIDS Organ transplant patients Rheumatoid Arthritis 35
Causes and Risk Factors l The Exact causes are still unknown – Higher risk for individuals who: l l Exposed to chemicals such as pesticides or solvents Infected w/ Epstein-Barr Virus Family history of NHL (although no hereditary pattern has been established) Infected w/ Human Immunodeficiency Virus (HIV) 36
Classifications l l l Based on cell type and location(s) Non symptomatic -> Aggressive – Worst prognosis < 1 year 37
Non-Hodgkin’s Lymphoma (NHL) l l A diverse group of primary malignancies of lymphoreticular tissue The clinical course and natural history is more variable than Hodgkin’s disease The pattern of spread is irregular and more patients have leukemic features Current histologic classifications utilize electron microscopic morphology, histochemical studies and selected cell surface antigens. – For our purposes NHL is classified according to nodular (favorable) and diffuse (unfavorable) types 38
NHL l l l In contrast to Hodgkin’s disease, about two-thirds of patients initially have asymptomatic lymphadenopathy In addition to peripheral and mediastinal lymphadenopathy NHL is commonly found initially as an abdominal mass or as hepatic or splenic enlargement Fever, weight loss and night sweats are frequently present The median age at diagnosis is 50 No sex preference is noted 39
NHL l l Patients below 35 or over 65 are more likely to have diffuse histology As with Hodgkin’s, chemotherapy and / or radiation therapy are the primary forms of treatment Staging laparotomy is seldom required Significant therapeutic benefit can be achieved by splenectomy in 80 -90 % of patients with advanced lymphomas (including Hodgkin’s disease) 40
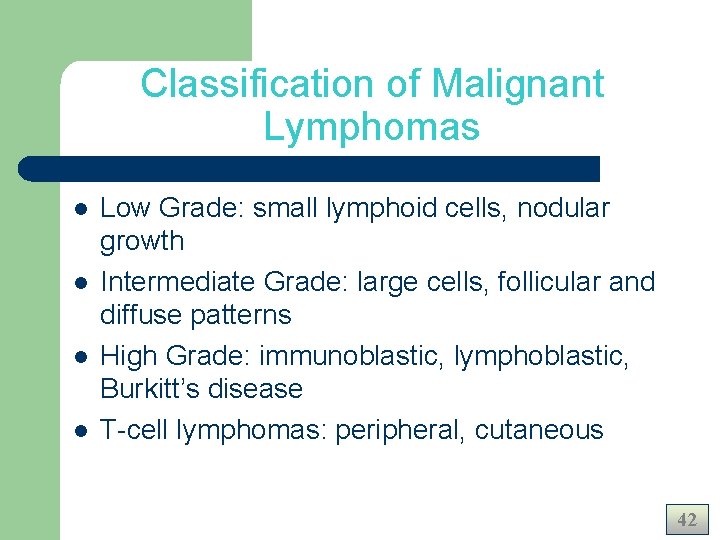
Classification l Usually classified by how the cells look under a microscope and how quickly they grow and spread – Aggressive lymphomas (high-grade lymphomas) – Indolent Lymphomas (low-grade lymphomas) 41
Classification of Malignant Lymphomas l l Low Grade: small lymphoid cells, nodular growth Intermediate Grade: large cells, follicular and diffuse patterns High Grade: immunoblastic, lymphoblastic, Burkitt’s disease T-cell lymphomas: peripheral, cutaneous 42
Non-Hodgkin’s Lymphoma Staging l l Stage is the term used to describe the extent of tumor that has spread through the body( I and II are localized where as III and IV are advanced. Each stage is then divided into categories A, B, and E – – – A: No systemic symptoms B: Systemic Symptoms such as fever, night sweats and weight loss E: Spreading of disease from lymph node to another organ 43
Staging 44
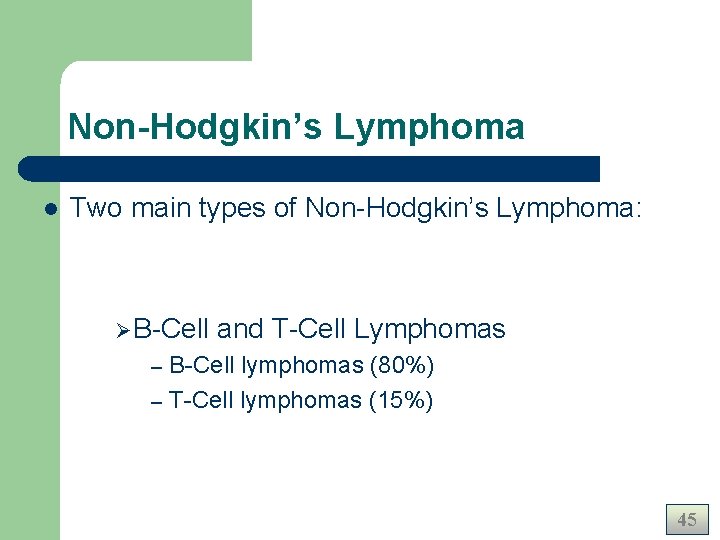
Non-Hodgkin’s Lymphoma l Two main types of Non-Hodgkin’s Lymphoma: Ø B-Cell and T-Cell Lymphomas B-Cell lymphomas (80%) – T-Cell lymphomas (15%) – 45
NHL – Classification: l l l According to cell type – T cell, B cell, Histiocytic & Misc. NHL According to Clinical grade – Low grade, Intermediate & High grade NHL. Histopathological – Diffuse/Follicular NHL, – Small, Intermediate & Large cell NHL Ex: Lennert’s lymphoma is a low grade Tcell NHL. Burkitt’s lymphoma is a high grade B cell NHL 46
Kiel Classification of NHL l B Cell NHL: – – l T Cell NHL: – – l Low Grade: lymphocytic, plasmacytic, centrocytic, mixed centrocytic centroblastic. High Grade: Centroblastic, Immunoblastic, Burkitts, lymphoblastic. Low Grade: lymphocytic, mycosis, Lennerts High Grade: immunoblastic, lymphoblastic etc. Rare types: 47
NCI – Working Formulation l Low-grade NHL: – – l Intermediate-grade NHL: – – l Follicular large cell Diffuse small cleaved High-grade NHL: – – l Small lymphocytic Follicular small cleaved Immunoblastic Lymphoblastic Miscellaneous: Histiocytic, Mycosis etc. 48
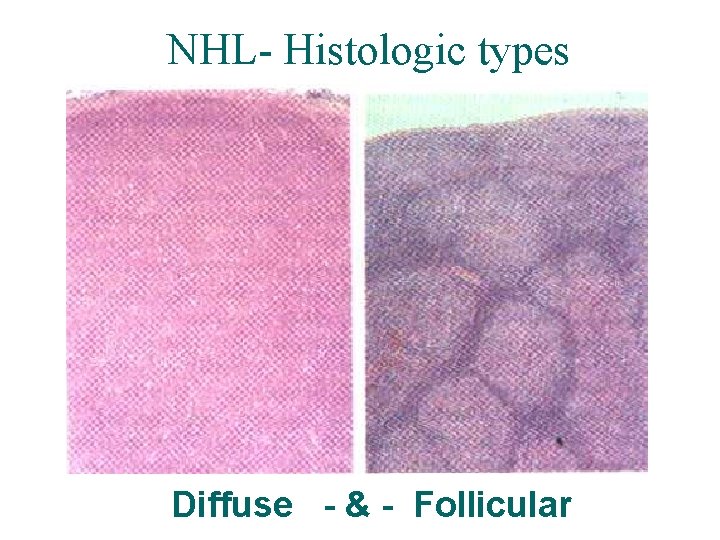
NHL- Histologic types Diffuse - & - Follicular
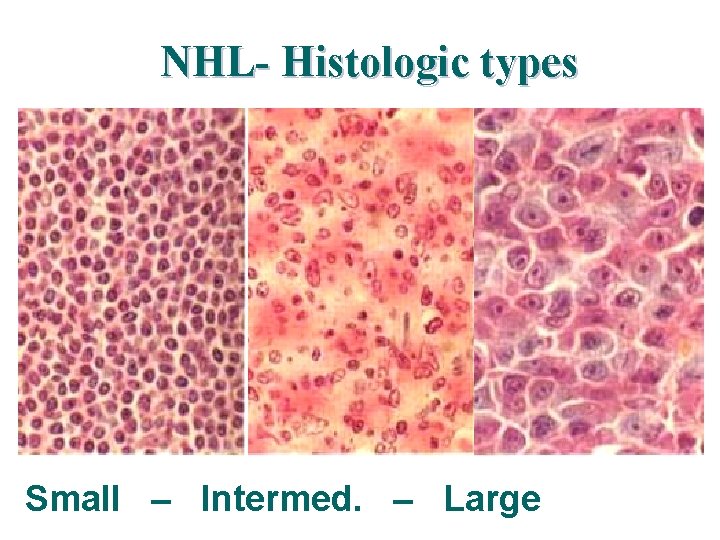
NHL- Histologic types Small – Intermed. – Large
Staging of Lymphoma
Lymphoma spread to Spleen
Lymphoma spread to Spleen
Laboratory Diagnosis:
Laboratory Diagnosis: l Haematological: – – – l Bone marrow: – – l Normocytic normochromic anemia, High ESR* Leucocytosis, Eosinophilia, lymphopenia Leukoerythroblastic picture - BM infiltration* Normal, or late involvement. Trephine biopsy- diffuse or follicular infiltration Biochemical: – – – High serum LDH – poor prognosis Hypercalcemia, Alkaline phosphatase, Uric acid. Serum transaminases & Bilirubin – Liver 55
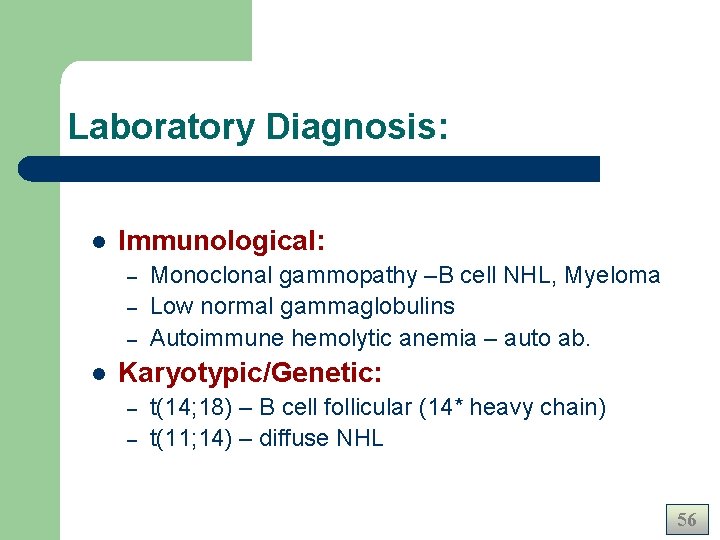
Laboratory Diagnosis: l Immunological: – – – l Monoclonal gammopathy –B cell NHL, Myeloma Low normal gammaglobulins Autoimmune hemolytic anemia – auto ab. Karyotypic/Genetic: – – t(14; 18) – B cell follicular (14* heavy chain) t(11; 14) – diffuse NHL 56
Diagnosis l l l X-Rays CT scans Magnetic Resonance Imaging (MRI) Biopsy Lymphangiogram – Pictures of the lymphatic system taken w/ x-ray after a special dye is injected to illuminate lymph nodes and vessels 57
Treatment l Non-Hodgkin’s Lymphoma is usually treated by a team of physicians including hematologists, medical oncologists and a radiation oncologist. l In some cases such as for Indolent lymphomas, the Doctor may wait to start treatment until the patient starts showing symptoms, known as “watchful waiting” 58
Treatment Options l l l Chemotherapy Radiation Bone Marrow Transplantation Surgery Bortezomib (Velcade) Immunotherapy l Using the bodies own immune system combined with material made in a lab. 59
Treatment: l Staging & grading l Chemotherapy – CHOP, MCHOP. . Radiotherapy – Local/regional/TBI Combination – Intensive Chemo/Radio-TBI with Autologous bone marrow rescue. l l 60
Survival Rates l Survival Rates vary widely by cell type and staging. – 1 Year Survival Rate: 77% – 5 Year Survival Rate: 56% – 10 Year Survival Rate: 42% 61
Burkitt’s Lymphoma
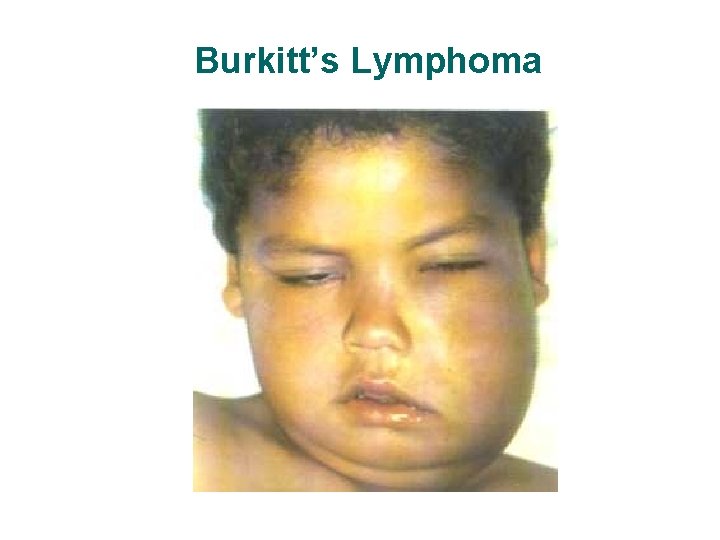
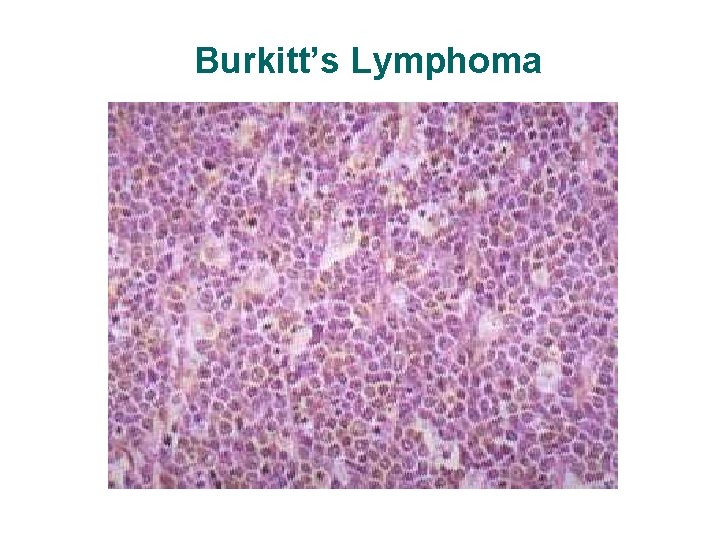
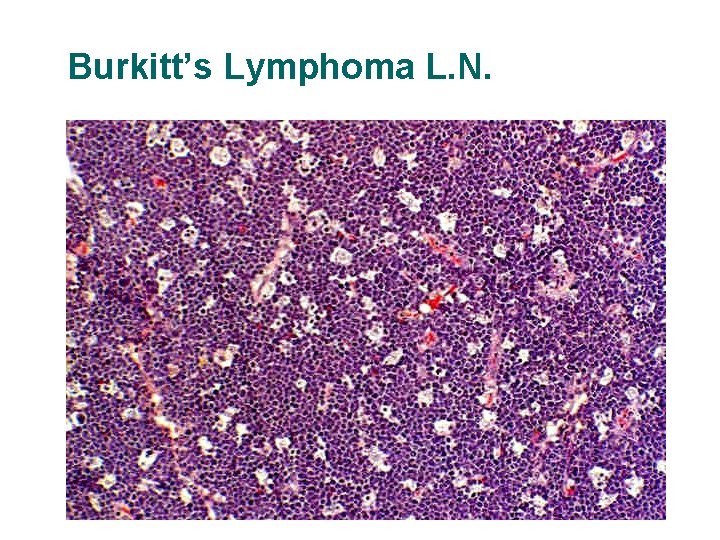
Burkitt’s Lymphoma l l l Unusual, B-Lymphoblastic high grade Young african children, jaw bones Isolated histiocytes, starry sky pattern EBV infection related. t(8; 14) Chemotherapy – good response But relapse usual, 30% cure. 63
Burkitt’s Lymphoma
Burkitt’s Lymphoma L. N.
Lymphoma Summary: l l l l Solid malignancy of lymphoid tissue. Lymphadenopathy, fever, anemia. Hodgkins & Non-Hodgkins (NHL) types. RS-Cells, eosinophilia – Hodgkins. Low-grade, Intermediate & High grade. Blood, Biochemical, BM, LN - biopsy Immunological & Genetic tests. Chemotherapy, Radiotherapy, combination 66