
Genital Infections James Huffman PGY1 11 2 2006




























- Slides: 46
Genital Infections James Huffman, PGY-1 11. 2. 2006
Objectives o Focus on approach and resources o Discuss work-up and diagnostic studies o Review treatments o Focus on Canadian 2006* STD Guidelines o (PID/HIV/HSV/HPV/sexual assault/urologic diseases not covered) *http: //www. phac-aspc. gc. ca/std-mts/sti_2006/pdf_2006_e. html
Resources o Calgary STD Clinic n n n www. calgaryhealthregion. ca/hecomm/std. htm 403 -944 -7575 #404 - 906 - 8 th Avenue SW o Canadian 2006 STD Guidelines n Preview available on Public Health Agency of Canada’s website (link from STD clinic)
Genital Infections in the ED Disease Gonorrhea Chlamydia Syphilis Chancroid Gardnerella Genital herpes Genital condylomata Trichomonas Scabies Implicated organism Neisseria gonorrhea Chlamydia trachomatis Treponema pallidum Hemophilus Ducreyi Gardnerella vaginalis Herpes simplex virus Human papilloma virus Trichomonas vaginalis Sarcoptes scabiei
Case: o 18♂ with 3 day history of burning on urination and urethral discharge. o 3 sexual partners (all within the last year). Most recently a one night stand 1/52 ago – worried he “caught something” from her. No GP. o What now?
Taking a sexual history: o Explain rationale and ask permission n Current and prev symptoms (duration) n Prior Hx of STI’s n Recent sexual contacts n Use of contraceptives n Types of sexual practices n Need menstrual Hx in women n Don’t forget about abuse!!!
Physical exam o Must do it…might as well do it well. n n Feel for nodes, retract foreskin, palpate scrotum, skin lesions, look in folds, inspect perianal region, speculum exam +/- bimanual Have patient milk urethra Include oropharyngeal exam Don’t forget about joints
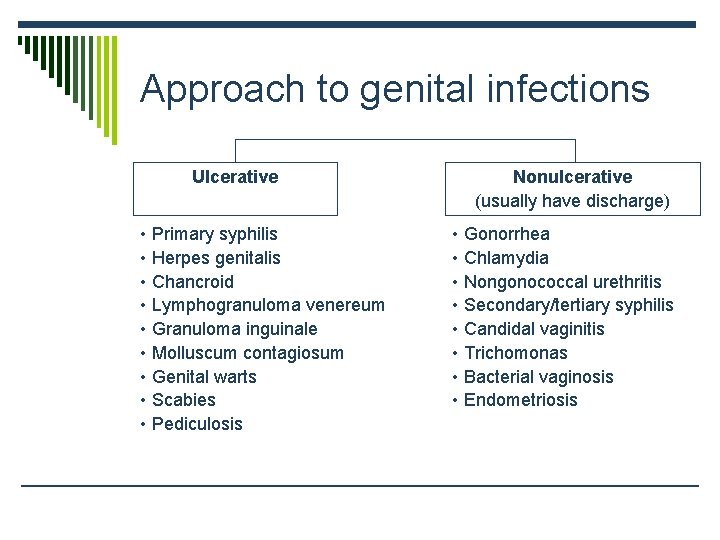
Approach to genital infections Ulcerative • Primary syphilis • Herpes genitalis • Chancroid • Lymphogranuloma venereum • Granuloma inguinale • Molluscum contagiosum • Genital warts • Scabies • Pediculosis Nonulcerative (usually have discharge) • Gonorrhea • Chlamydia • Nongonococcal urethritis • Secondary/tertiary syphilis • Candidal vaginitis • Trichomonas • Bacterial vaginosis • Endometriosis
Don’t forget about… Non-infectious causes of genital discomfort: n n n Allergic or chemical vaginitis Atrophic vaginitis Pediculosis pubis Vaginal foreign bodies Latex allergy
Any Guesses? How much was Marilyn Monroe paid for her nude calendar photos? n Nothing n $50. 00 n $550. 00 n $1, 750. 00
Diagnostic tests to consider: o Urinalysis o Urethral C&S/Gram stain o Cervical/Vaginal C&S & Gram Stain (female) o ELISA/DNA probe testing for Chlamydia n (nucleic acid amplification urine test in Calgary) o +/- HIV, HEP B&C, Syphilis, HSV, and HPV o +/- pharyngeal/rectal C&S
Urethral swabs: o Unnecessary if adequate discharge present with milking of the urethra (ie discharge C&S adequate for gonorrhea but not for chlamydia) and urine nucleic acid amplification techniques available (PCR/LCR) – i. e. Calgary
Urethral swabs: o Ideally patient should not have voided x 2 hrs o Moisten tip with water o Should go in slowly 3 -4 cm (males) or 12 cm (females) rotate slowly withdraw gently prepare smear innoculate culture medium/place in transport medium
Disorders with discharge: i. e. Urethritis o Tend not to have ulcerations or significant lymphadenopathy o Chlamydia and Gonorrhea most common o Also: non-gonococcal urethritis, trichomoniasis, BV, candidiasis and PID
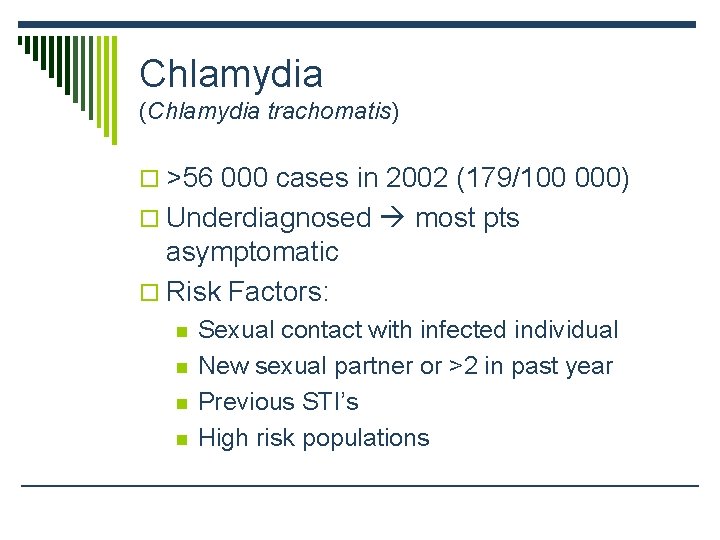
Chlamydia (Chlamydia trachomatis) o >56 000 cases in 2002 (179/100 000) o Underdiagnosed most pts asymptomatic o Risk Factors: n n Sexual contact with infected individual New sexual partner or >2 in past year Previous STI’s High risk populations
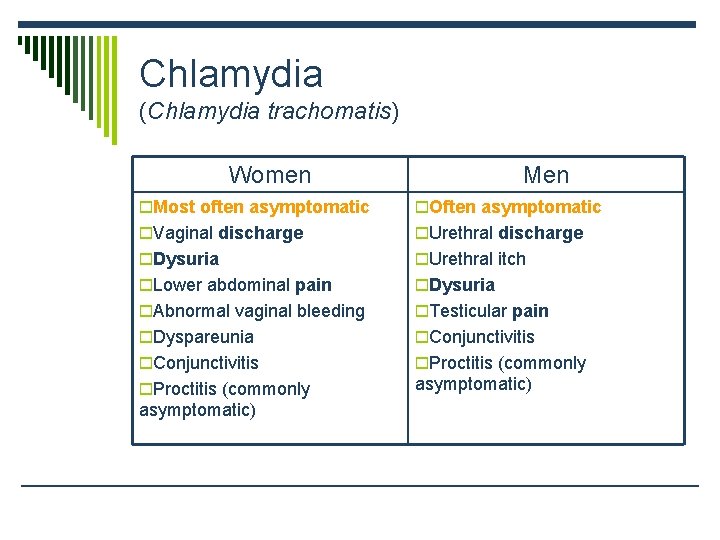
Chlamydia (Chlamydia trachomatis) Women Men o. Most often asymptomatic o. Often asymptomatic o. Vaginal discharge o. Urethral discharge o. Dysuria o. Urethral itch o. Lower abdominal pain o. Dysuria o. Abnormal vaginal bleeding o. Testicular pain o. Dyspareunia o. Conjunctivitis o. Proctitis (commonly asymptomatic)
Chlamydia (Chlamydia trachomatis) Bonus Points Name for the perihepatitus caused by C. trachomatis? Fitz-Hugh-Curtis syndrome
Chlamydia (Chlamydia trachomatis) Major Sequelae: 1. Females o o o PID Ectopic Infertility Chronic pelvic pain Reiter Syndrome 2. Males o o Epididymo-orchitis Reiter Syndrome
Chlamydia (Chlamydia trachomatis) Diagnosis: o Nucleic Acid Amplification Tests (NAATs) n Can be performed on swabs (endocervical and urethral) and urine n Best as it is hard to culture an intracellular pathogen n Better if patient hasn’t voided x 2 hrs n Collect only the initial 10 -15 m. L of urine n 98% sensitive and 100% specific (better than culture) o Culture in sexual abuse cases
Chlamydia (Chlamydia trachomatis) Treatment indicated when: o Positive chlamydia test o Diagnosis of a syndrome compatible with a chlamydial infection o Diagnosis of chlamydial infection in a sexual partner o Diagnosis of N gonorrhoeae is made
Chlamydia (Chlamydia trachomatis) Treatment (non-pregnant, non-lactating adults) o Doxycycline 100 mg PO bid x 7 days OR o Azithromycin 1 g PO as a single dose Confirmatory testing not routinely recommended unless pregnant
Any Guesses? The first vibrators were invented in ______ as treatment for what was known then as hysteria. o 1755 o 1869 o 1904 o 1946
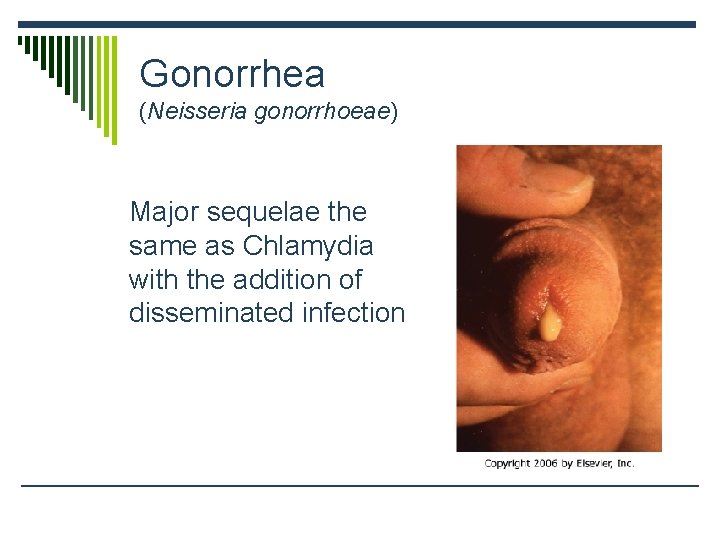
Gonorrhea (Neisseria gonorrhoeae) o 127 cases/100 000 o Penicillin-resistant organisms >1% nationally o HIV transmission is enhanced with concomitant Gonorrhea infection o Risk factors similar to those for Chlamydia o 1 -14 d incubation period o Assume co-infection with Chlamydia
Gonorrhea (Neisseria gonorrhoeae) Females • Cervicitis • PID • Urethritis • Perihepatitis • Bartholinitis Males • Urethritis • Epididymitis Both • Pharyngitis • Conjunctivitis • Proctitis • Disseminated Gonococcal infection: arthritis dermatitis endocarditis meningitis
Gonorrhea (Neisseria gonorrhoeae) Major sequelae the same as Chlamydia with the addition of disseminated infection
Gonorrhea (Neisseria gonorrhoeae) Diagnosis: o Culture is the preferred method (may be negative in first 48 h) o NAATs (avail but do not provide sensitivities) o Urethral gram stain with intracellular diplococci generally diagnostic o All sites aside from urethra and cervix require culture or NAAT (no gram stain)
Gonorrhea (Neisseria gonorrhoeae) Management: Test results available Gram Stain • Treat for gonococcal and chlamydial infection if Gm neg intracellular diplococci observed • Gram-negative diplococci outside PMNs must be confirmed by culture • PMNs without diplococci does not indicate or exclude gonococcal infection Culture NAAT • Treat all positives
Gonorrhea (Neisseria gonorrhoeae) Management: Test results unavailable Mucopurulent discharge • Treat for N gonorrhoeae and Chlamydia trachomatis No discharge • Defer therapy until smear/culture/NAAT results OR • Treat for N gonorrhoeae and C trachomatis if follow up uncertain and history and symptoms suggestive, or if partner is infected
Gonorrhea (Neisseria gonorrhoeae) Treatment Urethral, endocervical, rectal and pharyngeal infection o Cefixime 400 mg PO single dose OR o Ciprofloxacin 500 mg PO single dose OR o Ofloxacin 400 mg PO single dose OR o Ceftriaxone 125 mg IM single dose Gonococcal ophthalmia/disseminated infection o Ceftriaxone 2 g/day IV/IM AND azithromycin/doxycycline o Consultation/Admission
Gonorrhea (Neisseria gonorrhoeae) o Follow up cultures for test of cure are indicated 4 -5 days after completion of therapy o NAATs are not recommended for test of cure
Nongonococcal Urethritis o Urethral discharge, dysuria or urethral pruritis o C. trachomatis implicated in many cases o All patients should be evaluated for both gonorrhea and chlamydia o If no cause is found, treatment is the same as indicated for chlamydia
Primary Prevention “When in doubt, pass out! It’ll keep you from getting ‘the HIV’”.
Disorders with Ulcers o Patients will refer to just about anything “down there” as a “sore” n Good history and physical exam are key o Attention to the characteristics of the lesion(s), presence of adenopathy and presence of systemic symptoms o Most common: Herpes, Syphilis, HIV
Syphilis (Treponema pallidum) o The “Great Imitator” – ability to infect any organ of the body o ~3. 4 cases/100 000 (nationally) o Current outbreak in Calgary o Primary mode of transmission is sexual contact (vaginal, oral, anal) o 1°, 2° and early latent phases are considered infectious
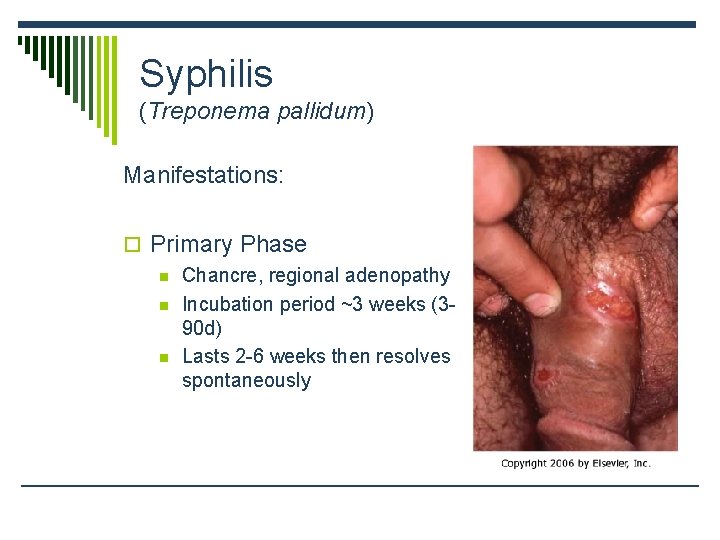
Syphilis (Treponema pallidum) Manifestations: o Primary Phase n Chancre, regional adenopathy n Incubation period ~3 weeks (390 d) n Lasts 2 -6 weeks then resolves spontaneously
Syphilis (Treponema pallidum) Manifestations: o Secondary Phase n Rash, fever, malaise, lymphadenopathy, mucous lesions, condylma lata, alopecia, meningitis, headaches, uveitis n Also resolves spontaneously
Syphilis (Treponema pallidum) Manifestations: o Latent Phase n n Asymptomatic – lab testing is only way to identify Early latent phase (infected <1 year prior) Late latent phase (all others) Lasts at least 3 -4 years
Syphilis (Treponema pallidum) Manifestations: o Tertiary Phase n n n CV Syphilis – Ao aneurysm, AR Neurosyphilis – meningitis, peripheral neuropathy (tabes dorsalis) Gumma – tissue destruction of any organ
Syphilis (Treponema pallidum) Diagnosis: o Darkfield examination – 80% sens. o Serologic testing n n n Non-treponemal (RPR) *may be nonreactive! Treponemal (MHA-TP, FTA-BS) Both types required for definitive diagnosis
Syphilis (Treponema pallidum) Treatment: o Primary and Secondary phases: n n Obtain material for Dark-field microscopy, test ulcers for HSV, serology (both NT and T tests) Referral to Calgary STD clinic o Latent Phase: n Serology and PE for tertiary findings n Referral to STD clinic
Syphilis (Treponema pallidum) Treatment: o Tertiary phase: n Serology and CSF p If CSF negative, treat as latent phase p If CSF positive, treat as neurosyphilis
Syphilis (Treponema pallidum) Treatment 1°, 2° and early latent phase: Benzathine penicillin G 2. 4 million units IM single dose *Only available from the STD clinic Penicillin Allergy: Doxycycline 100 mg PO bid x 14 days
Syphilis (Treponema pallidum) Treatment: Late latent phase & Non-neurosphyilis tertiary Benzathine penicillin G 2. 4 million units IM q 7 d x 3 doses Neurosyphilis Penicillin G 3 -4 million units IV q 4 h x 10 -14 days
Back to the case… o Hx: as before. Not using condoms. o PE: Mucopurulent urethral discharge and tender testicle (mostly around epididymis). Nil else. o Labs: Urine NAAT positive for Gonorrhea. o Patient treated for Gonorrhea and Chlamydia. STD clinic/Public Health notified.
Resources o Calgary STD Clinic n n n www. calgaryhealthregion. ca/hecomm/std. htm 403 -944 -7575 #404 - 906 - 8 th Avenue SW o Canadian 2006 STD Guidelines n Preview available on Public Health Agency of Canada’s website (link from STD clinic)
Questions?